Getting the Muscle Resection Right
The anterior compartment comes off easiest if you just bluntly dissect the periosteum away from the tibia before cutting. Most people make this harder than it needs to be by trying to preserve too much periosteum, which then causes adhesions later when the residual limb is bearing weight. The tibialis anterior, extensor hallucis longus, and extensor digitorum longus all get cleanly transected about 1 to 2 centimeters distal to where you plan to cut the bone. You want a clean edge, not a frayed one, because that frayed edge is what gets incorporated into scar tissue down the road. The peroneal muscles on the lateral side are where things usually start going sideways. I had a case recently where the fibular head was more prominent than expected due to the patient's body habitus, and the standard posterior flap length calculation ended up leaving the peroneal tendons dangerously exposed near the incision line. My workaround was to extend the distal incision by roughly 1.5 centimeters on the lateral side and deepen the subcutaneous dissection just enough to allow passive tension-free closure over those tendons. The patient healed without any breakdown issues. It is a small adjustment but it makes a real difference in the wound closure phase.
Below Knee Amputation Anatomy: What the Nerves Actually Do
The tibial nerve is the one that gives you trouble if you let it retract too far proximally into the popliteal fossa. You need to gently mobilize it and then transect it with a scalpel blade after applying gentle traction, letting it snap back into the soft tissue bed away from the bone cut surface. If you cauterize it aggressively with electrocautery, you send a thermal injury zone about 3 to 5 millimeters into the surrounding perineurium, and that is where neuroma formation likes to start. A clean cold cut is significantly better for long-term outcomes. The common peroneal nerve at the fibular neck is more of a technical challenge. It sits right against the bone here with very little soft tissue coverage. You have to be deliberate about how you isolate it. Pulling too hard will stretch the end and make it prone to irritation from the fibular stump. I prefer to free up a small segment, ligate the vessel running alongside it if there is active bleeding, and then let it retract naturally without any forceful retraction. The sural nerve follows a similar principle but is usually smaller and less problematic unless the patient has significant edema or prior surgical scarring in the calf region.
The Bone Work and Flap Design
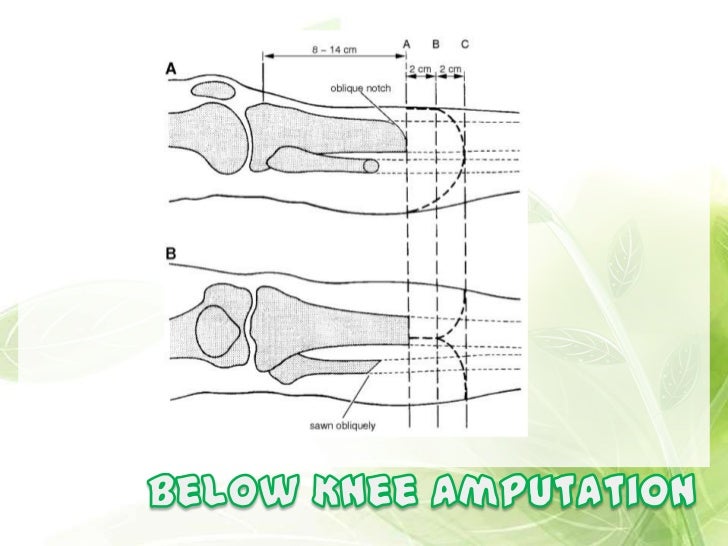
For the tibia, a standard below-knee amputation leaves a stump that is roughly 12 to 15 centimeters long measured from the knee joint line. This length provides enough lever arm for the residual limb to function effectively with a prosthetic below-knee device while still preserving adequate soft tissue coverage. Anything shorter than 10 centimeters starts to compromise the mechanical advantage of the remaining gastrocnemius and soleus muscles, and anything longer than 18 centimeters begins to behave more like a knee disarticulation in terms of prosthetic fitting challenges. The fibula should always be cut about 1 to 2 centimeters shorter than the tibia. I know this sounds counterintuitive to some people who think matching bone lengths is ideal, but leaving the fibula flush or longer creates a bony prominence on the lateral aspect of the stump that presses directly against the prosthetic socket during weight bearing. That pressure point is what causes skin breakdown and phantom pain complaints in follow-up visits. Bevel the fibular cut distally and medially so the cut surface faces downward and away from the soft tissue envelope. The posterior myocutaneous flap, sometimes called the Boyd flap when modified, relies on the fact that the posterior calf skin is generally more pliable and better vascularized than anterior skin. The flap should be designed to reach the anterior tibial wound edge with zero tension. If it does not reach without forcing it, you extend the posterior incision slightly or release the medial and lateral fascial septa a bit more. Forcing a posterior flap anteriorly under tension is one of the most common errors I see, and it directly correlates with wound dehiscence rates in the first two weeks postoperatively.
Get the Full Details

What Happens When You Ignore the Vascular Supply
The medial and lateral sural arteries run within the gastrocnemius and soleus muscle bellies respectively. During muscle transection, you will see bleeding from these vessels and from the nutrient arteries of the tibia and fibula. Some surgeons ligate every visible vessel individually. That takes time and adds ischemia to the muscle ends. My approach is to ligate the larger named vessels with absorbable suture and then use electrocautery on the smaller muscular branches. It is faster and the hemostasis is adequate for routine cases. Peripheral arterial disease changes everything about the decision-making process. In a patient with significant popliteal or tibial vessel disease, the posterior flap may not have reliable perfusion even if it looks healthy intraoperatively. I learned this the hard way with a diabetic patient who had a palpable dorsalis pedis pulse but a heavily calcified anterior tibial artery on preoperative angiography. The posterior flap looked fine, closed without tension, and then started breaking down on day four. The workaround in that situation would have been to take a longer amputation through the proximal third of the calf where the muscular branches from the posterior tibial artery provide more robust collateral flow. Length matters more than you think when vascular compromise is part of the equation.
Practical Considerations for Residual Limb Function
After hemostasis is achieved and the wound is closed, the residual limb should be shaped into a tapered conical form. The distal end needs to be broad enough to bear weight but narrow enough at the very tip to prevent a bulbous that catches on bedding or prosthetic components. Layered closure of the fascia, muscle, subcutaneous tissue, and skin in separate planes distributes tension across multiple tissue layers rather than concentrating it at the skin surface. Skin closure with staples or interrupted sutures comes last. A drainage suction bulb or closed suction drain placed through a separate stab incision posterior to the main wound helps prevent hematoma formation beneath the flaps. I usually leave the drain in place for 24 to 48 hours depending on output. A compressive dressings change protocol starting immediately post-op and transitioning to a rigid dressing within the first week is standard practice in most centers. Early controlled weight bearing through a temporary prosthesis can begin once the incision has adequately healed, usually around three to four weeks post-surgery.