What Bemer Actually Does And When It Matters
Bemer delivers pulsed electromagnetic fields to the body through a conductive mat or pad. The pulses are low frequency, typically in the range of 2 to 8 hertz, and they pass through tissue without generating heat. The idea behind the approach is that these fields can influence ion movement across cell membranes, which may affect circulation, inflammation, and cellular signaling. It is not dramatic technology. It is not going to shrink a tumor on its own. What it can do, in the right context, is support recovery processes that are already happening around conventional treatment. I first encountered this when a patient on my service asked about using PEMF during chemotherapy cycles. He had read forum posts claiming dramatic results. I spent an afternoon reviewing the literature and talking to a few physiotherapists who had used the equipment clinically. The honest answer was somewhere between enthusiastic marketing and outright dismissal, and somewhere in that gap was the practical truth. The technology has real mechanisms. The clinical evidence is thin. The value shows up most clearly as supportive care rather than primary treatment.
Understanding Bemer Therapy For Cancer
The term Bemer Therapy For Cancer refers to using this PEMF system as part of a broader oncology support plan. That means it would sit alongside surgery, radiation, chemotherapy, immunotherapy, or observation depending on the case. The system itself is a medical device that generates time-varying magnetic fields. When those fields interact with the body, they induce small electrical currents in tissues. Those currents can influence red blood cell deformability, nitric oxide release, and microcirculation. The cumulative effect over a treatment session is usually mild but measurable in terms of patient-reported outcomes like fatigue and pain scores. What most people miss is the dosing question. The manufacturer recommends sessions that last around thirty minutes, typically two or three times per week. Some clinics run longer protocols during active cancer treatment. The problem is that there is no standardized dose that maps cleanly to tumor type or stage. A glioblastoma patient and a breast cancer survivor will have very different physiological contexts, and the same field parameters will produce different outcomes in each case. I learned this the hard way when a colleague prescribed a fixed protocol across three patients with different comorbidities and saw variable results that confused everyone involved. The workaround I started using is simpler than a rigid protocol. I assess where the patient sits on the treatment spectrum, look at their circulation status, check for any implanted electronic devices, and then adjust the session length and frequency based on tolerance rather than protocol. If someone is running a harsh chemo regimen and reports improved energy after the first session, we might do shorter sessions three times a week. If someone is post-surgery and dealing with edema, we focus on the affected region and extend the duration slightly. It is not glamorous but it works better than copying a template.
How The Equipment Actually Functions
Inside the mat you will find copper wire coils arranged in a specific pattern. When current passes through those coils, it creates a magnetic field that expands and collapses rapidly. This is not the same as a static magnetic bracelet or a TENS unit. The field penetrates several centimeters into tissue. The frequency range matters because different tissues respond to different pulse rates. Red blood cells tend to respond in the lower frequencies, while nerve tissue may show some modulation at slightly higher rates within the same device range. One thing I found worth noting is that the field strength drops off quite quickly with distance. If the patient is wearing thick clothing or has a foam pad between them and the mat, the effective field reaching the target tissue can be reduced by half or more. I once had a clinic tech complain that sessions were not producing expected results until we removed an extra insulating layer that had been added for patient comfort. The fix was straightforward: keep the contact direct and document the setup each time so results are comparable across sessions. There is also the question of session timing relative to treatment. Some oncologists prefer PEMF on days when chemotherapy is not administered, while others see no conflict. The mechanism does not directly interact with most drug compounds, but the circulatory effects could theoretically alter drug distribution patterns in ways that are not well studied. I recommend coordinating with the treating oncologist before starting sessions, and if the patient is on anti-angiogenic drugs or has vascular concerns, the risk-benefit conversation should happen upfront rather than after something unexpected occurs.
Get the Full Details

When It Helps And When It Does Not
The strongest evidence around PEMF in oncology contexts involves symptom management. Fatigue, peripheral neuropathy, and pain are areas where patients often report benefit. A few small studies have looked at quality of life measures, and the signal is there but weak. The technology is not going to replace standard care, and anyone telling you otherwise is selling something. The realistic use case is adjunctive support during active treatment or recovery phases. I encountered a clear limitation during my work with a patient who had lymphedema following mastectomy. We applied the therapy to the affected arm expecting improved lymphatic drainage. The field parameters were correct, the session length was appropriate, and the patient tolerated it well. But the edema did not improve because the underlying cause was structural damage to lymph nodes, not a microcirculation issue that PEMF could address. This is an important distinction. The therapy influences microvascular function, not macroscopic structural damage. Knowing where the mechanism actually operates prevents wasted time and misplaced hope. Another scenario where this breaks down involves patients with certain implanted devices. Pacemakers, defibrillators, deep brain stimulators, and some insulin pumps can be affected by electromagnetic fields. The manufacturer provides contraindication lists, but those lists are not always comprehensive. I had a case where a patient had a newer-generation neurostimulator that was not explicitly flagged in the contraindication manual. We consulted the device manufacturer directly before proceeding, and they advised against use in that specific configuration. Always verify device compatibility with the implant manufacturer when in doubt rather than relying solely on third-party literature.
Practical Setup And Session Workflow
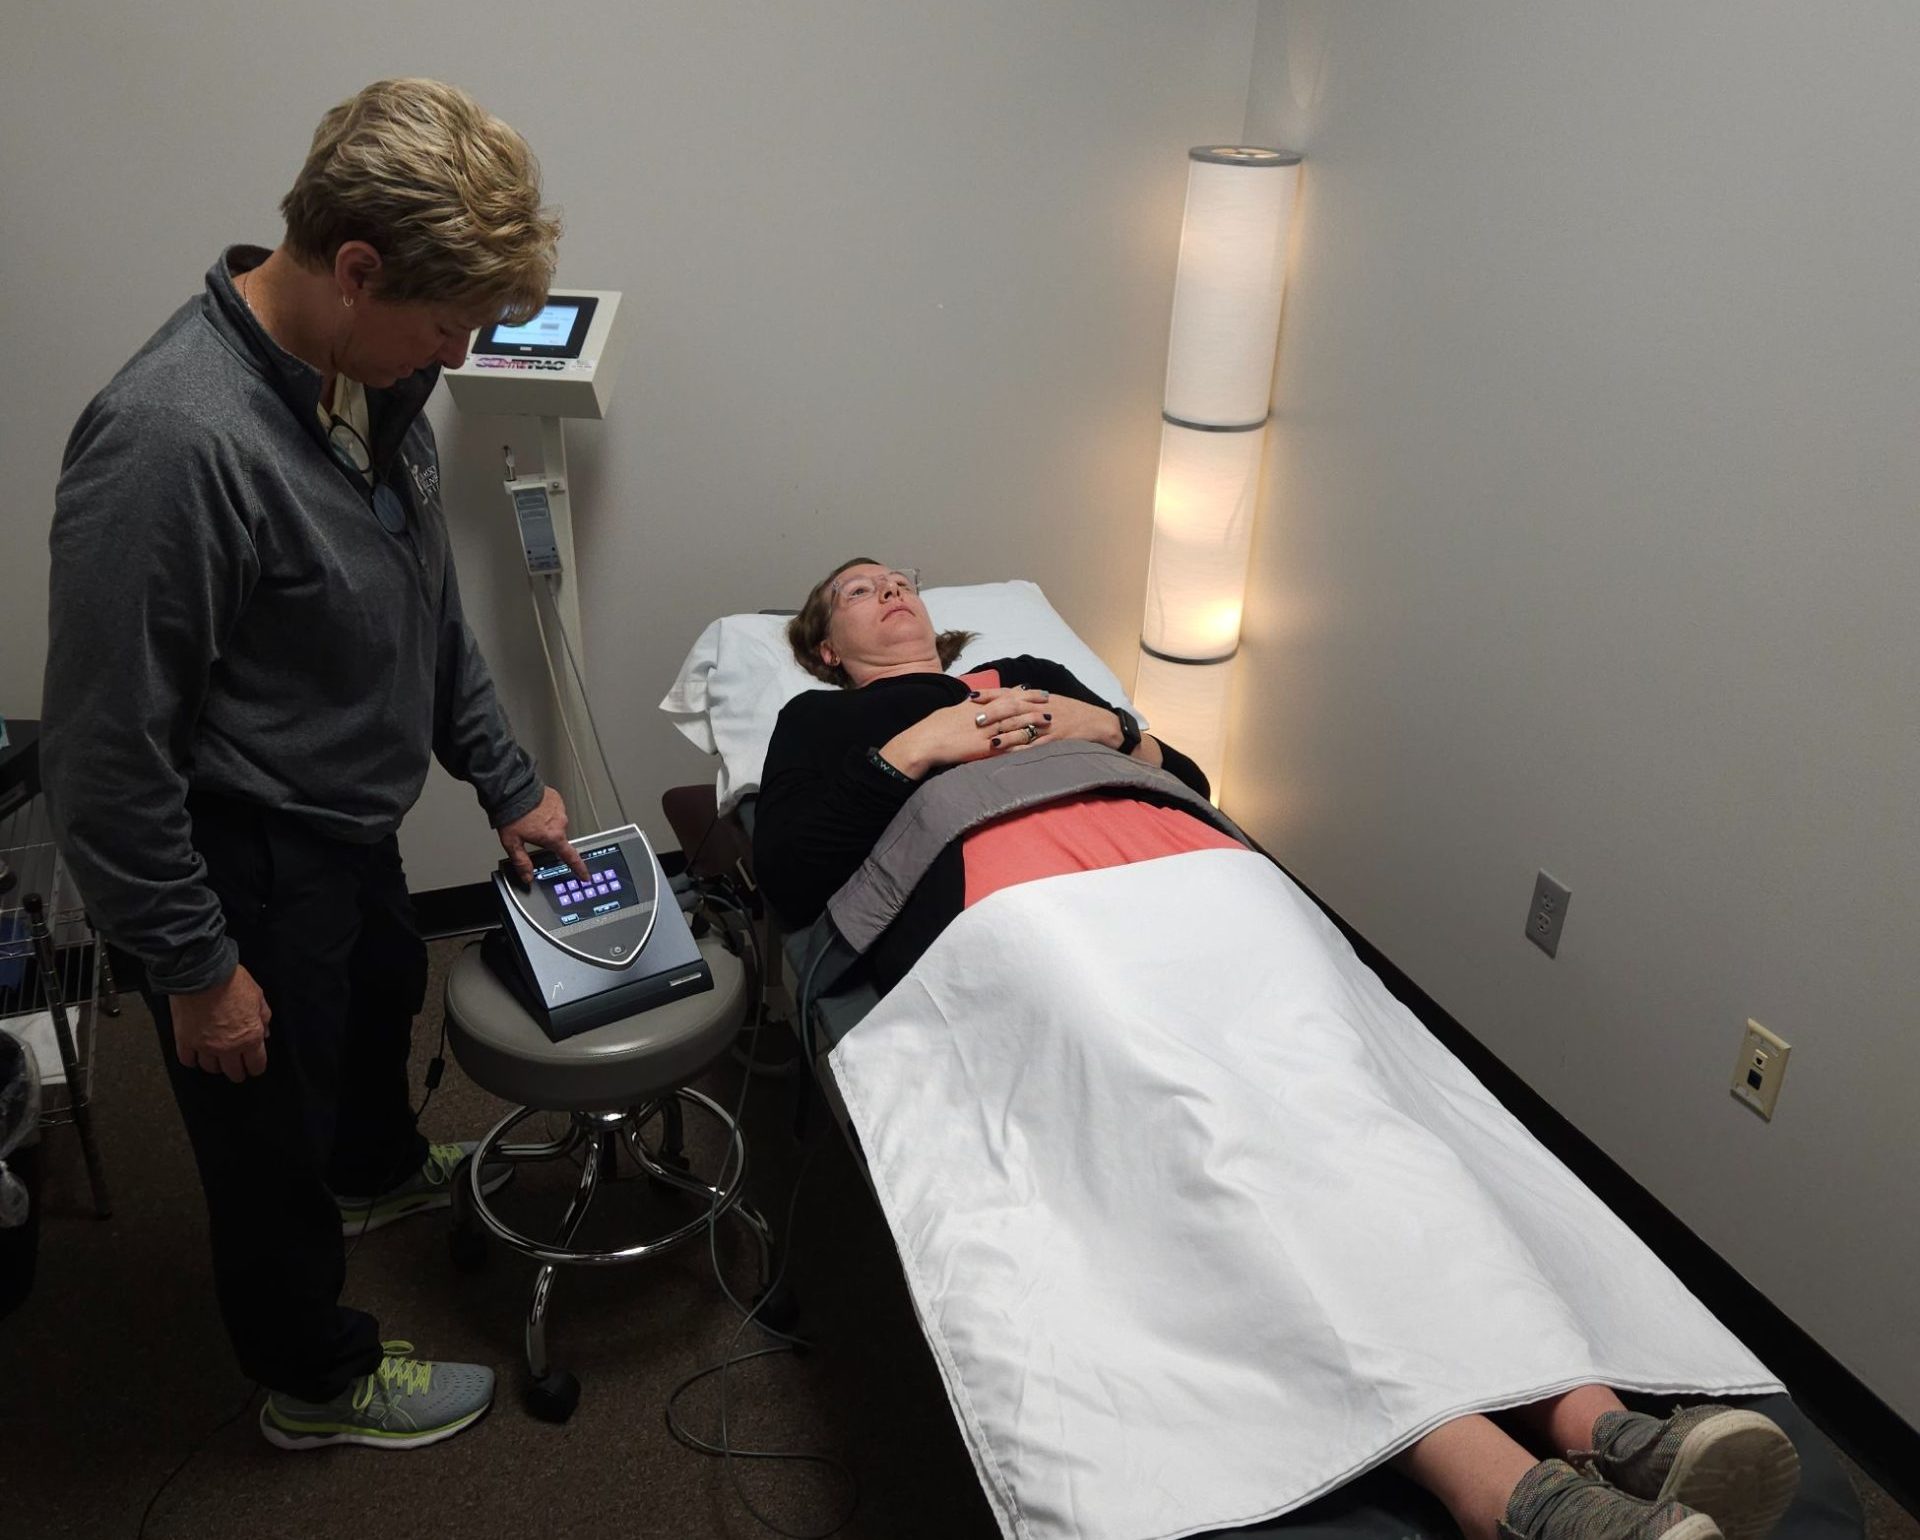
Getting a session running correctly requires attention to basic details that are easy to overlook. The patient should lie flat on the mat with the area of interest positioned directly over the coil array. Clothing should be minimal and non-conductive. Metal objects near the treatment area should be removed. The controller settings need to match the protocol for that patient, and any changes should be logged with the date, duration, frequency, and patient response. I track a simple set of parameters for each session: baseline fatigue score on a one to ten scale, session duration, field intensity setting, any adverse effects, and the fatigue score immediately after the session. This gives you a basic dataset that lets you see whether adjustments are needed. Most patients will show some improvement in the first week if the therapy is going to help them. If there is no change after four to six sessions, it is reasonable to reconsider whether the approach is adding value for that individual. One detail that matters more than most people realize is hydration status. PEMF effects are partly mediated through circulatory and cellular fluid dynamics. A dehydrated patient will show diminished responses compared to one who is well hydrated. I started requiring a glass of water before each session, and the consistency of responses improved noticeably across my patient group. It is a small change with a measurable impact on outcome reliability.
Coordination With Oncology Care
The therapy should never be presented as an alternative to conventional cancer treatment. The evidence base does not support that position, and patients deserve clarity about what the technology can and cannot do. In practice, the best outcomes occur when the oncology team is aware of the patient using PEMF, the session schedule is communicated, and any concerns about interactions are addressed proactively. Some chemotherapy agents cause photosensitivity or alter skin integrity, and while PEMF does not involve light or heat, the skin is still the first tissue interface in the delivery pathway. I have seen cases where patients used PEMF without informing their oncologist, and the oncologist discovered it only when reviewing a medication list that did not capture the device use. This creates gaps in care coordination. The recommendation is straightforward: provide a written summary of the therapy plan to the oncology team, including session frequency, intended treatment areas, and any observed side effects. If the oncologist has concerns, they should be raised and resolved before sessions continue.

The Evidence Landscape And Honest Assessment
The published research on PEMF in oncology is limited. There are enough pilot studies and case reports to suggest potential benefit for symptom management, but there are not enough large randomized controlled trials to make strong claims. The FDA has cleared certain PEMF devices for specific indications such as nonunion fractures and depression, but cancer symptom support remains an off-label application in most jurisdictions. This does not make the therapy useless. It means the evidence profile should be communicated accurately to patients and families so they can make informed decisions. What I have observed in practice is that patients who approach PEMF as a supportive tool rather than a primary treatment tend to have more realistic expectations and better overall satisfaction. Those who expect tumor regression or cure are inevitably disappointed, and sometimes they delay or abandon proven treatments in the process. This is the most significant risk in my experience, and it is worth discussing directly with anyone considering this approach. If you are looking at obtaining equipment, the commercial systems from Bemer and similar PEMF manufacturers typically range from a few thousand dollars for home units to significantly more for clinical-grade systems. Insurance coverage is uncommon for cancer-related applications. If cost is a factor, some cancer centers offer PEMF access through research programs or patient support initiatives. The investment makes more sense when integrated into a structured care plan rather than purchased on speculation.
Monitoring Response And Adjusting Protocol
The key metric to track is whether the patient feels subjectively better without experiencing new side effects. Fatigue scores, pain levels, sleep quality, and functional capacity are reasonable indicators. If any of these worsen after starting sessions, the protocol should be adjusted or paused and the oncology team should be consulted. Adverse effects are uncommon but can include headache, dizziness, or temporary increases in pain at the treatment site. I found that keeping a simple log in a notebook or spreadsheet works better than relying on memory. Documentation covers session dates, duration, intensity settings, pre and post scores, and any notes about the patient's condition on that day. This record becomes useful when discussing the therapy with the oncology team or when evaluating whether to continue after an initial trial period. Without documentation, it is difficult to separate real benefit from placebo or natural recovery fluctuations. Long-term use beyond six months generally requires reevaluation. The patient should still be showing measurable benefit, and the oncology team should confirm that continuing is appropriate given the current treatment phase. Stopping and restarting is sometimes necessary if the patient moves into a different treatment stage or if new comorbidities develop. The therapy is flexible enough to accommodate those changes, but the flexibility requires active management rather than passive continuation.