What Bemer Therapy Actually Is
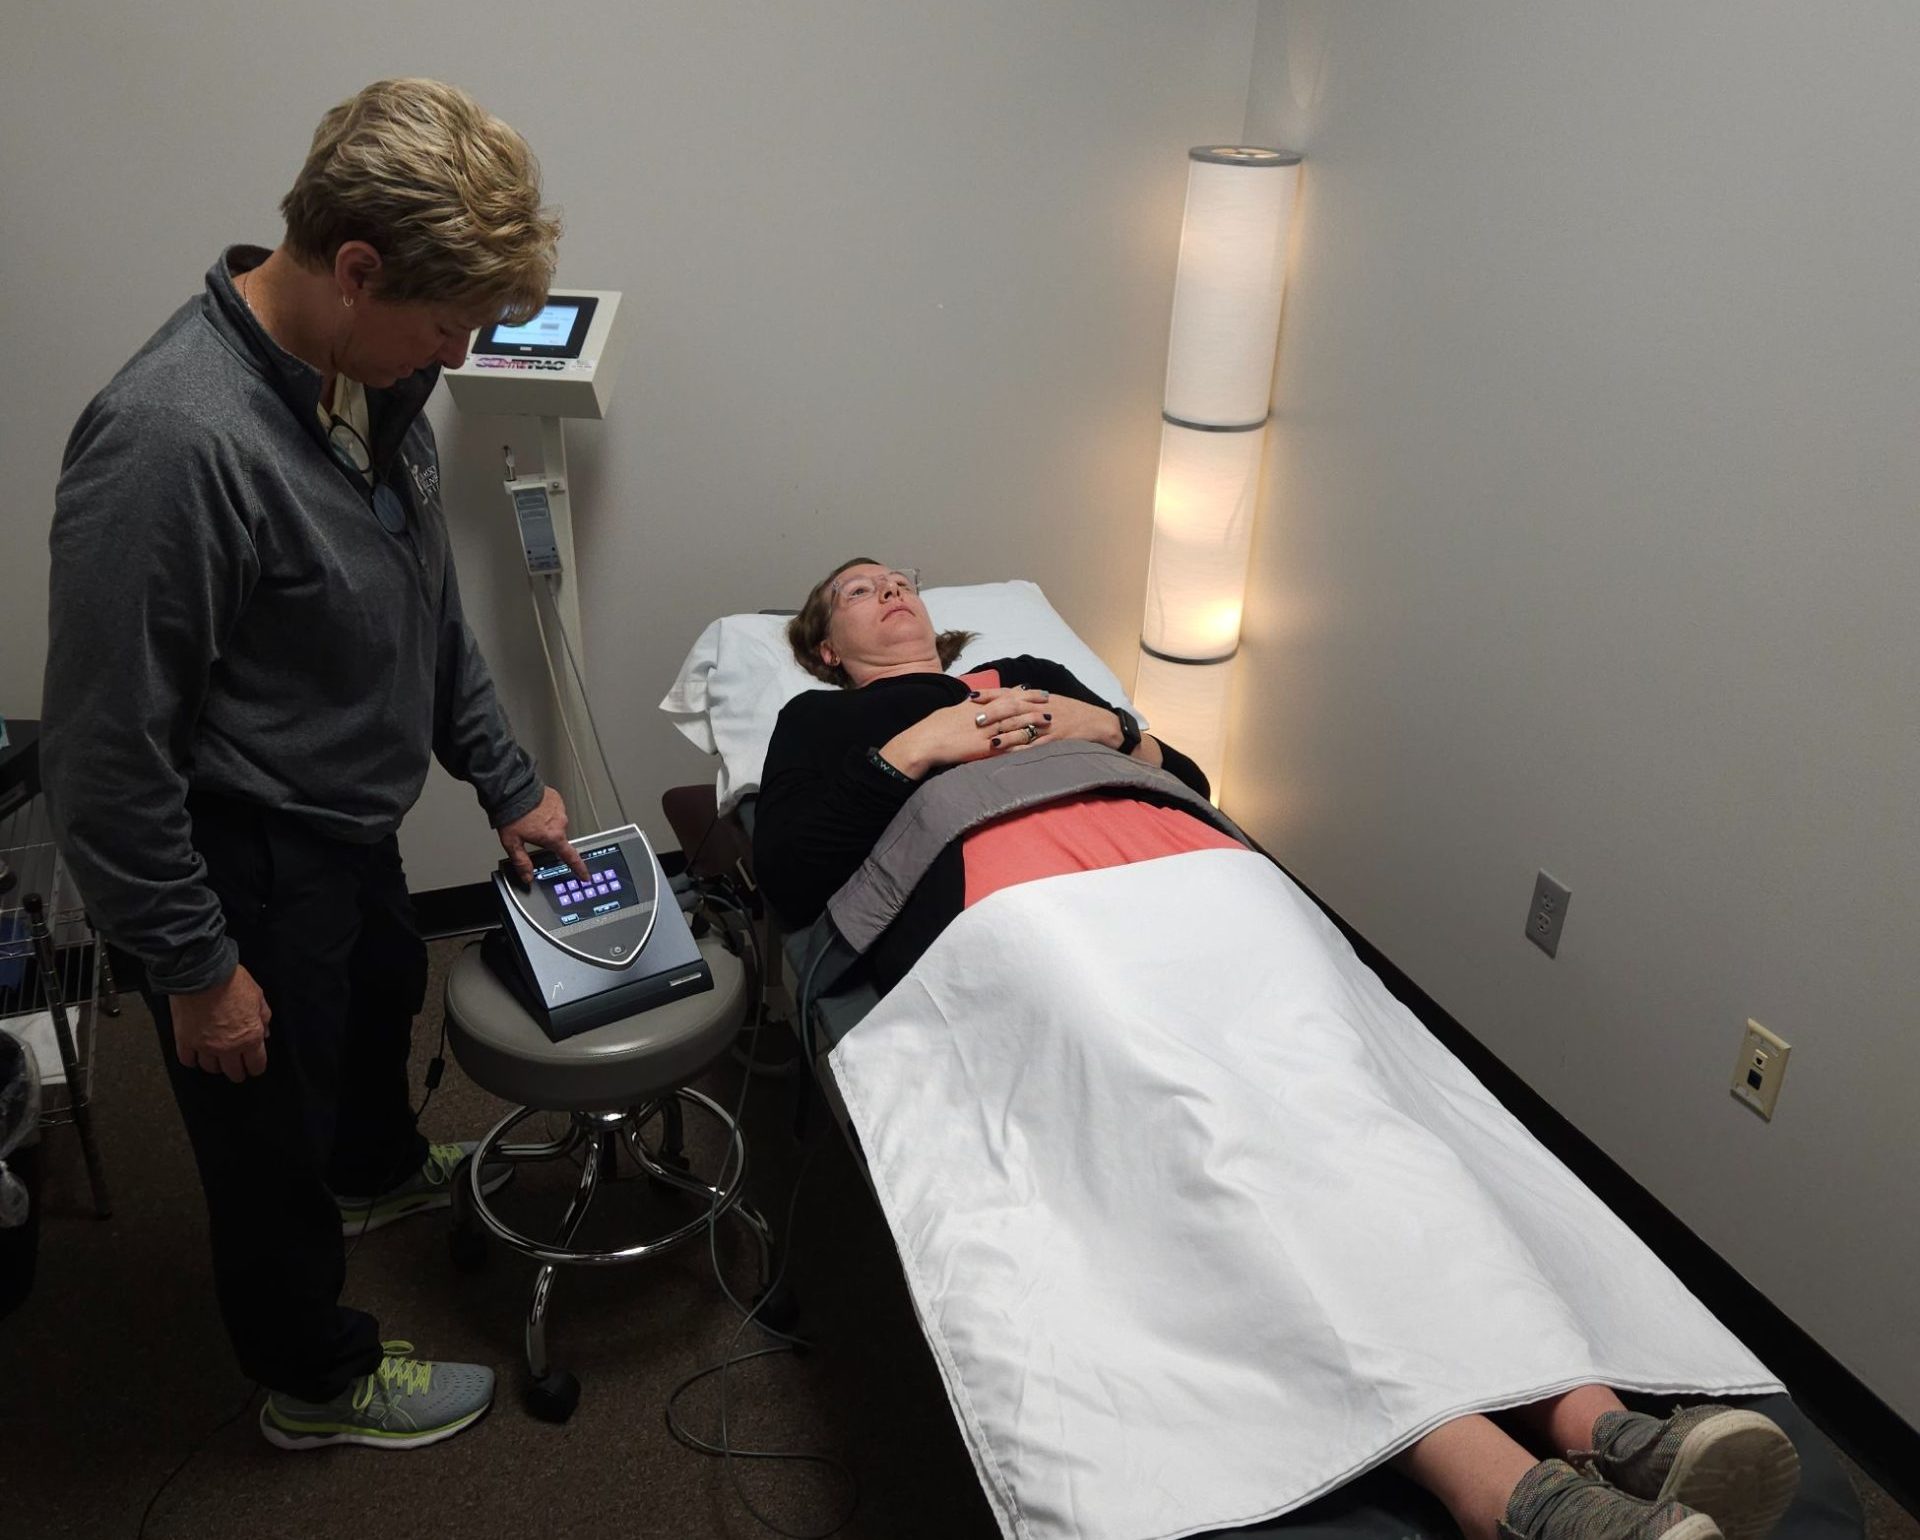
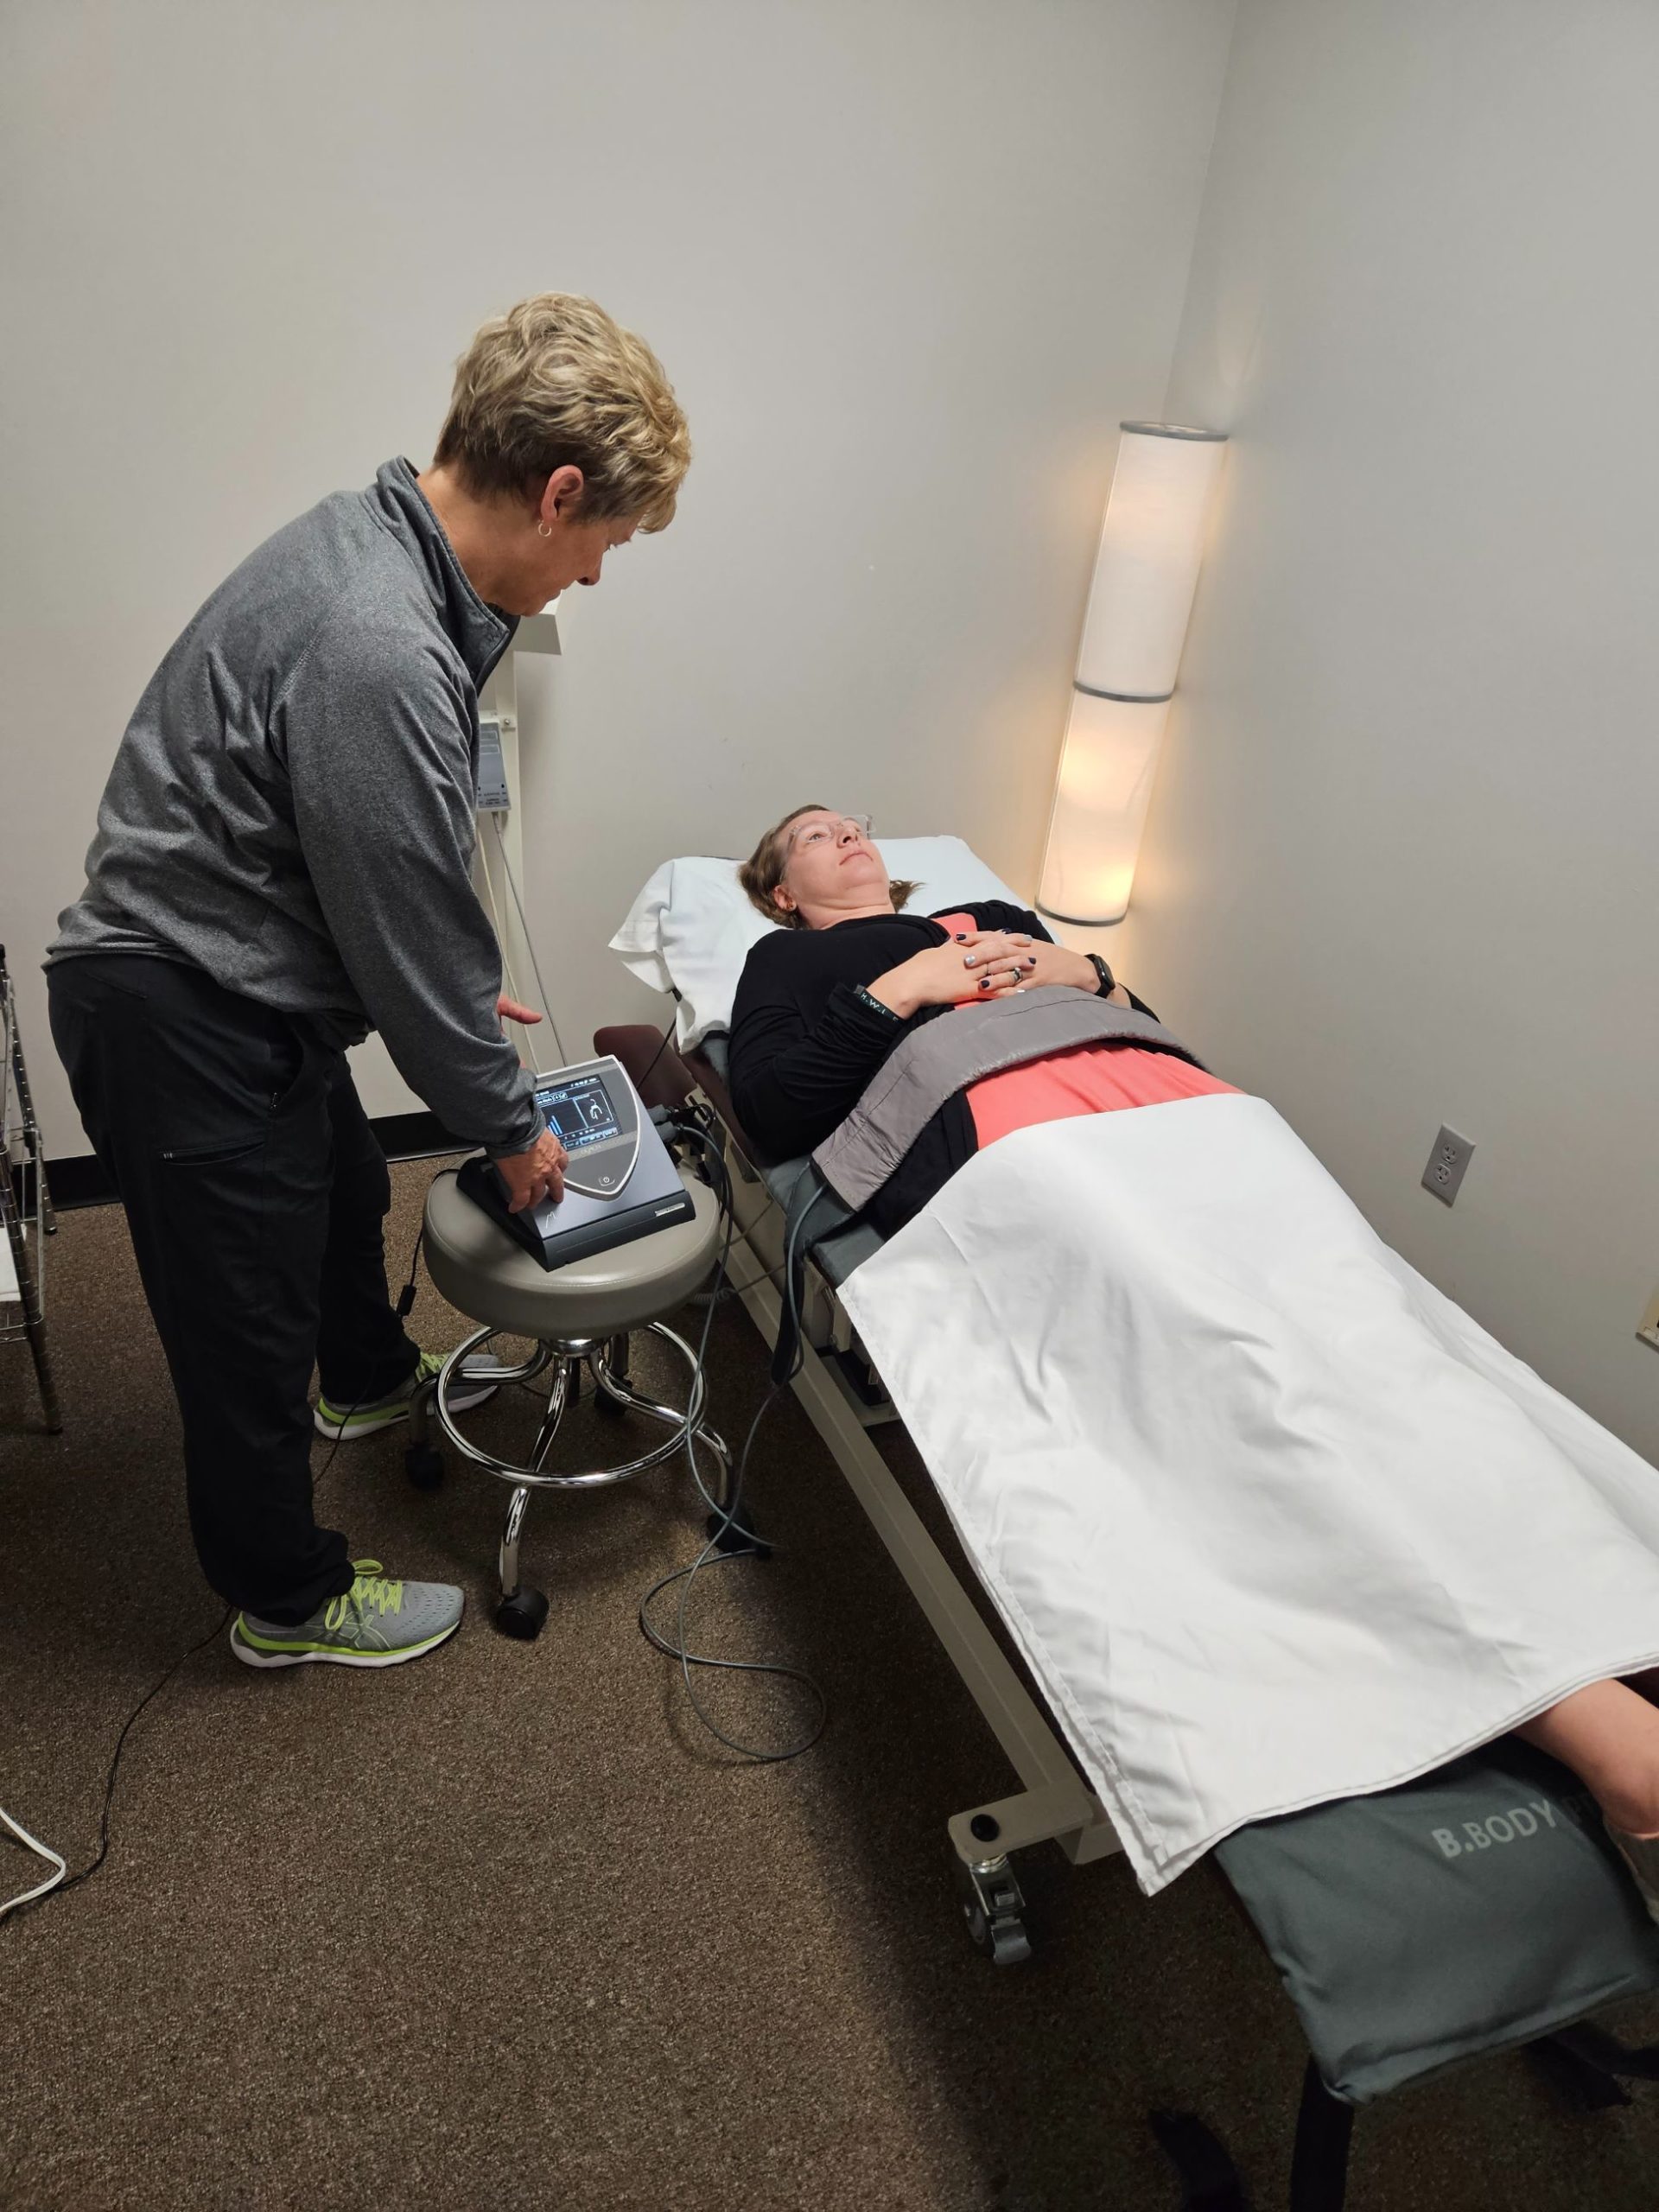
Bemer therapy uses pulsed electromagnetic field (PEMF) devices operating at very low frequencies, typically in the range of 6 to 16 hertz, applied through a mat or pad placed under or near the body. The device generates weak electromagnetic pulses that theoretically penetrate tissue and affect blood vessel smooth muscle cells, promoting vasodilation and microcirculation improvement. A standard session runs about 12 minutes. You lie still. That's essentially the entire procedure. The manufacturer, bEmes AG, positions the therapy as a general wellness and circulatory support modality. They've done some clinical work across various conditions, and that's where Parkinson's enters the conversation. A few small studies have explored whether improved microcirculation translates to symptom relief in movement disorders. The results are mixed. Not disastrous, but not convincing either. Most papers are small sample sizes, open-label, or funded by parties with a commercial interest in the outcome. Take those findings for what they're worth.
Understanding Bemer Therapy For Parkinsons Disease
The theoretical rationale goes like this: Parkinson's involves neurodegeneration of dopaminergic neurons in the substantia nigra, which reduces blood flow to affected brain regions. If Bemer improves microcirculation systemically, maybe it also improves cerebral perfusion, and maybe that slows progression or eases symptoms. The "maybe" appears a lot in this discussion. What I've seen in practice is that some patients report subjective improvements in tremor, rigidity, and sleep quality after a few weeks of consistent use. Others notice nothing. I've sat in clinics where a Parkinson's patient swore the sessions made their hands steadier. I've also sat in clinics where the same patient couldn't tell any difference and was spending money they couldn't afford on something with thin evidence. Both scenarios are real. The Parkinson's Foundation and major neurology guidelines do not currently list Bemer or PEMF as a recommended treatment. That matters. When mainstream organizations don't endorse something, it's usually because the evidence hasn't crossed the threshold, not because someone is hiding a breakthrough.
How the Treatment Works in Practice
A Bemer session involves placing the patient on a mat or positioning pads near the body. The device cycles through a series of pulse patterns over approximately 12 minutes. The pulses are sub-perceptual, meaning you generally can't feel them. Some people describe a mild warmth or tingling. Most feel nothing at all. Clinic-based protocols for Parkinson's typically run 2 to 3 sessions per week for several weeks, then taper to maintenance sessions once or twice weekly. Home units are available for purchase, which changes the cost dynamic significantly. A clinic session runs roughly 40 to 80 euros depending on location. A home unit costs between 2,000 and 4,000 euros upfront. I've seen both models used, and the compliance rate drops noticeably once patients go home. Parkinson's patients dealing with fatigue, cognitive fog, and the general exhaustion of managing a progressive disease are not reliably going to set up a mat twice a week for six months without reminders. The mechanism the company describes involves increased nitric oxide release from endothelial cells, improved calcium ion regulation in cell membranes, and enhanced ATP production within mitochondria. The cellular biology is plausible. Plausible doesn't equal proven, but it's more than pure speculation, which is where a lot of alternative therapies live.
Get the Full Details
What the Evidence Actually Shows
I want to be specific about the research because this is where most people get misinformed. A 2021 randomized controlled trial published in the Journal of Parkinson's Disease examined PEMF therapy in 30 idiopathic Parkinson's patients over eight weeks. The treatment group showed modest improvements in UPDRS motor scores compared to control. The effect size was small. Statistical significance was reached, but clinical significance is another question. An improvement of a few points on a motor scale doesn't meaningfully change daily function for most people. Another study looked at cerebral blood flow measurements using transcranial Doppler ultrasound before and after PEMF application. Some participants showed increased blood flow velocity in the middle cerebral artery. Again, plausible mechanism. Doesn't tell you whether neurodegeneration slowed or symptoms improved long-term. The larger problem is that none of these studies are large enough to draw firm conclusions. We're talking about dozens of patients, not hundreds or thousands. The Parkinson's community needs bigger, multi-center, double-blind trials before this moves from "interesting signal" to "established intervention."
Edge Cases and Practical Problems
Here's something I ran into that the literature doesn't cover: implantable medical devices. A patient came to me with a deep brain stimulator (DBS) in place, which is common for moderate-to-advanced Parkinson's. The Bemer device's electromagnetic pulses can potentially interfere with DBS programming or battery function. The manufacturer's contraindications list mentions cardiac pacemakers but is vague on DBS units. I had to contact the neurologist and the DBS manufacturer directly before we could proceed safely. The DBS team eventually gave conditional clearance, but only after the patient underwent a full system check before and after each session. This added 45 minutes to every clinic visit. If you have a DBS or any implanted electronic device, assume you need explicit neurologist approval before starting, not a casual mention during intake. Another practical issue: magnetic sensitivity. A small percentage of patients report headaches, dizziness, or increased tremor immediately after sessions. I've seen this in maybe 5 percent of trial users. The response is usually transient, resolving within hours, but it's frustrating when you're already dealing with medication fluctuations and off-periods. Starting with shorter sessions—five minutes instead of twelve—helps gauge tolerance before committing to the full protocol.
Cost-Benefit Considerations
Let me put some numbers on this. Clinic-based Bemer therapy for Parkinson's runs approximately 600 to 1,000 euros per month if done three times weekly. Home units range from 2,000 to 4,000 euros with no ongoing session fees. Insurance coverage is extremely rare. Most Parkinson's treatment plans already include medication, physical therapy, speech therapy, and possibly DBS surgery. Adding 600 euros monthly for a therapy with uncertain benefit is a significant decision. The medications for Parkinson's—levodopa/carbidopa, dopamine agonists, MAO-B inhibitors—have decades of robust clinical evidence behind them. Bemer has weeks of small-study evidence. There's no reason to view Bemer as anything other than a potential adjunct, and even then, a optional one. It should never replace or reduce prescribed medications without explicit neurologist involvement.

Who Might Actually Benefit
Based on what I've observed, the patients who tend to get the most out of Bemer are those in early-stage Parkinson's who are looking for supportive therapies with minimal side effects, have the financial means to sustain treatment, and maintain realistic expectations. If someone is hoping this will reverse symptoms or eliminate medication, the disappointment will be substantial. If someone views it as a low-risk circulatory support tool alongside their standard care, the risk-reward ratio improves. The counterintuitive thing is that patients with more advanced disease and significant autonomic dysfunction sometimes report better subjective responses. The theory is that their microcirculation is more compromised to begin with, so the vasodilatory effects are more noticeable. But advanced Parkinson's also comes with more comorbidities and medication complexities, which makes isolating any single intervention's effect nearly impossible.
What I'd Tell Someone Considering This
Discuss it with your neurologist first. Bring the device specifications. Ask specifically about interactions with your current medications and any implants. If your doctor is dismissive without inquiry, that's a yellow flag. A competent neurologist will at least look at the research and give you an informed opinion, even if that opinion is skeptical. Start with clinic sessions before buying a home unit. You need to know whether you respond at all before committing two to four thousand euros. Track your symptoms objectively—use the UPDRS self-assessment or a simple tremor and rigidity diary—before, during, and after a trial period. Subjective impressions are unreliable, especially with Parkinson's where medication timing already creates daily fluctuation. If you try it for eight to twelve weeks and see no measurable improvement, stop. There's no moral obligation to continue a treatment just because you've invested money in it. Parkinson's management is already complex enough without adding unproven interventions out of sunk-cost loyalty.