
The actual mechanics of contrast therapy
I spent a few years working with athletes who couldn't shake chronic lower leg inflammation, and we ended up doing a lot of hot cold therapy because standard anti-inflammatory approaches weren't cutting it. The whole concept is simpler than most people make it, but the way you apply it matters way more than the idea itself. You cycle between heat and cold exposure in set intervals. Heat causes vasodilation — blood vessels widen and push more blood into the area. Cold causes vasoconstriction — vessels clamp down and flush blood out. When you switch back and forth, you create a pumping action that moves inflammatory fluid out of the tissue and brings in fresh oxygenated blood. That's the entire mechanism. It's not magic, it's just fluid dynamics working on your capillary beds. The typical protocol I used was three minutes of heat followed by one minute of cold, repeated for four to six cycles, always ending on cold. The last cold phase is important because it leaves the vessels constricted, which limits residual swelling after you finish. I know that sounds backward — you'd think ending on heat would feel better — but the finish matters more for the actual therapeutic outcome.
Benefits Of Hot Cold Therapy in practice
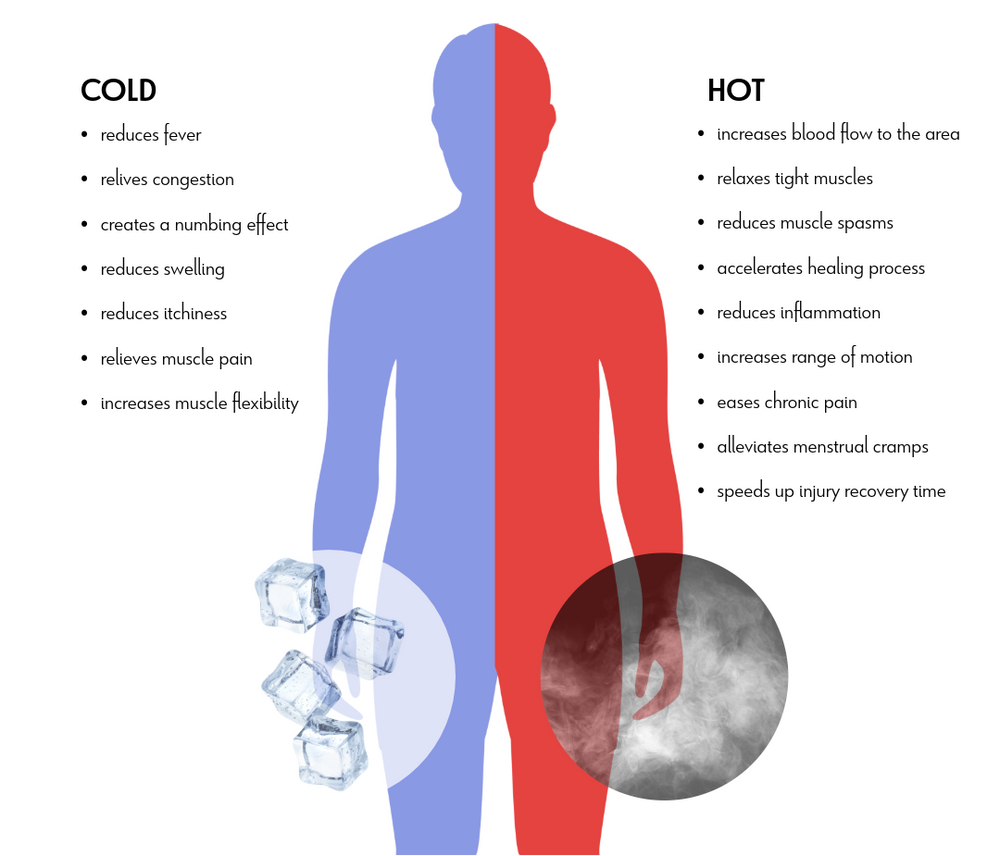
Here's what actually improves with consistent use. Delayed onset muscle soreness drops noticeably after the first week if you're doing it within twenty-four hours of intense exercise. Joint stiffness in the knees and ankles improves more reliably than I expected, probably because the pumping action gets fluid moving around the synovial space. Sleep quality tends to get better on nights you do a full session before bed, though the timing has to be right — doing it too close to bedtime can actually keep you wired for an hour or two. For acute injuries, the picture is different. I had a guy who rolled his ankle badly and immediately started doing contrast therapy on it. That made the swelling worse. You should never do this in the first forty-eight hours after a fresh injury. The heat phase expands blood flow into tissue that's already hemorrhaging, and you're literally pouring more fluid into an area that can't handle it yet. Ice alone for the first two days, then you can introduce contrast.
Equipment and setup
You don't need expensive gear. I've seen people use household items effectively, though the results vary depending on how consistently you can maintain the temperatures. For a full-body setup, a hot tub or heated plunge at around thirty-eight to forty degrees Celsius paired with a cold plunge or ice bath at around ten to fifteen degrees Celsius works well. The temperature gap doesn't have to be extreme. A ten-degree difference between sessions is enough to trigger the vascular response. Some people blast themselves at five degrees in the cold phase, but that's unnecessary and increases the risk of cold shock response, which makes the whole thing counterproductive because your body goes into stress mode instead of just responding to the temperature change. If you're working with a specific body part instead of doing full-body sessions, a simple setup is a bowl of hot tap water and a bowl of ice water. Submerge the affected area for the duration of each phase. I've used this approach for wrist tendonitis and it took about three weeks of daily sessions before the chronic tightness actually started to loosen up. Not overnight, but noticeable by day twenty-one.
Get the Full Details
There are commercial contrast therapy systems that cycle automatically with controlled water temperature and sometimes pneumatic compression. They're effective, but they're also expensive. A properly dialed-in DIY approach with basic equipment gives you about eighty percent of the benefit for maybe ten percent of the cost.
What most people get wrong
The biggest mistake I see is doing it too aggressively. People jump straight into five-minute heat sessions and two-minute ice baths, usually because they watched something online that looked impressive. Your tissue temperature doesn't actually reach the target temperature that quickly. Skin temperature equilibrates in about ninety seconds to two minutes, but core tissue temperature takes significantly longer. A three-minute heat phase is usually the sweet spot because it gets adequate warming without causing overheating or prolonged vasodilation that makes the subsequent cold phase less effective. Another common error is not protecting areas with poor circulation. I once had a client with mild Raynaud's in his fingers who tried full-hand contrast therapy and ended up with a significant flare-up that lasted three days. If you have any circulation issues, neuropathy, or reduced sensation in the area you're treating, you need to be much more conservative with the temperatures and durations, or skip it entirely for that area. The number of cycles matters less than consistency. Doing four cycles every other day beats doing eight cycles once a week. The vascular adaptations build up incrementally, and skipping days doesn't erase the progress you've made, but it does slow it down.
When it doesn't help
Contrast therapy isn't a universal fix. For structural problems like a torn meniscus or a stress fracture, cycling temperatures won't change the underlying issue. It might reduce some surrounding soft tissue inflammation, but the core problem remains. For nerve pain, the evidence is mixed at best. Some people report relief, others notice nothing, and a small number find it makes the neuropathic symptoms worse. If you have cardiovascular disease, the rapid shifts in blood vessel constriction and dilation create significant hemodynamic stress. Blood pressure spikes during the cold phase and drops during the heat phase. For someone with controlled hypertension, this is usually manageable. For someone with uncontrolled high blood pressure or a history of cardiac events, it's a real risk. I always recommended my clients with any cardiovascular history clear this with their doctor first. Pregnant women should avoid full-body contrast therapy, particularly the cold phases, because the core temperature fluctuations and blood pressure shifts aren't well studied in that population. Localized contrast on an isolated area like a sore shoulder is a different calculation, but even that isn't something I'd recommend without medical guidance during pregnancy.

A specific edge case I ran into
One of my clients had severe plantar fasciitis in both feet. Standard contrast therapy with whole-foot immersion didn't produce meaningful improvement after about two weeks. The issue was that his feet have relatively poor circulation compared to larger muscle groups, and the temperature change wasn't penetrating deep enough to affect the fascia. The workaround was to switch to alternating wet and dry heat and cold instead of water immersion. We used a heating pad for three minutes followed by an ice pack wrapped in a thin towel for one minute, same cycle ratio. The dry methods allowed more precise temperature control at the skin surface and the direct contact pressure of the packs seemed to enhance the mechanical component. He saw noticeable improvement in about ten days with this modified approach, compared to the two weeks of minimal change with water immersion. Different problem, slightly different method, same underlying principle.
The realistic timeline
If you're doing this correctly — proper temperatures, correct cycle durations, consistent frequency — you should start noticing some benefit within seven to fourteen days for soft tissue issues. Chronic conditions take longer. I've seen cases where the real improvement didn't show up until after three or four weeks of daily sessions. The early days often feel like nothing is happening, and that's when people quit. For prevention and maintenance once the acute issue is resolved, dropping down to two or three sessions per week is sufficient. You don't need to keep doing daily contrast therapy forever. The body adapts, and the conditioning effect persists with less frequent maintenance. The whole thing is straightforward in theory and most of the complexity comes from individual variation. What works for one person's knee might not work for another person's knee, and there's no substitute for paying attention to what your body actually does in response to the cycles. Keep it simple, stay consistent, and don't treat it like a cure-all.



