What Narrative Therapy Actually Does
Narrative therapy is a form of talk therapy that treats problems as separate from the person. The idea came from Michael White and David Epston in the 1980s. They were reacting against the way traditional psychiatry labels people. Instead of calling someone depressed or anxious, narrative therapists ask what story the problem is telling, and then help the person rewrite it. I started using this approach about eight years ago. Initially I was skeptical. The terminology felt pretentious at first. Outwardising – that's the technical term for separating the person from the problem – sounds complicated until you actually do it with a client. Then it clicks. It's not fancy. It's just practical reframing.
Benefits Of Narrative Therapy in Practice
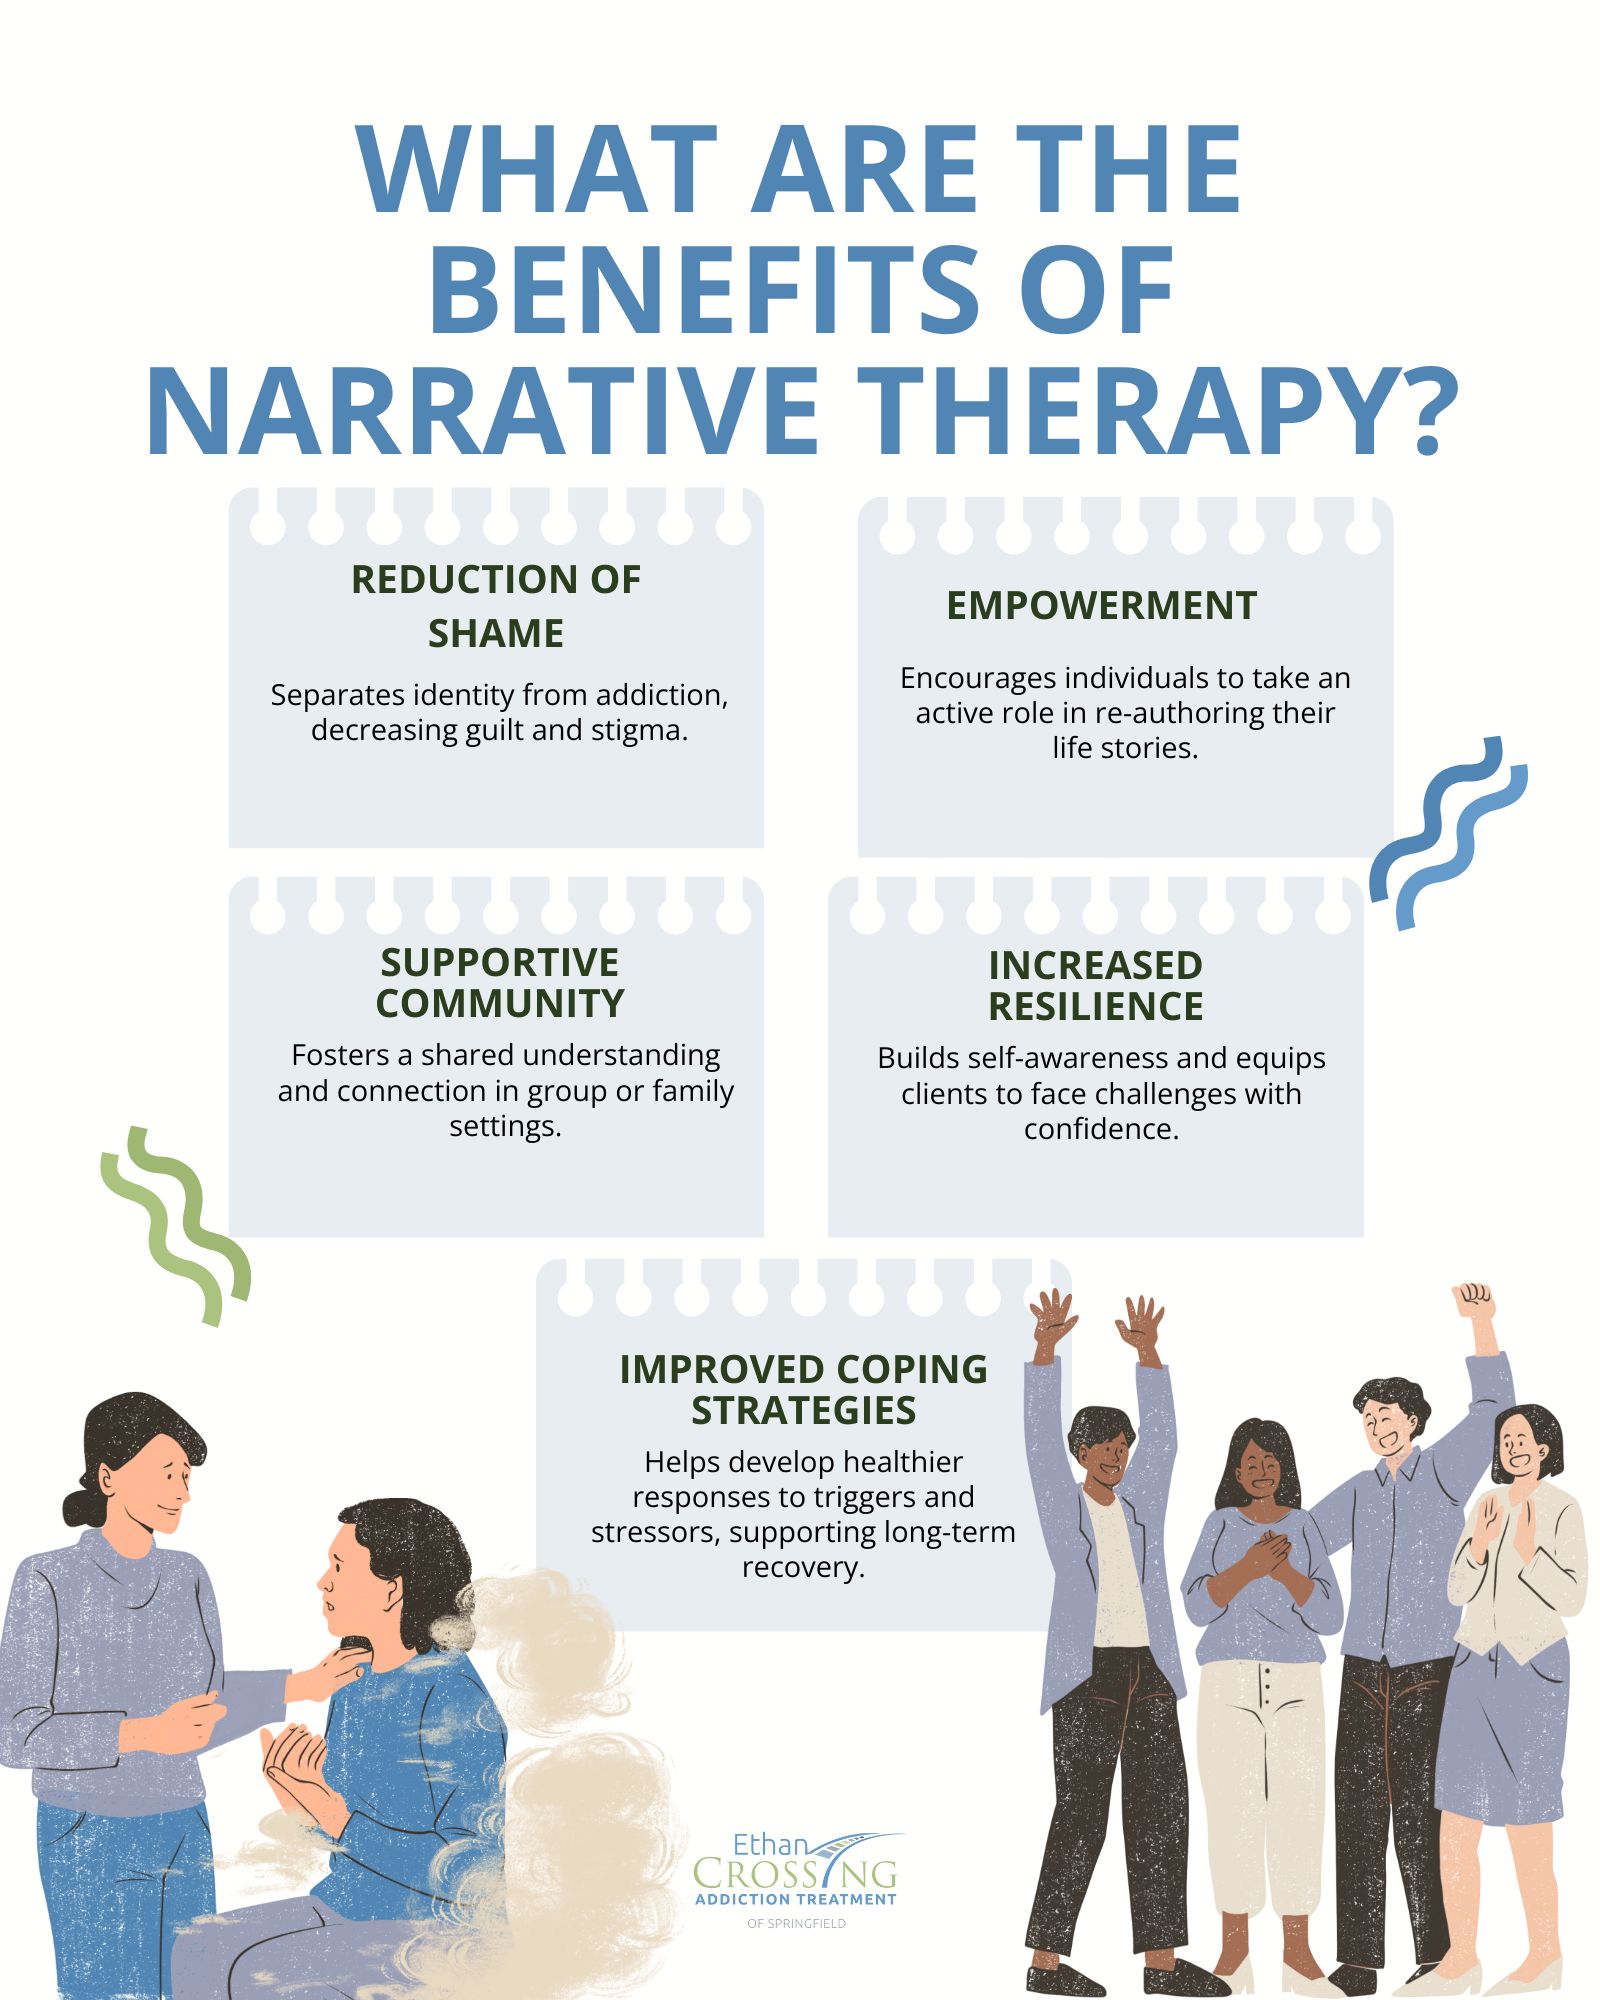
The main benefit is that it reduces shame. When someone carries a diagnosis like "I am a depressed person," they internalize it. Narrative therapy shifts that to "depression is visiting me." The problem becomes external. That single shift changes how a person relates to their own suffering. It also helps with identity consolidation. People often arrive with fragmented self-stories. They see themselves as failures, victims, broken. The therapist guides them to find unique outcomes – moments when the problem didn't win. Those moments get collected like evidence. Over several sessions, the alternative story becomes stronger than the problem-saturated one. Another benefit I've seen repeatedly: it works well with people who resist traditional therapy. If someone walks in saying they don't have a problem, narrative therapy gives them space to talk without feeling judged or pathologized. The therapist isn't looking for symptoms. They're looking for the story.
It's also useful for children and adolescents. The language is more accessible. A kid can talk to their "worry monster" or negotiate with "anger." It makes therapy feel less clinical and more collaborative.
Get the Full Details

How the Method Actually Works
Session one usually involves a mapping conversation. The therapist asks what brought the person in, but not in a diagnostic way. They ask about the problem's history. When did it start? What does it do? How does it show up? This externalizes the issue immediately. From there, the therapist looks for unique outcomes. These are exceptions to the problem's rule. Maybe someone with anxiety went six hours without worrying. That's a unique outcome. The therapist highlights it. They ask questions like "What would have to be true for that to happen?" or "Who noticed that you handled it differently?" As the therapy progresses, the therapist might use therapeutic documents – letters, certificates, or summaries that reinforce the new story. I've written hundreds of these. They sound informal because they are. A letter might say something like "I've been thinking about how you handled the panic attack last Tuesday. Most people wouldn't have walked out of that meeting." That's it. No drama. Just acknowledgment.
Externalizing conversations are the core technique. You name the problem. You personify it if needed. You create distance. I once worked with a man who had severe OCD. He called his obsession "The Inspector." Every time he checked something, he'd say "The Inspector wants another look." That naming gave him agency. He could argue with The Inspector. He could refuse. The problem was no longer him.
A Specific Edge Case I Encountered
Here's something most guides won't tell you. Narrative therapy doesn't work equally well for everyone. I had a client with severe complex PTSD who couldn't separate from her trauma narrative. The problem wasn't externalizable for her. It was too embedded in her identity. Every time I tried to "outwardise" the abuse, she'd collapse back into it. We spent three sessions going in circles. The workaround was to slow down. Instead of pushing for separation, I let her tell the story fully first. Not the rewritten version. The original. The problem-saturated one. She needed to feel heard before she could hear herself differently. After about six sessions of just listening, the unique outcomes emerged on their own. She started noticing moments when the trauma didn't control her. That's when the narrative work actually became possible. So here's the counter-intuitive part: sometimes you have to not do narrative therapy at first. You have to let the person stay in their story before you can help them leave it.

Common Pitfalls
The biggest mistake therapists make is moving too fast to the alternative story. Clients aren't ready. They've been carrying their problem-saturated narrative for years. Asking them to rewrite it in session two feels dismissive. It reads as if you're saying their pain doesn't matter. Another pitfall is the language becoming too jargon-heavy. If you're using terms like "externalizing conversation" or "unique outcome" with a client, you've lost the room. The techniques should be invisible. The conversation should just feel like talking. And here's something important: narrative therapy can fail with people who have active psychosis or severe dissociation. The deconstruction of reality that narrative therapy encourages can be destabilizing. In those cases, grounding techniques and more structured approaches come first. I've seen therapists try narrative methods with borderline personality disorder clients and make the fragmentation worse. It happens. Don't force it.
What the Research Says
Evidence for narrative therapy is mixed but leaning positive. Studies show it's effective for depression, anxiety, and trauma-related conditions. The effect sizes are moderate. Not as strong as CBT for some conditions, but comparable for others. The real advantage might be in retention. People tend to stay in narrative therapy longer because it feels less like treatment and more like conversation. There's also a cultural dimension. Narrative therapy aligns well with indigenous and community-based healing practices. The emphasis on storytelling, community witness, and collaborative meaning-making resonates with many non-Western frameworks. That's not a minor point. It makes the approach more accessible in diverse settings. One thing the research doesn't capture well: the therapeutic relationship in narrative therapy tends to be flatter. The therapist is not the expert. The client is. That matters. It changes the power dynamic. Some clients thrive in that environment. Others miss the guidance. Both are valid reactions.
Practical Takeaways
If you're considering this approach, start with the basics. Learn to listen for the problem-saturated story. Notice the language people use about themselves. "I'm a failure" versus "I failed at this task." That distinction matters more than people realize. Practice externalizing with yourself first. Name your own patterns. Give them silly names if you need to. It sounds trivial but it trains the muscle. You'll pick up the technique faster. Be patient with the process. Narrative change doesn't happen in one session. It takes repeated telling, revising, and reinforcing. The work is in the consistency, not the intensity.

And know when to step back. If the client is getting worse, if the narrative is collapsing rather than expanding, adjust. This isn't a rigid protocol. It's a flexible framework. The best narrative therapists I know are the ones who can read the room and pivot when needed.


