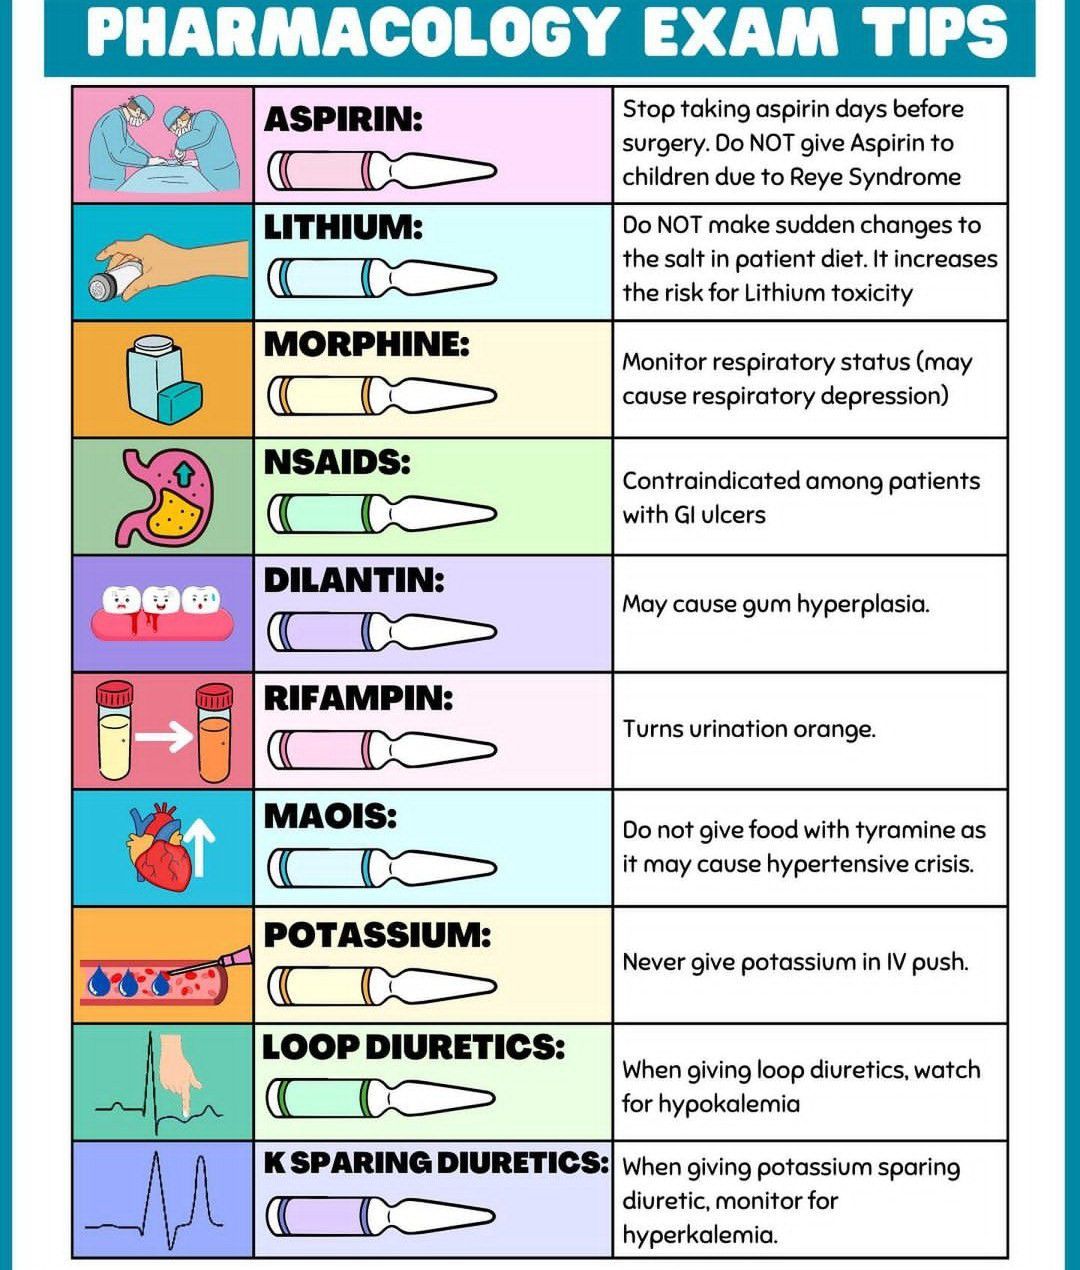
How to Actually Study Pharmacology Without Losing Your Mind
Most students approach pharmacology the wrong way. They try to memorize every drug individually, treating each one as a standalone fact to cram. It doesn't work well. The subject is too vast and too interconnected. What actually helps is organizing by mechanism, building comparison tables, and using active recall instead of passive reading. I spent weeks drowning in drug monographs during my second year before I figured out a system that stuck. Here is how it works in practice.
The Best Pharmacology Tricks for Long-Term Retention
The core principle is grouping. Instead of studying drugs one by one, study entire classes together. When you learn that all ACE inhibitors share the same mechanism, the same side effect profile, and the same contraindications, you are not memorizing ten separate drugs. You are memorizing one pattern and learning to spot the exceptions. That is dramatically faster and more durable. I used to make flashcards for every individual drug. One card for lisinopril, one for enalapril, one for captopril. Complete waste of time. I switched to a single card that asks: what are the distinguishing features of each ACE inhibitor? The answer is basically nothing clinically significant for most of them, with a few notes on prodrug status and half-life. That one card replaced twelve useless ones. The second trick is creating comparison matrices. Draw a grid with drug classes as rows and features as columns. Columns might include: mechanism, primary indication, major side effects, contraindications, and notable drug interactions. Fill it in as you study. When you get to antiarrhythmics, for example, you will see that Class IA drugs like quinidine and procainamide share prolongation of the QT interval, while Class IC drugs like flecainide do not. Spotting these patterns visually is something you cannot do from isolated flashcards.
Active recall matters more than anything else. Reading a textbook chapter four times will not help you retain more than reading it once while actively testing yourself. Close the book and write down everything you remember about beta-blockers. Then open the book and fill in the gaps. The gaps are where your learning happens. This is what Most students skip because it feels uncomfortable. That discomfort is the signal that it is working. Here is a specific edge case I ran into that illustrates why this approach matters. I was studying anticoagulants and had memorized the reversal agents for warfarin (vitamin K) and heparin (protamine sulfate) separately. During an exam, they asked about dabigatran reversal. I froze because I had studied it in isolation and could not retrieve it. The problem was not that the fact was hard. The problem was that I had not connected it to the broader pattern of direct thrombin inhibitors and their specific reversal agent, idarucizumab. After that, I built a single anticoagulant matrix that included mechanism, reversal agents, and monitoring parameters for every major class. It took two hours to build and has saved me countless hours since. Another technique that works well is the drug name pattern method. Many drug classes have naming conventions that tell you something about their mechanism or use. Drugs ending in -pril are ACE inhibitors. Drugs ending in -lol are beta-blockers. Drugs ending in -statin are HMG-CoA reductase inhibitors. This sounds basic but students consistently overlook it because they treat naming as trivia instead of a learning shortcut. When you see a new drug name, the suffix alone can trigger the entire mechanism family in your memory.
Get the Full Details

Spaced repetition software like Anki is useful if you use it correctly. The mistake most people make is dumping pre-made decks into Anki and letting it grind through thousands of low-quality cards. Those decks are full of trivial recall questions that do not test actual understanding. Build your own cards using the matrix method I described. A good card might ask you to name three drugs in a class and their distinguishing features, not just recall a single fact. This forces you to think comparatively and makes the review sessions more efficient. The biggest limitation of this approach is that it requires upfront investment. Building your first set of comparison matrices and custom flashcards takes two to three times longer than passively highlighting a textbook. If you are studying the night before an exam, none of this helps. What works here is starting early, ideally weeks before the test, and revisiting the material repeatedly over time rather than in one massive cram session. Sometimes the matrix approach also falls short when drug information changes rapidly. New drugs get approved, guidelines shift, and your hand-drawn comparison tables become outdated. In those cases, keeping a living digital document that you update regularly is more practical than static paper notes. I switched to a shared spreadsheet for my final two years and it cut my review time roughly in half compared to my earlier system of bound notebooks.
One more thing that people overlook: clinical context. Every drug you study should be tied to at least one real clinical scenario. Why is metformal first-line for type 2 diabetes? Because it works differently than sulfonylureas and does not cause hypoglycemia as often. Understanding the clinical reasoning behind a drug's placement in a treatment algorithm makes the pharmacology stick in a way that pure mechanism memorization never will. When you know why a drug is used, the how and what become secondary and easier to recall under pressure.