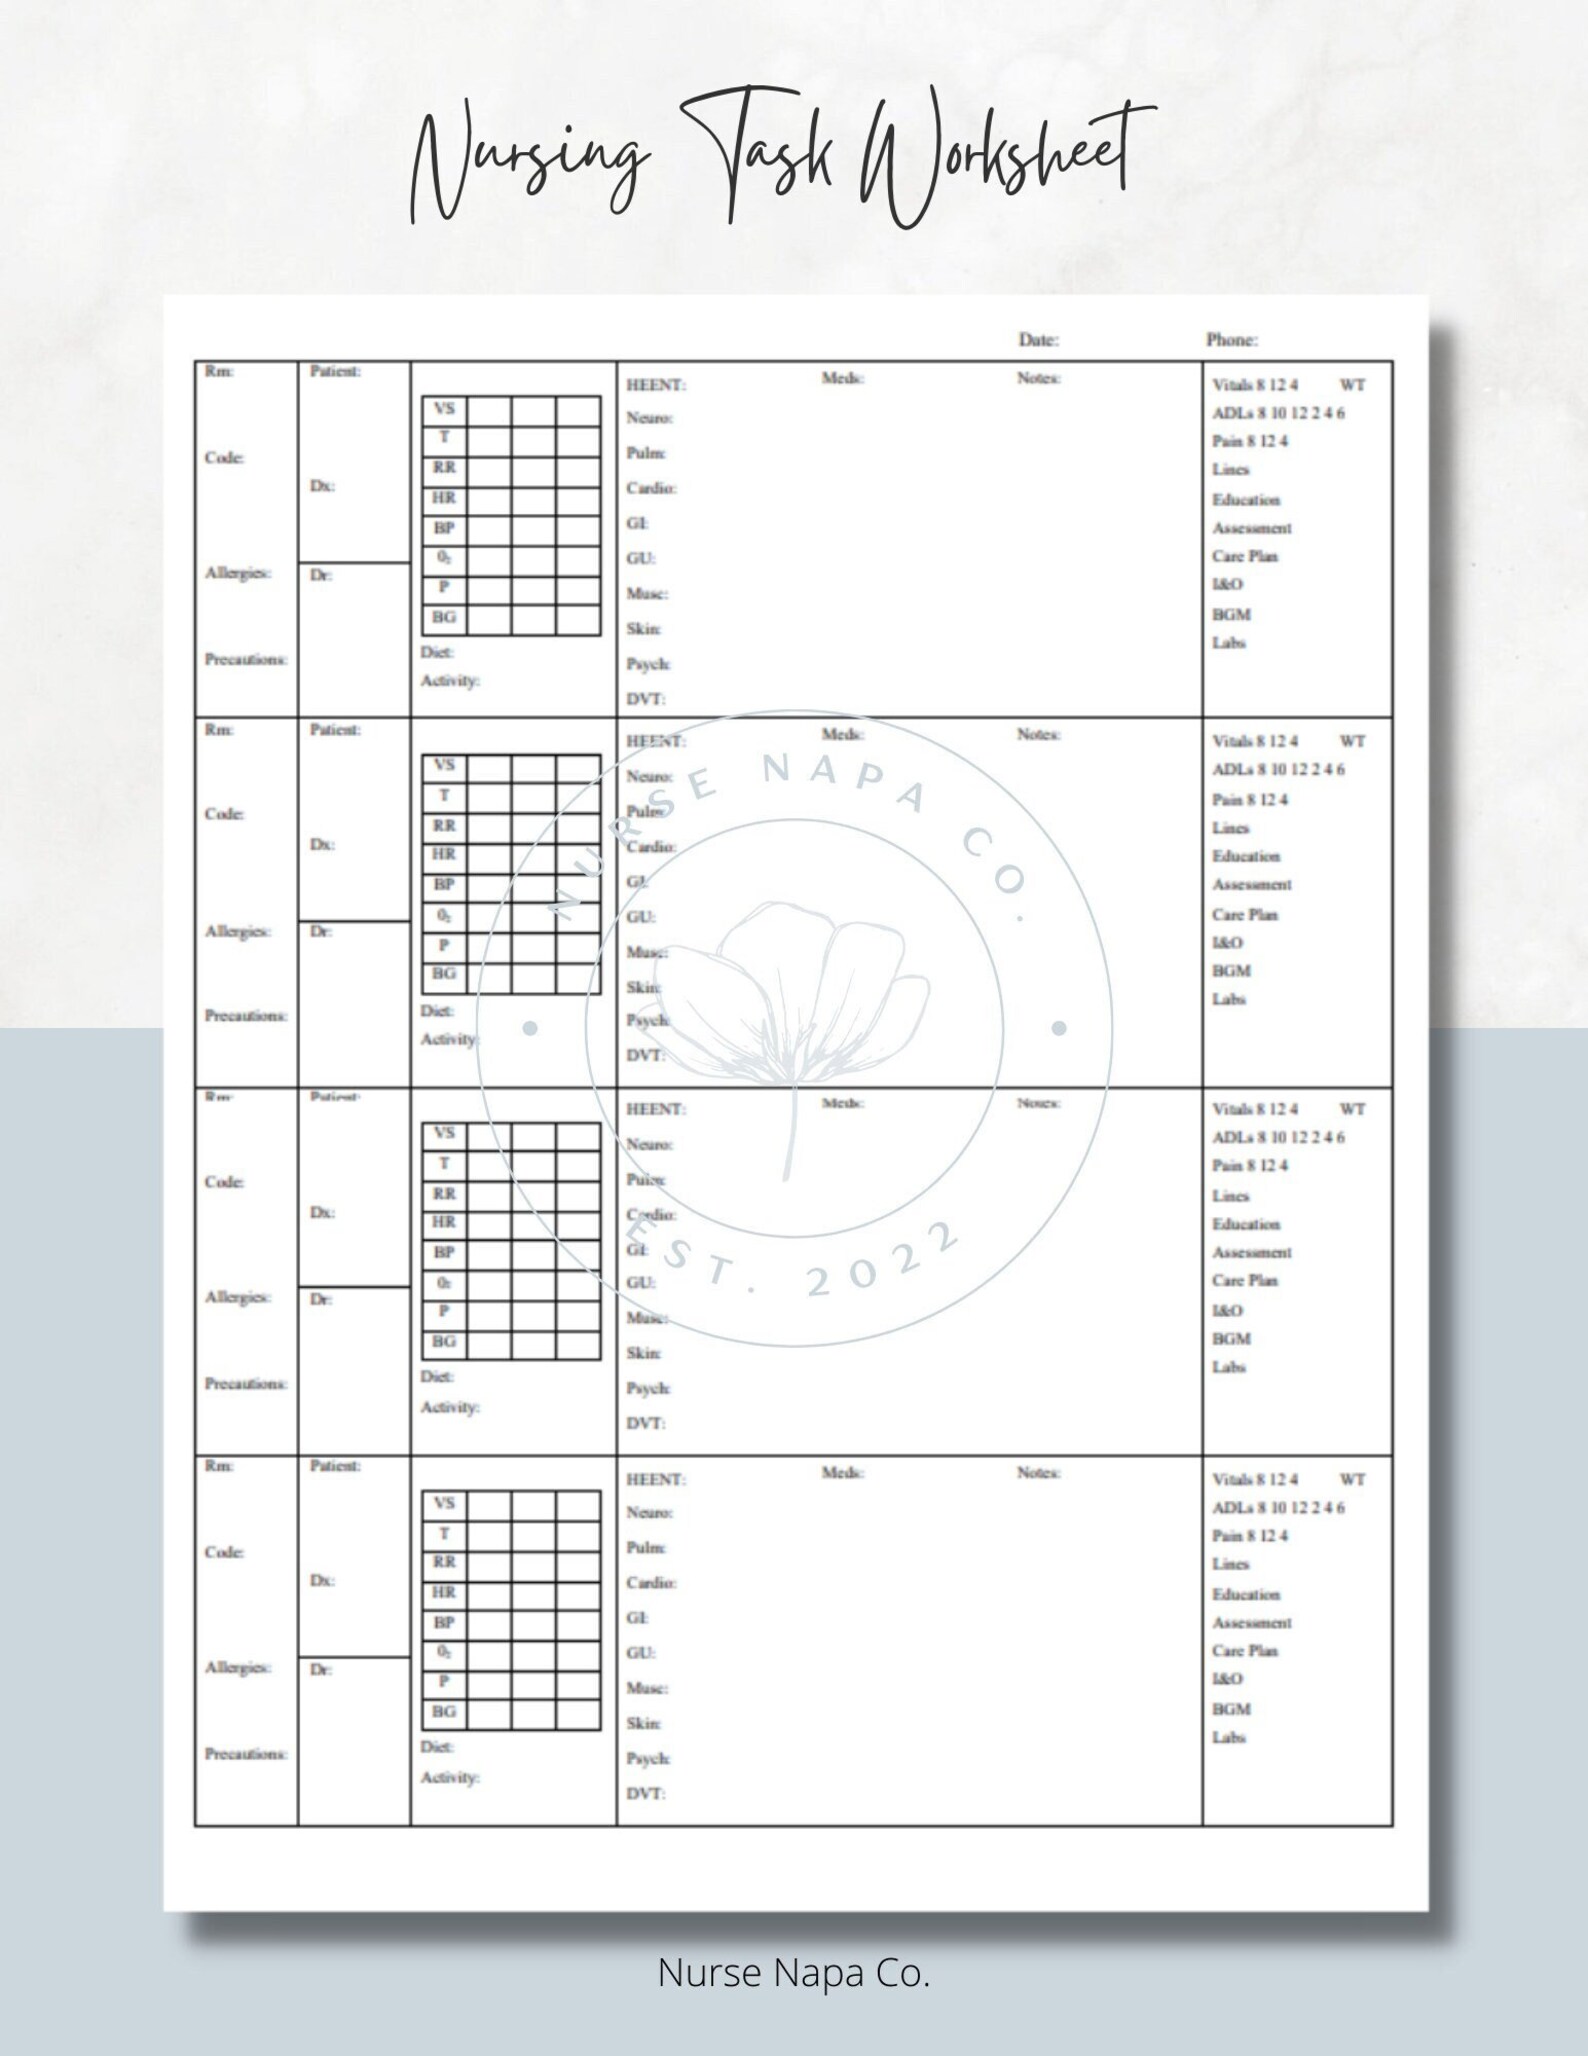
Nursing worksheets are a pain in the ass if you do them wrong
I spent seven years doing clinical documentation before I stopped fighting the system and actually learned how to make a worksheet work for me instead of the other way around. Most people treat these like busywork — they fill out the fields, hand it in, and move on. That's not how you avoid the re-dos and the charting audits. Here's what I wish someone had told me on day one.
The Best Way To Nursing Worksheet Isn't About Speed
It's about structure. A nursing worksheet is essentially your legal record for a patient encounter — vitals, assessments, interventions, outcomes, everything that shows up if a charge nurse or compliance officer looks at your work. I've seen people spend 45 minutes filling out a worksheet by hand, only to have it sent back because they skipped the "patient response to intervention" column or used abbreviations that aren't on the approved list. The best approach is to build a template that matches your facility's actual fields, not some idealized version. Print out five of the actual worksheets your unit uses, highlight every required field in yellow, and then create a master copy with those fields as the skeleton. When you're doing real charting, you're just populating what's already there. I learned this the hard way during my med-surg rotation. My preceptor pulled me aside after I submitted a worksheet missing the "fall risk reassessment time" entry — something I hadn't even known was a required field. She showed me her own worksheet with exactly that field marked. I made a checklist from hers and haven't had a returned worksheet since.
What Most People Get Wrong
Abbreviation discipline is the number one issue. You think "q4h" is obvious. Your instructor doesn't. They want "every 4 hours." Same thing, different level of pain. Every facility has an approved abbreviation list. Find it. Tape it to your binder. Read it before you fill anything out. The second mistake is leaving assessment fields blank because you think "nothing abnormal" means the field can be skipped. It can't. If a field exists on the worksheet, you address it. Write "no acute distress observed" or "within normal limits" — something that proves you actually looked. A blank field looks like you forgot, not like you checked. There's also the timing problem. Worksheets are supposed to be completed contemporaneously, meaning at the time of the encounter. I've seen students fill out three weeks of worksheets on Sunday night before clinical. It doesn't work. The dates don't match the flow sheets, the medication times are wrong, and your instructor can tell because the handwriting gets messier the further back in time you go. Do them after each shift, even if it takes twenty extra minutes.
Get the Full Details
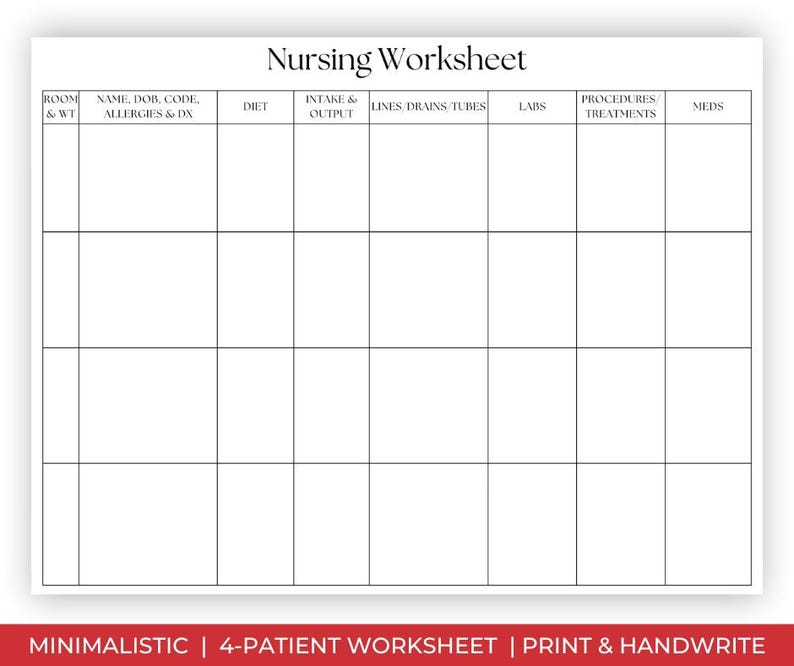
My Go-To Method
Here's the workflow that actually works for me: First, I keep a small notebook next to my computer during shift. I jot down the key data points as they happen — vitals, interventions, patient statements. Not full sentences, just triggers. "BP 142/88, given 5mg PO hydralazine at 1400, recheck q30min." Then, right before I leave or within the first thirty minutes of my break, I transfer those notes onto the worksheet. The data is fresh, the sequence is correct, and I'm not reconstructing a whole shift from memory. This usually cuts my worksheet time from about 35 minutes down to 12.
Before I submit, I run through a five-second checklist: all fields filled, abbreviations approved, dates and times consistent, signatures present. If anything is missing, I fix it now. I'd rather spend two minutes correcting it than getting it sent back and having to redo it after going home.
When Worksheets Fail You
I should be honest about the limitations. The worksheet system works fine for routine care. It breaks down when you're managing a rapidly changing patient — a sepsis alert, a code blue follow-up, anything where you're charting every ten minutes. In those situations, the worksheet becomes a reconstruction exercise, and that's where errors creep in. During critical events, use a separate quick-note pad for real-time timestamps, then transfer to the formal worksheet once the situation stabilizes. Don't try to fill out a printed worksheet while someone is actively crashing. Another limitation: electronic worksheets versus paper ones. If your program uses electronic charting simulations, the principles are the same but the interface adds its own friction — dropdown menus, mandatory pop-ups, system timeouts. I found that keeping a browser tab open with the approved abbreviation list and another with a blank worksheet template made the transition significantly faster. Without that prep, you're clicking through screens blind. If you're looking for a starting point, most nursing programs provide their own worksheet templates through the LMS. If not, the American Nurses Association has downloadable forms that cover the major categories — admission assessments, flow sheets, and discharge summaries. Don't build your own from scratch unless you have to. Use what's standard, learn it, then customize it to your situation.