Understanding the Biceps Brachii Attachment Points
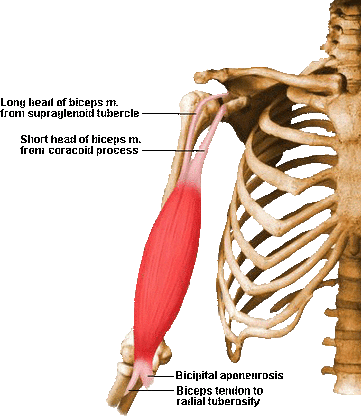
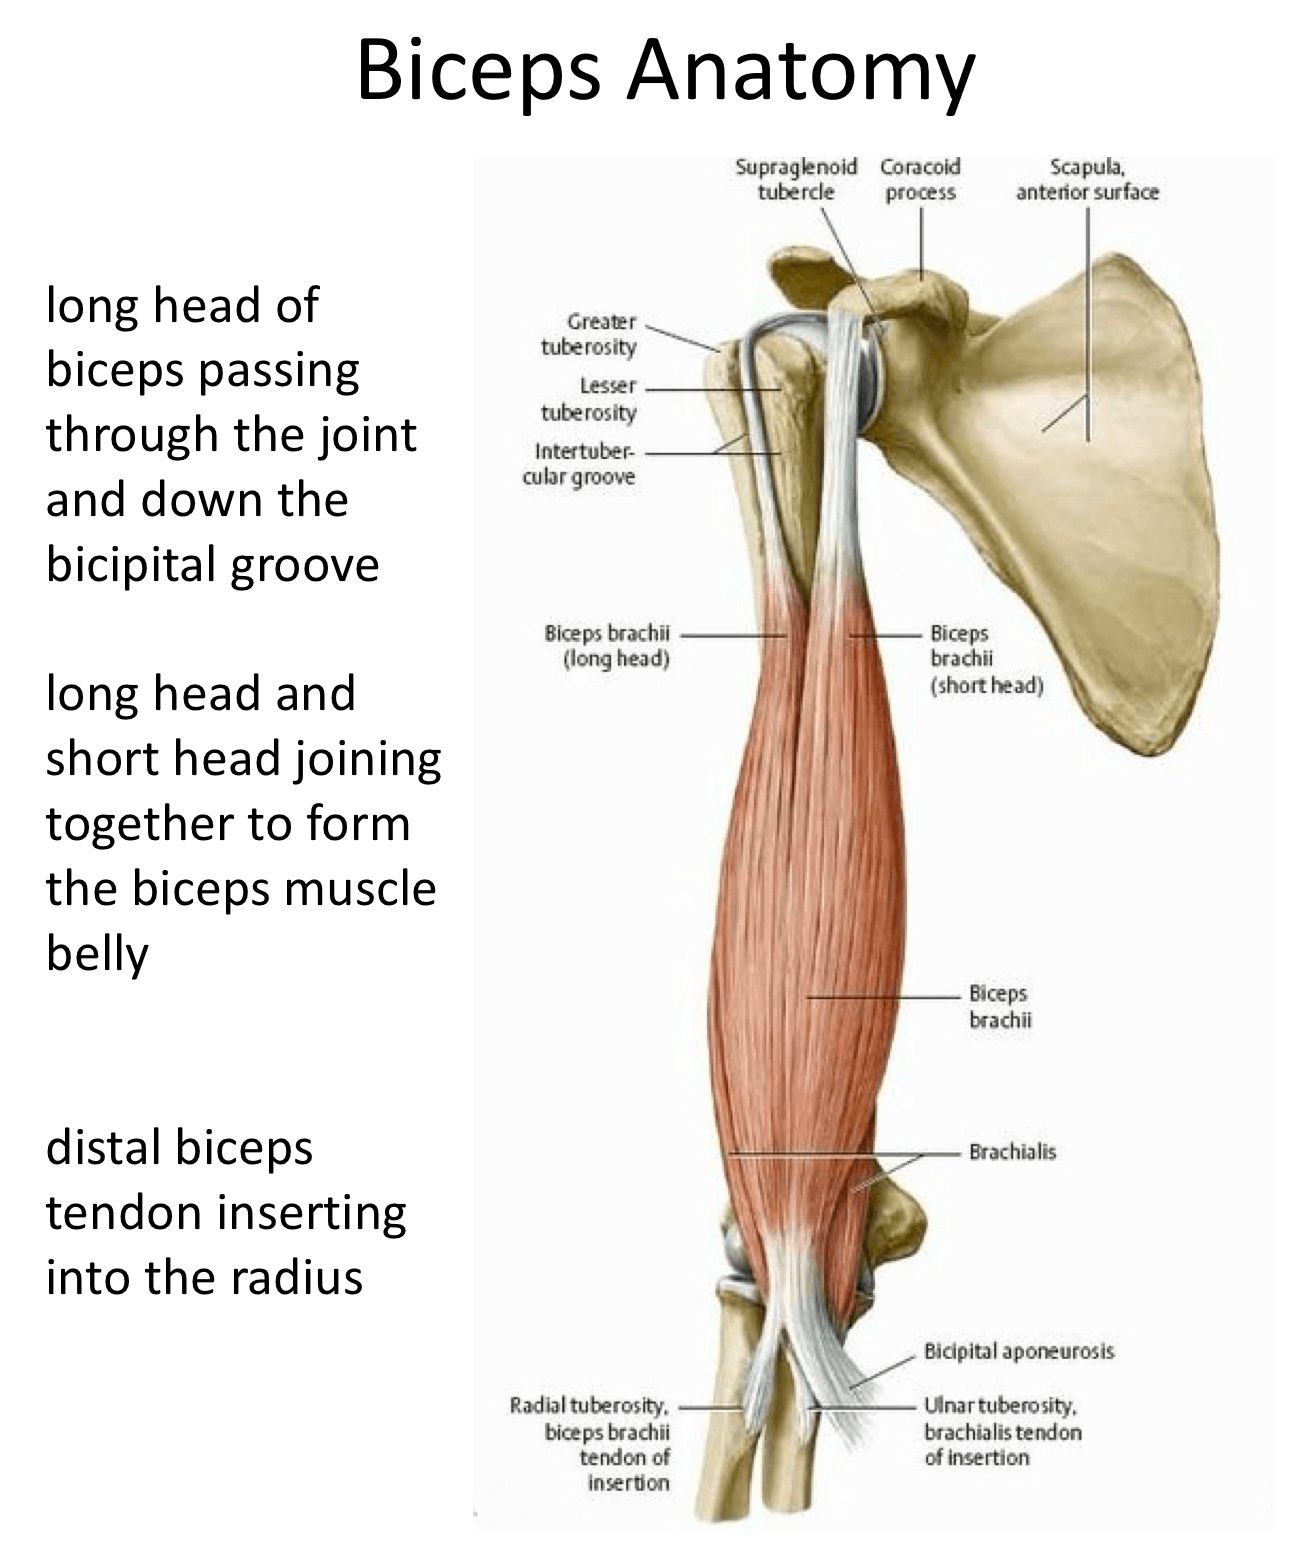
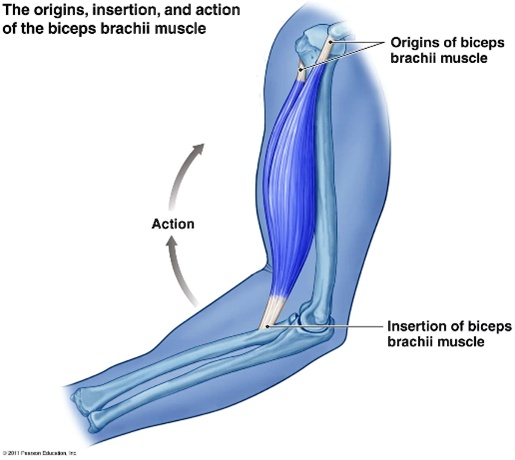
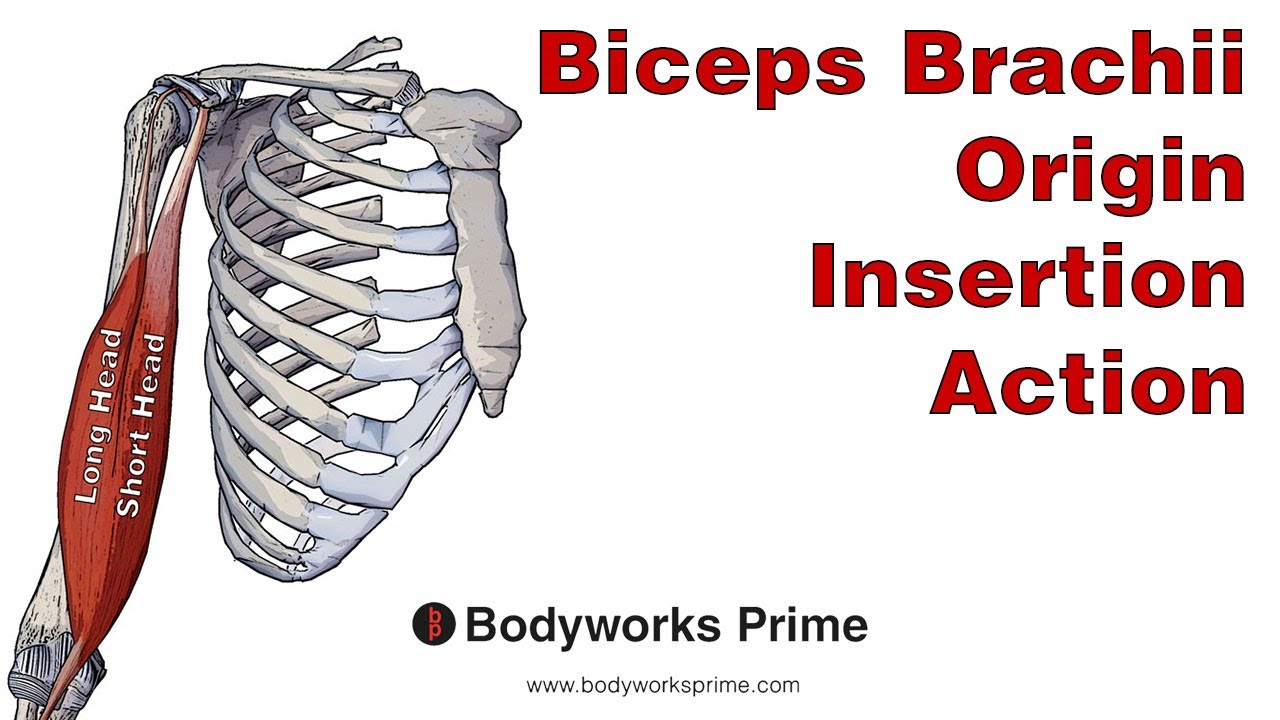
The biceps brachii is a two-headed muscle in the anterior compartment of the upper arm, and knowing exactly where it attaches and what each head does will change how you train it and rehab injuries around it. Most people who study this just memorize two origin points and one insertion point without understanding why the difference between those two origins matters in practice. Biceps insertion and origin is not a single structure - it is two separate tendinous beginnings converging into one functional unit before attaching distally. The long head originates from the supraglenoid tubercle of the scapula and passes through the shoulder joint capsule before joining the short head. The short head originates from the coracoid process of the scapula and stays entirely outside the shoulder joint. Both heads merge into a single muscle belly in the mid-arm and converge into the distal biceps tendon, which inserts primarily onto the radial tuberosity. A secondary attachment exists through the bicipital aponeurosis, which fans out into the deep fascia of the forearm near the medial side.
Biceps Insertion And Origin in Clinical Practice
I spent months dealing with a client who had chronic elbow pain that no one could pin down. Every trainer assumed it was just a tight biceps or overuse from curling. The real issue was a partial avulsion at the radial tuberosity insertion - barely visible on standard ultrasound because the tear was frayed, not clean. What gave it away was a specific weakness in supination against resistance when the elbow was held at 90 degrees, combined with tenderness directly over the tuberosity rather than along the muscle belly. We modified his training by removing all supination-dominant movements for six weeks and introduced controlled eccentric loading on light dumbbell curls at a slow tempo. The pain dropped significantly within three weeks. Here is something most anatomy textbooks gloss over: the long head of the biceps does far more work at the shoulder than at the elbow. When your arm is overhead or extended behind you, the long head fires hard to stabilize the humeral head in the glenoid. That is why shoulder impingement and biceps tendinopathy show up together so often - the tendon is being ground against the bicipital groove under load. If someone has shoulder pain and you only stretch their biceps without addressing scapular positioning, the pain will come right back. Another counter-intuitive fact is that the biceps is actually a much stronger supinator than flexor when the elbow is bent past 100 degrees. At that angle, the radial tuberosity is pulled closest to the humerus, giving the tendon its best mechanical advantage for rotation. Most people train supination wrong by doing hammer curls, which actually bias the brachioradialis and brachialis far more than the biceps. If you want to target the biceps insertion point properly, use supinated-grip curls with a controlled range of motion where the elbow stays close to the torso.
There is a notable anatomical variant that catches people off guard. Roughly 15 to 20 percent of the population has an anomalous insertion where a portion of the distal biceps tendon attaches to the antebrachial fascia instead of the radial tuberosity. This changes the force vector entirely - those individuals get less supination power and more flexion dominance. I learned this the hard way when a gymnast came to me with disproportionate biceps hypertrophy in one arm after a trauma. MRI showed a low-riding insertion that had partially avulsed and reattached abnormally. Standard curl exercises aggravated it because the leverage was wrong. We switched her to isometric holds at mid-range and avoided full elbow extension under load until the tendon remodeled. The bicipital aponeurosis is another structure that deserves more attention than it gets. It is not just connective tissue filler - it acts as a biological splint that reinforces the antecubital fossa and protects the brachial artery and median nerve underneath during elbow flexion. If a distal biceps rupture goes untreated, the aponeurosis can actually tear free from its medial attachments, and that is when you start seeing neurovascular compression symptoms. Early surgical repair within two to three weeks of injury makes a meaningful difference in outcomes because the aponeurosis has not yet retracted and scarred down. On the practical side, if you are assessing someone for biceps issues, do not just test elbow flexion strength. Test supination against resistance with the elbow at 90 degrees, test shoulder flexion against resistance with the arm overhead, and palpate along the entire course of the long head tendon inside the bicipital groove. Pain in the groove points to long head tendinopathy. Pain at the radial tuberosity points to distal insertion pathology. Pain at the coracoid process points to short head involvement. Three different problems, same muscle group, completely different treatments.
Get the Full Details
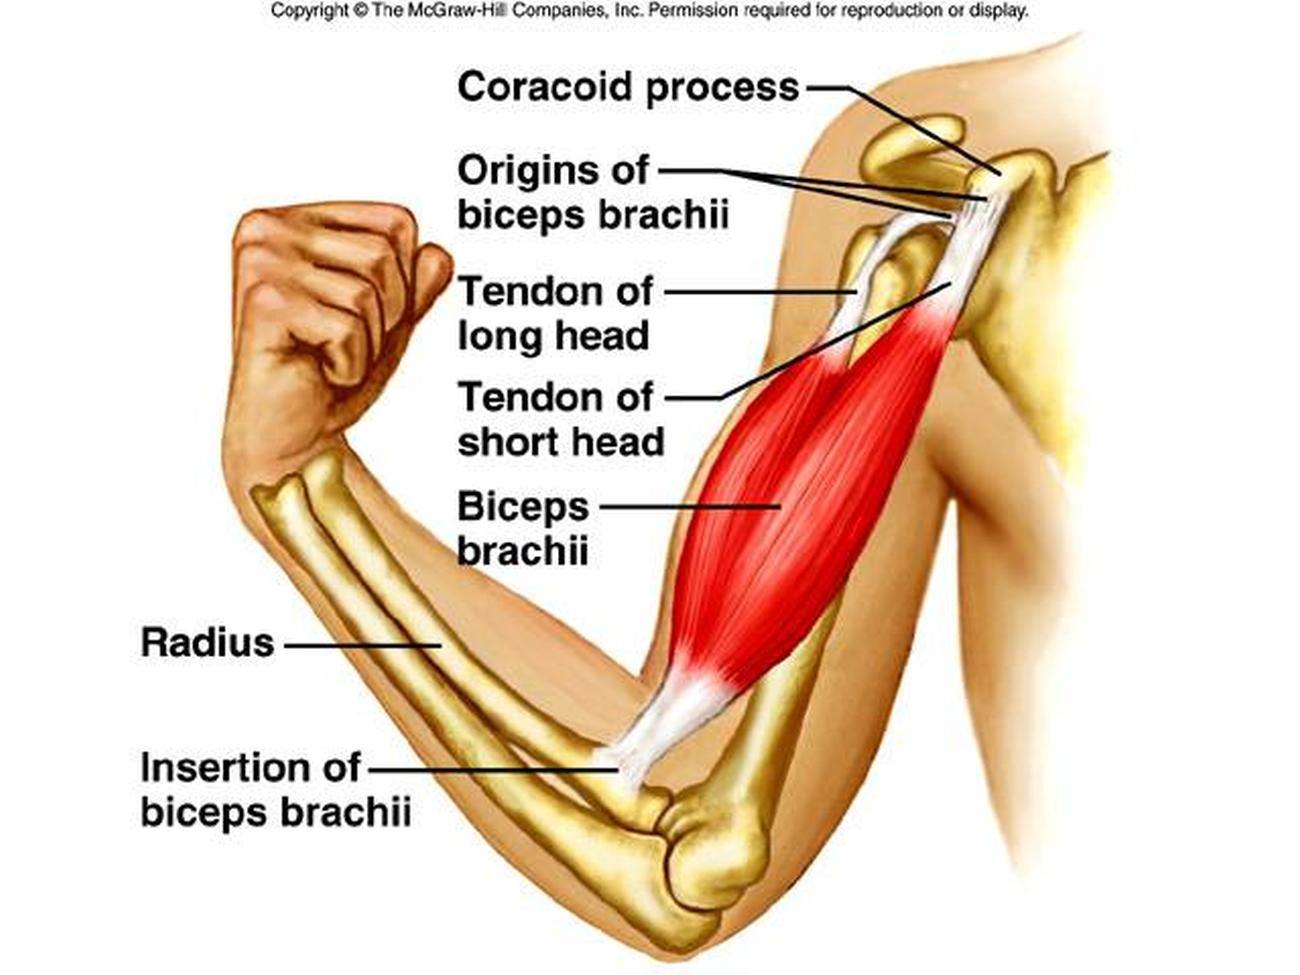
One limitation worth noting: the biceps insertion point on the radial tuberosity is inherently vulnerable to repetitive high-force supination. Throwers, weightlifters, and rock climbers all stress this attachment repeatedly. No amount of stretching or mobility work will prevent microtrauma at the insertion if the volume of supination-loading is too high. The only real workaround is periodization - cycling heavy supination work with deload phases and monitoring for early signs of radial tuberosity tendinopathy, which presents as deep, aching pain on the anterior lateral elbow that worsens with lifting and pressing movements.