Getting Thyroid Medication Right Is More Tricky Than Most People Realize
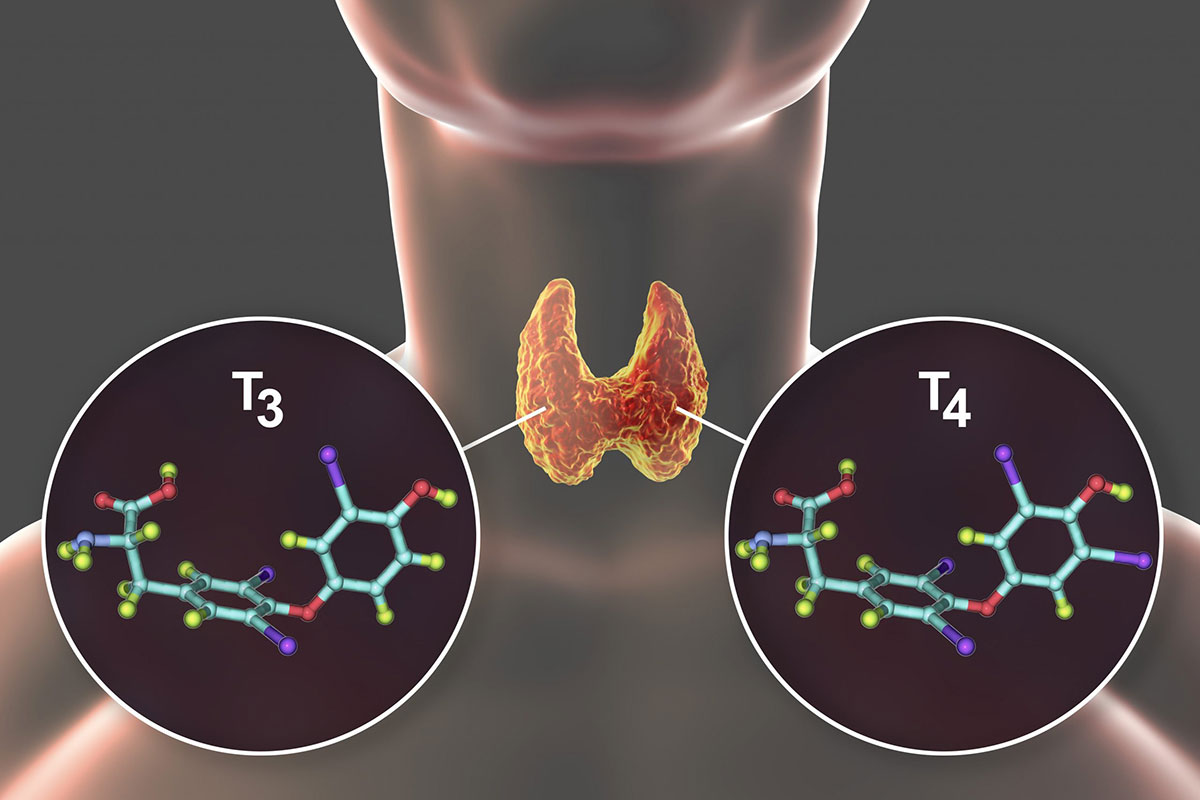
Most people start with levothyroxine (synthetic T4) and never think twice about it until their labs look fine but they still feel exhausted, foggy, and cold. That's where the whole bioidentical thyroid conversation starts, usually in Facebook groups and endocrinology forums where people share prescriptions they shouldn't be discussing with each other. I've been managing thyroid hormone replacement for roughly fifteen years across both functional medicine and conventional settings, and the thing nobody tells you is that dose adjustment is a mess of individual biochemistry, not a standard algorithm. The term refers to thyroid hormones that are chemically identical to what your thyroid gland produces: T4 (levothyroxine) and T3 (liothyronine). When people say bioidentical, they usually mean compounded versions of these exact molecules rather than the brand-name pharmaceuticals, or they mean desiccated thyroid extract like Armour Thyroid, which contains both T4 and T3 from porcine thyroid glands. The T3 in desiccated preparations is animal-derived but structurally identical to human T3, so it qualifies. Natural desiccated thyroid has a T4-to-T3 ratio of roughly 4:1, which doesn't match human physiology exactly, and that mismatch causes problems for a subset of patients. I've seen clients run perfectly reasonable TSH values on synthroid and still feel miserable, then stabilize on a compounded T4/T3 combination at a different ratio. The mechanism is straightforward: your body converts T4 to T3 in peripheral tissues through deiodinase enzymes, and that conversion process varies wildly between individuals based on genetics, gut health, stress levels, and selenium status. Some people are simply poor converters, and giving them T3 directly bypasses the bottleneck.
There's a specific problem that comes up constantly and almost nobody warns you about. A patient of mine was on 88 mcg of levothyroxine daily, TSH was 1.2, free T4 was solid, but free T3 sat at the low end of normal around 2.8 pg/mL. She reported brain fog and exercise intolerance that her previous doctor attributed to something else entirely. The workaround was switching to a compounded preparation with 100 mcg T4 and 25 mcg T3 split into two doses per day, then rechecking labs at six weeks. Her free T3 climbed to 3.9, and the brain fog lifted substantially within three weeks of the change. The key was checking free T3 before deciding anything was wrong—standard panels often skip it.
The Practical Setup and Dosing Reality
Compounded bioidentical thyroid medications come from specialty pharmacies, not your local pharmacy. You need a prescriber who's comfortable writing those prescriptions, which rules out a lot of endocrinologists who stick strictly to brand-name levothyroxine. Primary care providers in functional or integrative medicine settings are usually more willing, but verify that before you commit to a switch. The actual dosing follows standard thyroid hormone pharmacology: starting low and adjusting in 12.5 to 25 mcg T3 increments or 25 mcg T4 increments every six to eight weeks. You don't rush this. Thyroid hormone has a long half-life—about seven days for T4—and overshooting leads to hyperthyroid symptoms that take weeks to resolve. Monitoring intervals matter more than most people understand. Check TSH, free T4, and free T3 before any adjustment. Total T3 is useless for dosing decisions because it's influenced by binding protein levels. Reverse T3 testing is controversial and rarely changes management unless you're dealing with complex critical illness scenarios, which is most of your patients not. The biggest counter-intuitive insight I've learned is that TSH can be misleading during the first few months of bioidentical combination therapy. Suppression of TSH doesn't automatically mean you're over-replaced on T3. T3 crosses the pituitary quickly and can temporarily suppress TSH without reflecting true thyrotoxicosis at the tissue level. If your patient feels fine and their free T4 and free T3 are in the mid-range, a TSH of 0.3 isn't necessarily a crisis. Wait another four to six weeks and recheck before making changes. I've pulled doses too aggressively because I reacted to a low TSH too quickly, and the patient swung into uncomfortable hypothyroid territory as a result.
Get the Full Details

Where This Approach Falls Apart
Bioidentical thyroid hormone replacement therapy is not a universal solution. It fails in several scenarios that practitioners sometimes overlook. Patients with central hypothyroidism—where the problem originates in the pituitary or hypothalamus rather than the thyroid itself—don't respond to TSH-based monitoring at all. You have to dose based on free T4 and clinical response exclusively, and even then it's less predictable. Another hard limitation: people with severe malabsorption issues from conditions like celiac disease, H. pylori infection, or atrophic gastritis may not absorb oral thyroid hormone well regardless of whether it's compounded or brand-name. I had a case where a patient's labs wouldn't budge across multiple dose adjustments until we addressed an untreated H. pylori infection, after which the same dose produced normal results within two weeks. Compounded medications also carry quality control variability that brand-name drugs don't. Different pharmacies use different fillers and binders, and batch-to-batch consistency isn't guaranteed the way it is with FDA-approved products. If a patient switches pharmacies, they should recheck labs within six weeks regardless of how stable they were before. There's no workaround for that reality. If your goal is simply lowering thyroid hormone requirements or improving conversion efficiency without switching medications, addressing underlying drivers like iron deficiency, zinc deficiency, or chronic inflammation often moves the needle more than adjusting the hormone formulation itself. I've had patients who needed a 50 mcg T4 dose reduction after correcting a ferritin level that was sitting at 12 ng/mL, which is technically within the lab's reference range but suboptimal for deiodinase function. Standard ranges are not the same as optimal ranges, and that distinction matters considerably when you're managing thyroid replacement.