
Where Biostatistics Actually Shows Up In The Pharmacy World
I spent about six years working in a hospital pharmacy where we ran weekly medication utilization reviews. Every Thursday morning, someone would pull the latest dispensing data, cross-reference it with adverse event logs, and try to figure out whether a particular drug category was showing a signal. The process used to take three people two days because nobody could agree on which statistical method actually fit the dataset. That changed when we started applying formal biostatistics frameworks instead of just running basic averages and hoping for the best. The core issue most people miss is that pharmacy data doesn't behave like clean textbook examples. You've got right-censored outcomes from patients who switch medications mid-trial. You've got clustered data when multiple pharmacists work the same shift and enter orders in the same window. You've got zero-inflated counts when certain drug classes are barely used in your patient population. Running a standard t-test on that mess gives you results that look fine until someone actually checks the assumptions.
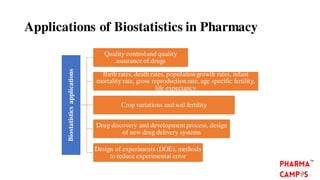
Biostatistics Application In Pharmacy
At its simplest level, this field sits at the intersection of three things: pharmaceutical research design, clinical outcome measurement, and statistical inference. The goal is to turn raw pharmacy data into decisions that actually hold up under scrutiny. A drug effectiveness study isn't just about counting prescriptions filled. It's about understanding selection bias when sicker patients get prescribed a particular medication. It's about handling missing data when patients don't show up for follow-up labs. It's about calculating the right sample size so your confidence interval isn't so wide the result is useless. In practice, this shows up in clinical trials, pharmacoeconomic evaluations, real-world evidence generation, and post-marketing surveillance. Clinical trials need survival analysis like Cox proportional hazards models when the outcome is time to adverse event. Pharmacoeconomics uses Markov models to compare long-term cost-effectiveness between drug classes. Real-world evidence often relies on propensity score matching because randomized controlled trials never actually capture the messy diversity of outpatient populations.
The Methods That Actually Matter In Day-To-Day Pharmacy Work
Regression modeling is probably the most common tool, but the type you choose depends entirely on your outcome variable. Logistic regression handles binary outcomes like whether a patient fills a prescription within seven days. Poisson or negative binomial regression works for count data like the number of medication errors per month. If your outcome is time-to-event, you're looking at survival analysis with Kaplan-Meier curves and Cox models. Linear regression sounds simple but breaks down fast when your residuals aren't normally distributed, which happens constantly with pharmacy datasets that have heavy tails or outliers from rare drug reactions. Mixed-effects models deserve more attention than they get. In pharmacy settings, you often have hierarchical data: patients nested within pharmacies, pharmacists nested within regions, prescriptions nested within days. Ignoring that clustering underestimates your standard errors and makes everything look more significant than it actually is. A random intercept for pharmacy location can account for site-level differences in prescribing culture without eating all your degrees of freedom. I once ran an analysis comparing two antihypertensive regimens and missed the clustering entirely. The p-value looked great at 0.02 until a colleague flagged that seven pharmacies contributed 80 percent of the data. Once I added a random effect, the confidence interval widened enough to include clinical irrelevance. Meta-analysis is another area where pharmacy professionals frequently encounter it, especially when making formulary decisions. You're not always running primary research. Sometimes you're synthesizing existing evidence across multiple trials. The question isn't whether to pool the data but how. Fixed-effect models assume one true effect size across studies, which is almost never realistic in pharmacotherapy. Random-effects models account for between-study heterogeneity, but they require enough studies to estimate that variance properly. Fewer than ten studies and your heterogeneity estimate is basically noise. I've seen formulary committees make spending commitments based on meta-analyses with four studies and an I-squared of 87 percent. That's not evidence, that's a guess with a forest plot.
Get the Full Details
A Specific Problem I Ran Into And How I Worked Around It
About three years ago, our pharmacy department wanted to evaluate whether a new diabetes medication was associated with improved adherence compared to the standard treatment. The dataset came from our electronic health record system covering eighteen months of dispensing data. The obvious approach was a Cox model with time-varying exposure. But the medication had a ninety-day supply limit built into the insurance policy, which meant everyone in the study was censored at exactly ninety days regardless of whether they stopped the drug or not. This wasn't clinical censoring, this was administrative censoring, and the Cox model would treat them identically. I solved this by using a joint modeling approach that separated the hazard of discontinuation from the hazard of the administrative endpoint. The outcome of interest was actually medication possession ratio over the first six months, which I modeled with a linear mixed model with random slopes for each patient. The administrative censoring was handled by treating days 90-180 as a separate follow-up period with a different risk set. The analysis took about twelve hours to run because the joint model required numerical integration, but the alternative was either ignoring the censoring mechanism or dropping half the dataset. I documented the method in a one-page protocol that the quality committee approved before we presented results to the therapeutics committee. The workaround taught me something useful: administrative censoring is more common in pharmacy data than people admit. Insurance coverage limits, formulary switches, prior authorization requirements, and pharmacy contract changes all create artificial endpoints that look like clinical decisions. If you don't model them separately, your hazard ratios are biased toward the null. I now run a quick check on the censoring distribution before any survival analysis. If there's a sharp peak at a specific time point, that's your administrative signal and you need a different approach.
Common Pitfalls That Waste Time And Money
P-hacking is the most obvious problem but it's not the most damaging in pharmacy settings. The worse issue is what I call assumption dressing. You run a test, the assumptions are violated, and instead of switching methods you just report the p-value anyway and describe the model as if it were valid. A logistic regression with complete separation gives you infinite coefficients. A Cox model with non-proportional hazards gives you a single hazard ratio that means nothing. A linear model with heteroscedastic residuals gives you confidence intervals that are too narrow. I've reviewed grant proposals and internal reports where these issues went completely unaddressed because the analyst didn't know what diagnostic plots to check. Another problem is small-sample bias in pharmacoepidemiology. When you're studying rare adverse events or specialized patient populations, you might have fewer than fifty events. Traditional asymptotic methods break down here. Exact logistic regression or Firth penalized likelihood estimation handles this much better. I learned this the hard way when analyzing antibiotic-associated diarrhea rates in a neonatal unit. The standard model produced an odds ratio of twelve with a confidence interval from 1.4 to one hundred four. After applying Firth correction, the estimate dropped to six with a much more reasonable interval from 2.1 to 17.3. Both were statistically significant, but the clinical interpretation was very different. Missing data is the third major issue. Pharmacy datasets routinely have twenty to forty percent missingness on key variables like BMI, lab values, or insurance status. People handle this by listwise deletion, which removes entire records with any missing values. If data are missing completely at random, this works fine. If data are missing at random or not at random, you're introducing selection bias. Multiple imputation is the standard solution, but it requires your imputation model to include all variables that predict missingness and all variables in your analysis model. I use the mice package in R with predictive mean matching for continuous variables and logistic regression for binary ones. Five imputed datasets usually stabilizes the estimates without adding too much computational overhead.
Software Choices For Actual Pharmacy Work
R is the default choice for anyone doing serious biostatistics. The ecosystem for survival analysis with timvary packages, mixed models with lme4 and nlme, and meta-analysis with metafor is genuinely unmatched. The learning curve is steep if you've only used SPSS or SAS, but the flexibility pays off quickly. Python is catching up, especially for people who want to chain statistical analysis with data engineering workflows. For hospital pharmacy departments that need reproducibility and audit trails, SAS still has institutional momentum, though license costs are real. For routine pharmacy analytics that don't require custom modeling, Excel is surprisingly capable if you use it correctly. The Analysis ToolPak handles basic regression and ANOVA. But Excel will silently give you wrong results if your data isn't formatted properly. Decimal separators, date formats, and hidden rows can all corrupt an analysis without any warning. I won't sign off on an Excel-based statistical report unless I can verify the underlying formulas against an independent calculation. Here's a practical workflow I recommend for pharmacy teams starting with biostatistics. First, document your data dictionary with variable types and expected ranges before touching any analysis. Second, run exploratory analysis on a sample of five hundred records to understand distributions and spot coding errors. Third, write your analysis plan including the primary statistical method, secondary sensitivity analyses, and handling of missing data before looking at the results. Fourth, code the analysis in a script rather than point-and-click software so it's reproducible. Fifth, have someone who didn't write the code review it for logic errors. This process takes about two weeks for a straightforward study but prevents the kind of retraction-worthy mistakes I've seen in pharmacy literature.
When Biostatistics Won't Help You
No statistical method fixes bad data collection. If your prescription fill dates are recorded as the date the order was placed rather than the date the patient picked up the medication, your time-to-adherence analysis is fundamentally flawed regardless of what model you use. If your adverse event reporting is voluntary and incomplete, your signal detection will miss real safety concerns. Statistical rigor amplifies good data and exaggerates bad data equally. Before investing in advanced analytics, invest in data quality. A clean dataset analyzed with simple methods beats a messy dataset analyzed with sophisticated techniques every time. Some questions in pharmacy simply aren't answerable with statistics alone. Drug-drug interaction mechanisms require pharmacological investigation. Patient adherence barriers require qualitative research. Health system formulary decisions require economic and operational analysis alongside statistical evidence. I've watched colleagues try to force a single statistical model to answer multidimensional problems. The results are technically correct and practically useless because the model wasn't designed for the question being asked.
Getting Started Without Overcomplicating Things
If you're a pharmacist or pharmacy student wanting to apply biostatistics practically, start with one concrete question from your own work environment. Maybe it's whether a medication therapy management program improved blood pressure control. Maybe it's whether a staffing change reduced prescription error rates. Define the outcome clearly, identify your data sources, and choose the simplest method that fits your data structure. Don't reach for survival analysis when a chi-square test answers your question. Don't build a multilevel model when a fixed-effects regression is sufficient. The biostatistics application in pharmacy space has real constraints: small sample sizes, messy data, administrative censoring, and institutions that treat statistical rigor as optional. But the practitioners who learn to navigate these constraints produce work that actually influences patient care. A well-designed prospective cohort study with proper confounding adjustment is worth more than fifty post-hoc subgroup analyses of a poorly conducted trial. Start where you are, use the tools you have, and document every assumption you make. The statistics will be honest about what your data can and cannot support if you give them the chance.



