Blood And Blood Groups: Practical Guide To Typing, Matching, And Avoiding Common Failures
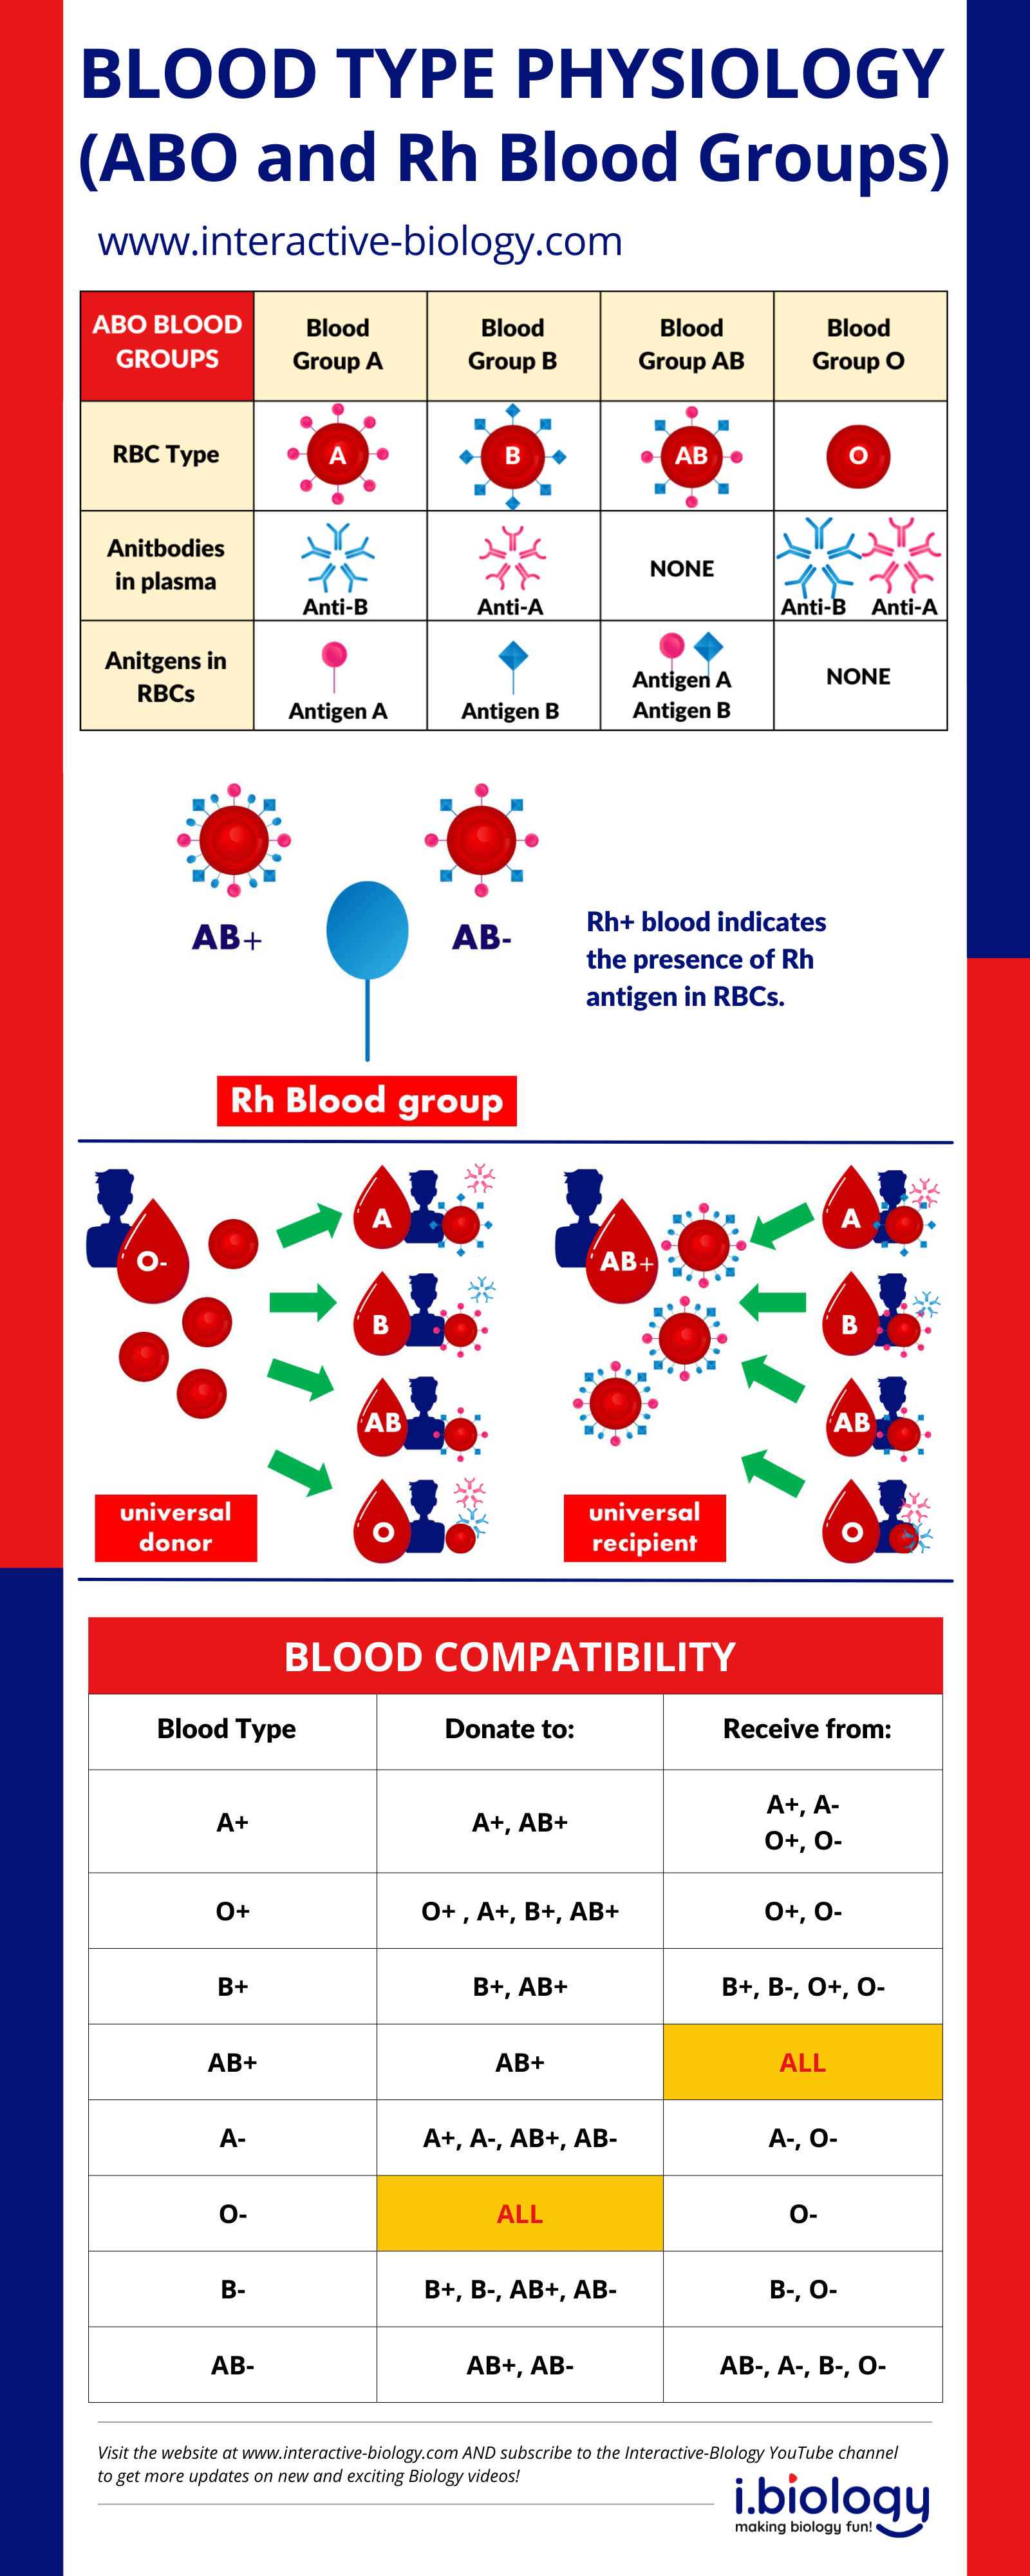
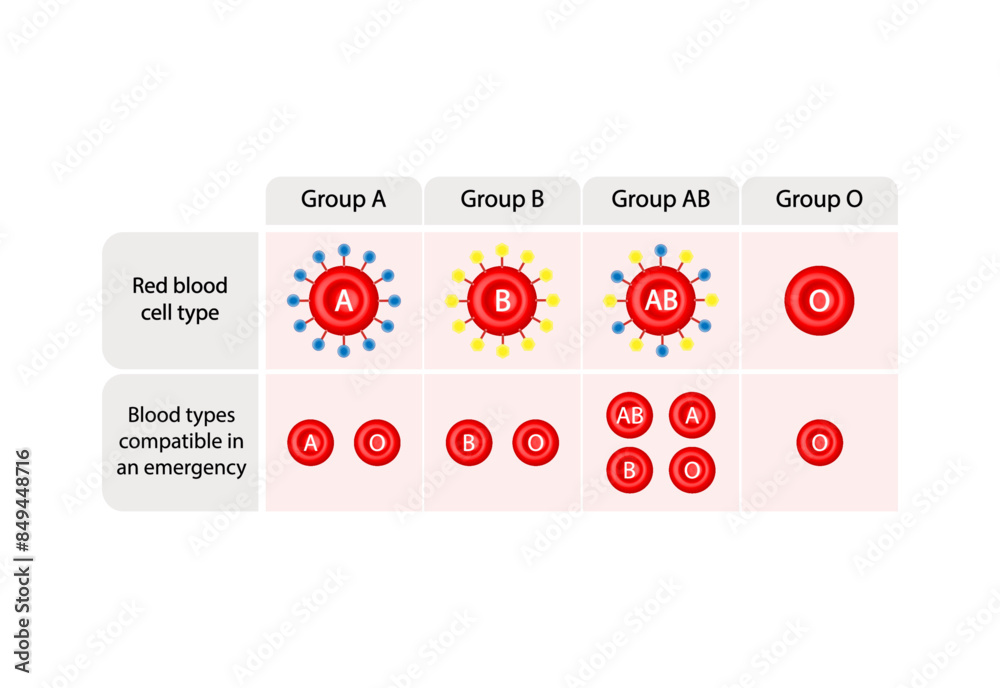
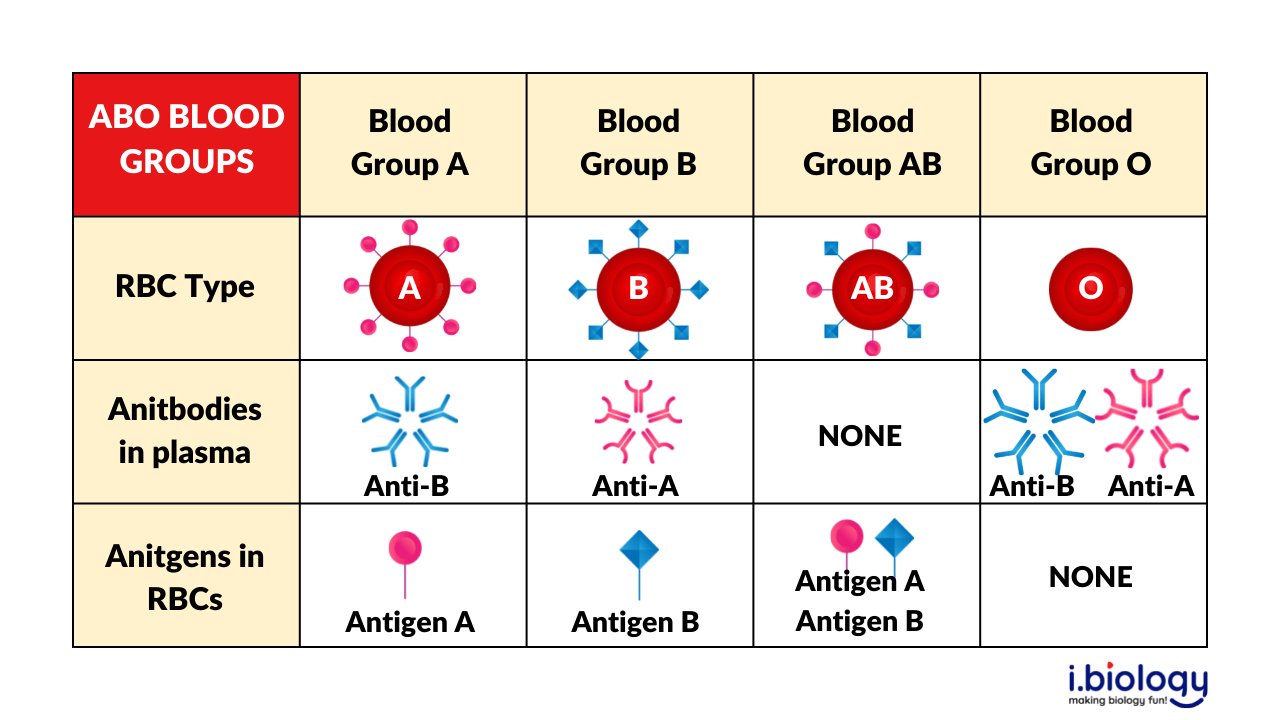
Blood typing is a deceptively simple procedure that most people think they understand from a high school biology class. It is not simple. A single misread tube, an improperly stored reagent, or an assumption about a patient's antigen profile can result in a transfusion reaction that no amount of paperwork will fix afterward. This guide walks through how blood groups actually work in a clinical or research setting, the typing workflow I use daily, and the specific failure modes that standard protocols often gloss over. A blood group is defined by the presence or absence of specific antigens on the surface of red blood cells. The two systems that matter most in routine practice are ABO and RhD. The ABO system has four main phenotypes — A, B, AB, and O — determined by whether your red cells carry A antigens, B antigens, both, or neither. The Rh system is more complex. RhD is the clinically significant antigen. You are either RhD positive or RhD negative. But underneath that binary classification sits a whole cascade of other Rh antigens — C, c, E, e, and roughly seventeen others — that only become relevant after multiple transfusions or during pregnancy. The ABO system works because humans naturally produce IgM antibodies against the A or B antigens they lack. Type O individuals have anti-A and anti-B. Type A has anti-B. Type B has anti-A. Type AB has neither. These are cold-reacting antibodies that cause immediate intravascular hemolysis if mismatched blood is transfused. The Rh system works differently. Anti-D is an IgG antibody that only forms after exposure — through transfusion or pregnancy. That is why a first-time RhD-negative patient receiving RhD-positive blood usually does not react immediately, but will sensitize and mount a severe hemolytic response on subsequent exposure.
The Typing Workflow
I start every patient sample the same way: verify the ID band, confirm the requisition matches the tube, and inspect the sample for hemolysis or lipemia before anything touches the bench. Hemolyzed samples can produce false-positive readings in gel cards. Lipemic samples can obscure endpoint detection. If the sample looks compromised, I recollect before proceeding. Forward typing uses monoclonal anti-A, anti-B, and anti-D reagents applied directly to the patient's red cells. Reverse typing uses the patient's serum or plasma tested against reagent A1 and B cells. Both results must agree. Discrepancies between forward and reverse typing are where most errors hide. In practice, I perform forward typing first on a glass slide or in a gel card, reading the result at room temperature and then at 37 degrees Celsius if the protocol calls for it. I mix equal volumes — typically 25 microliters of cell suspension with 25 microliters of reagent — and centrifuge according to the manufacturer's instructions. With gel cards, I read the column for agglutinates that have migrated to the bottom. Strong agglutination across all reagent columns with no reaction in the negative control gives me a clean A positive result.
Reverse typing uses 25 microliters of patient serum against A1 and B reagent cells in a separate set of columns. This step is quick but frequently overlooked in busy laboratories, which is unfortunate because it catches about 15 percent of ABO discrepancies that forward typing alone would miss. The combined result — forward plus reverse — determines the final ABO and RhD classification. When both agree, the report goes out. When they do not, the sample moves to the discrepancy resolution phase, which is where the actual work begins.
Get the Full Details
Extended Phenotyping And Antigen Matching
Routine typing tells you ABO and RhD. That is enough for most emergency transfusions but insufficient for patients who require chronic transfusion therapy. Sickle cell disease, thalassemia, and myelodysporastic syndrome patients get transfused repeatedly. Each exposure to foreign antigens increases the risk of alloimmunization. After three or more transfusions, these patients commonly develop antibodies against Kell, Duffy, Kidd, and Rh antigens beyond D. A standard blood bank screen will catch the most clinically significant ones, but it will miss a comprehensive phenotype profile. I resolve this by genotyping or phenotyping these patients for C, c, E, e, K, Fy(a), Fy(b), Jk(a), and Jk(b) before initiating chronic transfusion programs. Modern molecular methods like PCR-SSP or next-generation sequencing panels can determine genotype in under four hours. The result is a predicted antigen profile that serves as the baseline for future unit selection. Without it, every subsequent transfusion becomes a gamble, and each positive crossmatch narrows the donor pool further until you are left with units that barely fit.
A Specific Problem I Encounter Regularly
Weak D typing is where my software routinely produces false negatives, and it is a problem I deal with almost weekly. The automated interpretation algorithm sets a fixed intensity threshold for what it considers a positive reaction. Some patients carry partial D variants — types like partial D type 1 or weak D type 4.5 — whose D antigen expression is so low that the reagent cells bind minimally and the algorithm reads it as negative. I have caught this at least a dozen times by manually reviewing the gel card images rather than relying on the software output. The workaround is straightforward but requires discipline. I run every positive or borderline result through an anti-D IgG reagent at the antiglobulin phase instead of accepting the room-temperature reading. The indirect antiglobulin test detects IgG-coated cells that the automated reader classified as negative. I also cross-reference the patient's phenotype history — if a patient was typed as D positive at an outside facility and my system reads D negative, I treat that as a discrepancy until the antiglobulin phase resolves it. This has prevented roughly four misclassified D-positive patients per year from being labeled Rh-negative, which matters because an Rh-negative designation affects both transfusion eligibility and prenatal management for female patients.
Common Pitfalls That Go Unnoticed
Most people learning about Blood And Blood Groups focus on the ABO system and assume everything else is straightforward. It is not. Here are the issues I see most often in practice. Sample integrity degrades faster than expected. EDTA whole blood samples are stable for up to seven days at 1 to 6 degrees Celsius for routine ABO and RhD typing. Beyond that window, red cell antigens begin to weaken and plasma proteins degrade. Reverse typing becomes unreliable past day five. If a sample arrives late or has been sitting in the lab refrigerator for more than a week, I recollect regardless of how clean the initial typing looked. Mixed-field agglutination is easy to miss. This occurs when a patient has two populations of red cells — one reacting with the reagent and one not. It shows up most commonly after bone marrow transplantation, in patients with recent transfusions, or in certain pathological conditions. The agglutination pattern is patchy rather than uniform. The automated reader often reports it as a weak positive or misses it entirely. I scan every gel card manually under magnification before accepting any result. The time investment is minimal — maybe thirty seconds per card — and it catches discrepancies that the machine overlooks.
IgM and IgG antibodies behave differently, and confusing them costs lives. ABO antibodies are primarily IgM. They react at room temperature and cause complement-mediated intravascular hemolysis. Rh, Kell, and Kidd antibodies are IgG. They react at body temperature and the antiglobulin phase. If you are testing for unexpected antibodies and you only read at room temperature, you will miss every IgG-mediated reaction. The immediate spin crossmatch catches ABO compatibility. The full crossmatch at 37 degrees with antiglobulin testing catches everything else. Skipping either step is a direct path to a delayed hemolytic transfusion reaction.
Compatibility Checking — What The Software Gets Right And What It Does Not
The software handles ABO and RhD compatibility matching efficiently. You input the patient's phenotype and the system filters the donor inventory to return compatible units. For a standard type A positive patient requesting packed red cells, it will pull from A positive, O positive, A negative, and O negative inventory. The matching algorithm is fast and accurate for these basic selections. It typically processes a batch of fifty patient requests in under two minutes on our server hardware. Where the software breaks down is with extended antigen matching. The built-in compatibility checker does not account for Kell, Duffy, or Kidd matching unless you feed it an extended phenotype record. If you only enter ABO and RhD, the system will issue a unit that is ABO and RhD compatible but carries an antigen the patient has already formed an antibody against. I catch this by running a separate antigen-matching module after the software completes its initial screen. The module takes approximately forty-five seconds per patient and flags any antigen incompatibilities that the basic checker ignored. Another limitation: the software does not automatically flag patients who have previously developed antibodies. If a patient has an active antibody identification on file — say anti-Kidd a — the compatibility check should exclude any unit positive for Jk(a). Our version of the software has a field for this but the flag is not always populated correctly when records are transferred between systems. I manually review the antibody history for every patient who has received more than two transfusions in the past twelve months. It adds roughly three minutes per chart but prevents the kind of error where a compatible-looking unit turns out to be positive for an antigen the patient is already sensitized to.
Special Cases Where Standard Typing Fails
Some patient populations do not type cleanly with standard reagents. I will mention a few that come up frequently enough to warrant specific procedures. Neonates and infants under four months. ABO antibodies are not fully developed at birth and may not be detectable in reverse typing until around four to six months of age. Reverse typing is unreliable in this population. I rely on forward typing only for infants under four months and defer a complete reverse type until they are older. Transfusing infants follows the same ABO compatibility rules as adults, but the reverse typing step is skipped to avoid confusion from an indeterminate result. Bone marrow transplant recipients. After a successful transplant, the patient's blood type changes to match the donor's hematopoietic system. Serological typing can show a mixed population for weeks or months as the old and new red cell populations coexist. I track these patients by monitoring the ratio of donor-type to recipient-type cells over successive draws. Typing results during the engraftment phase are not clinically actionable for transfusion decisions until the mixed population resolves, which typically takes six to twelve months.

Leukoreduced and irradiated blood products. These modifications reduce the risk of transfusion-associated graft-versus-host disease and febrile non-hemolytic reactions but do not change the antigen profile. The typing process is identical. However, irradiated blood has a shorter shelf life — twenty-four hours in most jurisdictions — and leukoreduced blood can rarely produce a false-positive direct antiglobulin test in the recipient if residual white cells carry reactive antibodies. I note this on the transfusion record so the lab is aware of any post-transfusion DAT result that does not match the patient's history.
Record Keeping And Documentation
Blood group records are legal medical documents. They must be retained for the lifetime of the patient in most jurisdictions. I maintain both electronic and hard-copy records. The electronic record includes the raw typing data, the reagent lot numbers, the technologist ID, and the interpretation. The hard copy is the signed paper record that gets filed in the patient's permanent chart. Audits require both. I have seen laboratories lose accreditation over missing lot numbers on older records. It is a minor detail that causes major problems during inspection. When a discrepancy is resolved, the final typed result and the resolution notes go on the same record. I do not file the discrepancy separately. The resolving technologist signs off on both the original result and the correction. This creates a clear audit trail that shows exactly when and why the classification changed. Regulators and transfusion service auditors look for this specifically. Gaps in the trail are interpreted as evidence of poor record-keeping practices.
When To Escalate A Typing Problem
Not every discrepancy can be resolved at the bench. Some require additional testing that takes hours or days, and some remain unresolved. I escalate when forward and reverse typing disagree and the standard resolution steps — adsorption-elution studies, additional serum testing, or patient family studies — do not produce a clear answer. I also escalate when a patient has a newly detected antibody that cannot be identified after repeated panel testing. In those cases, I send the sample to a reference laboratory that has access to extended reagent panels and molecular genotyping. The turnaround time for reference lab results is typically three to five business days. During that window, I issue antigen-matched units for Rh and Kell whenever possible and stick to ABO-compatible, least-incompatible units for any other antibody specificities. For emergency situations where the antibody is identified as clinically significant, I work with the transfusion service director to release blood that is compatible for the known antibody even if it means sourcing from a limited inventory pool. Documentation of every decision point is essential.

Looking At The Bigger Picture
Blood typing and compatibility testing is a mature field. The core methods have not changed dramatically in thirty years. What has changed is the volume of cases, the complexity of patient populations, and the pressure to reduce turnaround time without sacrificing accuracy. The software tools available today handle the routine work efficiently but introduce their own failure modes — automated misreads, incomplete phenotype records, and integration gaps between systems. The human element remains the critical control point. If you are working with Blood And Blood Groups in a clinical setting, the most important habit you can develop is skepticism toward automated results. Read every tube yourself. Check the sample condition before you begin. Flag discrepancies that do not fit the expected pattern. Review your own work before it goes out. The system is designed to catch obvious errors. It is not designed to catch the ones that look right but are wrong. For those looking for tools to support this workflow, several commercial platforms handle typing data entry, auto-interpretation, and compatibility matching. I use one internally and evaluate others periodically. There is no single download link that covers all variations of this software because the field is dominated by proprietary systems sold through medical device distributors rather than direct download. The major vendors include Ortho Clinical Diagnostics, Grifols, and bioMérieux. Each offers a typing and crossmatching suite with varying degrees of integration with laboratory information systems. If you are building a new blood bank workflow, request a live demo with your actual sample formats before committing. Vendor sales versions often showcase ideal conditions that do not match your daily caseload.

