What Every Phlebotomist Needs to Know About Tube Colors
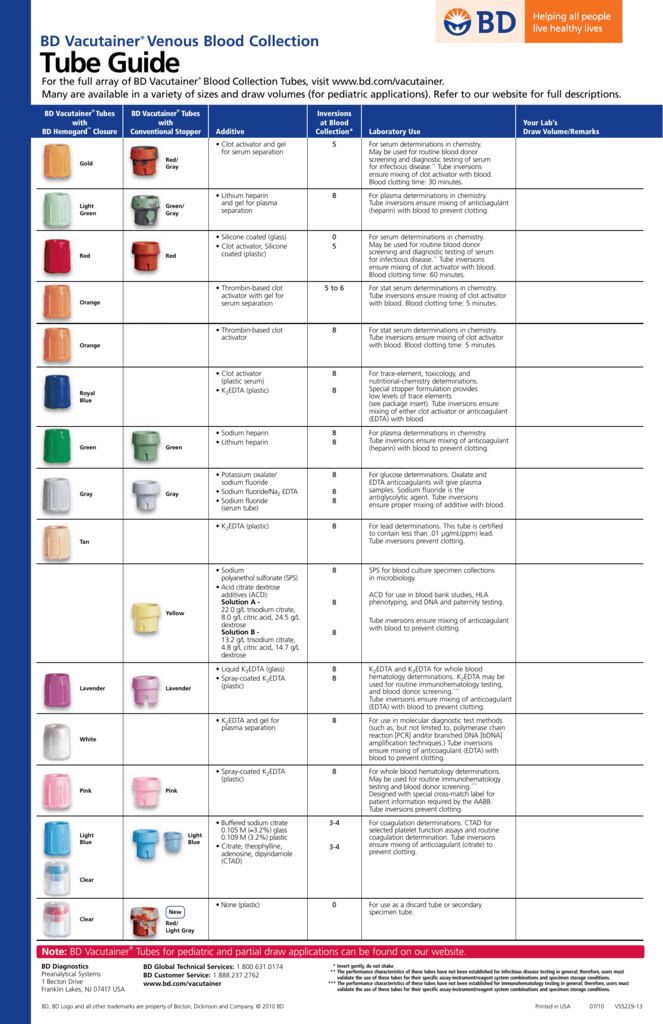
When you walk into a lab or clinic, the ordering of draw tubes isn't arbitrary. The cap color tells you what's inside, what additive is in there, and how many inversions it needs after you pull blood. Get it wrong once and you've got a hemolyzed sample, a coagulation test that comes back garbage, or a chemistry panel that looks like it came from a different patient. The Blood Collection Tubes Color Guide exists to keep that from happening, but the real problem isn't memorizing colors — it's understanding why each one behaves the way it does when it hits the patient's blood. I worked in a high-volume outpatient lab for years, and the most common mistake I saw wasn't picking the wrong tube. It was picking the right tube but handling it wrong. You can have a perfect lavender top tube and still ruin the sample if you're shaking it instead of gently inverting it. That said, knowing which color corresponds to which additive is the foundation, so let me lay that out first before we get into the stuff that actually trips people up on the job.
Top Tube Colors and What They Actually Contain
Here's the breakdown of the most common tubes you'll encounter, ordered roughly by how frequently they show up in a standard draw. Red top tubes. These are plain glass or plastic tubes with no additive. The blood clots on its own, and you spin it down to get serum. Used for immunology, serology, and most chemistry panels. Some red-top tubes have a silica coating inside to accelerate clotting — those are the ones with the speckled red or light red caps. If your protocol calls for a serum separator tube, that's a different animal entirely. Tiger top / Gold top tubes (SST). This is a serum separator tube with a clot activator and a gel barrier. The gel sits at the bottom of the tube, and after centrifugation it forms a physical barrier between the clot and the serum. This is the standard tube for most metabolic panels and liver function tests. One thing people get wrong: these tubes still need 5 minutes of clot time before you spin them. People see the gel and think "faster," but spinning before the clot forms gives you a fibrin strand mess that clogs analyzers and gets samples rejected. Wait the full five minutes. It takes three seconds longer and saves you a redraw.
Lavender top tubes. Contains EDTA (ethylenediaminetetraacetic acid) as the anticoagulant. This chelates calcium and prevents clotting. Used for CBCs, blood banking, and molecular testing. EDTA is very effective, which is also its problem — it's so good at binding metals that it can interfere with certain trace element tests and some chemistry assays. If you're drawing a tube for lead levels, don't use a lavender top. Use a heparinized tube instead. Light blue top tubes. This is the one that requires the most precision. Sodium citrate is the anticoagulant here, and it works by reversible calcium binding. The critical detail that nobody bothers teaching properly: the fill volume matters. The tube has a specific citrate-to-blood ratio, and if you underfill it by even a few tenths of a milliliter, the coagulation results are going to be garbage. Prolonged PT and aPTT values that make no clinical sense usually trace back to an underfilled light blue. Always fill this tube to the line, and draw it first if you're doing a coagulation panel. The rule about drawing light blue first exists because a micro-clot from a previous tube draw contaminates the sample. Green top tubes. Heparin-based anticoagulants. Lithium heparin for chemistry, sodium heparin for stat electrolytes and blood gases. Heparin doesn't interfere with most enzymatic reactions the way EDTA does, which is why chemistry panels sometimes use green tops instead of red or gold. But here's the catch — heparinized plasma is not suitable for hematology. You'll get distorted cell morphology under the microscope. Don't swap green for lavender on a CBC and then wonder why the differential looks wrong.
Get the Full Details

Gray top tubes. Sodium fluoride and potassium oxalate. Fluoride is a glycolytic inhibitor — it stops glucose from breaking down after the blood is drawn. Potassium oxalate prevents clotting. This tube is specifically for glucose and alcohol testing. If you don't use a gray top for a glucose test, the glucose value will drop by about 5-10% per hour at room temperature because the cells keep metabolizing. That's not a theory. I've seen diabetic patients misclassified because their fasting glucose was drawn into a plain red tube and sat on the cart for 40 minutes before spinning.
Yellow Tops and the Tubes You'll See Less Often
Yellow top tubes. These contain ACD (acid citrate dextrose) solution. Originally designed for blood bank and HLA testing, but they're also used for HIV PCR and DNA studies. The ACD formulation preserves viable lymphocytes better than EDTA. Not something you'll draw daily unless you're in a specialized lab. Royal blue top tubes. Trace element tubes. These are specially manufactured to have ultra-low levels of contaminants. If you're testing for lead, zinc, copper, or other trace minerals, regular tubes can leach enough metal from the glass or rubber stopper to skew results. Royal blue costs more and isn't always in stock, so plan ahead. Pink top tubes. These are essentially lavender tubes but made for immunohematology use. The EDTA concentration is calibrated for blood typing and crossmatching. Most labs just use lavender for everything, but if you're drawing for a direct antiglobulin test or antibody identification, pink is the specified tube.
A Real Problem I Ran Into and How I Fixed It
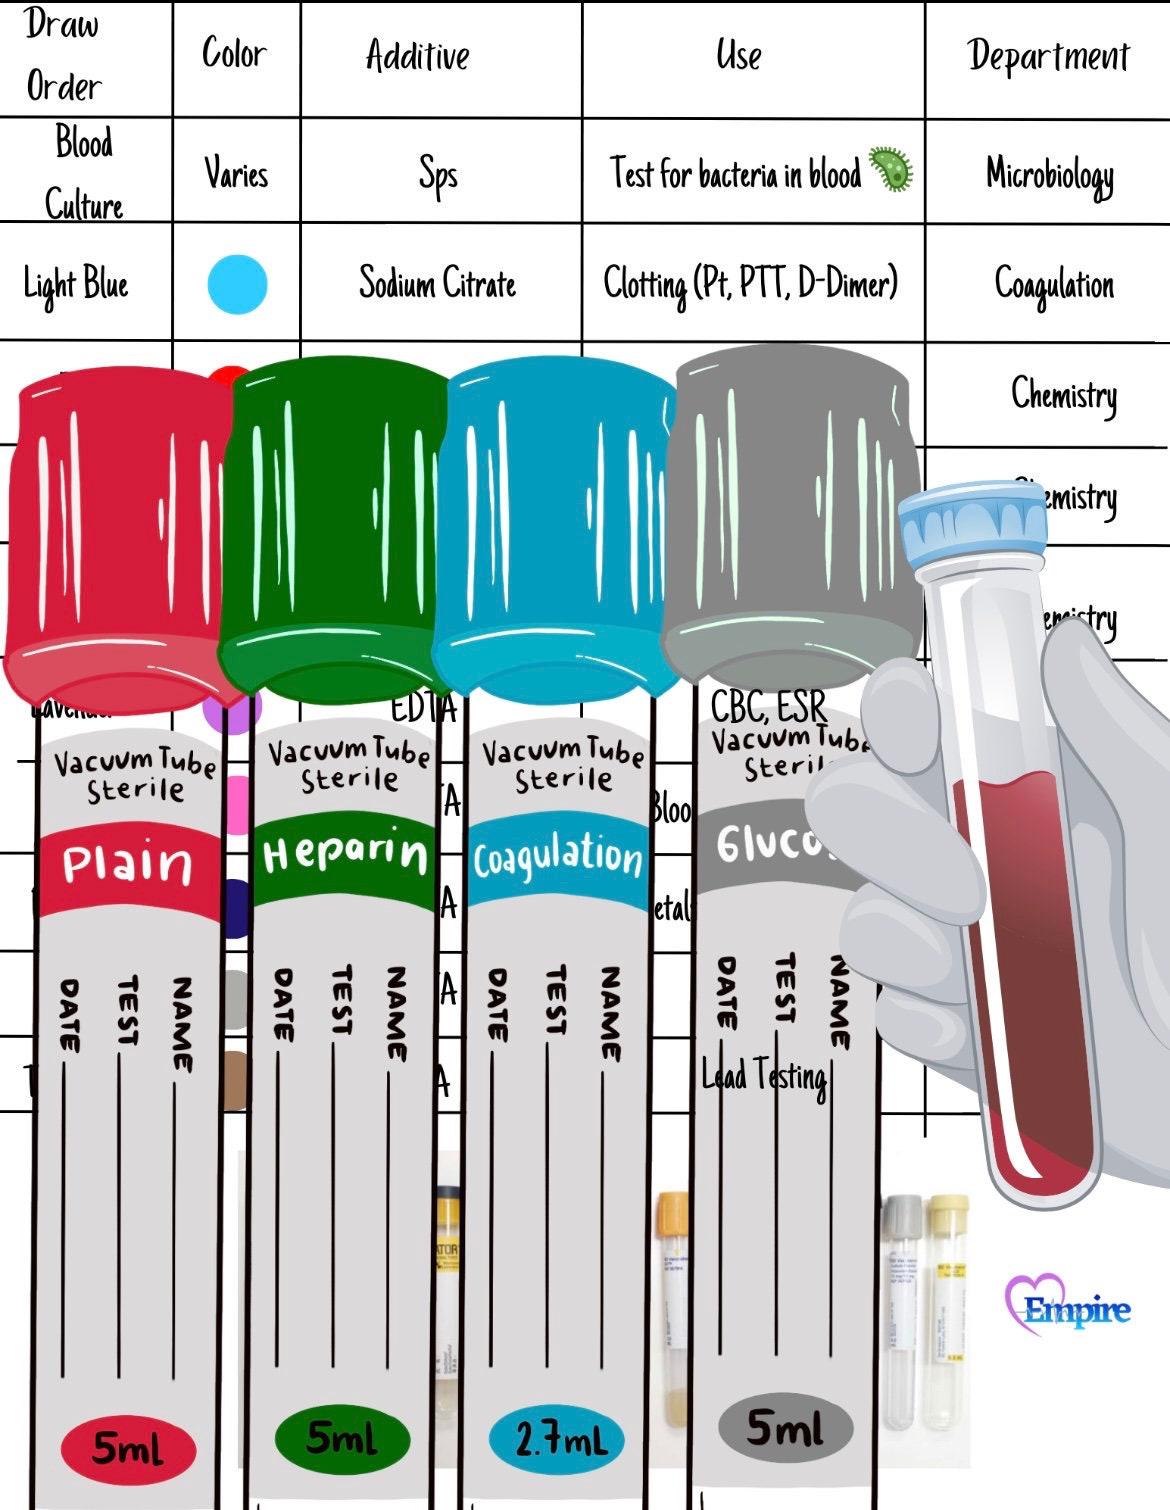
There was a stretch of time where our lab kept getting flagged for elevated potassium results that didn't match clinical pictures. Patients showed up with normal EKGs and normal symptoms but potassium readings in the 6.0 range. We ruled out hemolysis, renal failure, and lab error. Eventually we traced it back to the draw sequence. The phlebotomist on rotation was pulling a green-top heparin tube after a lavender-top EDTA tube using the same needle. A tiny amount of EDTA was carrying over into the green top, and EDTA-contaminated heparinized plasma gives falsely elevated potassium readings on some analyzers. The fix was straightforward — draw the light blue or green top before the lavender, or change the needle between tubes. But the root cause was a gap in training that nobody had bothered to close. This is the kind of thing that doesn't show up in a color chart. It shows up when your results don't make sense and you've already rejected the obvious explanations. The most counter-intuitive thing about blood collection tubes is that the color means less than you'd think in certain situations. Two different manufacturers might use the same cap color but have slightly different additive concentrations. A BD Vacutainer green top and a Greiner green top both say heparin, but the exact heparin concentration and tube wall treatment can vary. For most routine testing this doesn't matter. For specialized assays — things like therapeutic drug monitoring or toxicology — the manufacturer specification matters, and you should be checking the package insert rather than relying on cap color alone. Another thing the charts don't cover: tube fill order matters beyond just "blue first." The Clinical and Laboratory Standards Institute recommends this draw sequence: blood cultures, light blue, red or gold, green, lavender, gray. Deviating from this order introduces the risk of carryover between tubes. A tiny volume of EDTA from a lavender tube carried into a subsequent light blue tube by an unflushed needle will lengthen clotting times and invalidate coagulation results. It's not dramatic — it's milliliters of carryover — but the analytical impact is significant.
The biggest limitation of relying on the color guide alone is that it doesn't account for pediatric draws. In pediatric patients, you're often working with total volumes in the 2 to 3 milliliter range, and standard adult tubes simply cannot be filled correctly. You need pediatric-size tubes with proportionally smaller additive amounts. Using a full-size lavender tube and getting only 0.8 ml of blood means the citrate-to-blood ratio is completely wrong, the EDTA concentration is too high relative to the blood volume, and the sample is unusable. The color doesn't change, but the tube chemistry does, and the color guide won't tell you that. Similarly, if you're drawing from a patient with poor venous access and you're pulling back hard on the plunger of a syringe before transferring to tubes, you're introducing shear stress that causes hemolysis regardless of which tube color you're using. Hemolysis invalidates potassium, LDH, iron, and many other assays. No amount of color knowledge fixes that. Needle gauge, vacuum strength, and draw technique matter more than the cap.
Quick Reference Summary
If you need a fast lookup while you're actually at the patient's side, here's the core mapping without the commentary: Red — no additive, serum for chemistry/serology Gold / Tiger — serum separator with clot activator and gel
Lavender — EDTA, hematology and blood banking Light blue — sodium citrate, coagulation studies Green — heparin, chemistry and stat tests
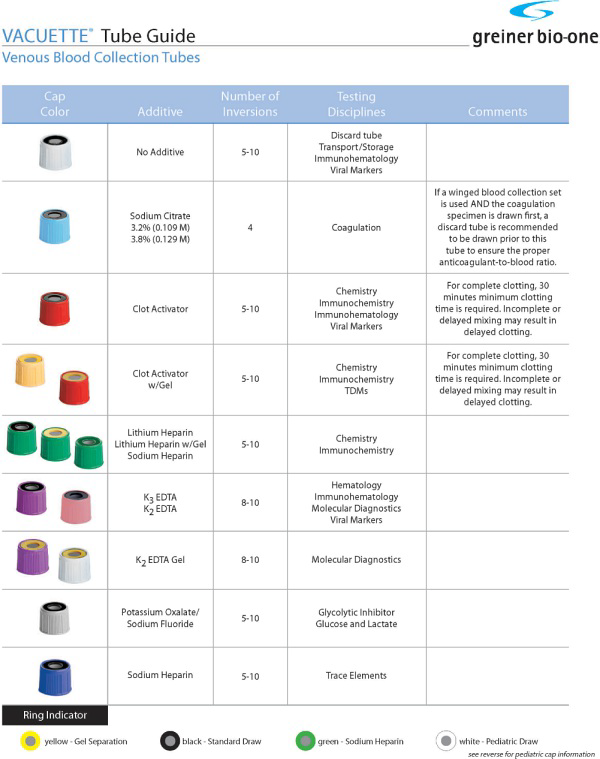
Gray — fluoride/oxalate, glucose and alcohol Yellow — ACD, DNA and blood bank specialty Royal blue — trace element testing
Pink — EDTA, immunohematology The complete Blood Collection Tubes Color Guide as published by the CLSI covers additional specialty tubes like the orange-top rapid serum tube and the brown top for lead testing, but the ones above account for roughly 95% of what you'll encounter in general practice. Anything beyond that you're probably in a reference lab or a specialized outpatient center, and you should already know what you're doing at that point.
Why This Matters Beyond the Draw Room
Bad tube selection doesn't just waste a needle stick. Rejected samples delay diagnoses. A coagulation sample drawn incorrectly might mean a patient on warfarin goes days without a valid INR check. A glucose sample drawn into the wrong tube could mean a hypoglycemic episode goes uncaught. The tubes themselves are cheap. The consequences of getting them wrong are what add up. I've seen entire lab rejection reports run 30% or higher on shift changes when new staff rotate through without proper tube training. The numbers go down fast once someone spends twenty minutes walking them through the order of draw and the inversion counts. Most of the errors aren't about color confusion. They're about people treating the tubes as interchangeable containers instead of purpose-built collection vessels with specific chemistry requirements. Keep this guide somewhere you can actually reach it while you're working. Not printed on a wall behind glass where you have to take off your gloves to read it. Laminated and within arm's reach at the supply station. Because the moment you realize you need it is usually the moment you're already holding two tubes and trying to remember whether the green one is serum separator or heparin.