Starting With The Gear, Not The Theory
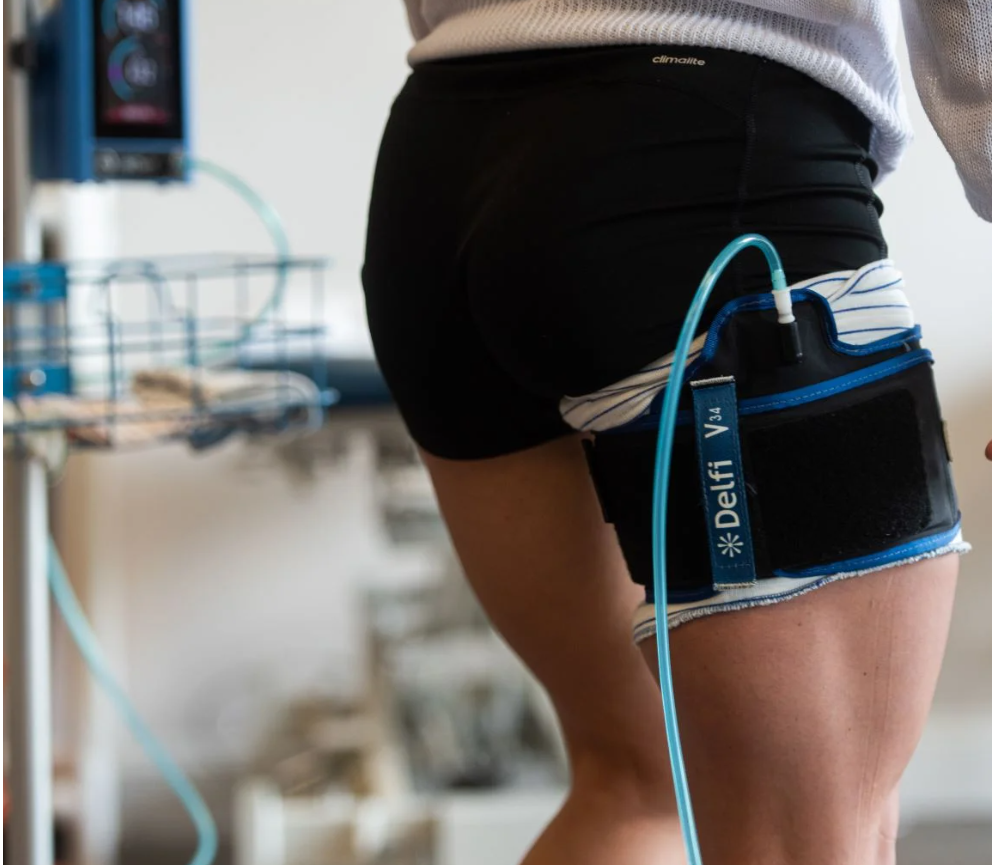
The biggest mistake I see with Blood Flow Restriction Therapy At Home is people buying cheap elastic wrap bands from Amazon and cranking them down until their limb goes numb. That is not how this works. You need a specialized BFR cuff system with a pressure gauge, and you need to determine your Limb Occlusion Pressure first. Without that number, you are guessing, and guessing with BFR is how you end up with a hematoma or nerve damage instead of gains. I spent years watching physical therapists struggle with this at home because most commercial kits don't explain the LOPE calculation clearly. Here is the actual process. You attach the cuff to your arm or leg, inflate it slowly while listening with a Doppler ultrasound device on the pulse point past the cuff. The pressure at which the pulse disappears is your LOP. For arms, you typically work at 50 to 80 percent of LOP. For legs, 80 to 100 percent of LOP. That is it. That is the entire protocol at its core.
Blood Flow Restriction Therapy At Home: What It Actually Does
When you apply partial arterial occlusion during light exercise, you trap metabolites in the muscle tissue. The accumulation of hydrogen ions, lactate, and inorganic phosphate creates a hypoxic environment that forces fast-twitch fiber recruitment at very low loads. A 20 percent one-rep max can trigger the same hormonal and cellular response as an 80 percent one-rep max if the flow restriction is dialed in correctly. This is why post-surgical rehab patients can maintain muscle mass with walking instead of heavy squats. It sounds too good to be true until you see the data. The mechanism involves venous blood leaving the limb through larger veins that remain collapsible under moderate pressure, while arterial blood continues entering through smaller, more rigid arteries. The capillary bed becomes engorged. Type IIx fibers that normally only fire under heavy loading get recruited anyway because the metabolic stress is artificially elevated. The liver senses the chemical change and releases more growth hormone. It is not magic, it is just physiology applied in a way most people never encounter outside a research lab. I learned this the hard way during my second year of studying rehab protocols. I had a patient who was three months post-ACL reconstruction and still atrophying despite compliance with standard PT. We introduced BFR at 80 percent LOP using ankle cuffs and straight-leg raises at basically zero resistance. Within six weeks, quadriceps cross-sectional area increased measurably on ultrasound. The key detail everyone misses is that the exercise intensity must stay genuinely low. If you push the reps too hard or add too much external load while restricted, you shift from metabolic stress into actual vascular trauma. The line is thinner than it looks.
Setting Up A Safe Protocol
Buy a pneumatic cuff system with a digital pressure controller and a Doppler device. Inflatable tourniquet-style bands for legs cost between 150 and 400 dollars depending on whether they are single-limb or dual-limb units. Arm cuffs run less, but the principle is identical. Do not use a manual blood pressure cuff unless you have experience reading those dials and can estimate LOP without a Doppler. I tried this once with a standard sphygmomanometer on my bicep and overshoot by about 40 millimeters of mercury because I could not hear the Korotkoff sounds clearly through the thick occlusion band. That is 40 millimeters of mercury too much pressure against my brachial artery for twenty minutes. Not worth the risk. The standard protocol for legs is four sets of thirty reps, then fifteen, fifteen, fifteen with ten seconds of rest between sets. The cuff stays inflated the entire time. For arms, you can do three sets of thirty at 50 percent LOP or three sets of fifteen at 80 percent LOP. Both approaches work. The lower pressure higher rep scheme feels less uncomfortable but takes longer. The higher pressure lower rep scheme is faster and still effective, but it burns like hell after the first set because you are pushing closer to occlusion threshold. Common exercises include squats, lunges, knee extensions, calf raises for the lower body and wall presses, lateral raises, and tricep extensions for the upper body. Anything that moves a joint through a reasonable range of motion is fine. You do not need machines. The restriction does the heavy lifting in terms of fiber recruitment. Your job is just to move slowly and control the eccentric phase.
Get the Full Details

Problems You Will Actually Encounter
The most annoying issue is cuff migration during exercise. I discovered this when doing BFR lunges at home. The cuff would slide up my thigh with every rep because the elastic tension from my quad contraction pushed it toward the hip. My workaround was wrapping a layer of conforming cohesive bandage beneath the cuff to create a friction anchor point. It added about thirty seconds to setup but eliminated the migration entirely. Without that, you lose pressure consistency between reps and the whole protocol becomes unreliable. Another problem is the skin irritation from prolonged occlusion. After repeated sessions, the areas where the cuff edges sit can develop contact dermatitis from the combination of pressure, sweat, and fabric friction. Switching to cuffs with wider contact surfaces distributed pressure more evenly and the irritation stopped within two weeks. Narrow cuffs concentrate stress along a smaller perimeter and make the skin react. Some people experience mild paresthesia during or after sessions, usually described as pins and needles in the distal limb. This happens when the pressure is slightly too high or when the session runs longer than twenty minutes of total inflation time. If this occurs, drop your working pressure by ten percent next session. It is not dangerous in most cases but it means you are operating above the intended window. Chronic nerve irritation from repeated episodes is a real thing and it accumulates.
Where BFR Fails Completely
This is not a solution for everything. BFR is contraindicated for people with history of deep vein thrombosis, uncontrolled hypertension, peripheral artery disease, compartment syndrome, or certain types of vascular grafts. It should not be used on limbs with active infections or open wounds. Pregnant women should avoid it entirely. People with sickle cell trait or disease should not use it because the hypoxic conditions can trigger red blood cell sickling in the restricted limb. Even for appropriate candidates, BFR will not replace heavy progressive overload for long-term strength development. It is a tool for maintaining mass during low-load periods, accelerating rehab, or adding volume without joint stress. If your goal is maximal strength or power output, you still need to lift heavy things. BFR complements that work, it does not substitute for it. I have seen too many people treat it as a replacement for actual training and then wonder why their numbers plateau after three months. The other limitation is compliance. BFR is unpleasant. Your limb feels like it is going to explode after the second set. Some people simply cannot tolerate the sensation enough to complete the protocol consistently. If that is you, standard hypertrophy training at moderate loads remains the better option. No amount of evidence will convince you to keep doing something that feels terrible when a perfectly effective alternative exists. Use BFR when it makes sense for your situation. Do not force it into situations where it does not belong.