Why Most Blood Lecture Materials Are Wasted Time
I went through about fourteen different Blood Lecture Anatomy And Physiology resources before finding anything that actually held up in a real classroom or lab setting. The problem is most of these lectures prioritize covering every single structure over teaching you how to actually recognize things under a microscope or trace blood flow through a diagram without second-guessing yourself. You will waste weeks on materials that look comprehensive but leave you unable to identify erythrocyte morphology on a stained slide. A solid lecture on blood anatomy and physiology needs to do three things well: show normal differential counts with real slide images instead of cartoon diagrams, explain the coagulation cascade in a way that connects to actual lab values, and make clear distinctions between hematology findings that look similar but have different clinical implications. The last one is where most people fall apart on exams. I remember spending three weeks trying to memorize coagulation factors from a lecture that presented them as a numbered list. It was useless until a professor pulled up an actual PT and PTT panel and showed us which factors each test actually measures. That one visual connection took twenty minutes and stuck far better than any amount of rote memorization. The cascade is not a story you recite. It is a system with overlapping checkpoints, and treating it like a linear pathway is how people get tripped up on inhibitor questions.
Core Concepts You Need to Actually Know
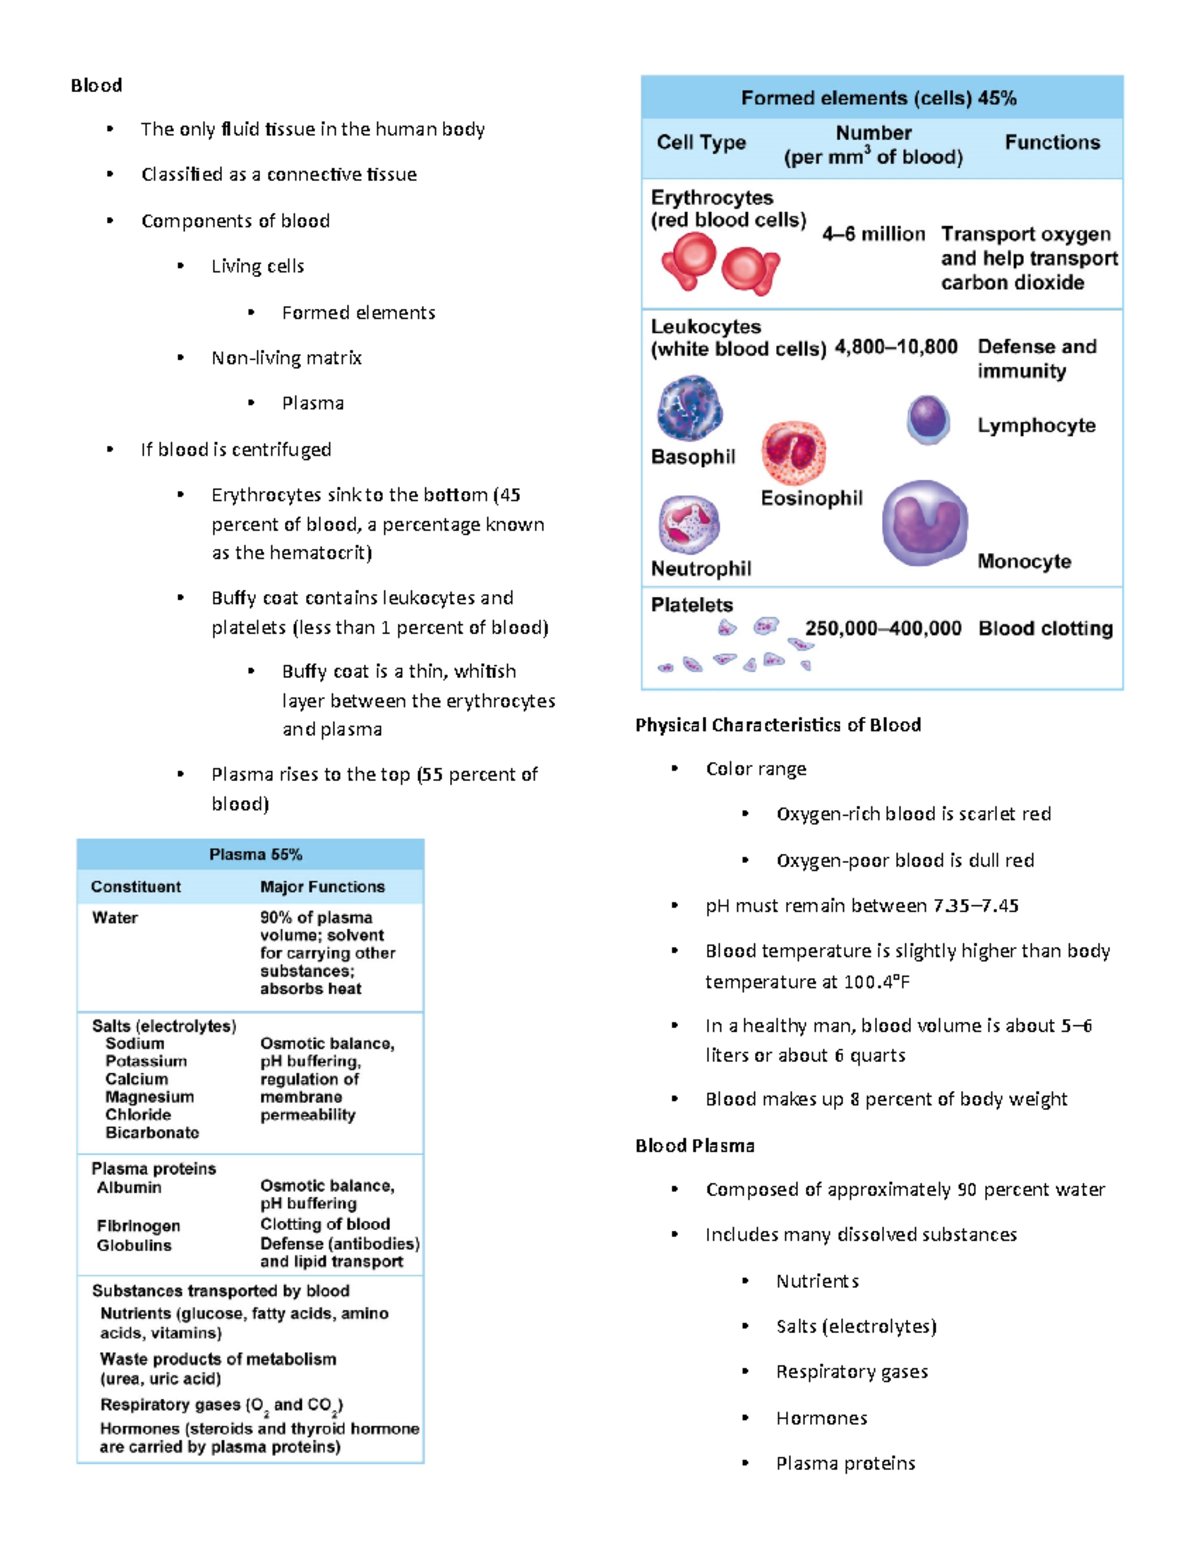
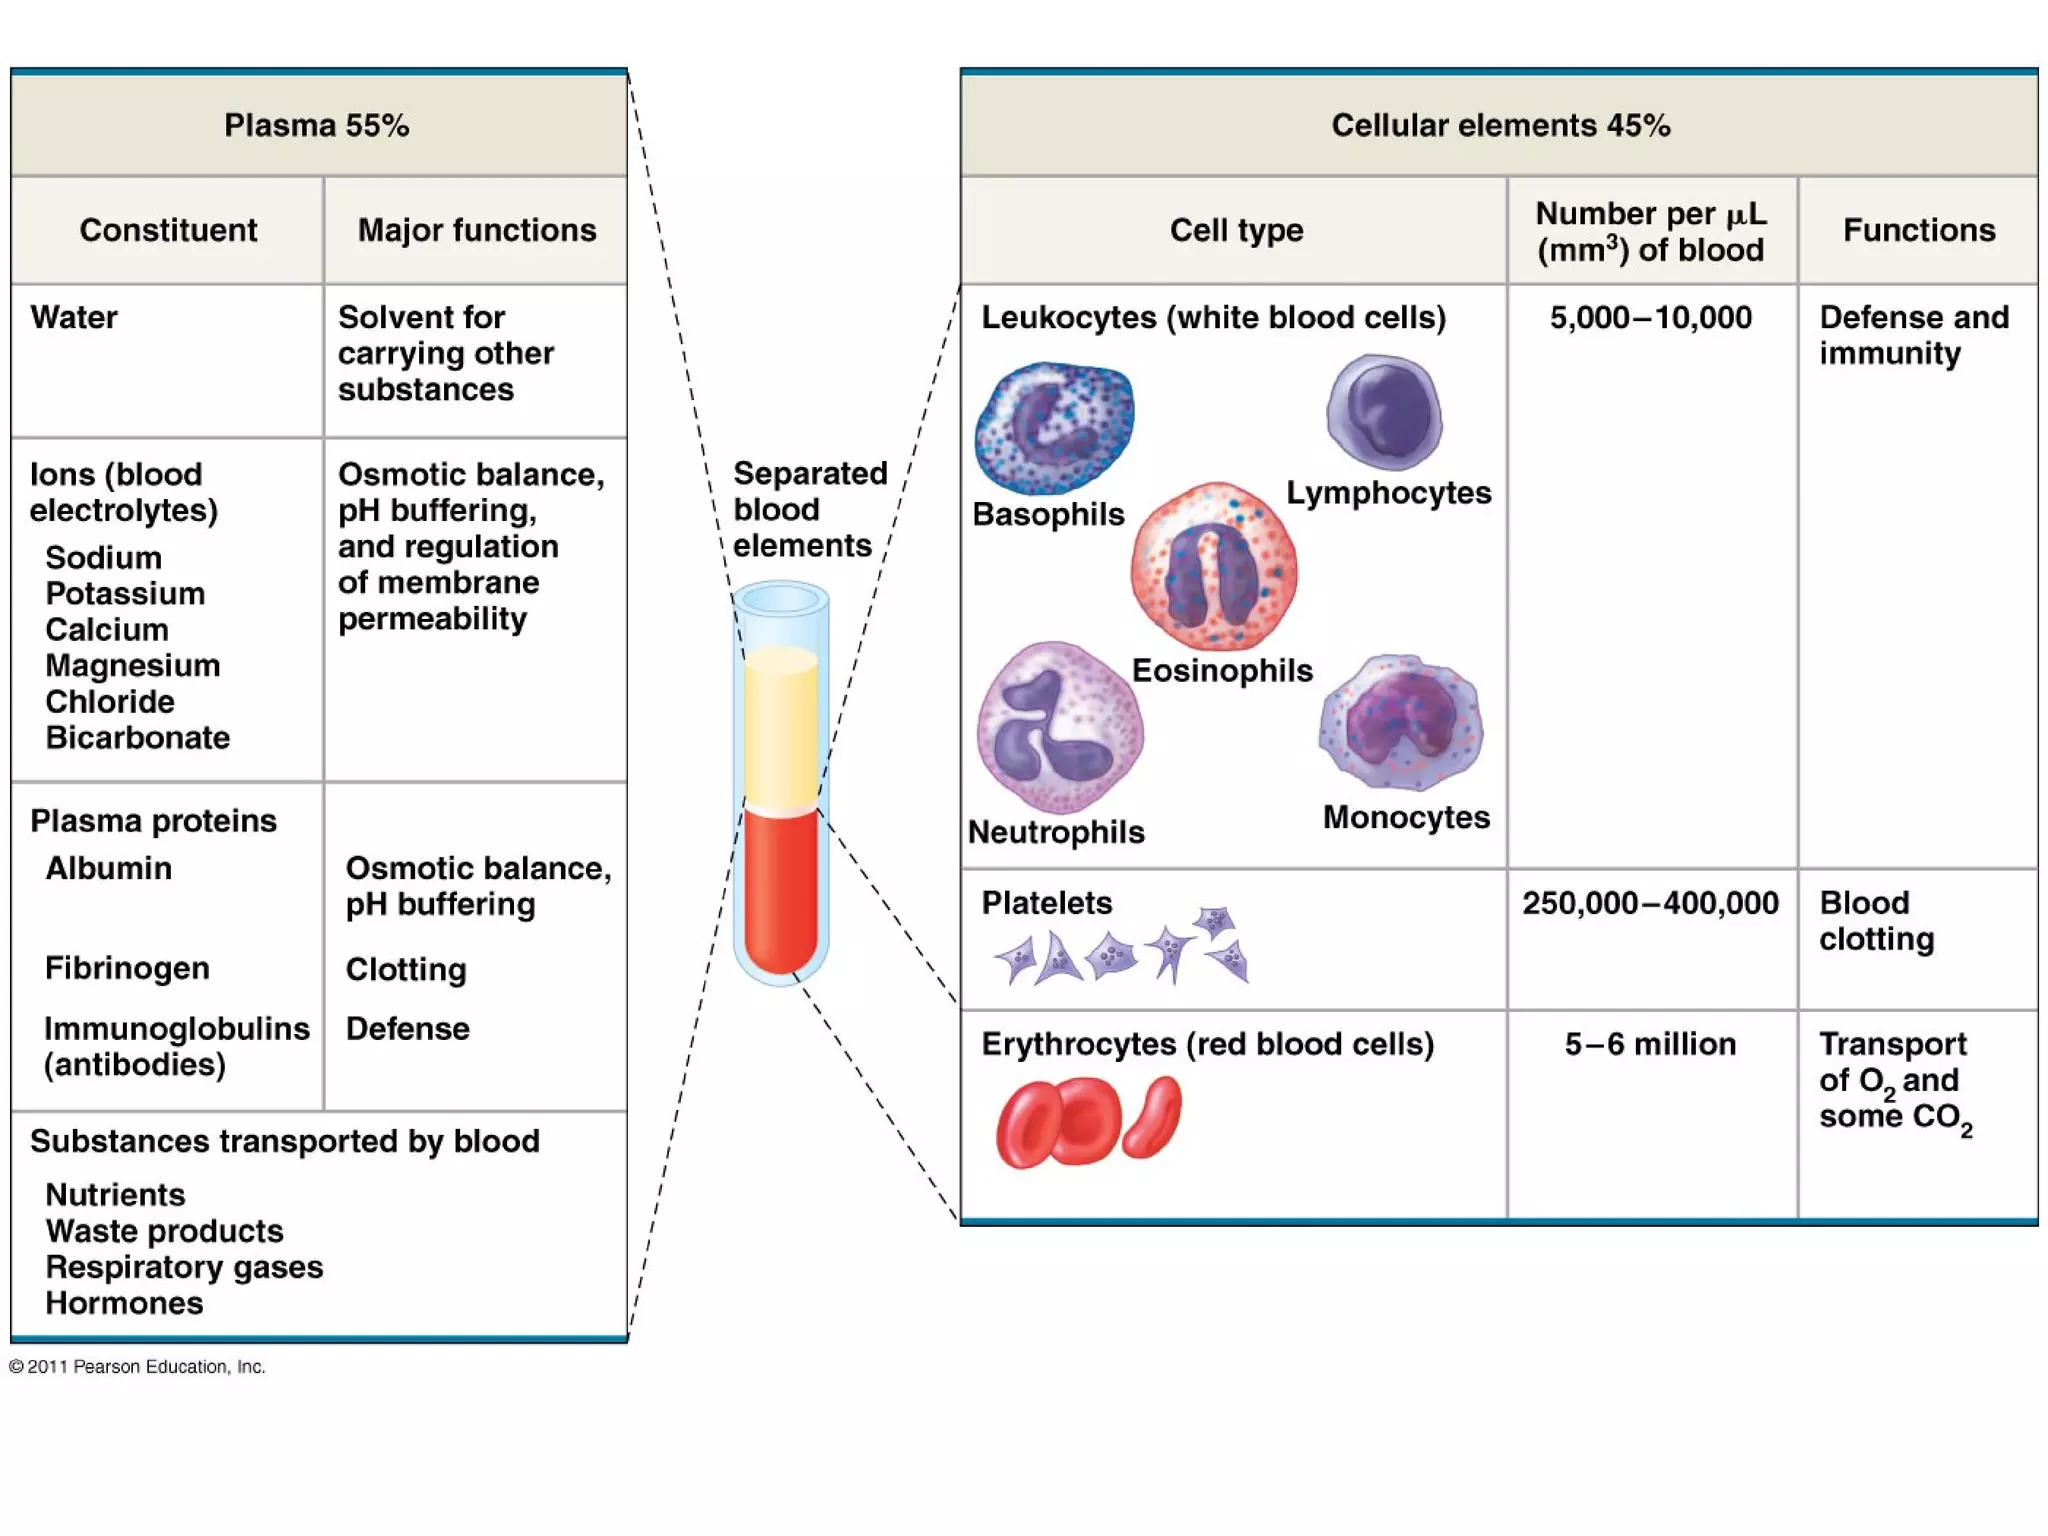
Red blood cell structure is simpler than lectures make it. Biconcave disc. No nucleus in mammals. Hemoglobin carries oxygen and CO2 in a ratio that shifts based on pH and temperature. The Bohr effect is not a trick question. It is the reason exercising muscle gets preferential oxygen delivery. If your lecture slides are spending more time on RBC lifecycle than on why sickle cells obstruct microvasculature, move on. White blood cell differentials come down to granule appearance and nuclear shape. Neutrophils have multi-lobed nuclei and primary granules. Eosinophils stain orange-red. Basophils are dark purple and harder to count consistently. Lymphocytes and monocytes are the agranulocyte group, and distinguishing them on a poorly stained slide is genuinely difficult even for experienced technologists. A good lecture will acknowledge this instead of pretending every sample looks like the textbook image. Platelets are cell fragments, not cells. That distinction matters when you are answering questions about their origin from megakaryocytes versus bone marrow stem cell differentiation. Lectures that blur this line will confuse you on mechanism questions later.
Plasma Proteins and Osmotic Pressure
Albumin maintains colloid osmotic pressure. Globulins handle immunity and transport. Fibrinogen handles clotting. That is the basic breakdown. What most lectures skip is the clinical relevance of hypoalbuminemia causing edema, or how multiple myeloma can spike globulin levels enough to alter blood viscosity. Understanding the numbers behind these proteins matters more than memorizing their names. Normal albumin is roughly 3.5 to 5.0 grams per deciliter. When it drops below 2.5, you start seeing peripheral edema in most patients. The lecture material should connect that threshold to Starling forces, not just list the range and move on.
Get the Full Details

Coagulation: Where People Mess Up
The intrinsic and extrinsic pathways converge at factor X. That convergence point is where most exam questions land. The common pathway then runs through prothrombin to thrombin to fibrinogen to fibrin. Yes, it loops back on itself through positive feedback. Yes, that is intentional and clinically relevant. Here is a detail I wish more lectures emphasized: the contact activation pathway, sometimes called the Fletcher trait pathway, is not essential for in vivo coagulation. People who memorize it as a required step will get burned. Factor XII deficiency does not cause bleeding. It causes a prolonged PTT in the lab with no clinical hemorrhage risk. I watched a study guide get this wrong three separate times before someone actually checked the literature.
How to Approach These Lectures Practically
Do not watch lectures passively. Pause after each major concept and try to explain it out loud without looking at your notes. If you cannot, you did not learn it. Repeat that process for hemopoiesis, the different blood cell lines, and coagulation before moving forward. Use hematology atlas images alongside your lecture. The VisualDx hematology section and the CDC's free blood smear images are reliable. Cross-reference what the lecturer describes with actual microscopic morphology. A lecture describing a hypersegmented neutrophil means something entirely different when you have seen one at 1000x oil immersion. For practice questions, stick to resources that explain why an answer is wrong, not just why the right answer is right. The distinction between a left shift and a leukemoid reaction is a classic exam trap, and you will only catch it by working through cases where the white count is elevated but the cause is fundamentally different.
Common Pitfalls in These Courses
Some Blood Lecture Anatomy And Physiology materials overemphasize embryologic development at the expense of adult hematology. Fetal hemoglobin switching is interesting. It is also low yield for most clinical scenarios unless you are studying hemoglobinopathies specifically. Balance your time accordingly. Another issue: lectures that present blood typing as simple A, B, AB, and O without covering the Rh system in adequate depth. The Rh incompatibility issue in pregnancy is clinically significant and appears far more often on exams than people expect. If your lecture spends ten minutes on ABO and two minutes on Rh, that is a red flag. The biggest problem I see is that many resources treat blood gas values and acid-base balance as a separate topic. They are not. Respiratory and metabolic disturbances directly affect hemoglobin oxygen affinity. A patient with chronic respiratory acidosis will have a right-shifted oxygen dissociation curve. Ignoring that connection makes both topics harder than they need to be.
What I Recommend Instead of Collecting More Lectures
Pick one solid lecture series and work through it completely. Add a hematology lab manual for hands-on correlation. Use flashcards only for the facts that refuse to stick through explanation alone, like the specific coagulation factors measured by PT versus PTT. Factor VII is extrinsic only. Factors VIII, IX, XI, and XII are intrinsic. Remembering that one fact saved me on three separate examinations. If you are preparing for a boards-level exam, integrate pathophysiology early rather than treating it as a separate unit later. Understanding why iron deficiency causes microcytic anemia before memorizing the MCV ranges will make the entire hematology section easier. The mechanism teaches the numbers, not the other way around.