The Actual Mechanism Behind Post-Exercise Blood Pressure Changes
When you exercise, your blood pressure responds in ways that depend heavily on what kind of exercise you're doing, how intensely you're pushing yourself, and whether you're consistent with it over time. The acute response is straightforward enough. During dynamic exercise like walking, running, or cycling, systolic blood pressure rises because your heart is pumping more blood to working muscles. Diastolic pressure usually stays flat or drops slightly because blood vessels in those muscles dilate, reducing total peripheral resistance. This is normal. What trips people up is what happens after you finish moving. Immediately post-exercise, most people experience a period called post-exercise hypotension where blood pressure actually dips below baseline for anywhere from 30 minutes to several hours. This is one of the reasons clinicians sometimes have patients wait before taking a reading after physical activity. I've seen lab-grade readings off by 15 to 20 millimeters of mercury just because someone sprinted up a flight of stairs and then sat down for a measurement without waiting. The vascular dilation doesn't reverse instantly.
Understanding The Blood Pressure And Exercise Relationship In Practice
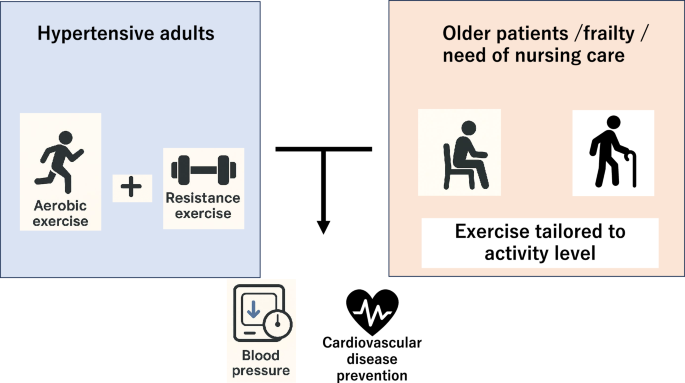
The chronic adaptation — the real value here — is that regular exercise reshapes how your cardiovascular system manages pressure over time. Consistent aerobic training reduces resting systolic pressure by an average of 5 to 8 millimeters of mercury in hypertensive individuals and about 2 to 4 mmHg in normotensive people. Resistance training shows more modest but measurable effects, generally in the 2 to 5 mmHg range. The combination of both tends to produce the strongest cumulative effect. One thing that catches people off guard is that the type of exercise matters far more than people expect. Isometric exercises like heavy wall sits, planks under maximal tension, or certain yoga holds can actually cause a sharp spike in both systolic and diastolic pressure during the hold. I spent months trying to figure out why a client's home blood pressure log showed elevated readings on days she did her usual pilates reformer routine, which includes several extended isometric holds. Once I separated out the isometric work from the cardio and flow portions, the pattern became obvious. The isometric holds were driving transient spikes that looked like poor control in her data, even though her actual resting pressure was fine. We modified her routine to use shorter holds with continuous breathing and the numbers normalized immediately. Another counter-intuitive detail involves timing. The blood pressure lowering effect of exercise is not permanent in the way people assume. Studies show the post-exercise hypotensive window typically lasts around 22 hours after a single session. This is why consistency matters more than intensity. A moderately intense 30-minute walk most days will manage your pressure far better than one brutal session per week that leaves you flat for three days. The vascular adaptations that matter — improved endothelial function, reduced sympathetic nervous system tone, better baroreceptor sensitivity — all require repeated stimulus to maintain.
Here is how you actually apply this without overthinking it. If you are looking at exercise as a blood pressure management tool, start with aerobic work at moderate intensity. You want to be at a level where you can talk in full sentences but you'd rather not carry on a long conversation. That's roughly 60 to 75 percent of your maximum heart rate, or about 113 to 142 beats per minute for a 40-year-old. Do this for 30 minutes, almost all days of the week. Add resistance training twice weekly with moderate loads, not maximal lifts. Avoid exercises that require you to hold your breath or strain for extended periods if you already have elevated blood pressure. There are hard limitations to be aware of. If your resting systolic pressure is above 180 or diastolic is above 110, exercise should be medically supervised. Pushing through uncontrolled hypertension with vigorous activity can push things into dangerous territory quickly. The same applies if you have known cardiovascular disease, retinopathy from diabetes, or severe peripheral arterial disease. Exercise is not a replacement for medication in these cases, and pretending otherwise gets people hurt. The blood pressure and exercise relationship is genuinely useful, but it operates within biological constraints and you need to respect them. For tracking purposes, the most reliable approach is measuring your blood pressure at the same time each day, ideally in the morning before food, caffeine, or exercise, while seated and rested for at least five minutes. Take two readings 30 seconds apart and average them. One reading is noise. Three readings are better. This is standard clinical protocol and it cuts down on the kind of panic that comes from seeing an occasional elevated number that has nothing to do with your actual baseline.
Get the Full Details