Getting a Blood Pressure Reading When Everything Is Going Wrong
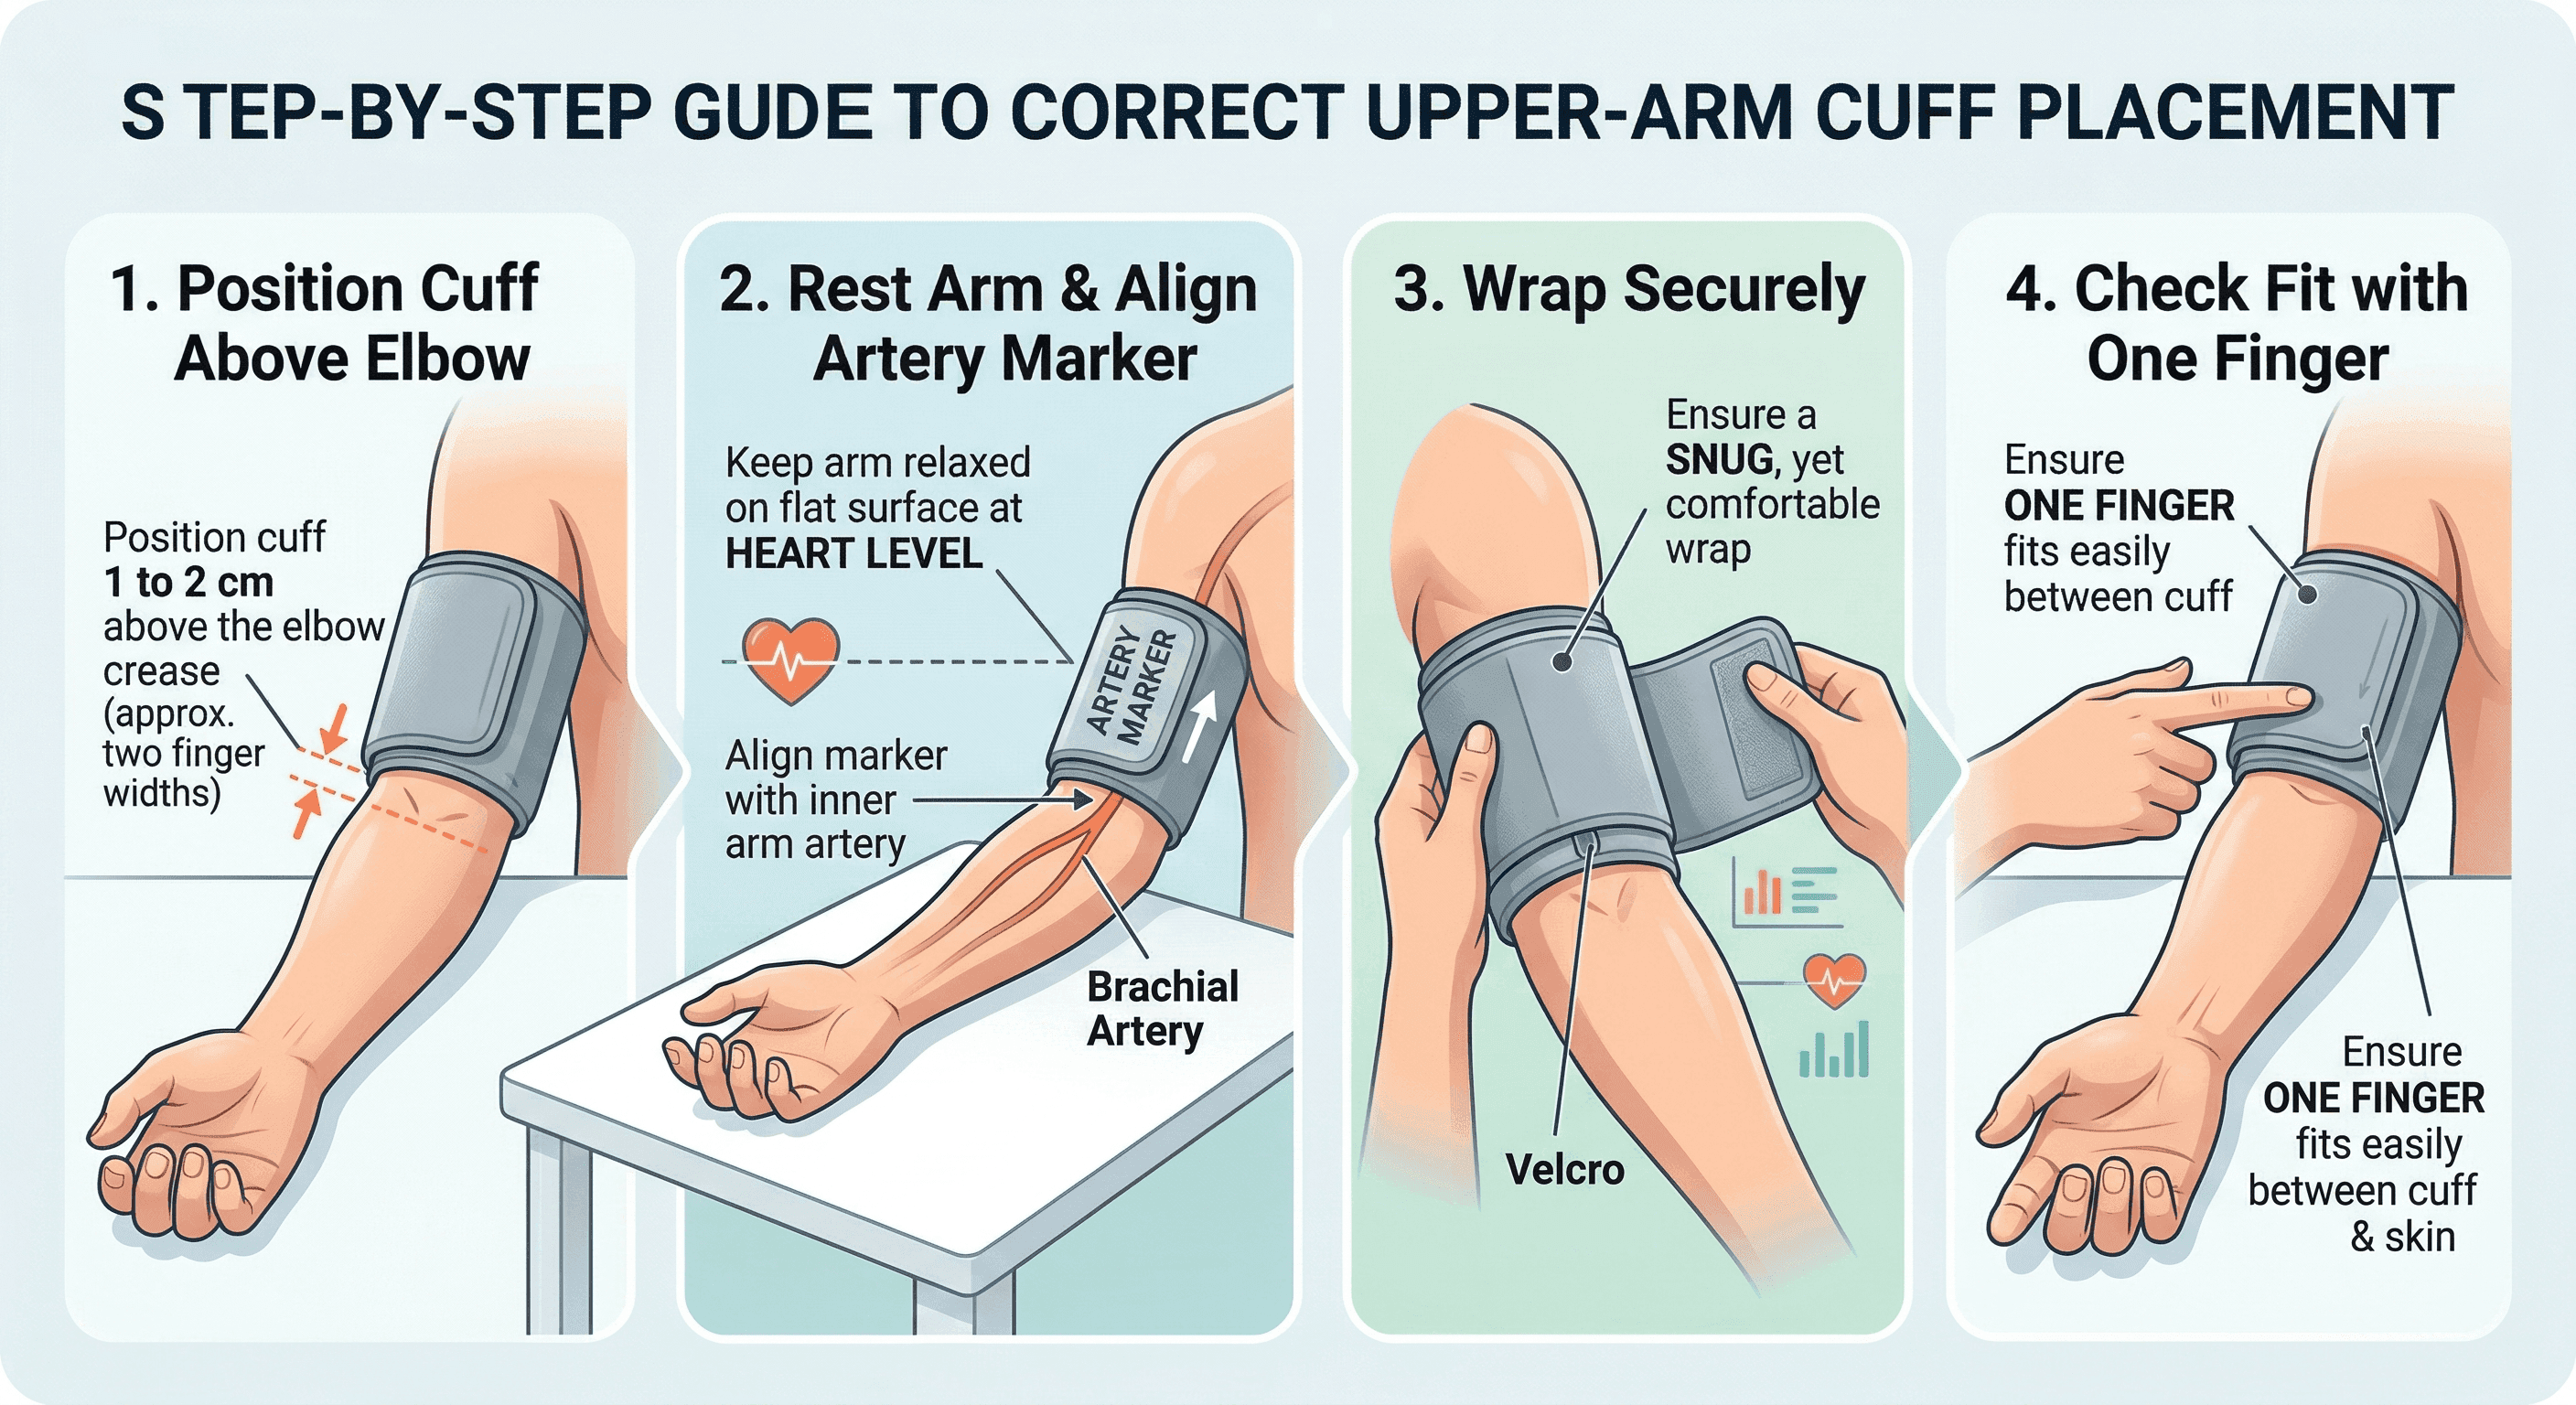
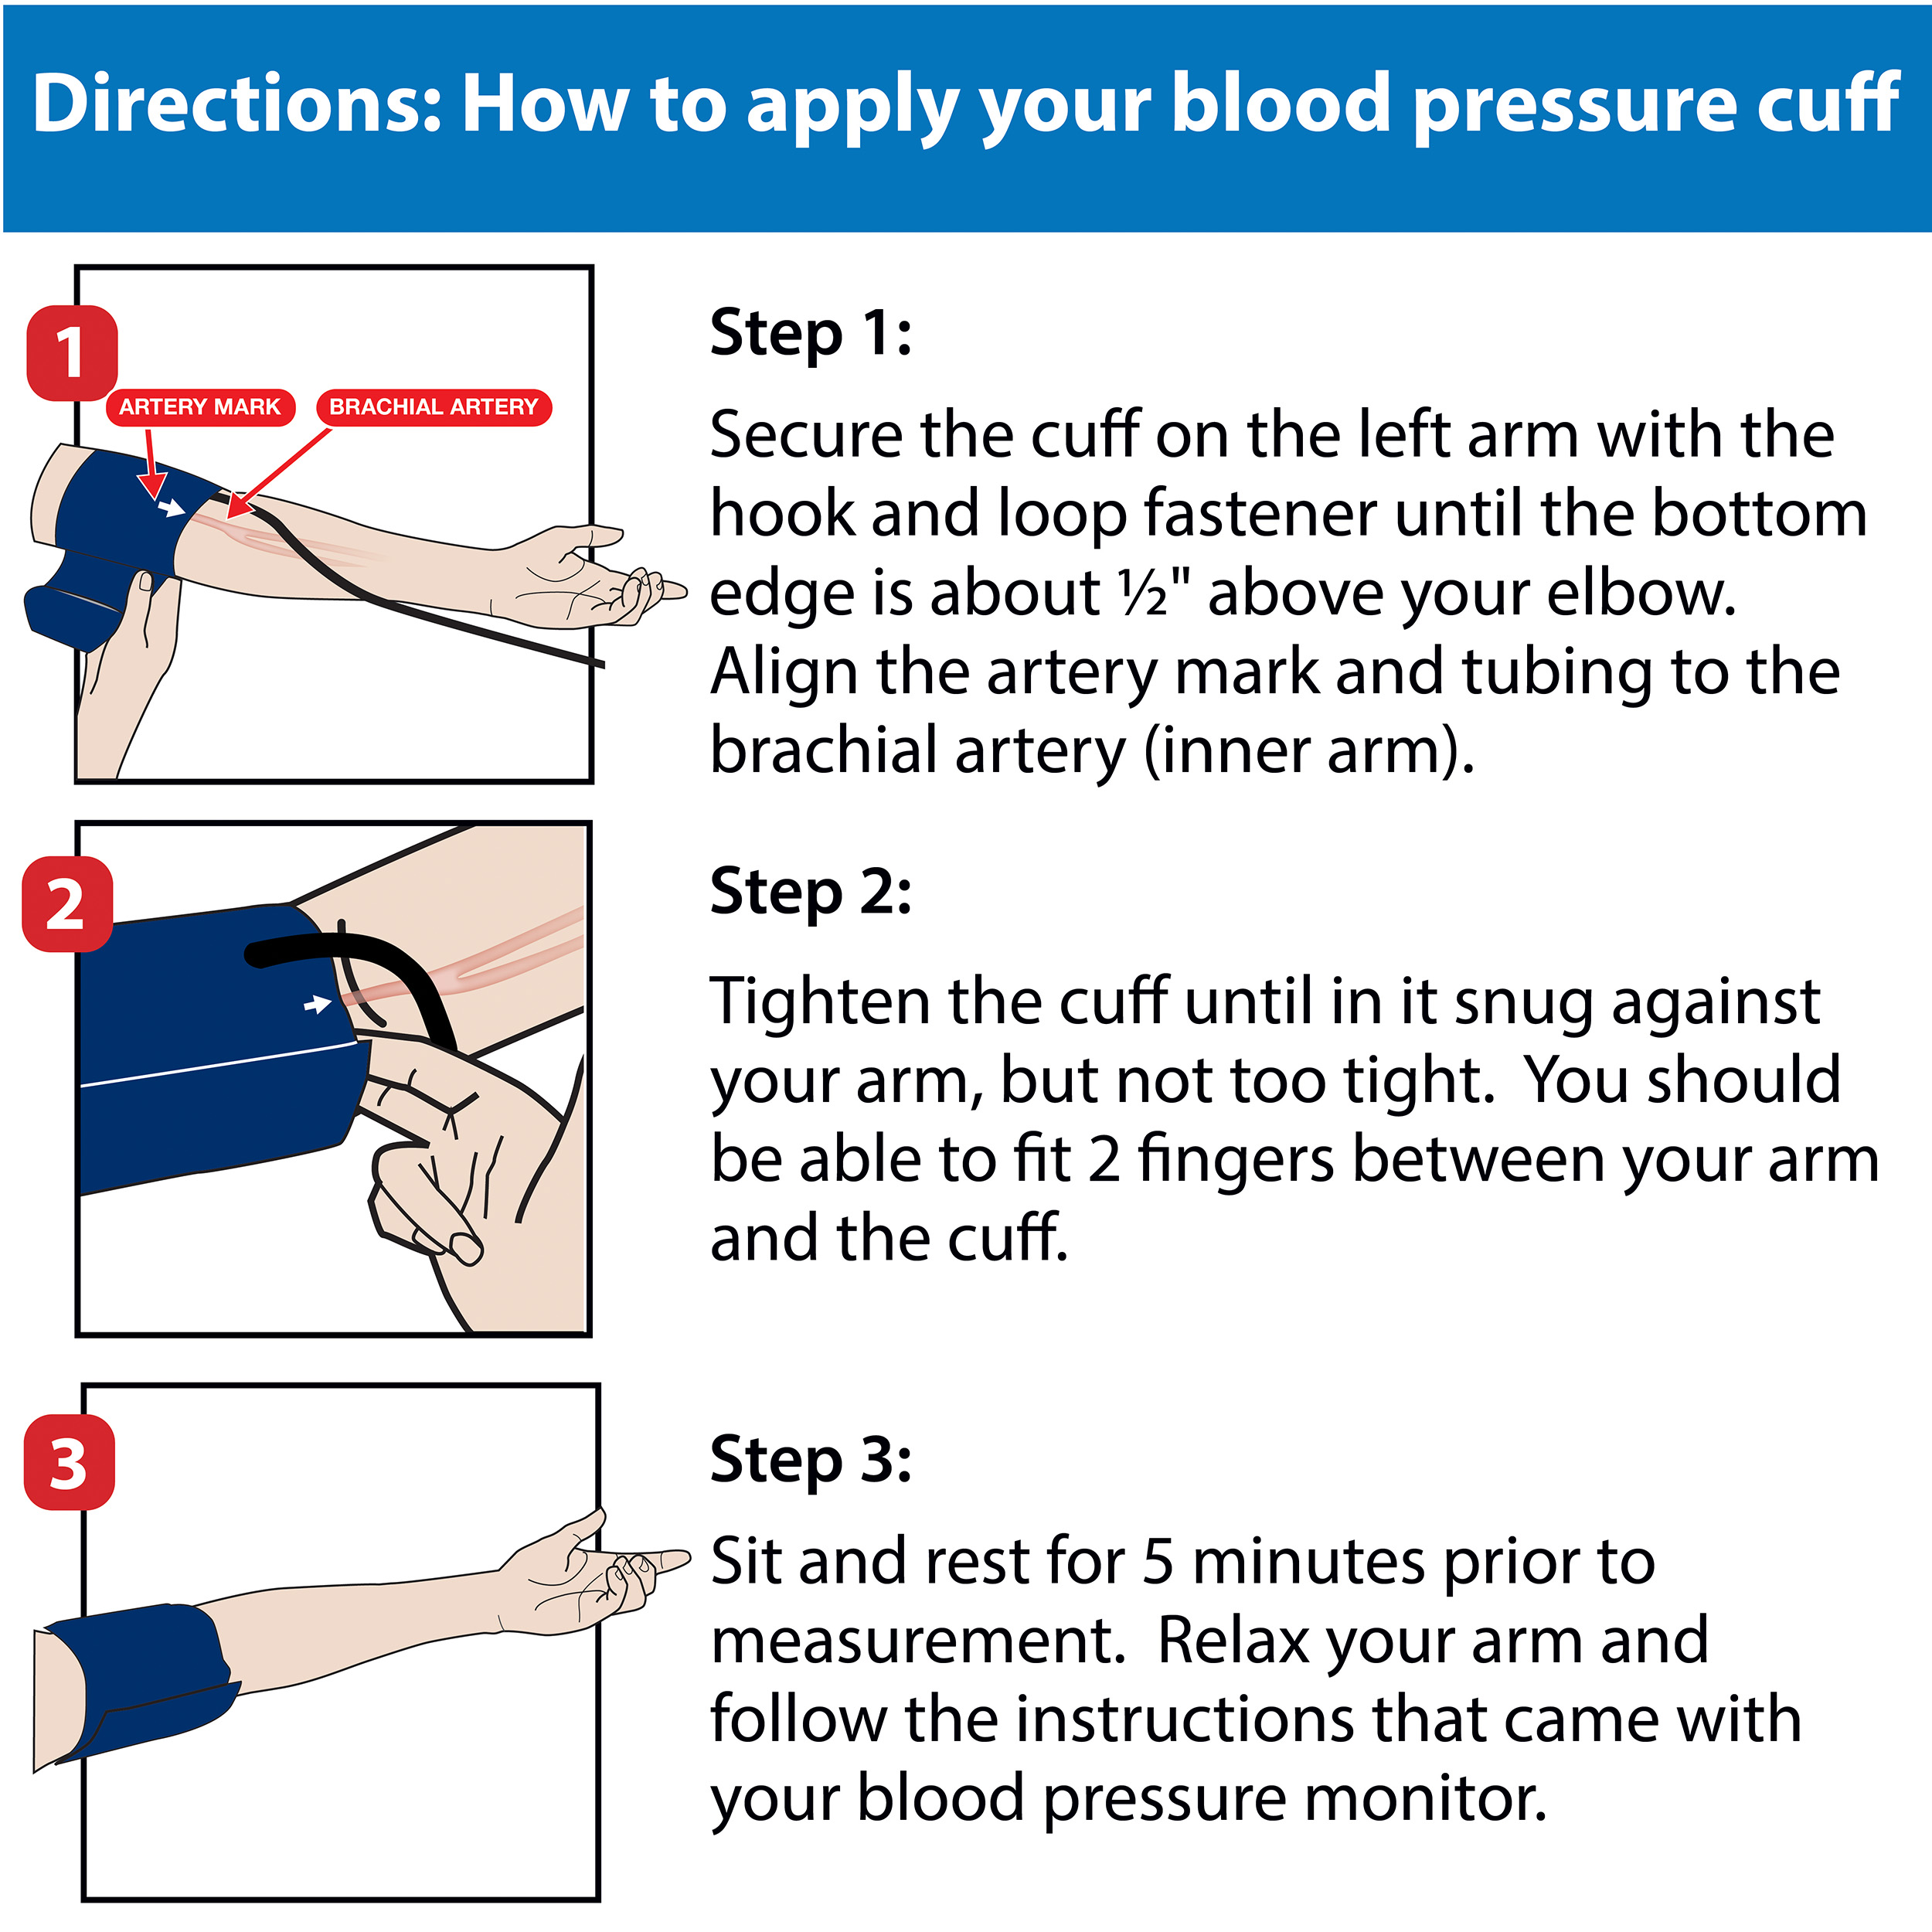
I have spent more hours than I care to count chasing phantom readings on equipment that should have been pulled from service years ago. The problem is almost never what the screen tells you. It is always something trivial, stupidly simple, but invisible if you are in a rush. I used to waste twenty minutes on a single patient before learning to stop and look at the whole system instead of staring at the numbers. Start with the cuff itself, not the monitor. A common mistake I see constantly is someone assuming the machine is broken when the cuff is the actual problem. If you are getting inconsistent readings or the machine keeps cycling without inflating properly, check the cuff before you touch anything else. The tubing connection at the patient end is where most failures happen. The plastic connector cracks inside the housing and you cannot see it from the outside. I found this out after replacing two monitors for what turned out to be a hairline fracture in the Luer lock fitting on a secondhand cuff. The fix was replacing just the connector sleeve, which costs about four dollars instead of buying a whole new cuff assembly. The placement of the cuff matters more than people realize. It needs to sit one inch above the antecubital fossa with the artery marker aligned directly over the brachial artery. When I worked clinic shifts, I would watch nurses place the cuff too high or rotated wrong and then wonder why the reading was ten to fifteen points off. That is not a machine error. The oscillometric sensor inside the cuff detects pressure changes in the artery below it. Misalignment means it is sensing tissue instead of blood flow dynamics. The reading will still appear on the screen and look completely normal even though it is wrong.
Here is something most guides do not mention. Arm circumference is not just about fitting the cuff. Using an incorrect size cuff does not simply make the reading less accurate. It systematically biases the result in a predictable direction. A cuff that is too small will consistently read higher than the actual blood pressure. I have seen patients flagged as hypertensive who were only getting inflated readings because the tech used a regular adult cuff on someone whose arm measured forty centimeters around. The correct cuff for that arm is an adult large or thigh cuff depending on the exact measurement. You need a proper tape measure and a cuff sizing chart. Not the one printed on the cuff box. Those are generic. Use the manufacturer's specific sizing guide that comes with the device. Patient positioning is another area where shortcuts cause real problems. The arm must be supported at heart level. Not held up by the patient. Not dangling. Supported. When I was training staff, I had someone hold their own arm up during a reading and the systolic came back twelve points higher than when we repeated it with the arm properly supported on a table. That is a huge difference clinically. It can change a treatment decision. The patient should be seated with back supported, feet flat, and the arm resting on a surface so the cuff is level with the right atrium. This is standard but it is also the step most often skipped in busy environments. About the machine itself. Oscillometric monitors have a known issue with arrhythmias. If the patient has atrial fibrillation or frequent ectopic beats, the monitor struggles to identify the mean arterial pressure correctly. It may display a reading but the value can be off by twenty to thirty millimeters of mercury. I learned this the hard way during a rotation where the automated cuff kept giving wildly different numbers on a patient we knew had irregular heart rhythm. Switching to manual auscultation resolved it immediately. The device is not broken. It is just hitting a limitation of its sensing method. Some newer monitors advertise arrhythmia detection mode. They help but they do not eliminate the problem entirely. Manual measurement remains the reference standard in these cases.
Pumping volume and inflation speed are settings that get ignored until something goes wrong. Most monitors auto-inflate to a preset pressure based on patient history or previous readings. This is convenient until it is not. If the preset is too high, the rapid inflation causes patient anxiety and adrenaline release, which temporarily raises blood pressure. The reading you capture is artificially elevated because the patient flinched from the sudden pressure. The workaround is to set the inflation limit lower and let it cycle up gradually. I usually set the max inflation to the patient's previous systolic plus thirty millimeters of mercury. This avoids unnecessary discomfort while still ensuring adequate inflation for detection. It cuts down on repeat readings significantly. Calibration drift is a real concern with home monitors that get used daily. I had a patient bring in their home monitor to compare against our clinical device and it read fifteen points higher across the board. We sent it for calibration and the correction factor was twelve millimeters of mercury on the pressure transducer. After adjustment, the readings matched. This happens more often with cheaper consumer-grade units. The pressure sensors degrade over time, especially with repeated full inflation cycles. If you use a home monitor regularly, plan on annual calibration checks. Compare it against a professional device at your next appointment and write down the difference. If the offset exceeds ten millimeters of mercury, the monitor needs attention. One edge case that cost me an hour once involved a monitor that refused to hold inflation. The gauge would build pressure normally but then slowly bleed down during the measurement phase. I replaced the valve, then the tube, then the cuff. Nothing fixed it. Turns out the air intake filter inside the pump housing was clogged with dust and lint from being stored near a window. The partial vacuum it created caused the check valve to behave erratically. Cleaning the filter with compressed air solved it. The lesson is that these devices breathe. Any obstruction to the intake compromises the entire pressure system. Check the filter every six months if the unit is used in a dusty or high-traffic environment.
Get the Full Details
When troubleshooting, I follow a specific order that saves time. First, verify cuff integrity visually and with a bulb test. Squeeze the bulb to thirty millimeters and hold for ten seconds. If it drops more than five, there is a leak somewhere in the circuit. Second, inspect the tubing for kinks or internal damage. Third, check the patient factors. Fourth, run a baseline reading on yourself or a colleague to confirm the machine produces a plausible result. Fifth, if the machine passes but patient readings remain erratic, consider arrhythmia or movement artifact and switch to manual measurement. This sequence catches the issue at the simplest point before escalating. The biggest mistake people make is assuming a digital readout is absolute truth. It is not. It is an estimate derived from detecting oscillations in the cuff pressure. The algorithm interprets those oscillations and calculates systolic and diastolic values based on population-derived formulas. Individual anatomy, vessel stiffness, temperature, and a dozen other factors shift where those oscillations appear. The monitor does not account for all of them. Understanding this changes how you approach every reading. You treat it as useful data, not a definitive answer. When something looks wrong, question the context before you question the equipment. Usually the context is the problem.


