How to Actually Read and Use a Blood Pressure Reading Chart
A blood pressure reading is just two numbers. The top number is the systolic pressure — your artery pressure when the heart beats. The bottom number is diastolic — the pressure between beats when the heart is resting. That's all the hardware does. The chart is just someone's way of telling you what to do with those numbers afterward. I've spent more time than I'd like explaining charts to people who come in after their pharmacy machine lit up with a scary result. Half the time the cuff was on the wrong arm and half the rest of the time they'd been sitting upright in a rushed state. Let's skip to the actual method first since that matters more than memorizing rows.
Understanding Your Blood Pressure Reading Chart
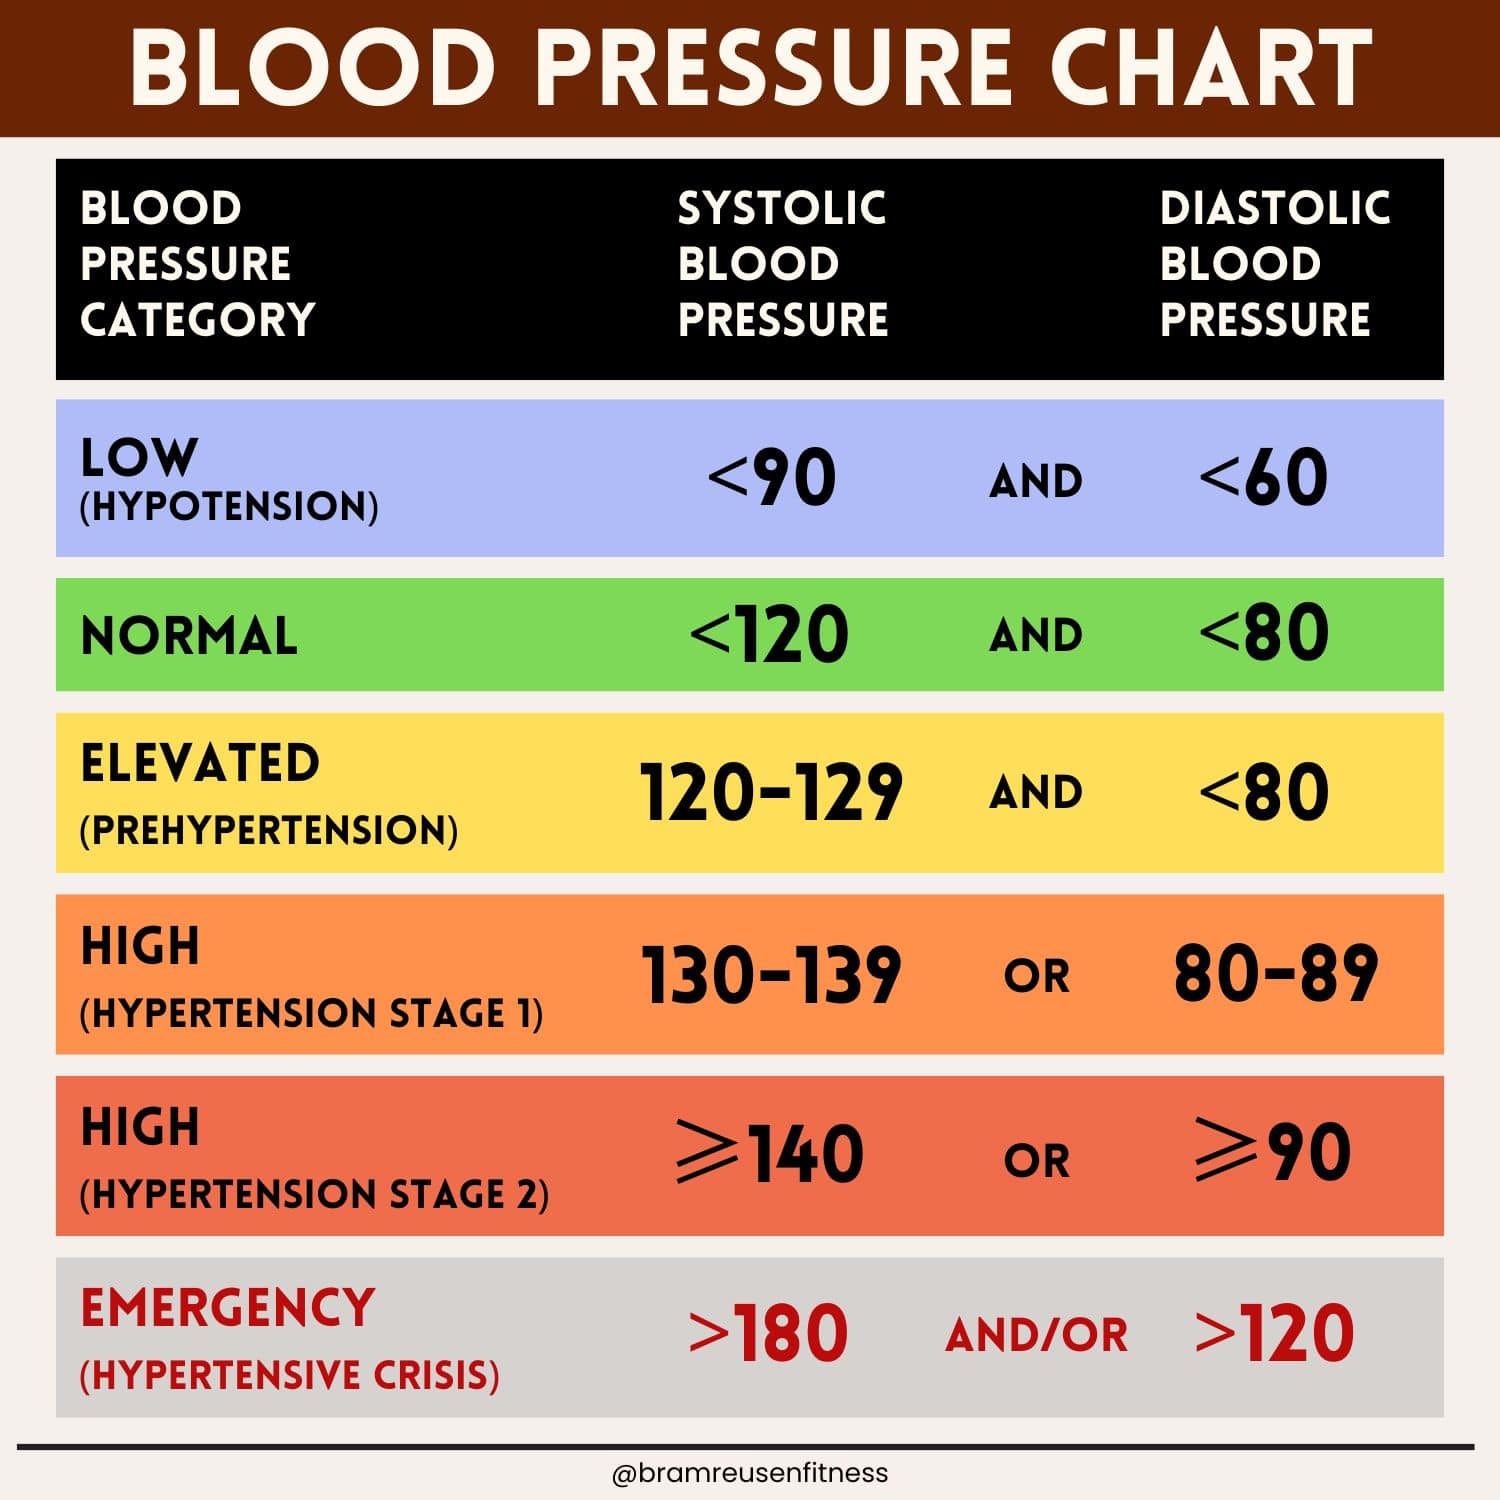
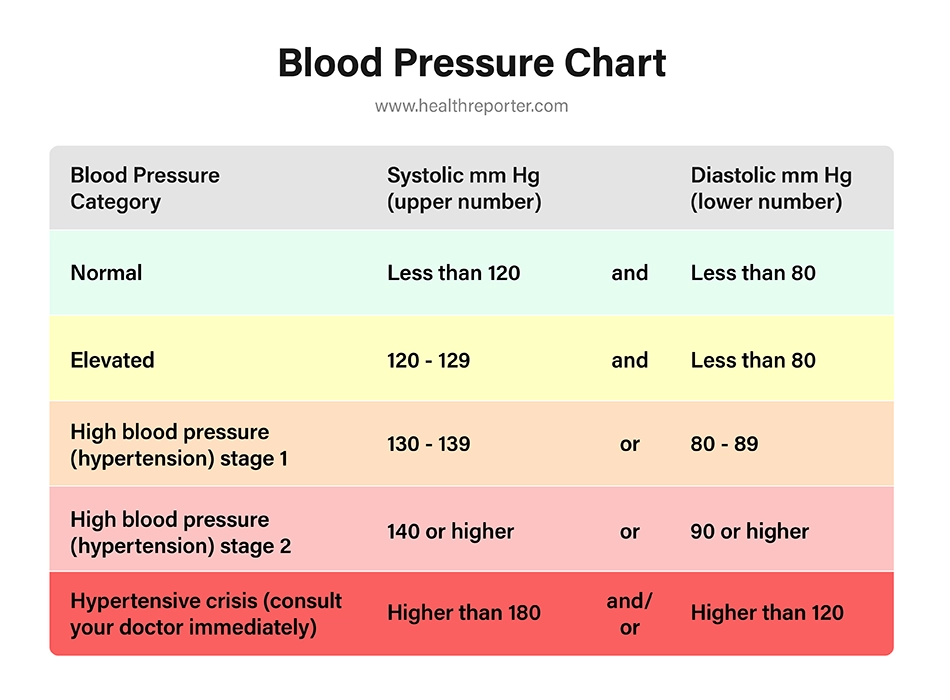
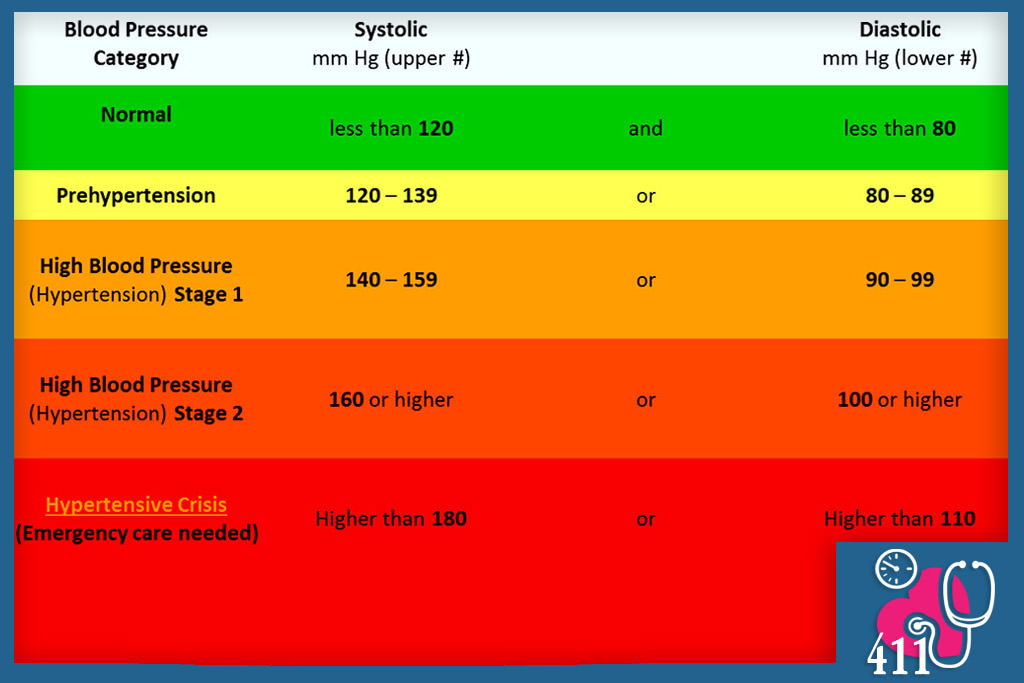
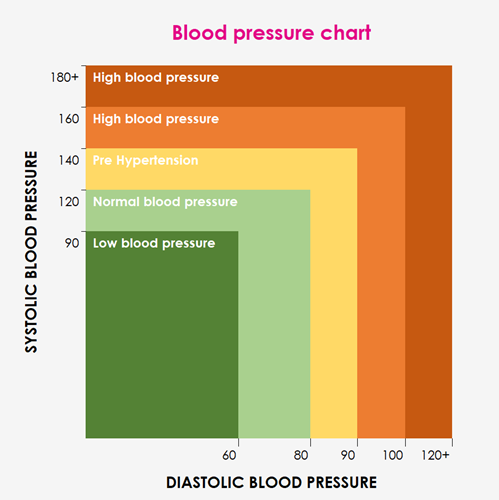
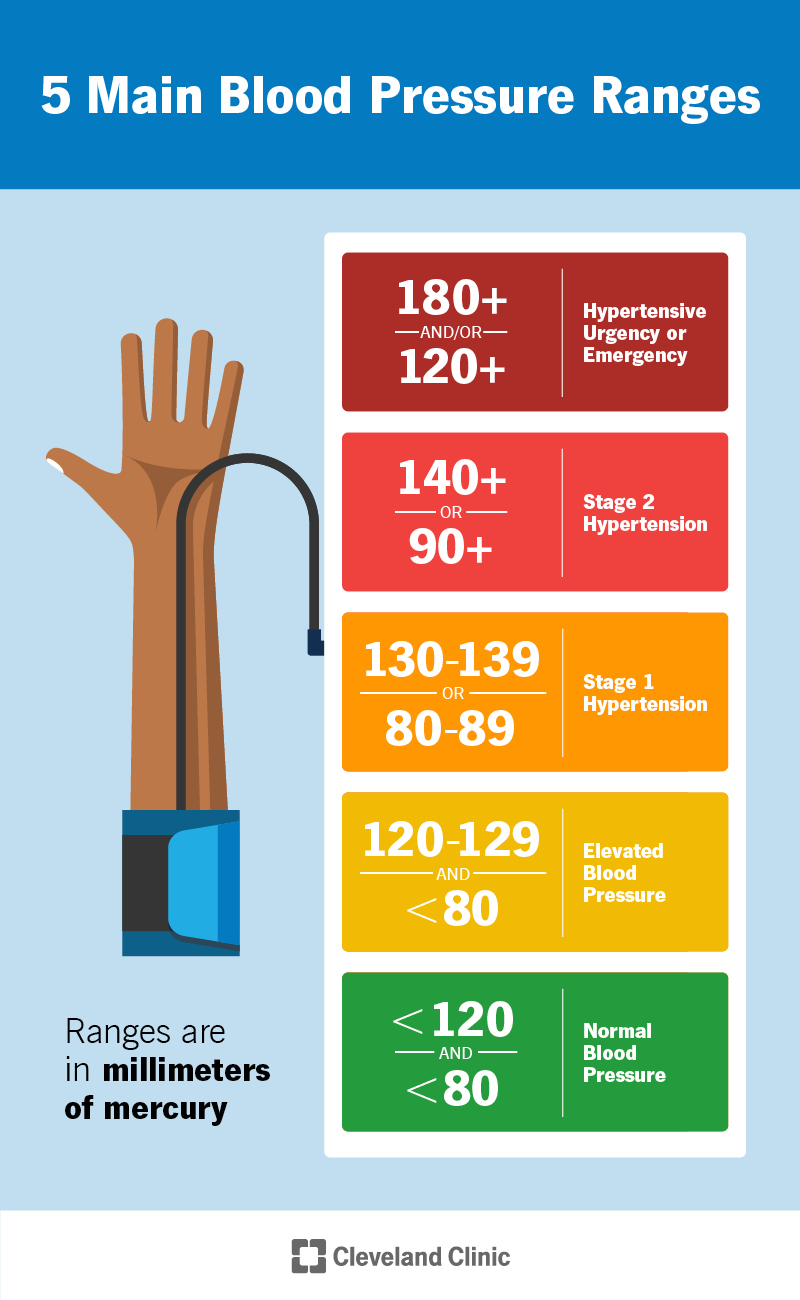
Here's how it works in practice. Sit quietly for five minutes before taking a reading. Feet flat on the floor, back supported, arm at heart level. Don't talk during the measurement. If you've smoked, exercised, or had caffeine in the last half hour, wait. Write down both numbers immediately — I always tell people to grab a notebook or use their phone because they'll forget the second number and it drives them crazy later trying to recall whether it was 84 or 94. The standard classification categories that most charts use — and yes, there are some disagreements in the field about this — break down as follows. Normal falls under 120 over 80. Elevated means systolic between 120 and 129 with diastolic under 80. Stage 1 hypertension is 130 to 139 systolic or 80 to 89 diastolic. Stage 2 hits at 140 or higher over 90 or higher. A hypertensive crisis is anything above 180 and/or 120, and that's the category where you stop taking more readings and go see someone now. The American College of Cardiology and the American Heart Association updated these thresholds in 2017, which means a lot of older charts floating around the internet are still using the pre-2017 categories where "prehypertension" covered 120 to 139 over 80 to 89. If you're looking at a chart from before 2018, it's probably using the old framework. That alone misclassifies a meaningful chunk of people as lower risk than they actually are.
There's a specific problem I ran into repeatedly that nobody seems to mention in these guides. White coat hypertension. Patients walk in, their blood pressure reads 150 over 95, and the chart says stage 2 hypertension. They get put on medication. Then we figure out their actual home readings average 122 over 76. The chart itself isn't wrong — the measurement context is. That's why I always recommend at least a week of home monitoring before trusting a single clinical reading. Home readings tend to run about five to ten millimeters of mercury lower than office readings on average, and the chart doesn't account for that gap by default. Conversely, masked hypertension is the trickier version of the same issue. Someone looks perfectly fine at the clinic with a reading of 118 over 74, but their ambulatory or home readings climb well into hypertensive territory throughout the day. The chart can't protect you from that because it has no idea how you look at 2 PM on a Tuesday when you're stressed at work. Ambulatory blood pressure monitoring is the actual solution there, not another office reading.
Get the Full Details
Practical Walkthrough
Take three readings, one minute apart, morning and evening for a week. Discard the first reading each session and average the remaining two. That average is your real number to compare against the chart. Most people think a single reading means something. It doesn't. Blood pressure varies by fifteen to twenty millimeters of mercury just from breathing patterns and body position. Averaging smooths that out enough that you're actually looking at signal instead of noise. One thing automated home cuffs get wrong regularly — and this is worth knowing — is atrial fibrillation detection. Some cheaper units flag irregular heartbeats, but many don't. If your chart says your blood pressure is fine but your pulse rhythm feels off, that discrepancy matters more than any single reading. The chart won't tell you that. Nobody designs these charts around arrhythmia.
When the Chart Doesn't Help
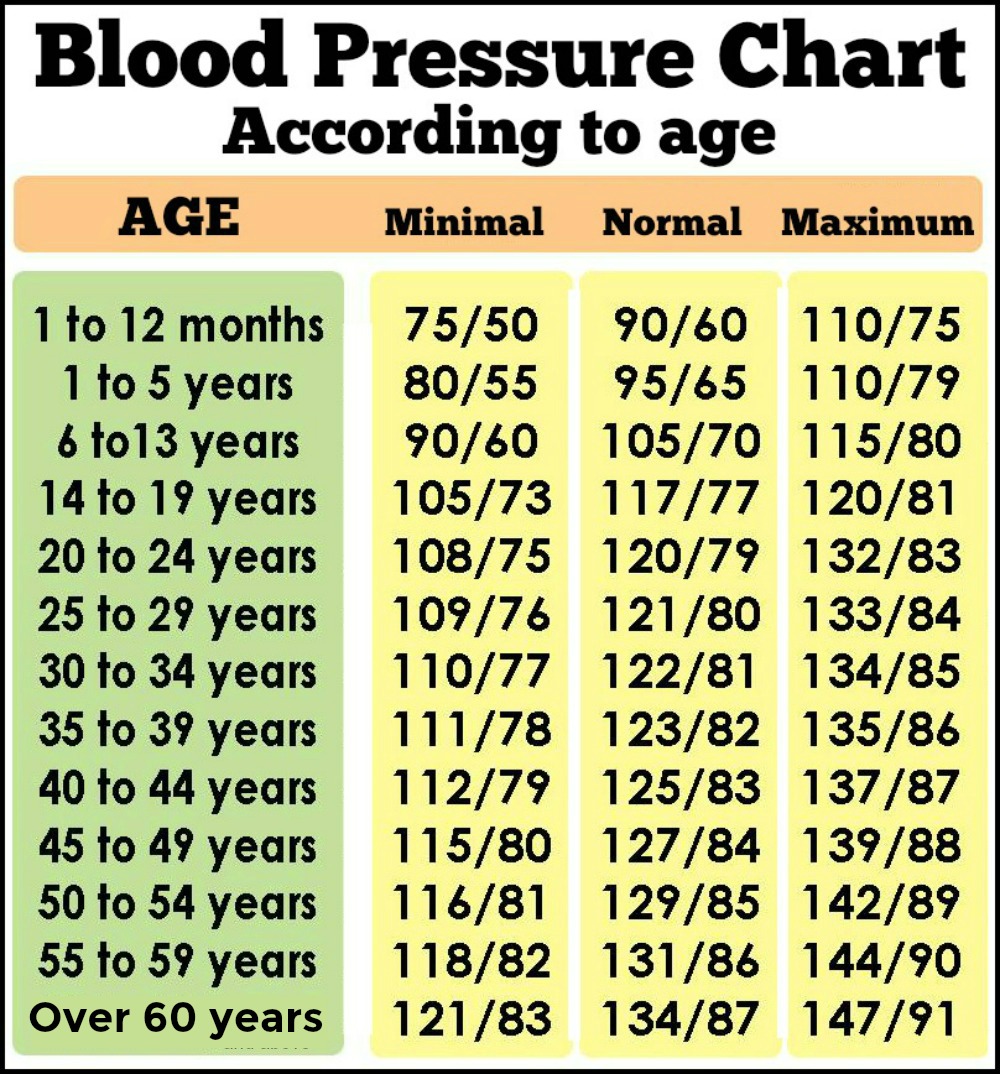
Isolated systolic hypertension is common in older adults where the top number runs high but the bottom stays normal. That's a very different clinical picture from combined elevation and the chart categories treat both situations identically, which they shouldn't. The treatment approach diverges significantly. An older patient with 160 over 78 needs different management than a younger one with 150 over 95, even though both fall into the same stage on most charts. Cuff size matters enormously and almost nobody checks it properly. Using a standard adult cuff on a larger arm can add ten to fifteen millimeters of mercury to the systolic reading. That single error can push someone from normal into stage 1 hypertension on paper. The reading is wrong, the chart interpretation is wrong, and the person walks away with a label they don't deserve. Measure your arm circumference and match it to the cuff. Most home units come with one cuff size and that's often insufficient for anyone past a slim build. If you want a downloadable reference, search for "blood pressure reading chart PDF" and look for one published by the American Heart Association or the CDC. Those are the most reliable sources and they update when the guidelines change. Any chart you find on a random health blog is probably using outdated thresholds or worse, no source at all.
The chart is a starting point, not a diagnosis. It summarizes population-level data into categories that help clinicians and patients have a conversation. It does not replace that conversation, and it definitely does not replace a week of proper home monitoring. Take the readings, average them, compare them to a current chart, and then take that data to someone who can actually do something with it.