Understanding the Practical Differences Between Serum and Plasma in Real Lab Work
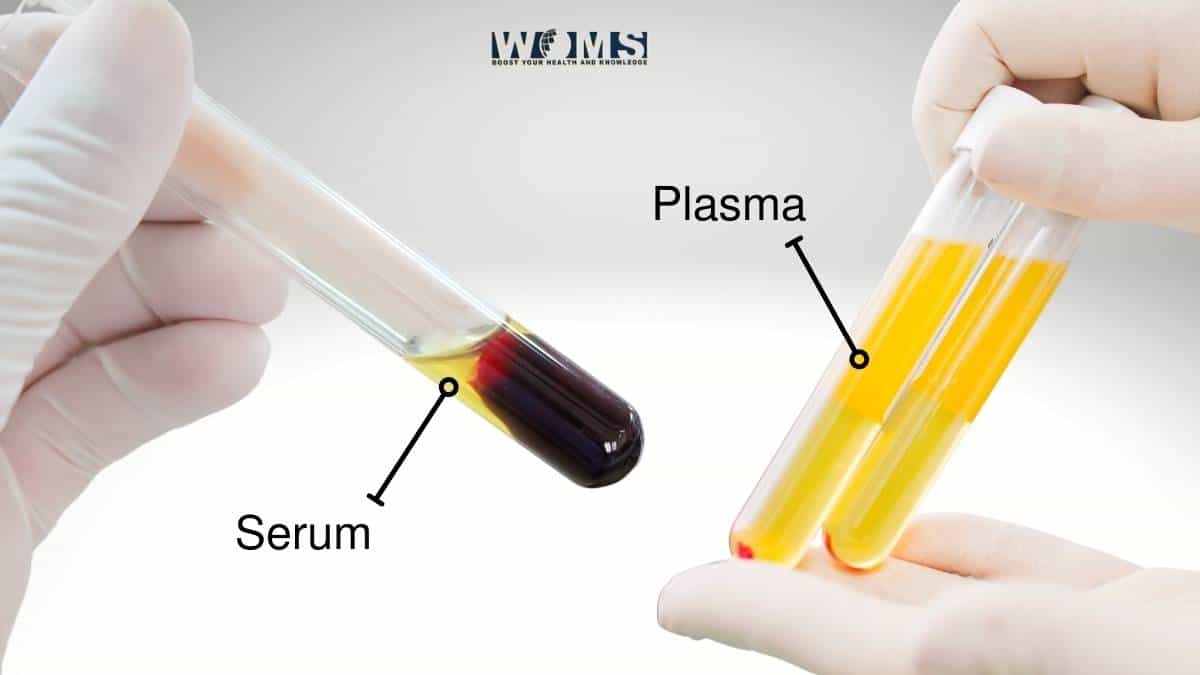
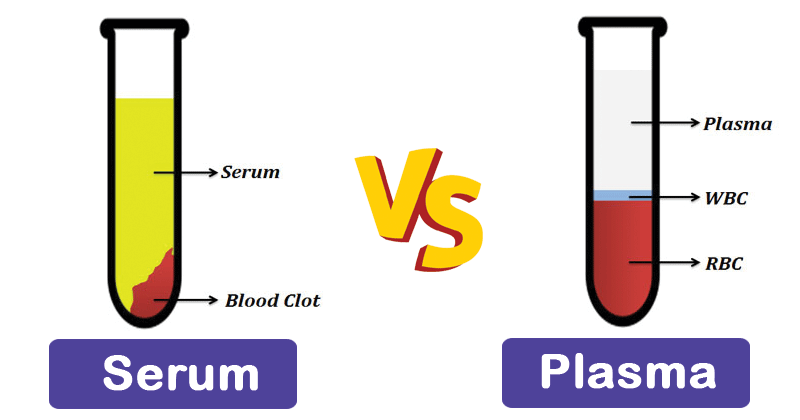
They come from the same source, but the processing path determines which one you're actually working with. Serum is what remains after blood has clotted and been spun down. Plasma is the liquid portion when you prevent clotting from the start. This sounds simple on paper, but it costs people samples regularly because the differences matter more than most protocols acknowledge. For serum, you draw blood into a tube with no additive—usually a plain red-top tube or a clot activator tube with silica particles. Let it stand upright at room temperature for 30 to 60 minutes. The blood has to clot fully before you touch the centrifuge. Spin it at 1500 to 2000 g for 10 minutes. The liquid sitting above the clot and the pellet is your serum. If you spin too early, you'll pull up fibrin strands that clog pipette tips and ruin assays later. For plasma, you need an anticoagulant in the collection tube. EDTA tubes (lavender top) are standard for molecular work. Heparin tubes (green top) work for chemistry panels. Potassium oxalate with sodium fluoride (gray top) is for glucose testing. Draw the blood, invert gently three to five times right away, and spin within two hours. The same speed and time as serum works fine. The liquid above the cellular layer is your plasma.
I once ran a batch of proteomics samples where the technician used EDTA plasma for a phosphorylation study without realizing that EDTA strips divalent cations from the reaction buffer. The kinase activity readings came back at near zero across the board. We lost a week and had to rerun everything with heparin plasma instead. It cost roughly $3,000 in reagents and labor that shouldn't have been spent at all.
Why the Choice Matters Beyond the Collection Tube
Plasma contains fibrinogen and other clotting factors because the coagulation cascade never fires. Serum has those proteins consumed during clot formation. If your assay depends on detecting fibrinogen or related biomarkers, plasma is your only option. You get higher volume from plasma too—roughly 10 to 15 percent more per draw—because the serum shrinks as the clot traps a portion of the liquid. Platelets are another factor. They release granule contents during clotting, which means serum has elevated concentrations of platelet-derived growth factor, PDGF, and beta-thromboglobulin compared to plasma. That's useful if you're studying those molecules intentionally, but it's noise if you're measuring cytokines or growth factors in a cancer panel. Platelet activation during clot formation can inflate IL-6 readings by tenfold or more in some cases. The pH difference is real and often overlooked. Plasma runs slightly more acidic than serum, around 7.35 compared to 7.40 or so, because the clotting process consumes bicarbonate. For assays with tight pH dependence, this shifts equilibrium constants enough to move your standard curve readings. You should always match your calibrators to your sample type.
Get the Full Details

Edge Cases and Where Each One Fails
Plasma is not a universal improvement. Hemolysis shows up differently in each matrix. Red blood cell rupture releases intracellular contents into the liquid, and this happens faster in plasma because the anticoagulant doesn't trigger the same stabilization effect that a forming fibrin mesh provides. If you're doing hemolyzed sample analysis, serum is more forgiving on first pass. Free DNA work has flipped the script in recent years. Circulating tumor DNA and fetal DNA studies typically use plasma because the clotting process in serum preparation releases genomic DNA from dying white blood cells, inflating background noise. Liquid biopsy protocols specify plasma for this reason, and using serum instead will drown out your signal. The turnaround is faster with plasma too since you skip the 30 to 60 minute wait for clotting. Serum freezes harder than plasma in practice. The absence of anticoagulant means different protein interactions during thawing, and I've seen serum samples develop fine precipitates after a single freeze-thaw cycle that plasma never showed. If you're doing repeated aliquoting, plasma stores more consistently across multiple thaw events.
Some analytes are simply unstable once the clotting cascade begins. Complement proteins C3 and C4 degrade during clot formation, so any immunology work involving those markers must use plasma collected on ice and processed quickly. Glucose drops in serum over time due to ongoing glycolysis in trapped cells, even after clotting. Fluoride tubes prevent this, but only if you started with the right tube type from the draw.
What Beginners Get Wrong
The biggest mistake is assuming you can swap one for the other in an established protocol without revalidating. Reference ranges differ between serum and plasma for many analytes. Sodium, for example, runs about 3 to 5 percent higher in plasma than in serum because water shifts into the cellular phase during clotting. If you apply a serum reference interval to a plasma result, you will flag normal values as abnormal. This happens in clinical labs more often than anyone wants to admit. A second mistake is improper mixing of anticoagulant tubes. Invert gently. Vigorous shaking creates foam and hemolysis. I once received a shipment of 48 EDTA tubes that had been shaken during transport, and every single sample showed elevated potassium from ruptured red cells. The samples were unusable for electrolyte testing and had to be recollected. Third, people centrifuge at the wrong speed for their application. A standard 1500 g spin leaves platelets in plasma. If you need platelet-poor plasma for coagulation studies or certain immunoassays, you need a second spin at 2000 to 2500 g after the first separation. Skipping this step introduces platelet contaminants that interfere with light scattering readings in spectrophotometric assays.
Practical Recommendation
Use plasma when you need maximum sample volume, are working with labile analytes, or doing cell-free DNA analysis. Use serum when your protocol is already validated for it and you want to avoid anticoagulant interference with downstream chemistry. Know your analyte stability profile before you commit to one matrix. Once you pick a type, stick with it across your entire study. Mixing serum and plasma data from the same project introduces systematic bias that no amount of statistical correction will fully remove. The choice between them isn't about preference. It's about what stays stable in your sample and what your assay can tolerate. Get the tube right at the draw, process it promptly, and don't let someone save thirty seconds by skipping the clotting wait when serum is what your method requires.