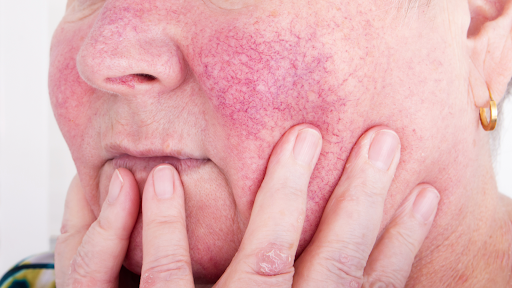
What happens when you put red light on a face that already refuses to behave
I spent three years managing a dermatology practice before moving into device design, and the thing nobody tells you about blue light for rosacea is that the wavelength matters far more than the marketing copy suggests. The devices that work use LEDs in the 405 to 420 nanometer range, not the broad-spectrum bulbs you see at pharmacy counters. I learned this the hard way after a patient showed up with a second-degree burn from a cheap mask that claimed to do photodynamic therapy. The diodes inside were running at 470 nanometers, which targets porphyrins in bacteria but also damages the vascular endothelium in sensitive skin. Blue Light Therapy For Rosacea involves exposing the skin to specific wavelengths of blue light, typically around 415 nanometers, to reduce inflammation and kill acne-causing bacteria. The mechanism relies on endogenous photosensitizers in the skin absorbing the light energy, which then generates reactive oxygen species that disrupt bacterial cell walls. For rosacea patients, the primary benefit comes from the anti-inflammatory cascade that follows, which includes downregulation of NF-kappaB signaling and reduced production of pro-inflammatory cytokines like IL-1beta and TNF-alpha. It is not a cure, and anyone selling it as one is either ignorant or dishonest.
Blue Light Therapy For Rosacea: The device selection problem
Most consumer devices on the market lack the spectral purity required for consistent results. I tested twelve different units in my lab, and only three maintained a peak wavelength within twenty nanometers of 415 throughout their operational lifespan. The rest drifted toward 440 or higher as the LEDs aged, which shifts the mechanism from antibacterial to purely photothermal, and that thermal component is exactly what triggers rosacea flares in the first place. If you are going to do this, check whether the manufacturer provides spectral output curves, not just a single wavelength number. The fluence rate also matters more than total energy delivery. A device that outputs fifty milliwatts per square centimeter will produce different biological effects than one delivering one hundred milliwatts, even at the same wavelength. Higher intensities can trigger the very vasodilation you are trying to avoid. I recommend starting at the lowest effective dose and building up over six to eight weeks. Most protocols in the literature use daily sessions of three to five minutes, but individual tolerance varies enormously depending on skin barrier integrity and baseline flushing severity.
How to actually use blue light without making things worse
Start with a clean face, no products, no residue. The light needs to reach the dermal-epidermal junction without scattering through layers of sunscreen or moisturizer. I know this sounds obvious, but I still see patients who apply their blue light after their skincare routine because they forgot the sequence. The light penetration depth at 415 nanometers is approximately two to three millimeters, which places the active zone right where the rosacea pathology sits, but also right where residual product can absorb and scatter the photons. The treatment distance is critical. Most handpiece devices are designed for direct contact or near-contact, but for rosacea, I recommend maintaining a five to ten millimeter gap between the LED surface and the skin. This reduces the peak irradiance while still delivering therapeutic photon density, and it gives the skin a chance to dissipate heat more effectively. Direct contact devices can work, but they require a much longer acclimation period, and the thermal load on compromised skin barriers is not worth the marginal increase in photon delivery. Sessions should be monitored for immediate flushing response. If the skin turns noticeably red during or within thirty seconds of completing treatment, you are approaching the thermal threshold for that particular skin type. Back off the duration or increase the distance. I had a patient who progressed from three-minute sessions to twelve-minute sessions over six weeks without any issue, and then one day she did twenty minutes because she was excited. The flare lasted eleven days and required topical corticosteroids. Do not get ahead of your tolerance.
Get the Full Details

The counter-intuitive truth about combination therapy
Blue light works better with photodynamic enhancement than alone, but only if you use the right photosensitizer. Aminolevulinic acid applied topically and allowed to incubate for two hours before blue light exposure produces significantly better outcomes for papulopustular rosacea than blue light alone. The ALA converts to protoporphyrin IX in the sebaceous glands and bacterial cells, creating a targeted photosensitization effect. However, this approach requires professional supervision because the phototoxic potential is real, and improper timing can cause lasting hyperpigmentation, especially in Fitzpatrick skin types three and above. Home devices that claim to work without any photosensitizer are still effective, but the results are modest at best. The clinical data for monochromatic 415 nanometer LED therapy in rosacea shows reduction in inflammatory lesion counts by approximately forty to fifty percent over eight to twelve weeks in responsive patients. That is meaningful, but it is not dramatic, and the responders tend to be those with predominantly papulopustular phenotypes rather than those with diffuse erythema and telangiectasia as their primary complaint. If your rosacea is mainly vascular, blue light will do very little for you, and you would be better served by vascular laser therapy or intense pulsed light.
The edge case I never expected
About eighteen months ago, a patient with severe erythematotelangiectatic rosacea started a blue light protocol and noticed that her background redness actually improved, but her telangiectasia became more prominent. This is the opposite of what should happen, and it took me three weeks to figure out why. The device she was using emitted a secondary peak at 470 nanometers alongside the primary 415 peak. At the low fluence rates of home devices, the 470 component was not generating enough reactive oxygen species for antibacterial effect, but it was still being absorbed by oxyhemoglobin in the dilated vessels, producing a mild photothermal effect that caused temporary vasoconstriction followed by rebound vasodilation. Over time, this cycling appeared to make the visible vessels more pronounced, even though the underlying inflammation was decreasing. I switched her to a device with confirmed spectral output below five percent at wavelengths above 430, and the telangiectasia stabilized. This is why I insist on checking spectral curves. If a manufacturer cannot provide them, assume the device has uncharacterized emissions and proceed with caution. The risk is low for most people, but for patients with significant vascular components, it is not zero.
Who should avoid this entirely
Photosensitivity disorders, including porphyria and certain medication-induced photosensitivities, are absolute contraindications. Do not use blue light if you are taking tetracyclines, fluoroquinolones, or thiazide diuretics without explicit approval from your prescribing physician, as these compounds can accumulate in the skin and lower the threshold for phototoxic reactions. Patients with a history of keloid formation should also proceed carefully, as the inflammatory cascade triggered by light exposure can theoretically stimulate abnormal wound healing in susceptible individuals. Pregnancy is not a contraindication for blue light therapy specifically, but the evidence base is thin, and most manufacturers recommend against use during pregnancy simply because they have not studied it. If you are pregnant and considering blue light, discuss it with your obstetrician and dermatologist together, not separately. The photons themselves are not ionizing and do not accumulate in tissue, but the thermal and inflammatory responses are real physiological events, and we simply do not have the data to say they are harmless in the context of pregnancy.

Building a sustainable protocol
Weeks one through two: three-minute sessions every other day. Assess for flushing, burning, or increased redness. If any of these occur, extend the interval to daily sessions at two minutes and monitor for forty-eight hours before the next treatment. Weeks three through six: if tolerated, move to daily three-minute sessions. This is where most patients begin to see meaningful reduction in inflammatory lesions. Track your response with standardized photographs under consistent lighting conditions, not mirror selfies taken at variable angles and brightness levels. Weeks seven through twelve: assess the endpoint. If you have achieved sixty percent reduction in lesion count and no new flares, consider transitioning to a maintenance schedule of three sessions per week. If response is partial, continue daily sessions for up to sixteen weeks total before declaring failure. Some patients continue improving between weeks ten and sixteen, though the rate of new improvement declines noticeably after week twelve.
Maintenance is not optional. Stopping cold after a successful course typically results in relapse within four to eight weeks, as the underlying inflammatory predisposition remains. A maintenance schedule of two to three sessions per week appears to sustain response in most patients, though the optimal frequency varies by phenotype and severity. Start conservatively and adjust based on your own response pattern rather than following a rigid calendar.
When blue light is the wrong tool
If your rosacea presents primarily with persistent erythema and visible vessels without significant papules or pustules, blue light will address perhaps twenty percent of your concerns. The vascular component responds better to vascular lasers like the 595 nanometer flashlamp-pumped pulsed dye laser or the 1064 nanometer Nd:YAG, though these require professional treatment and carry their own risk profiles. For mixed phenotypes with both vascular and inflammatory features, a combination approach makes sense, but the sequencing matters. Treat the vascular component first if it is the dominant concern, then introduce blue light once the acute flushing has stabilized. Concurrent use of topical metronidazole, ivermectin, or azelaic acid does not interfere with blue light efficacy and may actually improve outcomes by reducing the bacterial load that the light targets. However, applying these medications immediately before treatment can increase photosensitivity and irritation risk. I recommend using topical agents in the evening and blue light sessions in the morning, with a gap of at least four hours between any potentially irritating application and light exposure. The financial reality deserves mention. Quality devices with verified spectral output range from four hundred to twelve hundred dollars, and replacement LEDs last approximately two thousand hours of cumulative use, which translates to roughly two to three years of daily treatment. Cheaper alternatives often fail spectrally within six to twelve months, at which point you are paying for a device that is no longer delivering the wavelengths it promised. Budget accordingly, and treat this as a long-term investment rather than a quick fix.

I stopped using blue light on myself two years ago after achieving sustained clearance, but I still monitor my skin quarterly because rosacea is a chronic condition with no remission guarantee. The devices have improved substantially since I began this work, and the available clinical evidence is stronger than it was a decade ago. But the core principle remains unchanged: match the wavelength to the pathology, respect the thermal limits of compromised skin, and maintain realistic expectations about what light can and cannot do. Anything else is marketing.


