Understanding Board-Based Radiation Therapy Setup
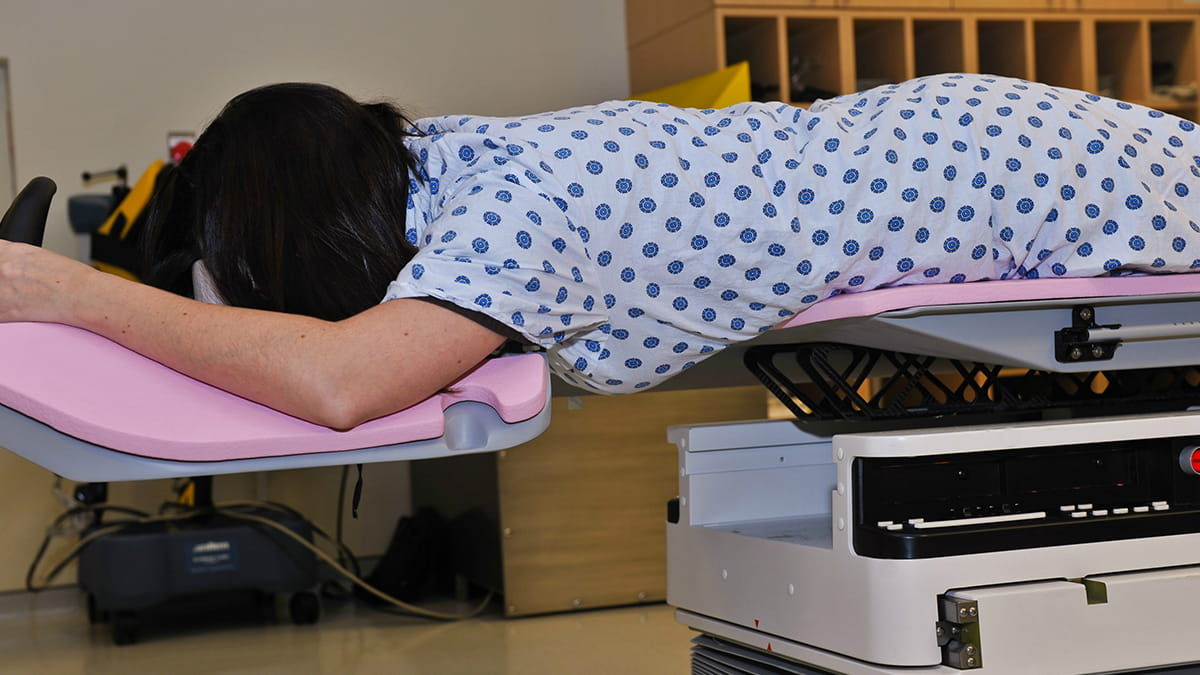
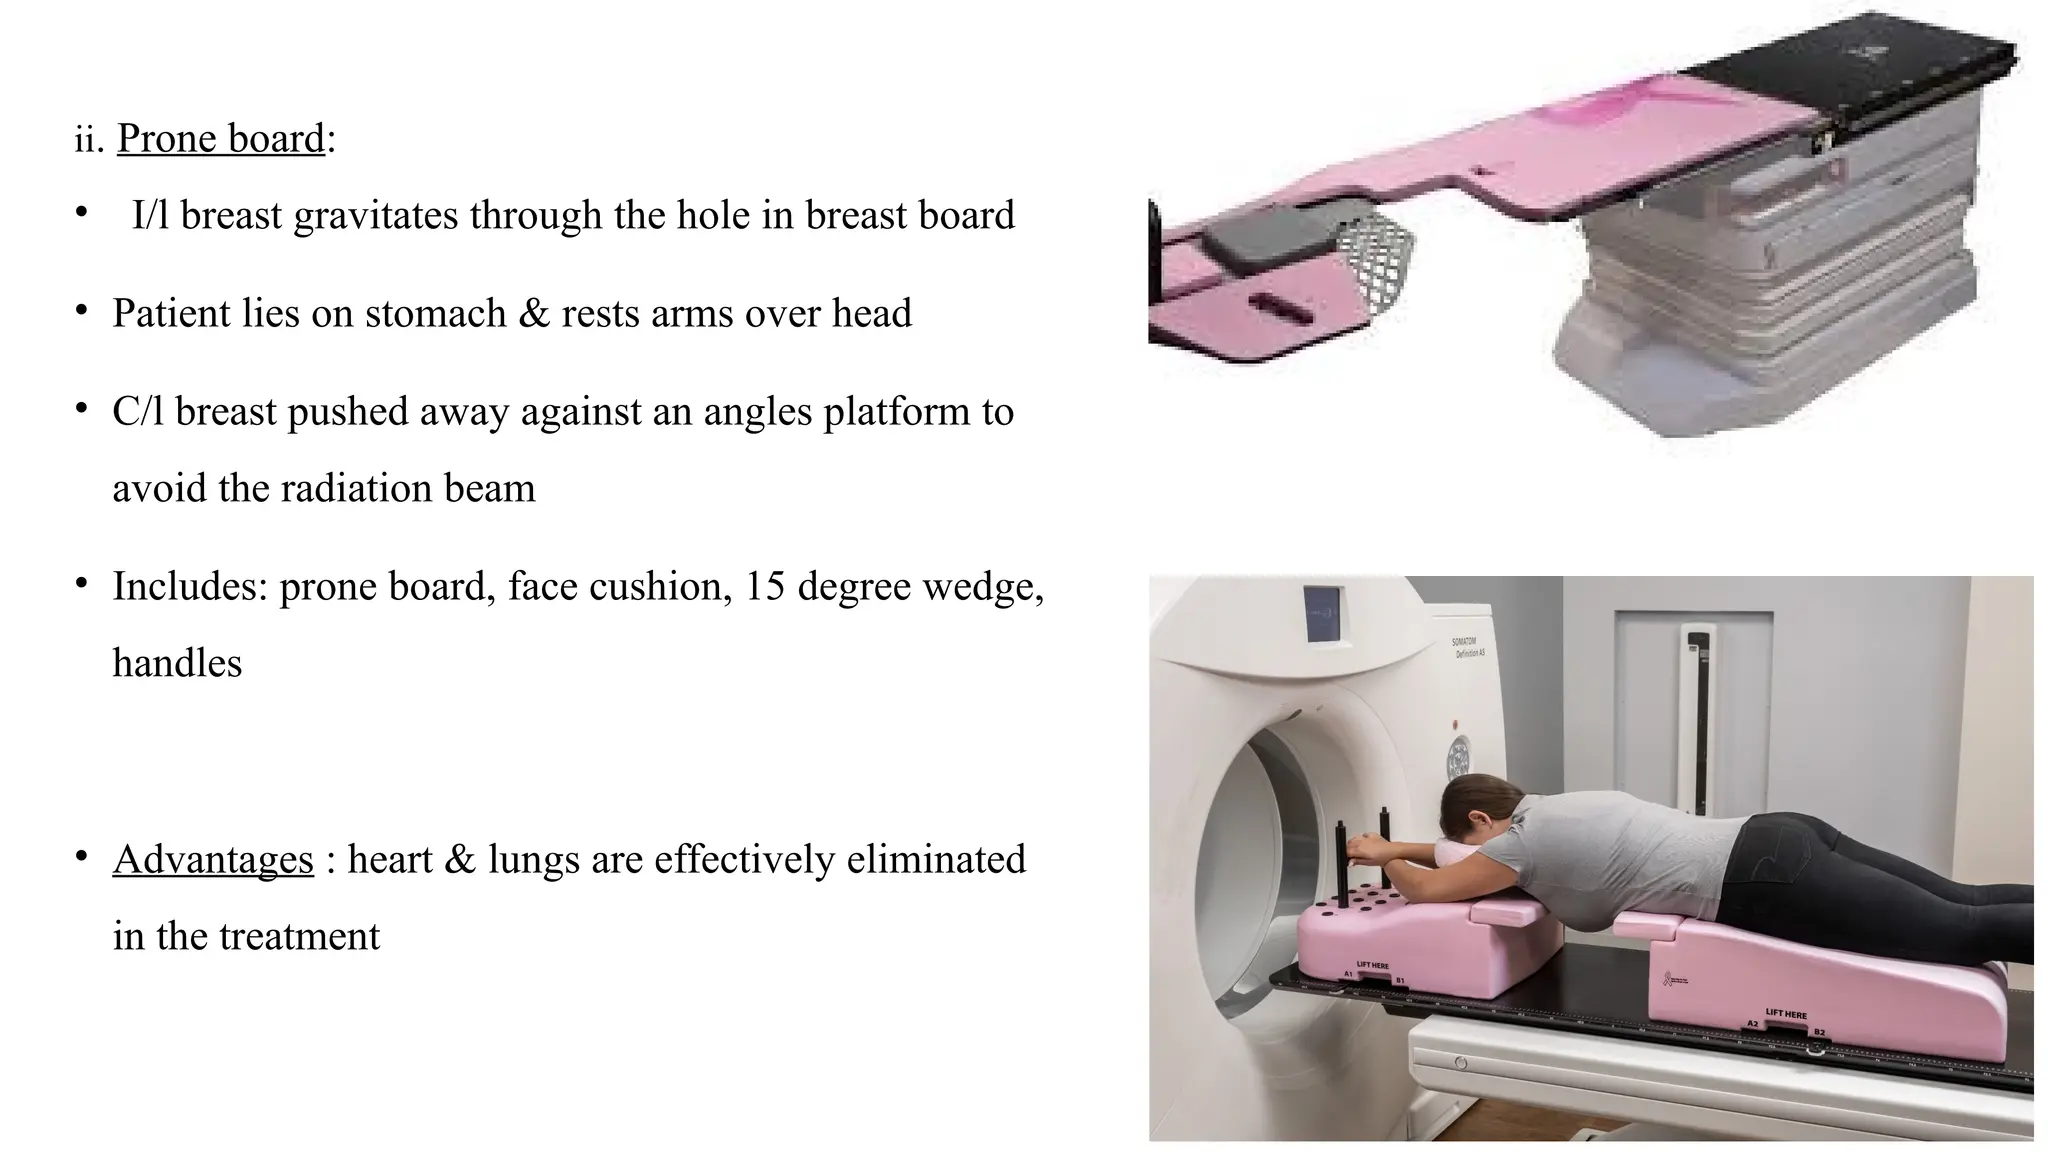
Board radiation therapy refers to the practice of using customized positioning boards and compensating devices during external beam radiation treatment. These boards are typically made from low-density materials like foam, plaster, or specialized polymers, and they serve two main purposes: patient immobilization and dose compensation for irregular anatomical surfaces. When you're treating a curved surface like a breast or head and neck region, a flat radiation beam will hit some areas harder than others. The board helps level the playing field by adding material where the beam needs extra attenuation or by physically supporting the patient in a reproducible position. I spent a good chunk of my early career dealing with breast treatment boards, and honestly, they're one of those things that seem straightforward until you actually try to optimize them. The basic workflow starts with a CT scan of the patient on the board itself. Not on a flat couch, not on a generic positioning pad — on the actual board that will be used during treatment. This is where most people go wrong. If you simulate on a different surface, the beam geometry changes, and your dose calculations become unreliable. I once had a case where a clinic was reusing older boards for new patients without rescanning them, and the dose uniformity in the deep portion of the breast was off by nearly 15 percent. That's clinically significant. The board material itself matters more than you'd think. Traditional foam boards are cheap and easy to machine, but they degrade over time, especially with repeated sterilization. Polystyrene foam absorbs moisture and can warp, which shifts the patient's position between fractions. I switched to water-equivalent urethane foam boards for our head and neck cases, and the difference in reproducibility was noticeable after about six weeks of daily use. The initial cost is higher, maybe three to four times that of standard foam, but you're saving time on repositioning and reducing the chance of a setup error that would require a repeat scan.
How to Create and Use a Treatment Board
Start with a CT simulation. The patient should be positioned exactly as they will be for treatment, wearing any masks, braces, or supports they'll use throughout the course. Capture the scan with a slice thickness of no more than three millimeters. Anything thicker and you lose detail when you're designing the board contours later. Once the scan is complete, the data goes to your treatment planning system or a dedicated board design workstation. Most modern TPS packages have a board generation module built in. You select the region of interest — the area the radiation beam will cover — and the software creates a compensating structure that matches the patient's surface topography. The key parameter here is the air gap. This is the distance between the patient's skin and the surface of the board in the treatment field. For most megavoltage photon treatments, you want an air gap of roughly five to ten millimeters. Too much gap and you lose dose build-up. Too little and the board material interferes with the beam entrance, creating hot spots. After the design is finalized, the board is manufactured. If you're doing this in-house, a CNC router or a thermal wire cutter works fine for foam boards. I've seen clinics use a simple hot-wire cutter for quick modifications between fractions — useful when a patient loses weight during treatment and the board no longer fits snugly. For patient-specific compensators made from higher-density materials, you'll need to send the design to a medical device manufacturer. Lead or brass compensators are machined from the same CT data, but they add complexity because they introduce additional scatter. I prefer to avoid metal compensators whenever possible and stick with tissue-equivalent board materials. The dose calculation is simpler and more accurate.
Once the board is ready, verify it against the CT scan. Place the board on the treatment couch and run a test beam. Check the dose distribution on a film or electronic portal imaging device. If the board was designed correctly, the dose profile across the treatment field should be uniform within acceptable tolerances — usually plus or minus five percent for the target volume. I learned this the hard way with a pelvic board where the compensation was calculated for the wrong isocenter depth. The central portion of the field was receiving about twenty percent more dose than planned. We caught it during the verification scan, but it could have been a serious problem if we hadn't bothered to check.
Get the Full Details
Common Pitfalls and Limitations
Board radiation therapy is not a universal solution. It works well for superficial and moderately deep targets where surface conformity matters. It breaks down when you're dealing with large field sizes greater than twenty by twenty centimeters — the board becomes too heavy and awkward to handle, and the structural integrity of the material starts to matter. A foam board that large will sag under its own weight, especially if it's mounted at an angle. I've had to reinforce large breast boards with a rigid backing frame, which adds time to the fabrication process and introduces another point of potential misalignment. Another limitation is that board therapy assumes the patient remains in the exact same position for every fraction. This sounds obvious, but it's not always true. Patients move. They get tired. Their anatomy changes. A board that fits well on day one might not fit well on day fifteen after tumor shrinkage or weight loss. The workaround is to schedule mid-treatment CT scans — not every clinic does this, and insurance coverage varies — but it's the only reliable way to know whether your board is still doing its job. There's also the question of dose calculation accuracy. Most treatment planning systems model board materials using effective atomic number approximations. This works fine for simple geometries but becomes less reliable when the board has complex internal structures or when you're using high-Z compensating materials. I recommend always cross-checking your plans with an independent dose calculation, especially for the first patient you treat with a particular board design. A twenty-minute check can save you from a systematic error that would otherwise go unnoticed across an entire treatment course.
The bottom line is that board radiation therapy is a practical tool when used correctly, but it requires attention to detail at every step — from simulation through manufacturing to quality assurance. The margin for error is smaller than most people assume, and the consequences of getting it wrong are real. If you're just starting out, don't skip the verification step. It takes longer upfront but prevents far more expensive problems down the line.