Body Cavities And Membranes: A Practical Walkthrough
Most anatomy students learn the ventral and dorsal cavities as a list to memorize before a practical exam. They pass, then forget it all a month later. The real utility comes when you understand how these spaces actually function during surgery, imaging, or when complications arise. This is where the memorization hits a wall and actual knowledge kicks in.The Basic Layout (Because You Still Need It)
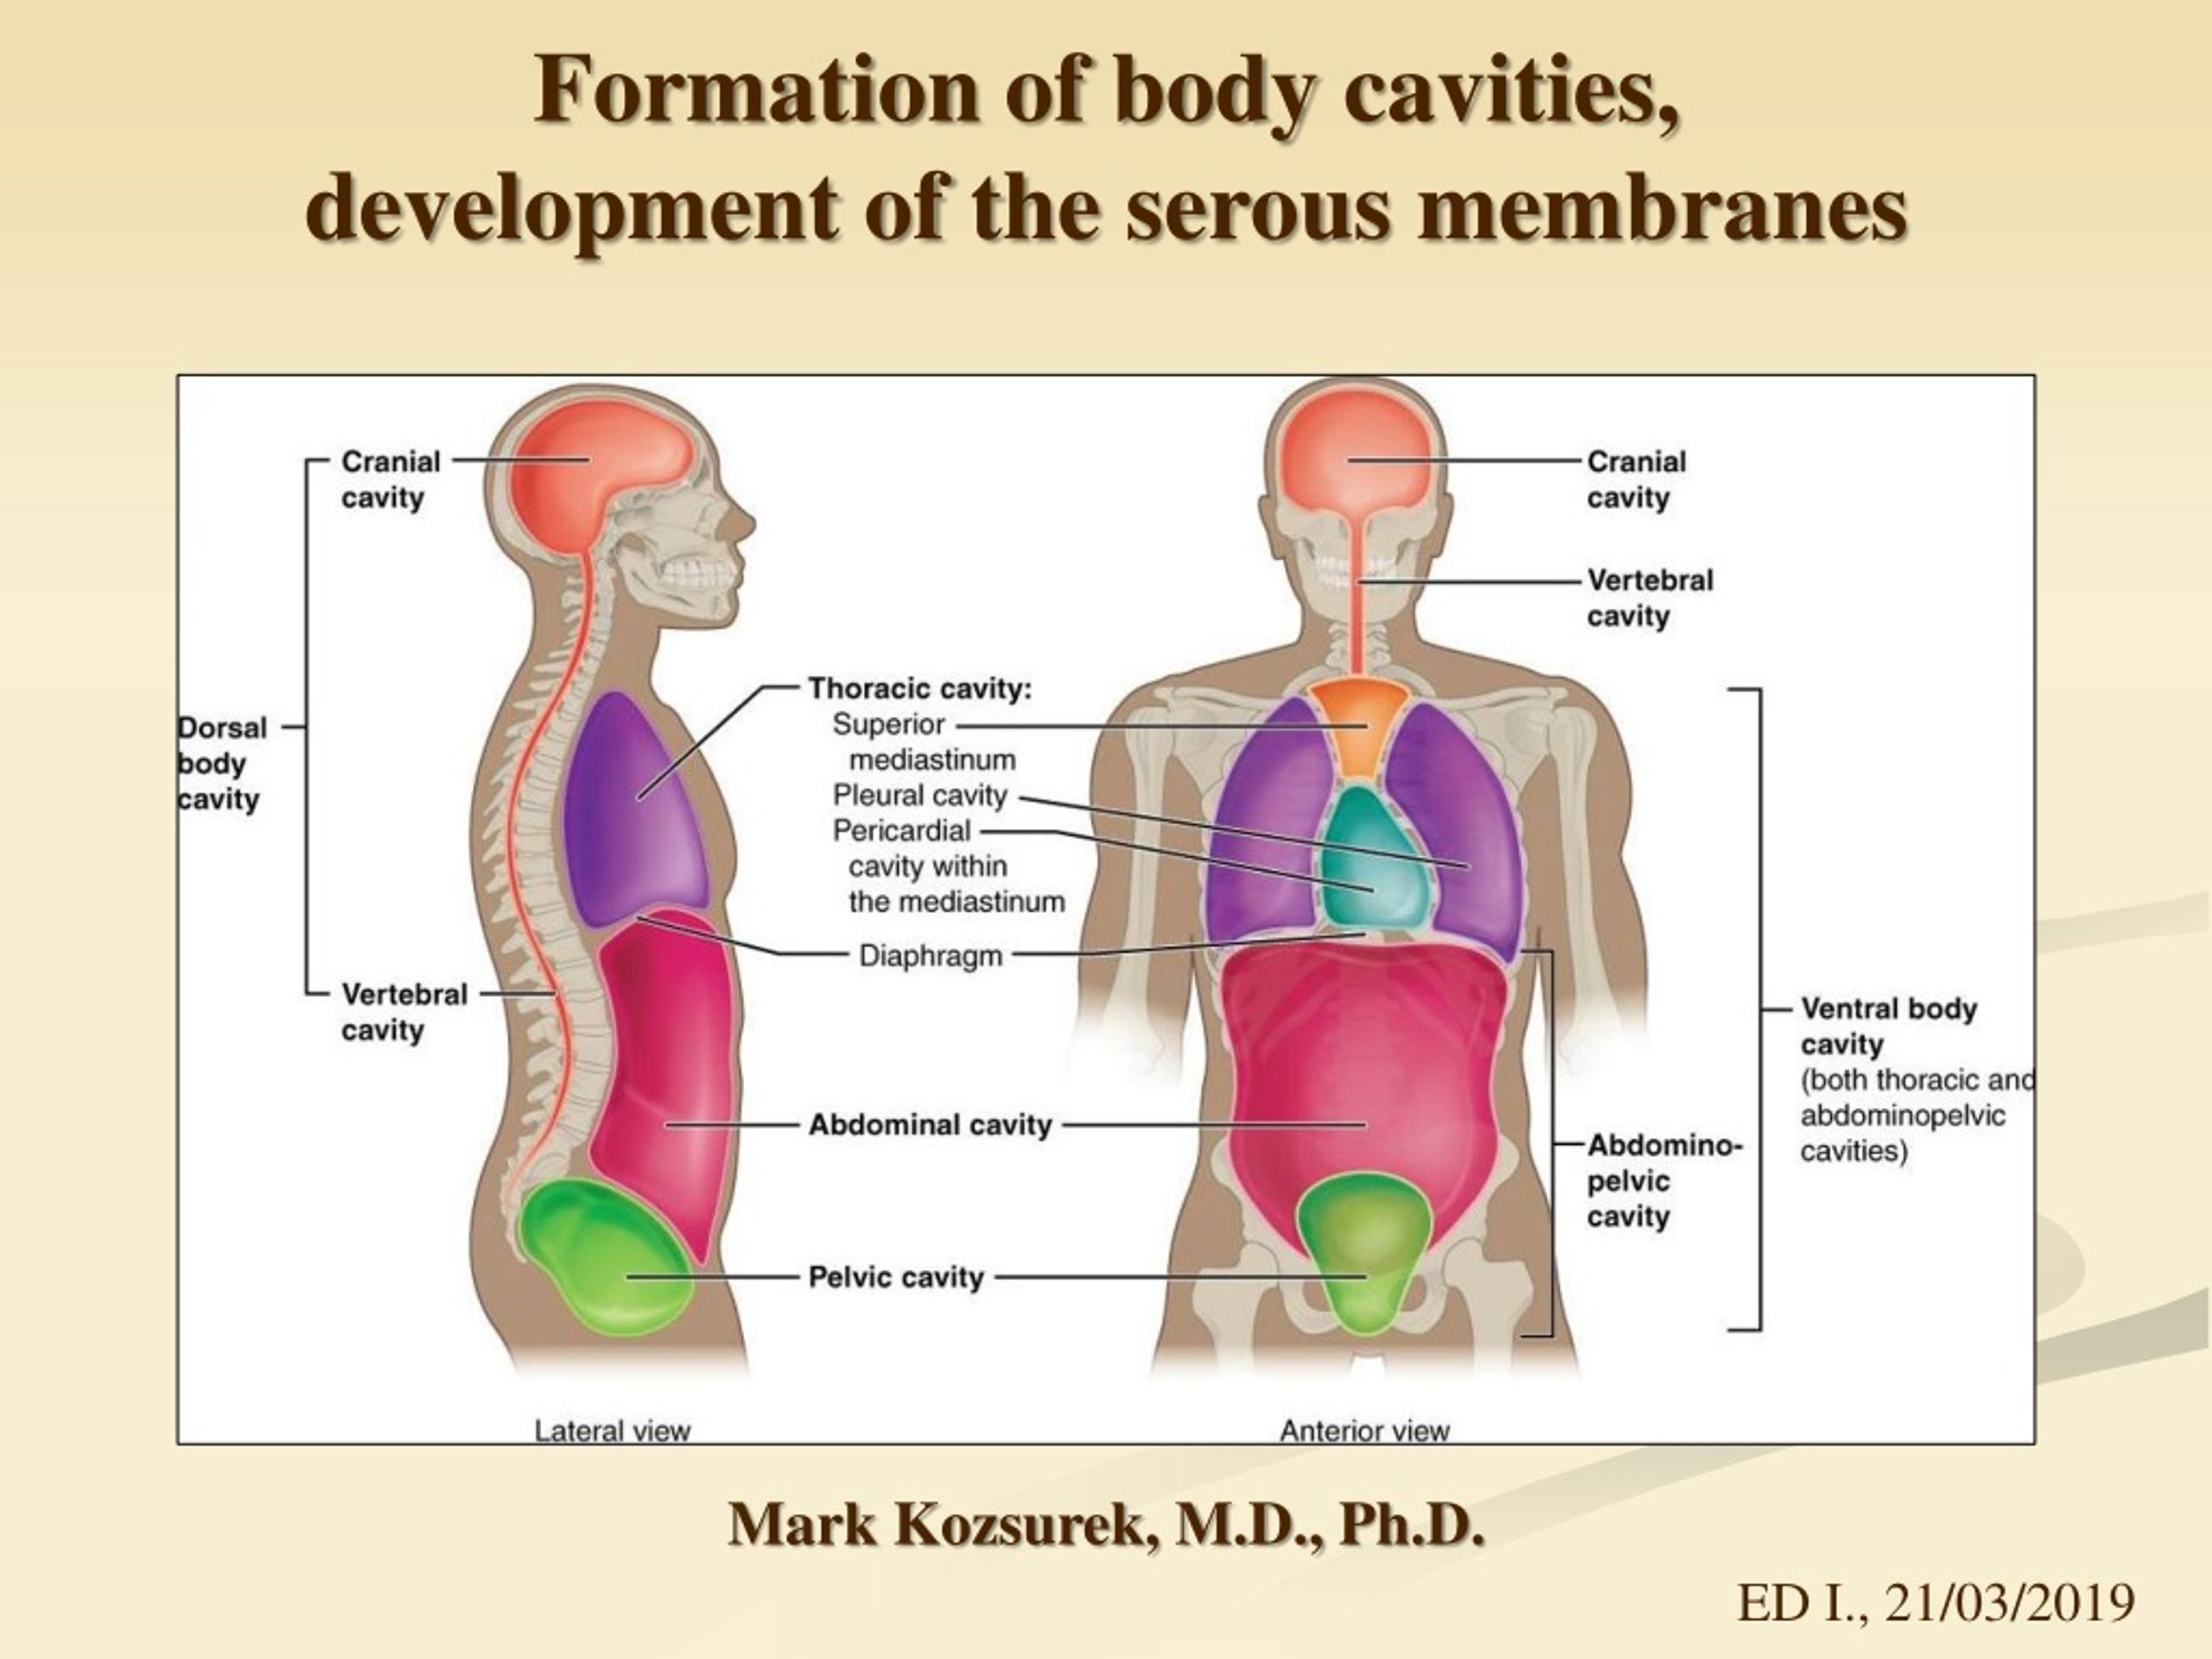
The body has two major cavity divisions. The dorsal cavity houses the central nervous system, split into the cranial cavity for the brain and the vertebral cavity for the spinal cord. The ventral cavity is the bigger one and the messier one in practice. It divides into the thoracic cavity and the abdominopelvic cavity. Within the thoracic cavity, you have the mediastinum in the center containing the heart and pericardial cavity, and on either side the pleural cavities around each lung. The abdominopelvic cavity is further divided into the abdominal cavity with its digestive organs and the pelvic cavity with the reproductive and urinary structures. That last division is mostly arbitrary from an anatomical standpoint since there's no physical barrier separating them.The thin layer separating all of this is the serous membrane, or serosa. Every ventral cavity is lined by a double-layered serous membrane. The parietal layer sticks to the cavity wall. The visceral layer wraps the organs. Between them is a thin film of serous fluid. Without that fluid, every heartbeat, every breath, every peristaltic wave would create painful friction between organs and their housing walls.
Why The Terminology Confuses Everyone (And What To Do About It)
Here's where people trip up. The same basic membrane structure gets different names depending on which cavity it lines. Parietal pleura and visceral pleura around the lungs. Parietal pericardium and visceral pericardium around the heart. Parietal peritoneum and visceral peritoneum around the abdominal organs. They're all the same tissue type, just different locations. Memorizing separate names for each one is unnecessary work. Learn the pattern once and you've learned it for all of them.The peritoneum is the exception that proves the rule because it's complicated by design. It forms a single continuous sac that folds back on itself, creating layers, spaces, and connective bridges called mesenteries. The greater omentum hangs off the stomach like an apron. The mesentery attaches the small intestine to the posterior abdominal wall. These aren't just decorative structures. They carry blood vessels, nerves, and lymphatics to the organs they suspend.
A Real Problem I Ran Into With The Peritoneal Cavity
A few years back I was working with a surgical team reviewing imaging for a patient who needed an appendectomy. The pre-op CT showed a localized abscess near the appendix. The standard approach would be a laparoscopic entry, but the abscess had created adhesions between the bowel and the anterior abdominal wall. If we'd just punctured the standard three ports without understanding exactly where those adhesions were, we could have punctured bowel on insertion.The workaround was straightforward once you think about it correctly. We used an open technique (Hasson method) for the initial trocar entry at the umbilicus, visually confirming we were entering the peritoneal cavity without resistance. Then we placed the other two ports under direct vision while rotating the camera to identify safe windows away from the adhesions. It added maybe eight minutes to the procedure but prevented what could have been a bowel injury requiring conversion to open surgery. This is the kind of thing that only becomes relevant when you actually understand the three-dimensional relationship between the peritoneal layers, the mesenteries, and the abdominal wall.
Serous Membranes: How They Actually Work In The Body
Serous membranes are simple squamous epithelium called mesothelium sitting on a thin layer of connective tissue. The mesothelium produces the serous fluid through ultrafiltration of plasma. The fluid is low in protein compared to blood plasma, which is why it's not sticky. That low viscosity is what allows organs to glide smoothly against each other. When inflammation hits a serous membrane, everything changes. Pleurisy makes breathing painful because the inflamed pleural layers rub together instead of sliding. Peritonitis from a ruptured appendix turns the entire abdominal cavity into a landscape of adhesive bands as the body tries to wall off the infection. The serous fluid becomes purulent or fibrinous. Organs stick to each other. This is why post-surgical adhesions are one of the most common causes of bowel obstruction decades after an operation. There's a clinical detail most students miss. The costodiaphragmatic and costomediastinal recesses of the pleural cavity are the lowest points when a person is upright. Fluid from pleural effusions collects there first. On an upright chest X-ray, you see blunting of the costophrenic angles. On a lateral decubitus film, the fluid layers out along the chest wall. Knowing where fluid goes is more useful than knowing every named recess.Body Cavities And Membranes In Clinical Practice
Paracentesis is the procedure where this knowledge matters most in everyday practice. Draining ascitic fluid from the peritoneal cavity sounds simple. Stick a needle in the abdomen, let the fluid out. The problem is knowing exactly where to stick it. The standard site is the left lower quadrant, about two to three centimeters medial and superior to the anterior superior iliac spine. You avoid the midline because the falciform ligament and linea alba have variable vascular patterns. You avoid the lower quadrants too far medially because the inferior epigastric vessels run there and a nick them and you've got a hematoma.I once watched a resident miss by about a centimeter and hit bowel because they were using surface landmarks without accounting for the fact that a distended bladder pushes bowel upward. A quick bedside ultrasound would have shown the fluid pocket and the bowel displacement in thirty seconds. That's the gap between textbook anatomy and real anatomy. Bodies aren't uniform. Landmarks shift with pathology, body habitus, and even breathing phase. The mucous membranes deserve a mention because they're often grouped with serous membranes in textbooks but they're structurally different. They line body cavities that open to the exterior. Respiratory, digestive, urinary, and reproductive tracts. They produce mucus instead of serous fluid. The function is protection and lubrication rather than friction reduction between organ surfaces. Don't confuse them on an exam.
Get the Full Details

What This Approach Won't Tell You
Cadaver-based anatomy has a fundamental limitation that no textbook addresses adequately. Tissues lose their tension after death. Organs settle. Fascial planes that are tight in a living person become loose and indistinct. The peritoneal reflections that are crisp on a diagram are often or collapsed in a specimen. Surface landmarks on a corpse don't always correlate with what you'll find during live surgery or ultrasound. This is why imaging-based anatomy and surgical experience matter more than gross dissection for clinical application.Another limitation is that body cavity volumes vary significantly between individuals. A large person and a small person have very different peritoneal cavity capacities. Ascites of two liters might be barely noticeable on a chest X-ray in a tall thin patient but cause visible diaphragmatic elevation in someone shorter. Volume estimates from textbook numbers are starting points, not rules. For students who want to actually visualize these structures rather than just label them, interactive 3D anatomy platforms like Complete Anatomy or Visible Body give you rotation and layering that a static diagram never will. They're not free, but the time saved in understanding spatial relationships usually justifies the cost if you're in a clinical program. Free alternatives exist too. Human Anatomy Atlas has a decent free tier, and the Netter's Atlas app is worth it if you can find a license through your school. The key takeaway isn't memorizing every named recess or listing every organ in each cavity. It's understanding that these membranes create potential spaces where fluid can accumulate, where infection can spread, and where surgical access requires knowing exactly what lies between the skin and the target. The anatomy is consistent in principle but wildly variable in practice. Treat it that way and you'll be fine.