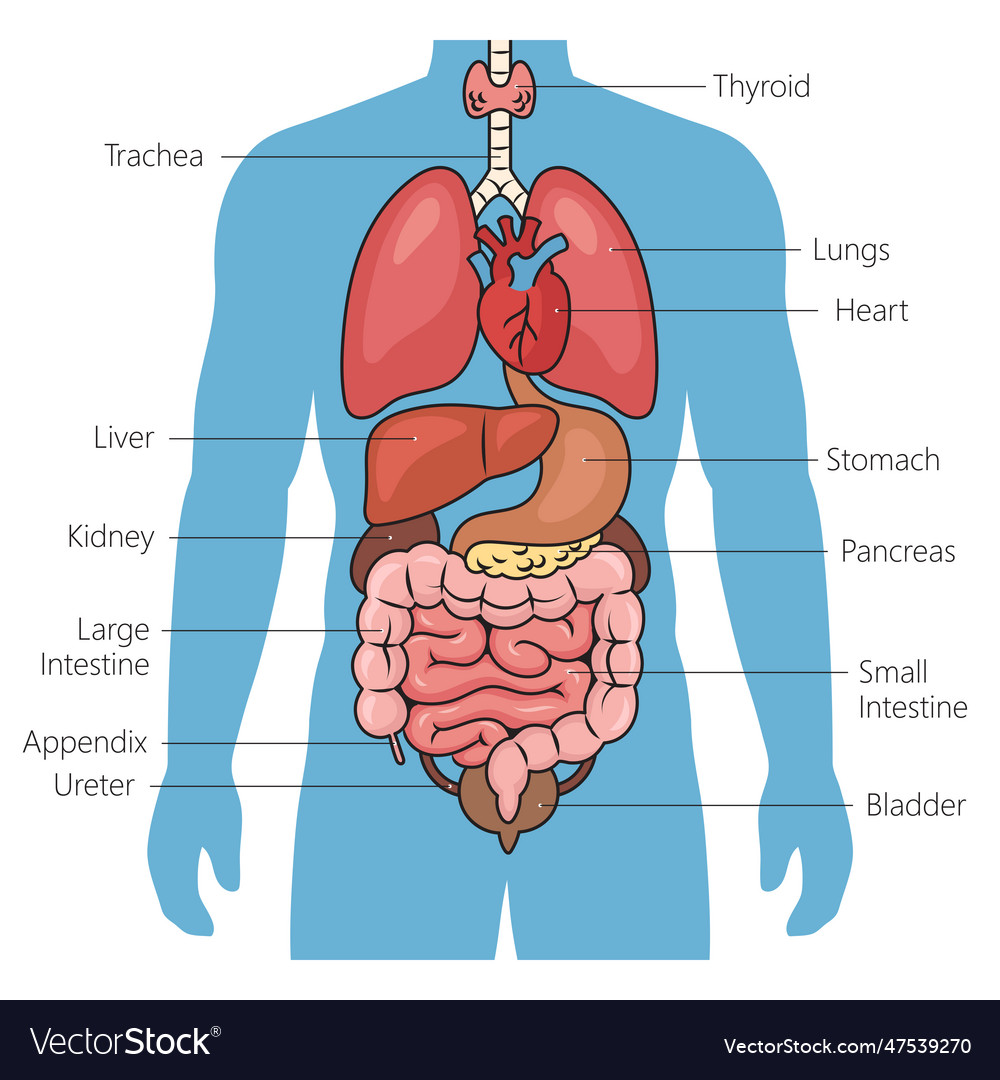
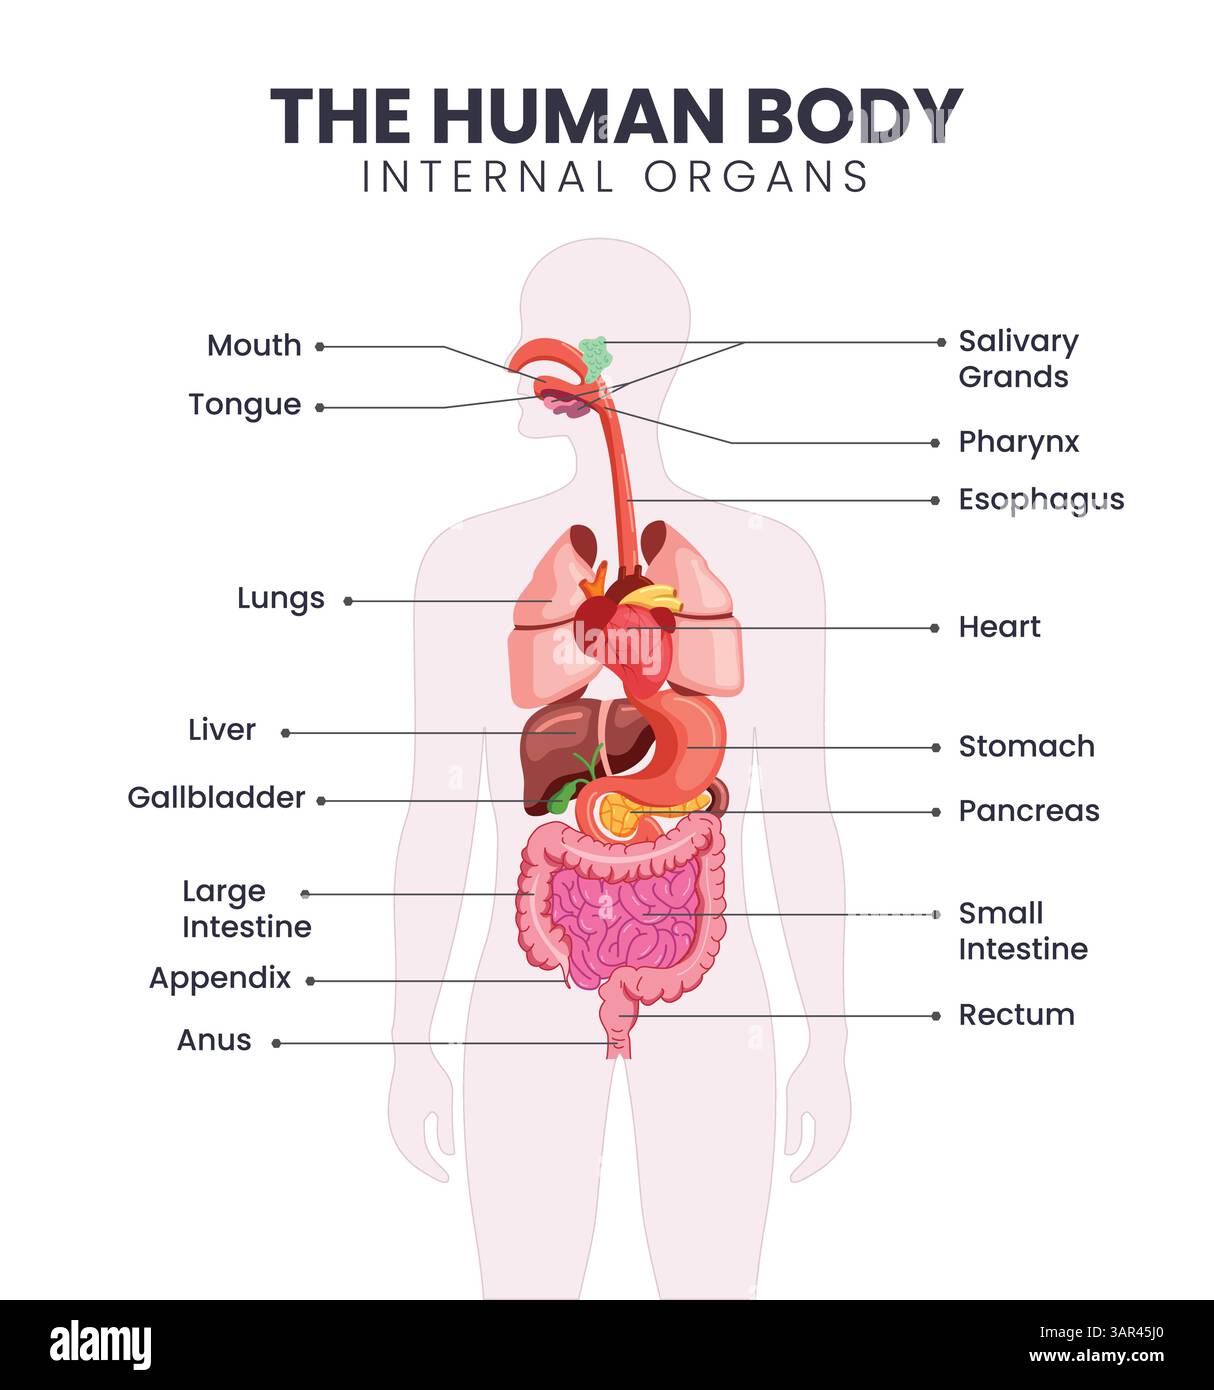
How I Actually Use Organ Location References in Clinical Practice
Most people learning anatomy treat the Body Location Of Organs as a static list. That approach works until you're standing in front of an ultrasound machine or trying to interpret a CT scan and nothing matches the textbook diagram. I stopped relying on those clean diagrams years ago. They lie to you by being too clean. Here is how I actually work with organ location references now, and what to do when the standard maps fail you.Body Location Of Organs: The Practical Reference Method
Start with the anatomical planes, not the organs themselves. When I need to know where something is, I ask which plane I am viewing and what structures sit immediately adjacent in that specific plane. A liver edge on a sagittal slice looks completely different from one on an axial slice. The organ has not moved; your perspective has. I use a layered approach. First layer is surface anatomy landmarks. Second layer is the peritoneal relationships. Third layer is the vascular supply because blood vessels do not lie about where things are. I found a case once where a student was completely lost trying to identify a structure on an axial CT because they had only memorized the organ's name and its "normal position." They did not know the inferior vena cava ran directly anterior to the right kidney. Once I showed them to trace the IVC first, the kidney appeared on the left side of the screen within seconds. The information was there the whole time. The reference tool I actually use daily is a combination of the Complete Anatomical Atlas and a simple grid overlay system. The atlas gives you the cross-references between imaging modalities, and the grid lets you map any organ's position relative to vertebral levels and costal margins. I built the grid myself out of graph paper. You can do the same in under ten minutes.
Why Textbook Diagrams Fail You
Textbook diagrams show organs in idealized positions. In reality, organ location shifts with breathing phase, body habitus, and even the position of nearby structures. The spleen drops two centimeters during deep inspiration. A distended bladder pushes the uterus superiorly and anteriorly. The liver changes shape when you move from supine to standing. These are not edge cases. They happen in every single exam or clinical rotation. I learned this the hard way during my second year of radiology rotation. I confidently identified a mass as hepatic based on a textbook location map. It turned out to be a retroperitoneal liposarcoma pushing anteriorly into the liver space. The mass was not in the liver. The liver was just being displaced. I felt like an idiot for about three days. Now I always check the fat planes. If the fat plane between the organ and the mass is obliterated, the mass is likely intra-abdominal. If the fat plane is preserved, look for another primary site.
The Vascular Anchor Technique
This is the part nobody teaches properly. Blood vessels are your true landmarks. Every organ has a named vascular entry point that stays relatively constant. The hepatic artery enters at the porta hepatis. The renal artery enters at the renal hilum. The superior mesenteric artery crosses the third part of the duodenum anteriorly. These relationships do not change. When I am looking at a scan and cannot orient myself, I find one major vessel and trace it. That vessel will lead me to the organ I am looking for, or it will tell me the organ I thought I found is actually somewhere else entirely. I spent an afternoon last month reviewing a pediatric CT where the bowel was malrotted. Using the SMA as my anchor, I traced it and found the duodenum did not cross the midline as expected. The entire small bowel was on the right side. The textbook diagrams would have sent me in the wrong direction for hours.
Get the Full Details

A Working Reference System
Here is what I actually keep open while working: 1. A cross-sectional anatomy atlas with axial, sagittal, and coronal views side by side. Gray's Atlas of Anatomy remains the gold standard but the netter version is cheaper and easier to carry. 2. A vertebral level quick reference chart. I keep it laminated on my desk. Knowing that the hilum of the left lung sits at T5-T6 while the right is slightly lower at T7-T8 saves me from second-guessing myself constantly.
3. A personal anomaly log. I write down every case where an organ was not where the atlas said it would be. Over three years, this grew to about forty entries. Some were congenital variations like situs inversus. Some were acquired shifts from large masses or surgical scarring. Others were just normal variants that textbooks omitted. This log is now my most useful reference document.
Common Mistakes I See Repeatedly
People confuse the anatomical position with the clinical position. A patient lying supine on an exam table is not in the standard anatomical position. Organs settle posteriorly due to gravity. The stomach and intestines shift. This matters more than you might think when you are correlating physical exam findings with imaging. Another mistake is treating organ location as fixed in the coronal plane. The kidneys are retroperitoneal and mobile. A renal cell carcinoma can track along the gerota fascia. I once followed a mass all the way from the kidney down into the pelvic floor because I kept looking for it at the standard renal bed location. The mass had simply grown downward following the path of least resistance. The third mistake is ignoring the patient's body type. A tall, thin person has their abdominal organs arranged differently than a shorter, broader person. The liver is more vertical in the former. The transverse colon sits lower in the latter. I adjust my mental model based on body habitus before I even look at the image.
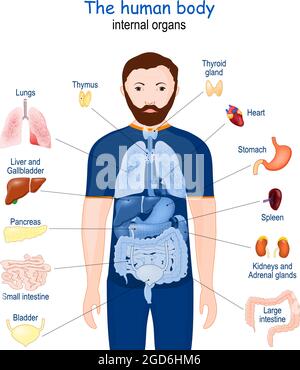
What This Approach Cannot Do
This method is not a substitute for formal training. If you are not in a medical or allied health program, stop reading here and do not attempt clinical interpretations. The information above is for educational reference only. Organ location varies between individuals, and misidentification has real consequences. The vascular anchor technique also fails in cases of severe anatomical distortion from prior surgery, radiation, or advanced disease. I have seen multiple cases where post-surgical adhesions pulled organs into configurations that no reference atlas would predict. In those situations, the only reliable approach is direct surgical exploration or contrast-enhanced imaging with three-dimensional reconstruction. For most people using this information, the biggest limitation is that organ location is a starting point, not an answer. Knowing where an organ should be tells you nothing about whether it is diseased, enlarged, displaced, or absent. That requires additional diagnostic steps beyond location mapping.