Medical Body Positioning Isn't Just Vocabulary — It's the Difference Between a Clean Scan and a Retake
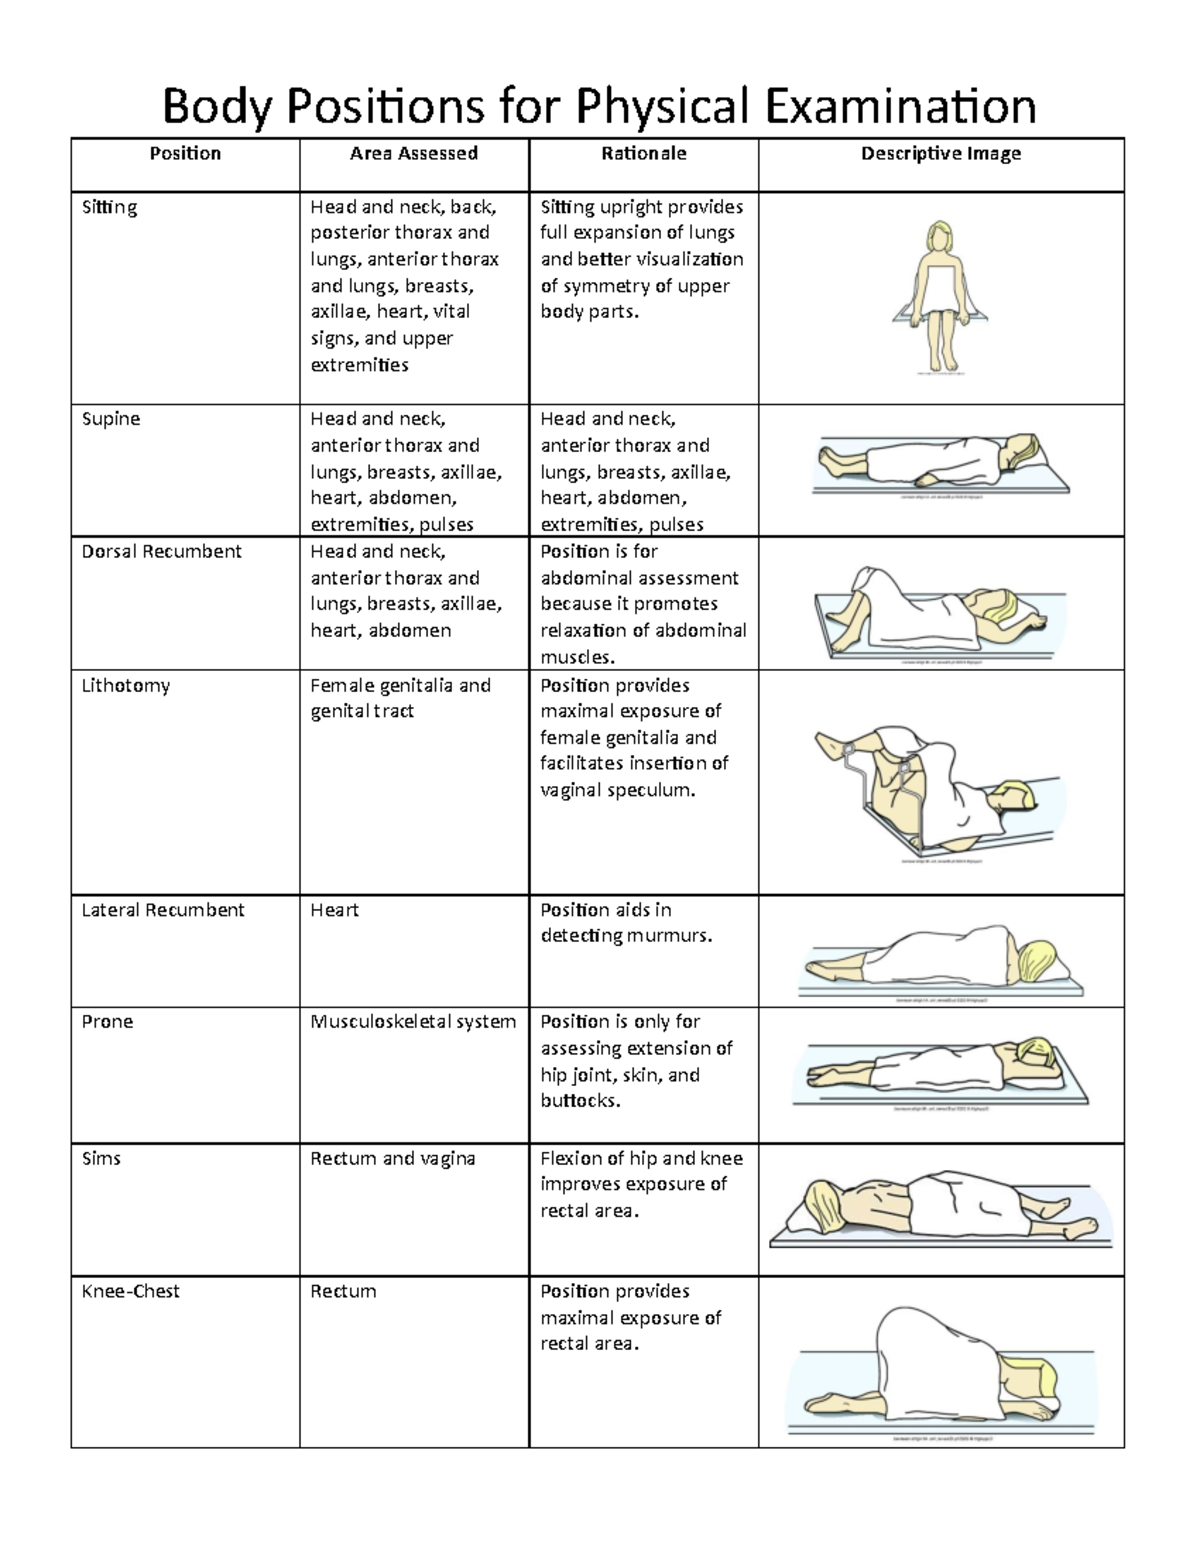
I spend most of my days dealing with imaging protocols and patient positioning documentation. The terminology around body positions in medicine is straightforward in theory and completely mangled in practice. Let me explain how it actually works when you're standing in a room with a patient who can't follow instructions, equipment that won't cooperate, and a radiologist waiting for images. Most people think of supine, prone, and lateral. Those are fine for a textbook. The real work happens when you need to describe something like left lateral decubitus with the central ray horizontal for a chest X-ray to detect a pleural effusion. Or when you're documenting Trendelenburg position at 15 degrees for a surgical procedure and the anesthesiologist needs the exact angle recorded. Here's the list most professionals actually need to know cold:
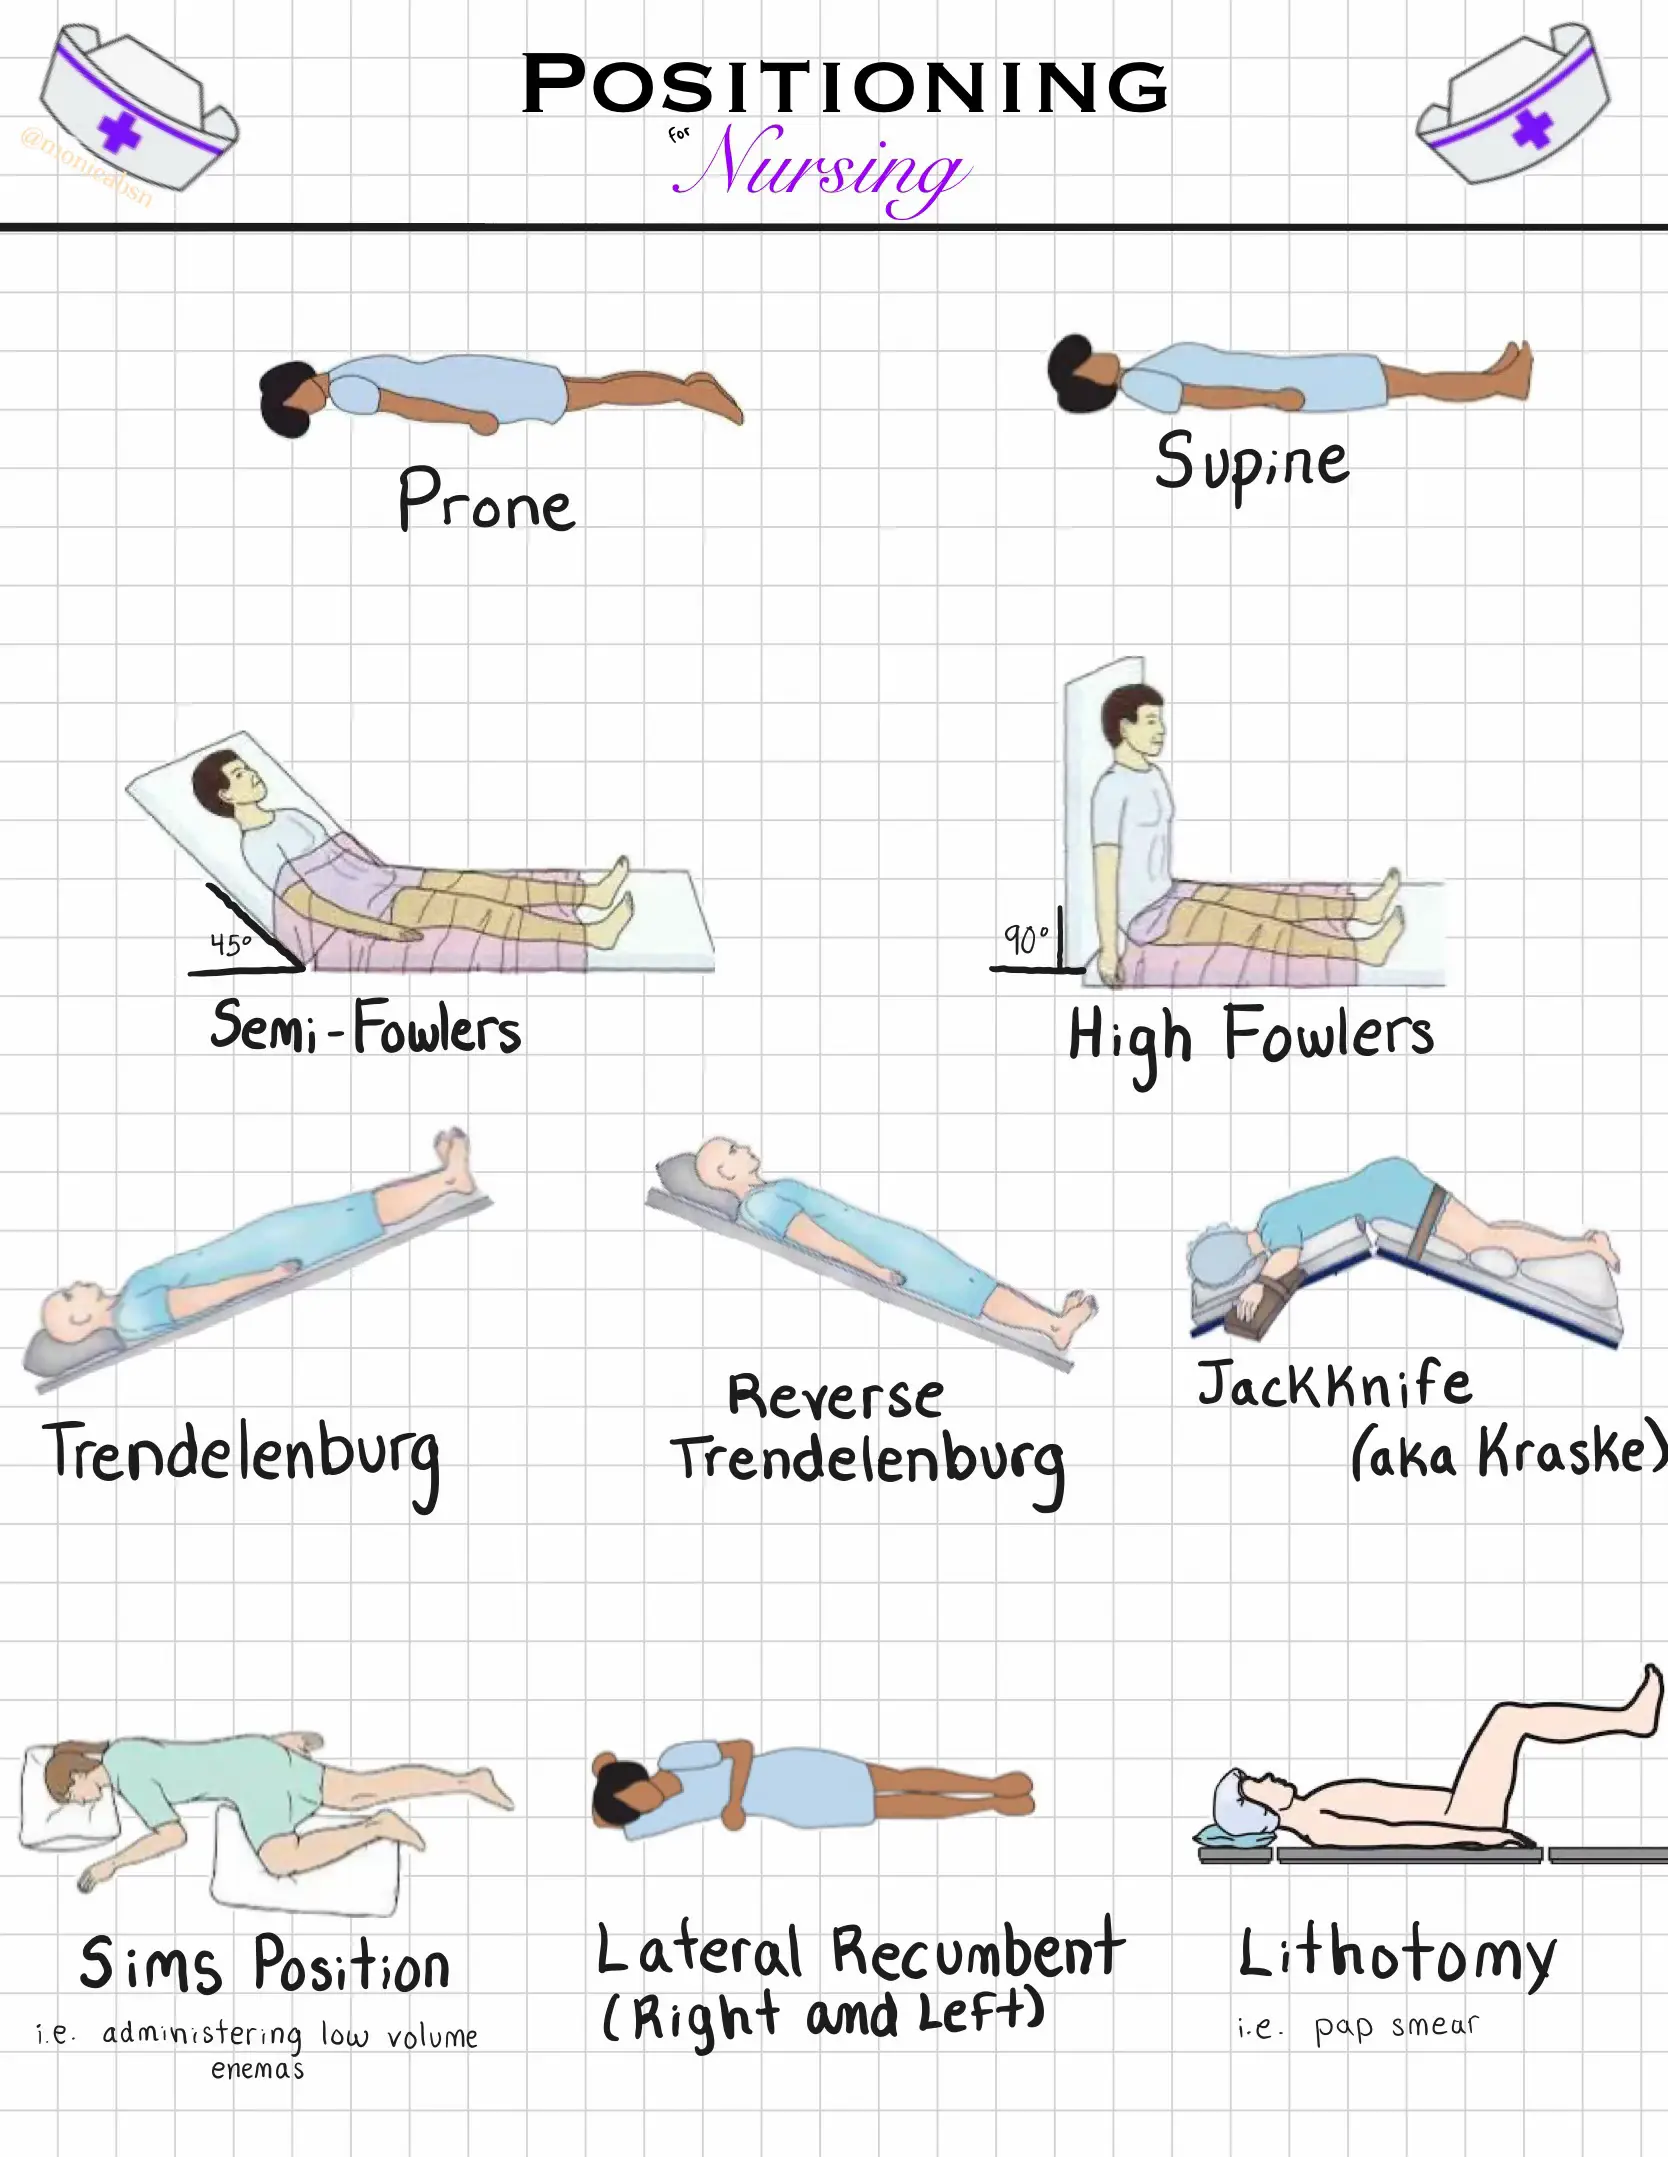
Supine (dorsal recumbent): Patient flat on back. Not just "lying down." If the knees are flexed and feet flat, that's different from supine with legs extended. I had a case where a CT scan of the abdomen was mislabeled because the technologist wrote "supine" when the patient was actually in semi-Fowler's with the head elevated 45 degrees. The contrast distribution looked completely different and the radiologist nearly missed a bowel obstruction. Prone: Face down. Simple. But the arms matter. Arms at sides versus arms overhead changes the appearance of the shoulder girdle and lung apices on imaging. When positioning a post-op spinal patient prone, you need to account for surgical dressings and drains. I once spent twenty minutes repositioning a patient with a lumbar drain because nobody had documented which side the tubing was on before transport. Lateral decubitus: Lying on one side. This is where things get tricky because "left lateral decubitus" means the patient is lying on their LEFT side, not that you're looking at the left side. It means the opposite side is up. I've seen at least three incident reports from misunderstanding this abbreviation. Write it out. Left lateral decubitus. Full words. Saves everyone time when the chart gets pulled three weeks later.
Fowler's and semi-Fowler's: Sitting up at 45-60 degrees and 30-45 degrees respectively. These aren't just comfort positions. They affect diaphragmatic excursion, intracranial pressure, and venous return. A chest X-ray taken in true upright versus semi-Fowler's will show different fluid levels and heart borders. Don't swap them interchangeably in documentation. Trendelenburg and reverse Trendelenburg: Head down and head up on an inclined table. Used in surgery and sometimes for imaging. The angle matters — 15 degrees is standard for many procedures, but some protocols call for 30. Document the degree. "Trendelenburg position" without an angle is useless for anyone reviewing the record later. Orthopneic (high Fowler's with leaning): Patient sitting upright, often leaning forward on an overbed table. This is the go-to position for dyspneic patients and for certain AP chest projections. It's also the position that makes transferring an unstable patient a genuine logistical problem.
Get the Full Details

How to Actually Use This Knowledge Without Creating Liability
Positioning documentation isn't just descriptive. It's legally binding and clinically consequential. Here's the practical approach I've settled on after years of making and correcting errors. Always record three things: the named position, the degree of any incline if applicable, and the patient's tolerance or modifications. "Supine, modified — left pillow under knee for comfort" tells a different story than "supine." The knee flexion changes abdominal wall tension and can affect ultrasound and CT measurements of the psoas muscle or aortic diameter. When I'm documenting for radiology, I add the beam direction relative to the position. A AP supine abdomen is not the same thing as a PA upright abdomen. One shows free air under the diaphragm far better than the other. I learned this the hard way during a night shift when I documented "abdominal series" without specifying projections and the attending radiologist flagged the report for incomplete positioning information. That was a teachable moment that stuck.
For surgical positioning, the record needs more granularity. Skin contact points, pressure relief devices, arm abduction degrees, and head alignment all belong in the note. I use a standardized template now that takes about 30 seconds to fill out but has prevented at least two peroperative nerve injury claims on my service. The template forces you to document ulnar nerve positioning, shoulder braces engagement, and heel suspension. Most people skip those fields under time pressure. Don't.
The Hidden Problem With Standardized Position Names
Here's something most training programs don't emphasize: the same position name means different things in different departments. "Lateral" in the ED might mean 90-degree side-lying. "Lateral" in radiology might mean a 45-60 degree roll for a specific projection. "Prone" in neurosurgery might mean a Jackson table with chest hangs and face cup, while "prone" in general radiology means flat on the table with a pillow under the abdomen. I encountered a real complication when a trauma patient was transferred between services. The receiving team read "prone" from the initial imaging report and assumed standard prone positioning. The patient was actually prone with a Frolov frame and cervical traction. Someone nearly pulled the traction weights thinking they were unnecessary. We now require the specific positioning apparatus to be named alongside the position in all transfer documentation. It adds eight words to the note and has eliminated an entire category of near-miss events. Another issue that nobody talks about enough is the interaction between body position and medical devices. A patient with an arterial line, a central venous catheter, a chest tube, a urinary catheter, AND external pacing wires cannot be positioned using textbook descriptions without considering each device's tubing length and anchor point. I position a patient in lateral recubent with four indwelling lines and one surgical drain. The textbook says roll 45 degrees. The reality is you roll 30 degrees, resecure each line with additional tape points, and check every hub before you finish the roll. Taking ten extra seconds here prevents a dislodged central line that would cost the patient at least two hours of procedural time and significant complication risk.
When the Terminology Breaks Down
Some patients simply cannot achieve standard medical positions. Obese patients, contracture patients, post-fracture patients, and those in protective spinals often need descriptive positioning rather than named positions. In those cases, stop trying to force a label. Describe what the patient is actually doing. "Patient positioned right-side down with 20-degree thoracic rotation, right arm extended above head, left arm at side supported by pillow" is more useful than writing "approximate lateral position" and moving on. The electronic health record systems I've worked with mostly have dropdown menus for standard positions. They're terrible for non-standard positioning. I've started adding a free-text positioning note even when the dropdown captures the basic position. The dropdown is for billing and quick reference. The free text is for the next clinician who needs to understand what actually happened. Body Positions Medical Terms are foundational, but they're a starting point, not the end of the documentation. The patients I see every day don't read the textbooks. The positioning you document needs to reflect the actual clinical situation, not the idealized version. That distinction is what separates competent documentation from documentation that holds up under scrutiny — whether that scrutiny comes from a radiologist, a surgeon, or a reviewer six months down the line.