Understanding Bone Age Assessment
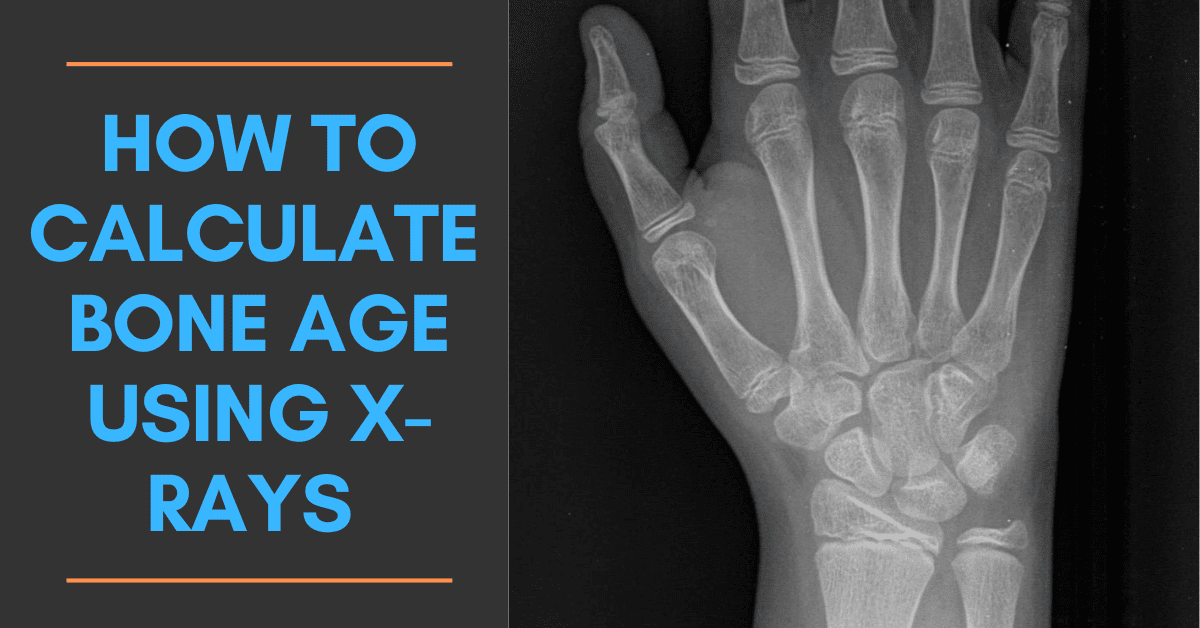
A bone age assessment compares a child's skeletal maturity to their chronological age using an X-ray of the left hand and wrist. The standard method, called the Greulich-Pyle atlas, matches the X-ray to reference images taken from healthy children in the mid-20th century. A trained radiologist or pediatric endocrinologist looks at the ossification centers in the carpals, metacarpals, and the distal radius and ulna, then assigns an age that represents how mature those bones appear. The clinical purpose is straightforward. When a child presents with short stature, early puberty, or growth concerns, knowing the bone age helps predict adult height and guides treatment decisions. It also flags conditions like hypothyroidism, growth hormone deficiency, or precocious puberty earlier than height charts alone would catch.
How a Bone Age Calculator Online Actually Works
Most online calculators don't generate the bone age themselves. They take an age already determined by a radiologist and add supplemental data like the child's height, weight, and sometimes parental heights to estimate predicted adult height. The two most common models embedded in these tools are the Bayley-Pinneau tables and the TW3 method. Some newer platforms claim to use AI-driven image analysis, but the accuracy of those systems still depends heavily on image quality and the training data behind them. If you upload a radiograph to an automated system, the software analyzes the visibility and fusion status of specific epiphyseal centers. It outputs a bone age number. You then plug that into a calculator to project height. That projection is where things get messy, and I will get to that.
Practical Steps for Using These Tools
Here is the workflow most clinics actually follow, not the idealized version. You need a high-quality PA hand X-ray. The patient should be positioned with the hand flat, fingers slightly spread, and the thumb in mild abduction. If the rotation is off by even ten degrees, the carpal bones overlap differently and can throw an automated system into error. I have seen AI tools misread rotation artifacts as delayed carpal maturation, which produced a bone age two years younger than what a human reader gave on the same image. That is a clinically significant gap. Once you have the image, upload it to a reputable platform. Look for one that is CE marked or FDA cleared if you are in the United States. The tool will return a bone age estimate with confidence intervals. Do not treat a single output as definitive. Run a second reading manually or have a radiologist confirm it, especially if the result differs from chronological age by more than twelve months in either direction.
Get the Full Details

Then move the number into a calculator. Enter the bone age, current height, current weight, and sex. Some calculators also ask for mid-parental height. The output is a predicted adult height range, usually given as a percentile or a centimeter band. That range is useful for counseling parents, but it is not a guarantee.
Where I Have Seen This Go Wrong
Early in my career, a teenager came in for a routine growth workup. The automated Bone Age Calculator Online read gave a bone age of 14.2 years for a boy who was chronologically 12.8 years old. His height was already well below the third percentile, and his parents were convinced he had hit puberty too early and shut down his growth plates prematurely. The elevated bone age suggested exactly that, so we started down the pathway for GnRH analog therapy workup. I pulled the original film and re-read it myself. The calcaneus and the distal femur reference points were there, but the soft tissue margins were blurred from a motion artifact during exposure. The AI model had interpreted the blurred epiphyseal edges as advanced closure. The true bone age was closer to 13.1 years, which changed the entire clinical picture. The boy had constitutional delay of growth and puberty, not precocious puberty. The automated read was aggressively pushing the age upward because motion blur mimics the appearance of closing physis on certain deep learning architectures that were trained primarily on crisp, diagnostic-quality images from academic centers. The fix was simple in retrospect but took three extra days to resolve. We repeated the X-ray with a faster exposure time and a sandbag immobilization device. The repeat image was clean. I read it against the Greulich-Pyle atlas and confirmed the lower bone age. We avoided an unnecessary and expensive endocrine workup by catching the artifact before it drove the clinical decision.
Limitations You Should Know About
No bone age tool is perfect. The Greulich-Pyle atlas itself is outdated. The reference population was mostly white, middle-class children from the 1930s and 1940s. Modern children mature earlier due to better nutrition and higher rates of childhood obesity. Several studies have shown that using the original Greulich-Pyle standards on contemporary populations systematically overestimates bone age by six to eighteen months, depending on the demographic group. The TW3 method accounts for some of this by using a more modern British reference sample and scoring each bone individually rather than matching whole-image patterns. It is slower and requires more training to use correctly, but it is generally more accurate for diverse populations. Automated systems introduce another variable. They perform well on straightforward cases where the ossification pattern is typical. They degrade when there is a chronic systemic illness, endocrine disorder, or skeletal dysplasia that alters bone maturation in ways the training data never saw. I have encountered cases of untreated celiac disease where the bone age was severely delayed, and the AI model simply output the chronological age because it lacked the pattern recognition for that specific pathology.
Predicted adult height calculations also carry wide margins. Even under ideal conditions, the prediction error is typically plus or minus seven to ten centimeters. For a family already anxious about a child's height, that is a lot of uncertainty wrapped in a single number.
When to Use Manual Reading Instead
There are situations where you should skip the calculator and go straight to a human reader. If the child has a known skeletal dysplasia, previous fracture through the physis, or a chronic inflammatory condition affecting the extremities, the standard references do not apply. Automated tools will not adjust for those confounders. A pediatric radiologist who can recognize abnormal ossification patterns will give you a far more reliable result. Similarly, if the bone age and chronological age diverge by more than two standard deviations, run the case by a specialist. That level of discrepancy usually signals an underlying pathology that a calculator cannot address.
Choosing a Bone Age Calculator Online
Not all platforms are equal. Look for one that explicitly states which method it uses, whether it has regulatory clearance, and what population it was validated against. Avoid free tools that do not provide any reference documentation. The cheap options often rely on outdated algorithms and no quality control pipeline. If a platform cannot show you the validation study, assume the output is unreliable for clinical use. The best calculators give you transparency. They show the confidence interval around the bone age estimate, they allow you to switch between Greulich-Pyle and TW3 methods, and they export the results in a format that integrates with your electronic health record. That last point matters if you are seeing more than a handful of pediatric cases per week. Manual data entry from a pop-up result window wastes time and introduces transcription errors.
A Quick Technical Note on Image Requirements
Pixel density matters more than most users realize. Automated systems typically require a minimum resolution of 200 to 300 DPI for the hand region. Scanned film at lower resolutions loses the fine trabecular detail in the distal radius and the carpal epiphyses, which are the exact areas the algorithm weights most heavily. If you are digitizing existing films, use a medical-grade film scanner, not a flatbed office scanner. The difference in contrast and resolution is substantial, and the output bone age can shift by several months depending on the digitization method. For digital radiography, ensure the DICOM header contains the correct patient sex and date of birth. A mismatched DOB throws off every subsequent calculation automatically.