What Actually Works When You Need Bone Grafts
Bone Augmentation In Oral Implantology is usually straightforward until it isn't. I've been placing grafts in compromised sites for over a decade, and the cases that trip people up are rarely the ones on the textbooks. They're the ones where you're working in a small vestibule with barely any attached keratinized tissue, or where the defect hasCommunication no good walls to hold the graft material. Let me walk through the practical side of this. Not the theory. The actual chairside decisions.
Bone Augmentation In Oral Implantology: The Basics You Already Know
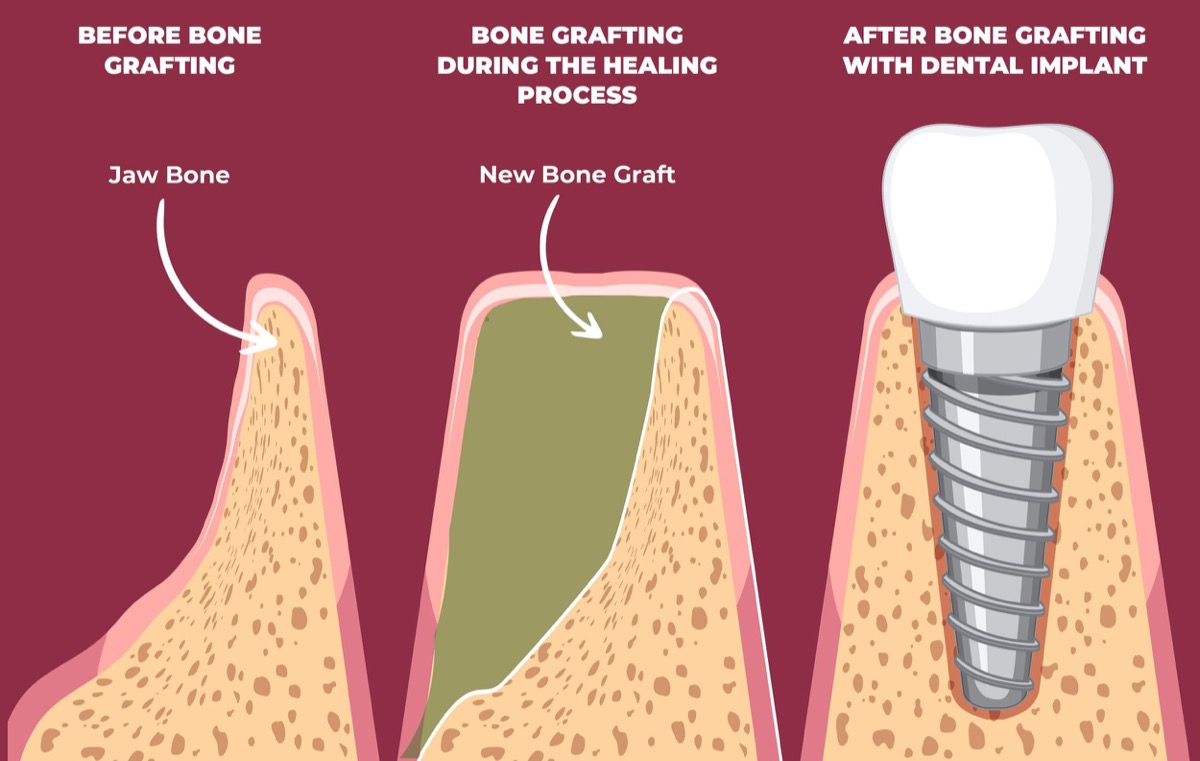
You need bone. Not just any bone, but dense enough bone to hold an implant through the healing period and beyond. When the alveolar ridge resorbs after extraction — which it does, consistently, losing about 30 to 50 percent of its width in the first year — you're left with a site that often can't support an implant without help. That's where grafting comes in. The graft materials fall into a few categories. Autograft is your own bone, harvested locally or from the chin or ramus. Allograft comes from a human donor, processed and freeze-dried or fresh. Xenograft is bovine-derived, usually Beta-TCP or deproteinized bovine bone mineral. Alloplast is synthetic, like hydroxyapatite or beta-tricalcium phosphate. Each has trade-offs. Autograft is the gold standard because it's osteogenic, but it requires a second surgical site and more chair time. Xenografts are slow-resorbing and act as a scaffold, which is useful when you need to maintain volume long-term. Alloplasts resorb at varying rates depending on the formulation. Allografts sit somewhere in between.
Block Grafts vs. Particulate Grafts: Which to Choose
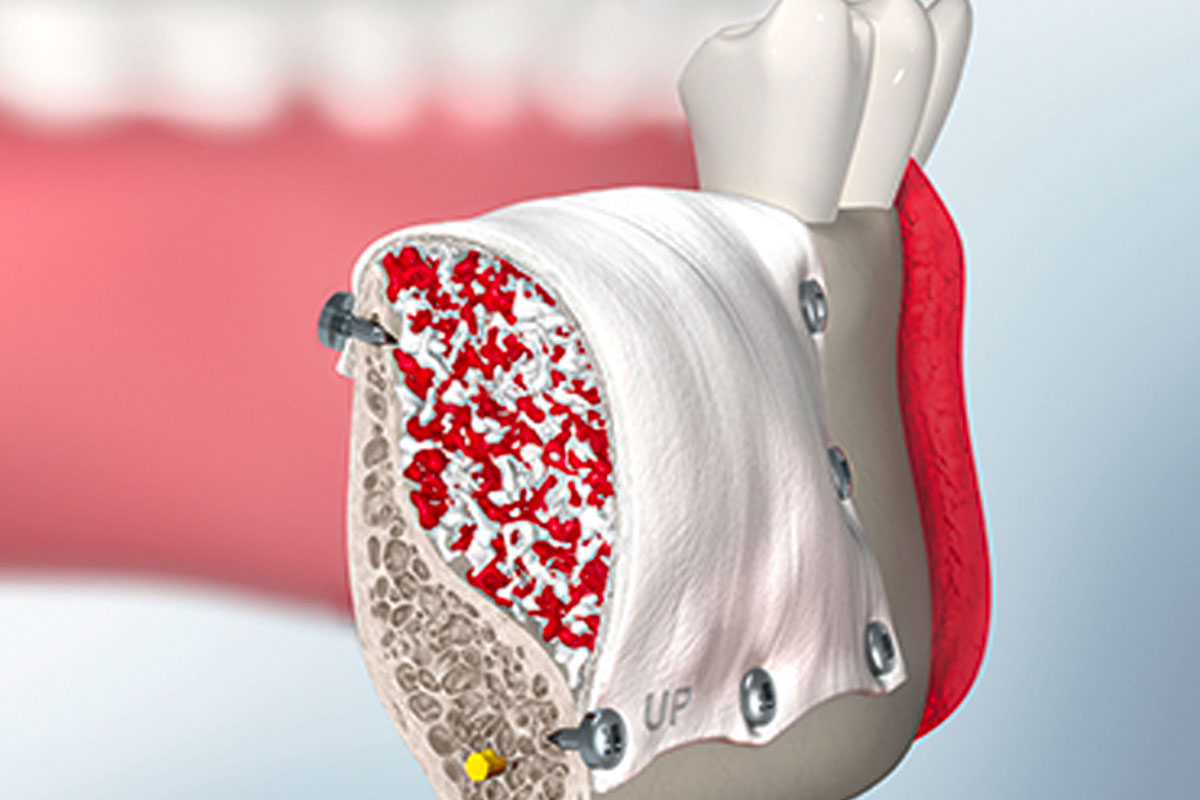
This is where most clinicians make their first mistake. They treat all defects the same way. A 4mm horizontal deficiency and a 6mm vertical deficiency are not the same problem, even though both "need grafting." For horizontal augmentation — widening a narrow ridge — particulate grafts work reasonably well when you have a good membrane and tension-free closure. The key is a corticotomy. Drilling multiple holes into the cortical plate of the recipient bed lets marrow elements seep through, bringing in osteoprogenitor cells and creating a fibrin clot that holds the particles in place. Without this step, particulate grafts in horizontal defects tend to migrate or get resorbed too aggressively. I typically use a combination of xenograft and autograft from the osteotomy preparations, layered with a resorbable collagen membrane. The autograft provides the osteoinductive signal, the xenograft maintains space. For vertical augmentation, particulate grafts alone are unreliable. The graft collapses under soft tissue pressure. Block grafts are the standard here. Wedge blocks, interpositional blocks, or onlay techniques depending on the anatomy. I prefer cancellous onlay blocks for moderate vertical deficiencies (3 to 5mm) because they integrate better than cortical blocks. Cortical blocks take longer to revascularize and have a higher rate of partial resorption. Cancellous blocks from the tibial plateau or iliac crest allow faster vascular ingrowth. But again, you're adding a donor site morbidity.
Get the Full Details
I've seen clinicians try to do vertical rebuilds with particulate grafts and guided bone regeneration alone. It can work in select cases — when the defect has at least three bony walls, when you can achieve primary closure without tension, and when you use a titanium-reinforced membrane to prevent collapse. But those are a lot of conditions to meet simultaneously. Most of the time it fails, and you end up doing the block graft anyway after complications.
My Typical Protocol for a Horizontal Ridge Deficiency
Here's a routine case I handle. Extracted upper premolar site, six months post-extraction, ridge width is about 4mm. Need at least 6mm for a 3.5mm implant with 1mm bone on each side. First, I de-epithelialize the recipient site. A simple crescent incision, reflect a full-thickness flap, remove the epithelial collar from the cortical surface. This improves graft-to-bone contact and reduces the risk of epithelial down-growth under the membrane. Next, corticotomy. I use a round bur or a piezo tip to create multiple perforations through the cortical plate, about 2mm apart, being careful not to penetrate the nasal floor or mental foramen. Blood should weep from each hole. If it doesn't, you haven't gone deep enough, or the cortical bone is too sclerotic. In older patients, the cortex can be so dense that simple perforations don't produce adequate bleeding. In those cases, I score the cortical surface with a fissure bur to create channels, then perforate.
Graft mix. I combine 50 percent xenograft (Bio-Oss or equivalent, 0.5 to 1mm granule size) with 50 percent autograft collected from the osteotomies. The autograft should be freshly harvested, not left exposed to air for more than a few minutes. Mixing it immediately into the xenograft maintains viability. Some clinicians add platelet-rich fibrin (PRF) to the mix. I don't routinely, because the evidence for a meaningful clinical difference in augmentation outcomes is weak. PRF is useful for socket preservation, less clear for onlay grafting. Placement. Compact the graft into the prepared site using hand instruments, not the syringe tip. Packing it in firmly reduces micromovement and improves stability. The graft should be slightly overcontoured — about 1 to 2mm above the expected final ridge height — because some resorption is inevitable, typically 10 to 20 percent over the first year. Membrane. A resorbable collagen membrane, overlapping the graft margins by at least 2 to 3mm onto native bone. Non-resorbable membranes (ePTFE) provide better space maintenance but require a second surgery for removal. I use resorbable membranes in most cases unless the defect is large or the soft tissue coverage is questionable. For those situations, a titanium-reinforced membrane gives you more predictable results, and you can place the implant through the membrane after healing.

Closure. Primary closure is critical. Any gap between the membrane and the soft tissue becomes a dead space where bacteria accumulate and the graft gets contaminated. I use 4-0 or 5-0 PTFE sutures, running sutures with vertical mattress sutures at the corners to tuck the flap edges under the membrane. If you can't achieve tension-free closure, don't proceed. Re-evaluate. Consider a different technique. A compromised closure is worse than no graft at all.
The Case That Almost Cost Me a Patient
Two years ago, I had a patient who needed a block graft on the anterior mandible for an atrophic ridge. The site was Class V Cawood and Howell — flat as a tabletop. The mucosa was thin, almost white, with minimal submucosal tissue. I took a cancellous block from the ramus, secured it with two fixation screws, packed particulate graft around it, and covered it with a resorbable membrane. Closed primarily. Looked good. Felt stable. At one week, the wound was opening at the midline. Not a dehiscence, not yet, but the edges were pulling apart. The tension was too high on that thin mucosa. I placed a collagen plug in the gap and instructed chlorhexidine rinses. At two weeks, the marginal tissue had necrosed — a thin sliver of gingiva at the suture line turned gray and sloughed off. The membrane was now partially exposed. This is the scenario every clinician dreads. The graft is now open to the oral environment. Here's what I did. I debrided the necrotic tissue, irrigated with hydrogen peroxide and saline, and packed the exposed area with a concentrated PRF membrane that I prepared from the patient's own blood. PRF releases growth factors over seven to ten days, which can help accelerate soft tissue healing in compromised wounds. I also switched to a non-resorbable membrane temporarily to protect the graft while the soft tissue recovered. The patient returned weekly for debridement and dressings. By week four, the soft tissue had healed sufficiently to replace the non-resorbable membrane with a resorbable one. By week eight, the graft had integrated. The implant was placed at six months with good bone density on CBCT.
The lesson was simple and brutal: thin mucosa on an atrophic ridge is not a contraindication for grafting, but it is a warning sign. I now use a subepithelial connective tissue graft as a overlay in these cases, or I stage the procedure differently — augment first, let it heal, then harvest connective tissue graft at the time of implant placement if more soft tissue is needed. Trying to do everything in one stage with thin mucosa is asking for trouble.

Common Pitfalls That Beginners Miss
The first one is underestimating the resorption rate. Grafts don't stay the same size. Even with perfect technique, you lose volume. The amount depends on the material, the defect type, and the patient's biology. Xenografts resorb slowly, so they retain more of their initial volume long-term. Autografts remodel predictably but can resorb 30 to 50 percent in the first six months if not protected. Particulate grafts without a membrane in large defects can show significant reduction in the first year. Plan accordingly. Overaugment, don't underaugment. The second is ignoring the period of implant loading. A graft is only as good as the stability it provides for the implant. Placing an implant too early — before the graft has matured — risks micromotion and fibrous encapsulation instead of osseointegration. The rule of thumb is four to six months for the maxilla, three to four months for the mandible. But those are averages. A dense block graft in the mandible might be ready in three months. A large sinus lift with xenograft in the maxilla might need six. CBCT at three months is not always necessary for routine cases, but it's invaluable for complex reconstructions. I take a follow-up scan at four months for maxillary grafts and at three months for mandibular cases. The third is membrane exposure. When a membrane becomes visible through the soft tissue, the graft is no longer protected. Bacteria colonize the membrane surface, and the graft underneath gets compromised. Small exposures (less than 2mm) can sometimes be managed with local debridement and chlorhexidine. Larger exposures usually require membrane removal and may result in partial or complete graft loss. Prevention is everything. Tension-free closure, proper flap design, adequate soft tissue volume — these matter more than the graft material itself.
Sinus Augmentation: A Different Beast
Posterior maxilla grafting involves the sinus. The lateral window technique and the transalveolar (osteotome) approach are the two main options. The transalveolar method is less invasive and works well when you have at least 5 to 6mm of residual bone and the sinus floor is relatively flat. You elevate the membrane through the extraction socket or osteotomy site using osteotomes or specialized balloons. The lift is usually 3 to 5mm. It's fast, less morbidity, and the graft stabilizes well because it's contained within the osteotomy walls. The lateral window approach is for larger lifts — when you need 6mm or more, or when the sinus floor is severely pneumatized. You create a bony window in the lateral sinus wall, elevate the mucoperiosteum, and pack the graft material. The membrane elevation is more controlled, and you can place more graft. But it's a bigger surgery, more postoperative swelling, and a higher risk of membrane perforation. A perforated membrane during sinus lift is not catastrophic if it's small (less than 4mm). You can patch it with a collagen membrane or fibrin sealant and continue. If it's large, the graft material will migrate into the sinus cavity, and you'll need to retrieve it, possibly convert to a different approach, or stage the procedure. I've lost grafts to membrane perforation twice in my career. Both were due to aggressive elevation in a sinus with a thick, fibrotic membrane — common in patients with chronic sinusitis or previous sinus surgery. The membrane doesn't peel away cleanly; it tears irregularly. In those cases, I now use a piezoelectric device for the lateral window osteotomy and membrane elevation. Piezo cuts bone without damaging soft tissue, and the fine tips allow more controlled membrane separation. It's slower, but the reduction in perforation rate is significant.
When Not to Graft
This is the part nobody talks about. Sometimes the best decision is not to augment. If the patient is a heavy smoker with poor oral hygiene, the success rate of grafting drops considerably. Smoking reduces blood flow to the surgical site, impairs healing, and increases the risk of graft failure. I don't refuse to treat smokers, but I counsel them thoroughly and often recommend a minimum of two weeks abstinence before and after surgery. Some won't comply, and in those cases, I either delay the procedure or reduce expectations significantly. Uncontrolled diabetes is another relative contraindication. HbA1c above 7.5 percent is a red flag. Wound healing is delayed, infection risk is higher, and graft integration is unpredictable. Coordinate with the patient's physician. Don't proceed without clearance. And sometimes, the implant can be placed without grafting. A short implant (6mm or less) in the posterior maxilla can avoid a sinus lift entirely. Modern short implants have good survival rates — 95 percent or higher at five years — when placed in adequate bone volume. A 6.5mm implant in a site with 8mm of bone is often a better choice than an 11mm implant in a grafted sinus. Less surgery, less morbidity, more predictability.

Bone augmentation is a tool, not a mandate. Using it when it's not needed is just unnecessary risk.

