Understanding Wrist And Hand Anatomy For Clinical Reading
The wrist and hand contain twenty-seven individual bones, and most people reading a radiograph miss roughly half of them before they even know what they are looking for. I spent years reading fractures on late-night shift X-rays, and the scaphoid alone will make you miss three separate injury patterns if you treat it like every other carpal bone. That is why I keep a specific mental checklist when anything proximal to the metacarpals comes across my screen. What follows is a straightforward breakdown of the Bones In The Wrist And Hand, written from the perspective of someone who has had to explain to a junior resident why their initial read on a "simple sprain" was wrong. This is not a complete atlas. It is a working framework that actually functions during a busy clinical day.
Bones In The Wrist And Hand: The Practical Layout
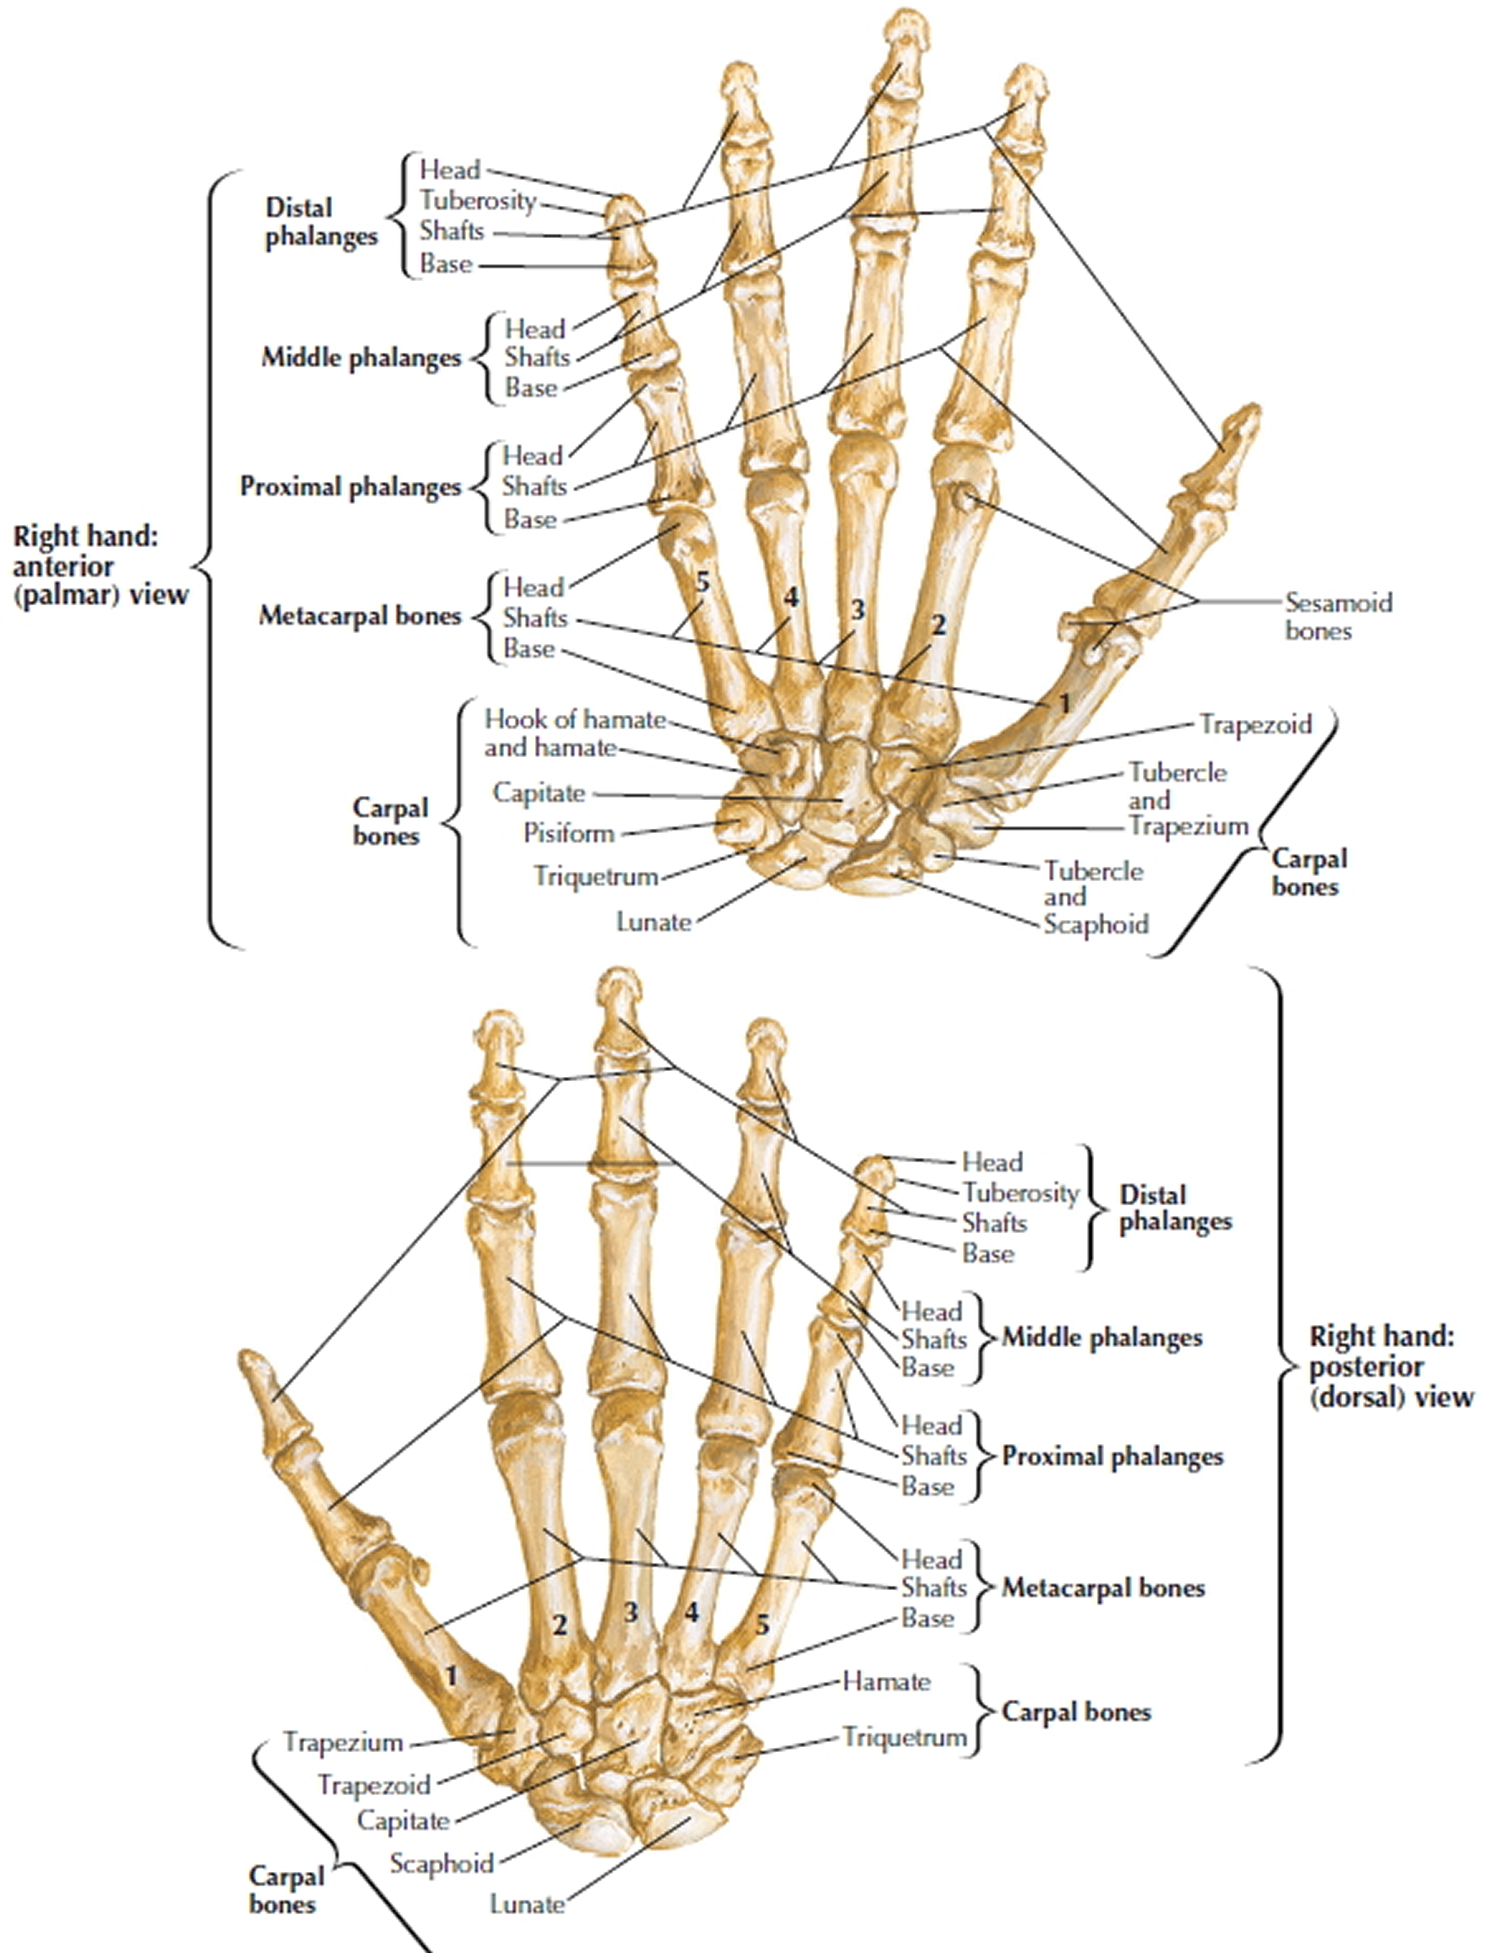
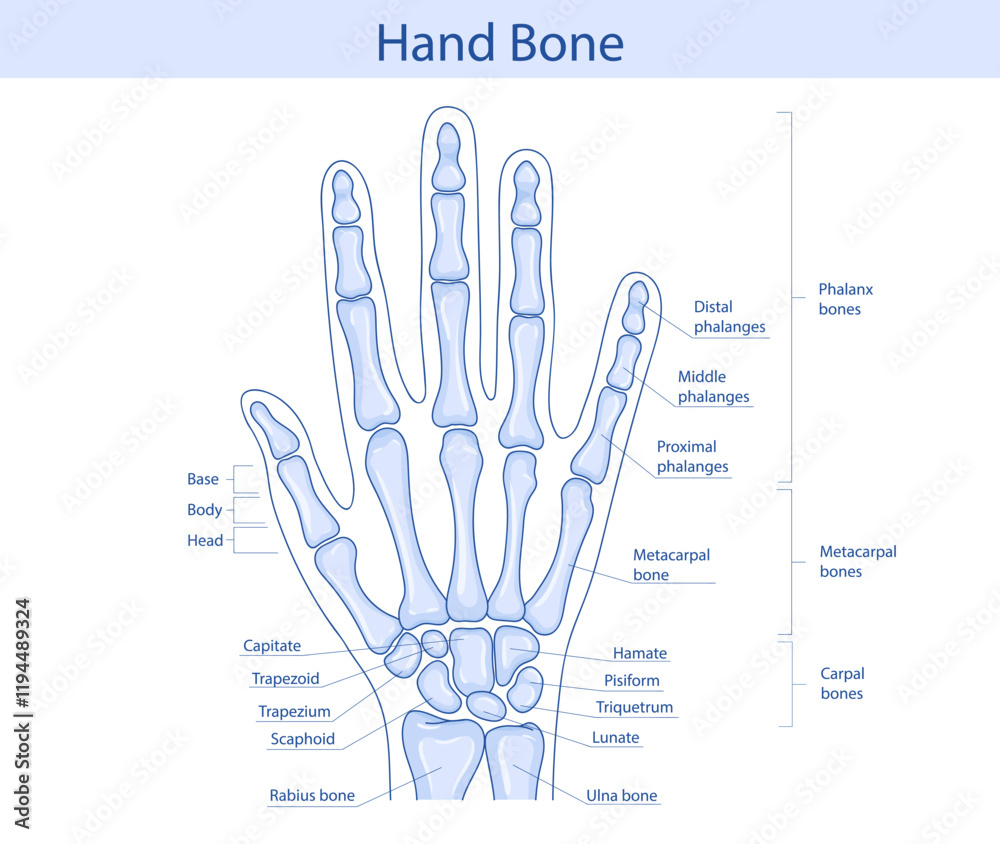
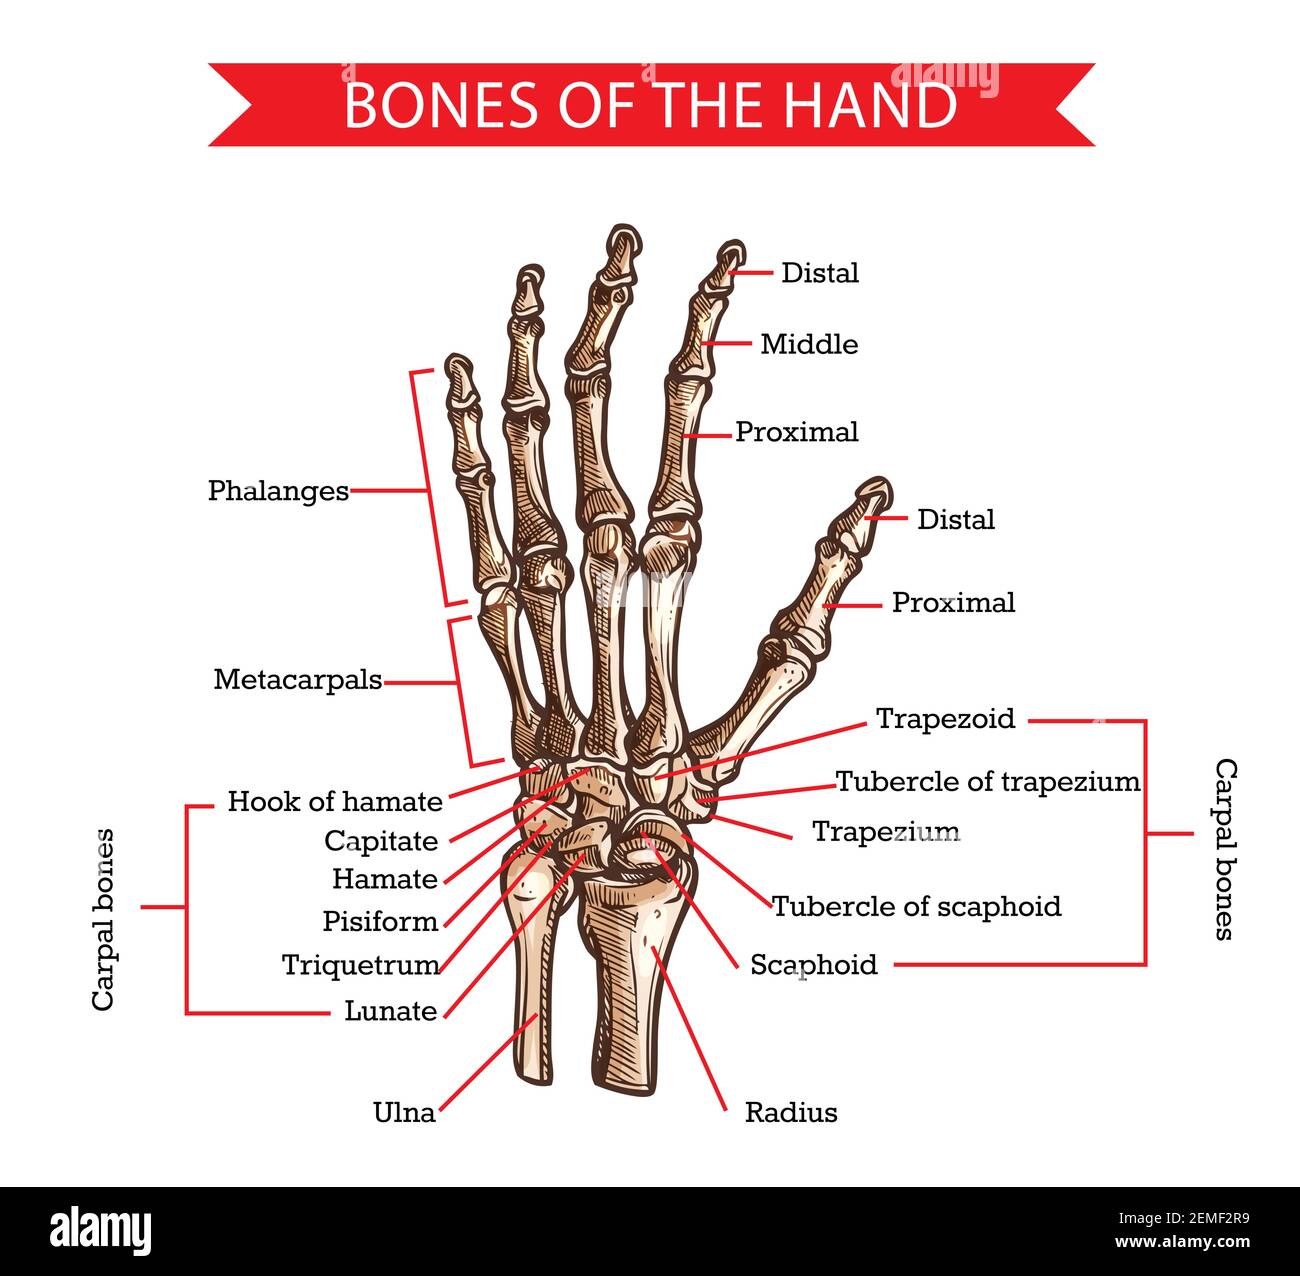
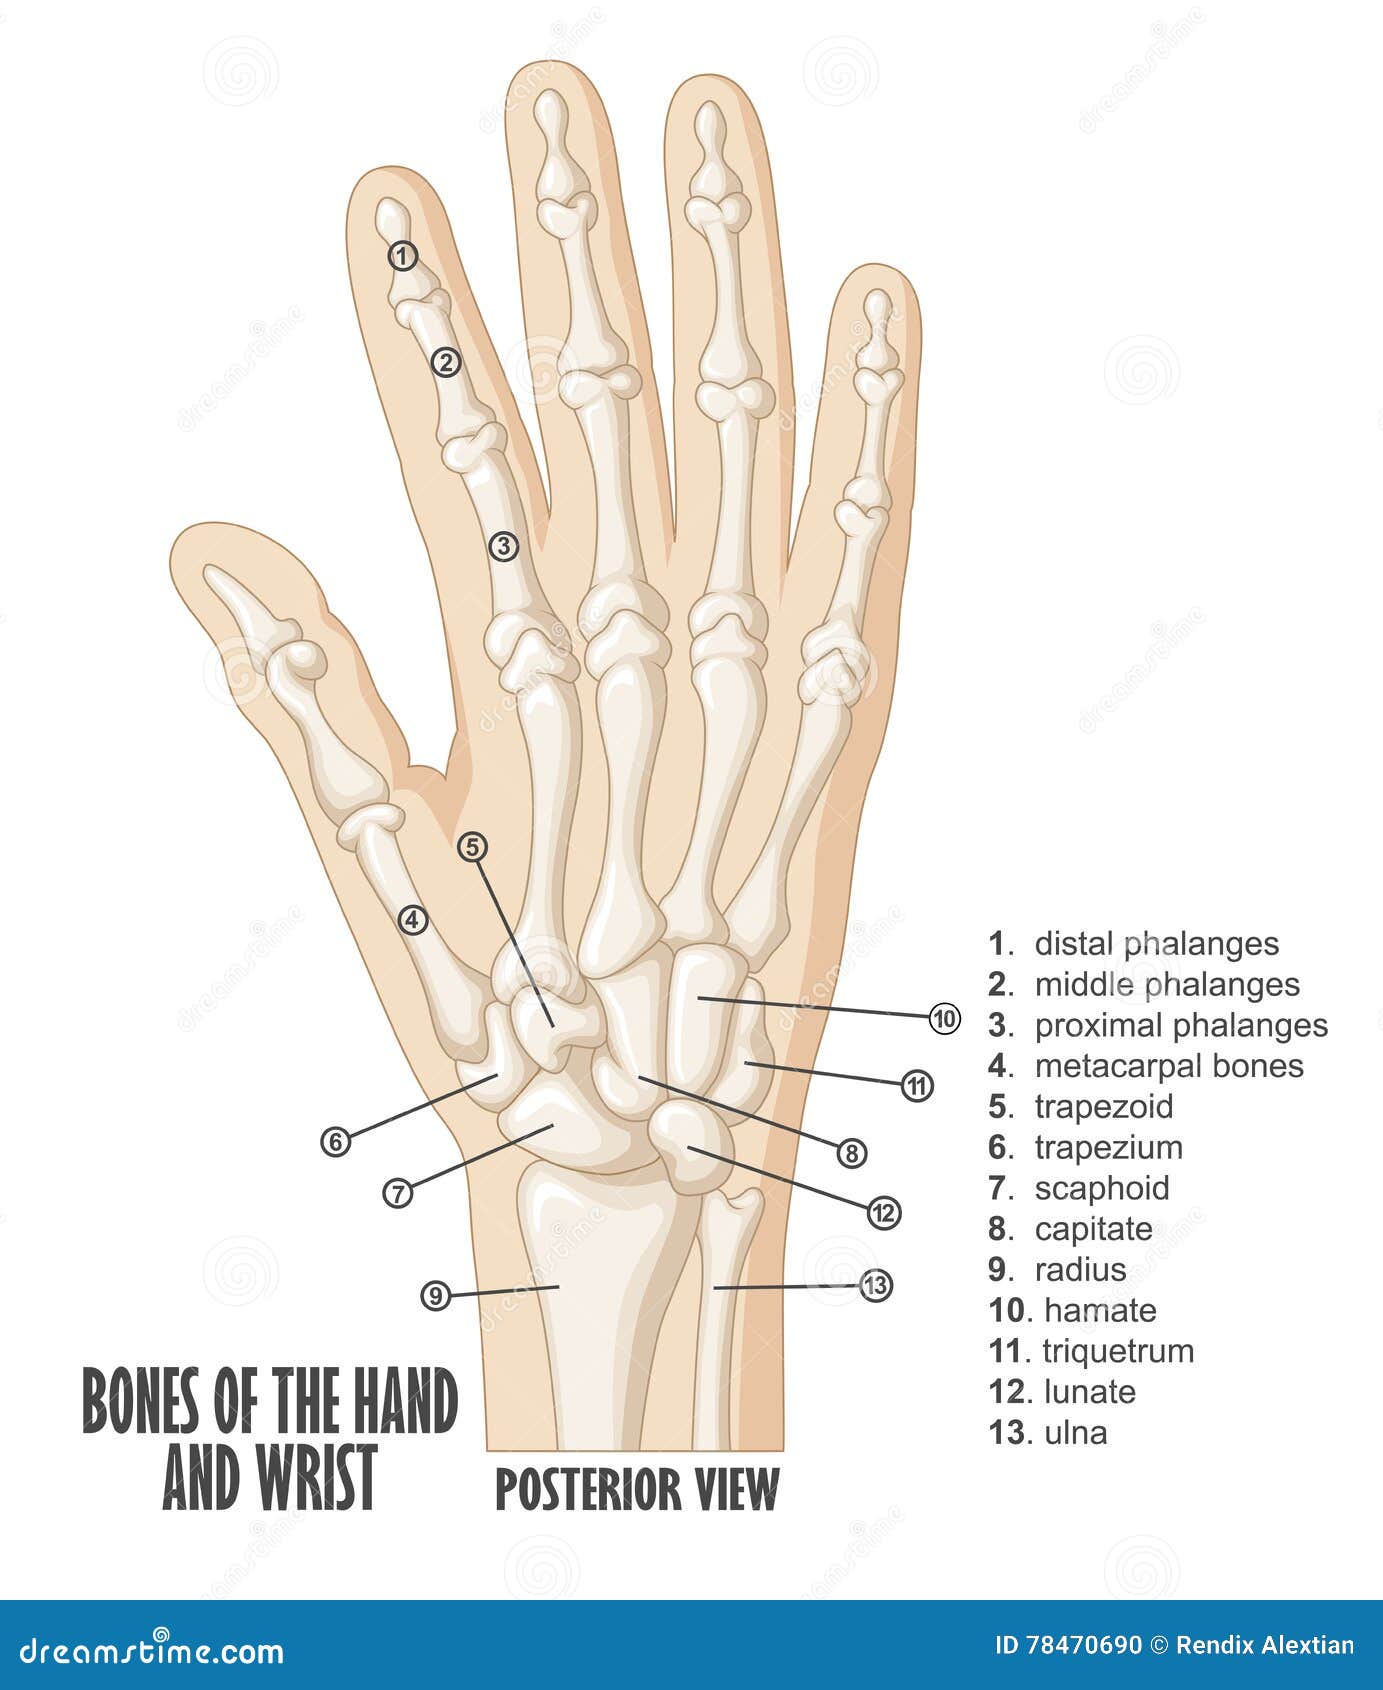
The carpal bones are arranged in two rows of four. Proximal row from lateral to medial: scaphoid, lunate, triquetrum, pisiform. Distal row: trapezium, trapezoid, capitate, hamate. The carpals articulate with the radius and ulna proximally, and the bases of the five metacarpals distally. Below that you have the metacarpals numbered one through five, and the phalanges, which total fourteen bones across the digits. That gives you the twenty-seven count. The scaphoid spans both rows functionally despite being classified in the proximal row, which is the first thing most people get wrong and the reason scaphoid fractures are missed at least forty percent of the time on initial imaging. The lunate is the keystone of the proximal row and articulates directly with the radius. Triquetrum and lunate share a common vascular vulnerability. Pisiform sits on top of the triquetrum and is sesamoidal in origin. Trapezium articulates with the first metacarpal for thumb opposition. Capitate is the largest carpal and sits centrally. Hamate has that distinctive hook projecting volarly, and the hook of hamate fractures are notoriously invisible on standard PA views without special projections. I once spent two hours trying to find a fracture line on a hamate shaft that was completely obscured because we were only looking at a plain PA film and a lateral. A dedicated ultralow-thumbs-up view revealed it immediately. That single projection saved a surgical referral that was nearly lost to a false negative. The hamate hook is another story entirely. You need a dedicated wrist series with a dedicated carpal tunnel view, and even then, CT will resolve it faster than you will trust your eyes on a two-dimensional image.
Vascular Patterns That Actually Matter
The scaphoid receives its blood supply retrograde, entering through the dorsal ridge and flowing toward the distal pole. A waist fracture disrupts flow to the proximal fragment in roughly seventy percent of cases. That is not a nice-to-know fact. That is the difference between a cast and a reconstruction. Proximal pole fractures carry a nonunion rate that approaches eighty-five percent if you miss the initial diagnosis and just immobilize them. I have seen it happen more times than I want to recount, and the patient ends up needing a vascularized bone graft from the distal radius, sometimes with fusion of the scaphocapitate unit if the damage is advanced enough. Lunateavascular status is better preserved but the perilunate dislocation sequence remains one of the most devastating injuries in the upper extremity if reduction is delayed beyond twelve hours. Median nerve compression at that point is not theoretical. It is usually already happening. The Guyon canal, formed by the hook of hamate and the pisiform, is another structure that gets overlooked on routine read sequences.
Get the Full Details

Common Errors On Plain Films
The biggest error I see is assuming a normal lateral film rules out a scaphoid fracture. Up to thirty percent of these fractures do not show on the initial lateral view alone. You need an oblique, a proper PA with ulnar deviation to open the scaphoid spaces, and if the clinical suspicion remains high after a negative series, you either immobilize and repeat imaging in ten to fourteen days, or you go straight to MRI or CT. I usually recommend MRI if it is available within a week because it picks up bone bruising and occult fractures simultaneously. CT is better for surgical planning once a fracture is confirmed. The overlap between the two is real but the indications are different enough that you should pick one before ordering the other. Another persistent mistake is mistaking accessory ossicles for fractures. The os styloideum at the base of the second metacarpal, the os trigonum of the wrist near the triquetrum, and bifid epiphyses at the distal radius are all common variants that look suspicious to an untrained eye. Smooth corticated margins and bilateral symmetry on the contralateral side are the reliable differentiators. If you are unsure, compare sides. Always compare sides.
Metacarpals And Phalanges In Practice
The metacarpals follow a fairly predictable pattern. Boxer fractures involve the fifth metacarpal neck. Bennett fractures involve the first metacarpal base and intra-articular extension into the trapeziometacarpal joint. Rolando fractures are the comminuted version of Bennett and carry a worse functional prognosis. You can tell them apart on a PA and oblique view alone if you look at the articular surface rather than just the shaft alignment. Shaft fractures are usually straightforward unless there is rotational malalignment, which you detect by having the patient make a fist and watching for crossover of the nails. Digital flexor tendon insertions and lateral band geometry mean even minor rotational errors compound quickly into claw-like deformities that are painful and difficult to correct later. The phalanges themselves are small and the soft tissue detail around them is limited on standard radiography. Distal phalanx tuft fractures from crushing injuries are usually visible but the tufts are often fragmented by the mechanism itself, making a clean fracture line impossible to define. In those cases you treat based on stability and skin integrity rather than pursuing a perfect radiographic classification. Tendon avulsions, mallet finger, and bumper fractures all occupy the same general radiographic space but require completely different management strategies. Knowing which one you are looking at is the actual skill here.
When Imaging Isn't Enough
Plain films miss dynamic instabilities. Ligamentous injuries like scapholunate dissociation and lunotriquetral tear often present with normal initial X-rays until the wrist is under stress. A grip stress view or fluoroscopic evaluation will reveal the widening that a static film hides. If you are relying solely on a standard three-view wrist series for anything beyond gross fracture detection, you are leaving a significant diagnostic gap. MRI arthrography fills that gap reasonably well and is the next step before you move to diagnostic arthroscopy, which remains the gold standard for ligamentous pathology but carries its own procedural risks and cost considerations. Ultrasound is useful for surface anatomy, tendon pathology, and some carpal ligament evaluations, but it cannot penetrate bone. It complements radiography rather than replacing it. CT is superior for complex intra-articular fracture characterization and preoperative planning, especially for distal radius and proximal row injuries. Each modality has a defined scope. Respect the scope.
What This Framework Won't Cover
This is not a substitute for formal anatomical study or structured radiological training. The descriptions above are simplified for practical reference, not for board examination purposes. Pediatric anatomy differs significantly due to ongoing ossification centers, and apophyseal variants in children can mimic fractures far more frequently than adult accessorial bones ever will. If you are interpreting imaging in a pediatric population, you need pediatric radiology reference material, not this summary. Similarly, osteoporotic wrists, diabetic hand changes, and inflammatory arthropathy alter bone appearance enough that standard interpretation rules require modification. Rheumatoid nodules along the extensor surfaces, DIP joint osteophytes in Heberden node presentations, and the characteristic periarticular osteopenia of inflammatory disease all change the diagnostic algorithm. The bones themselves are still the same twenty-seven plus metacarpals and phalanges, but the clinical context shifts the entire approach.
A Final Note On Scaphoid Management
If you suspect a scaphoid fracture and the initial imaging is negative, do not send the patient back without a plan. Thumb spica immobilization for ten to fourteen days followed by repeat imaging catches the majority of these. If repeat imaging remains negative but suspicion is still high, proceed to MRI. The cost and time tradeoff favor this pathway over immediate CT in most health systems, though individual institutional protocols may vary. I have seen too many scaphoid nonunions develop because the initial read was dismissed and the patient was told to return to normal activity without follow-up imaging scheduled. That is a preventable complication.