Why Learning Skull Anatomy Actually Matters
Most people think skull bones are just a collection of hard plates protecting the brain. That's technically correct but misses why anyone studying this really cares. The sutures between those bones tell you things. In forensics, for example, a fused sagittal suture on a set of remains can narrow down age more reliably than teeth in older adults. I've seen students skip the fine details because they figure "it's just bones" and then completely freeze when asked to identify something like the pterion region on an unknown specimen. The real problem is that skull anatomy books make everything sound far more straightforward than it actually is. They give you clean diagrams with labeled parts. They don't show you what happens when someone's skull doesn't follow the textbook perfectly, which is basically always the case in real practice.
Understanding the Bones Of The Skull
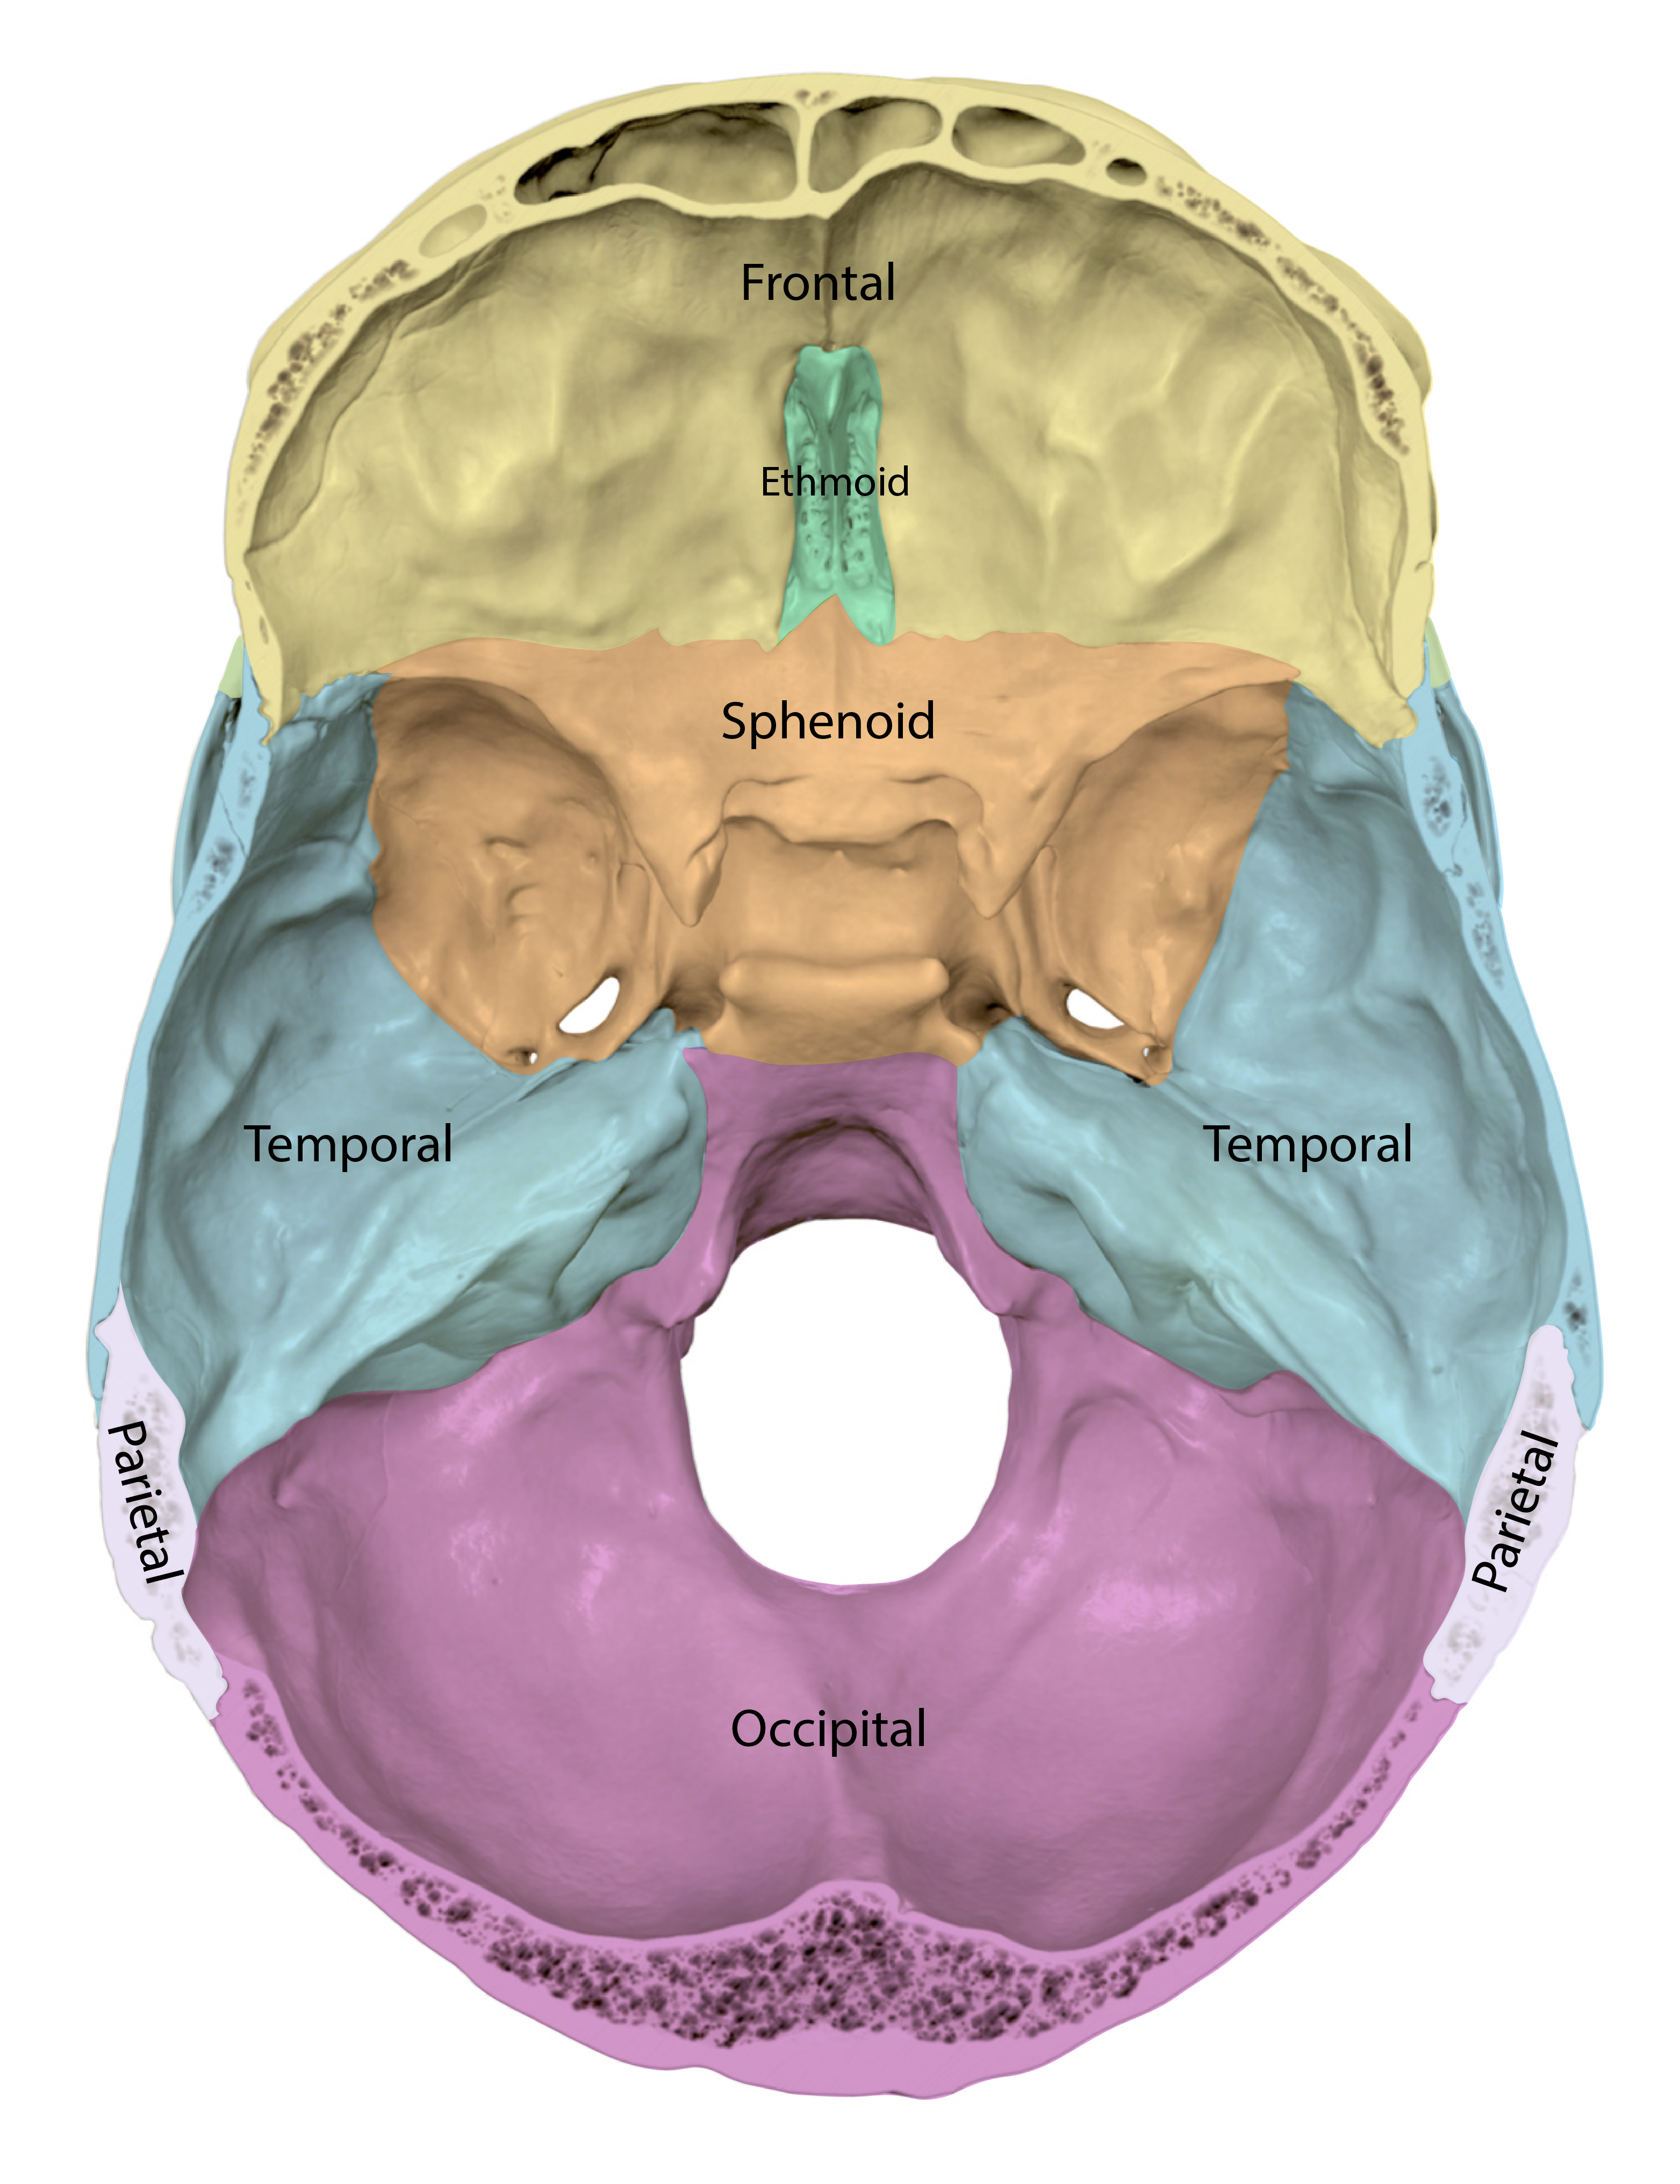
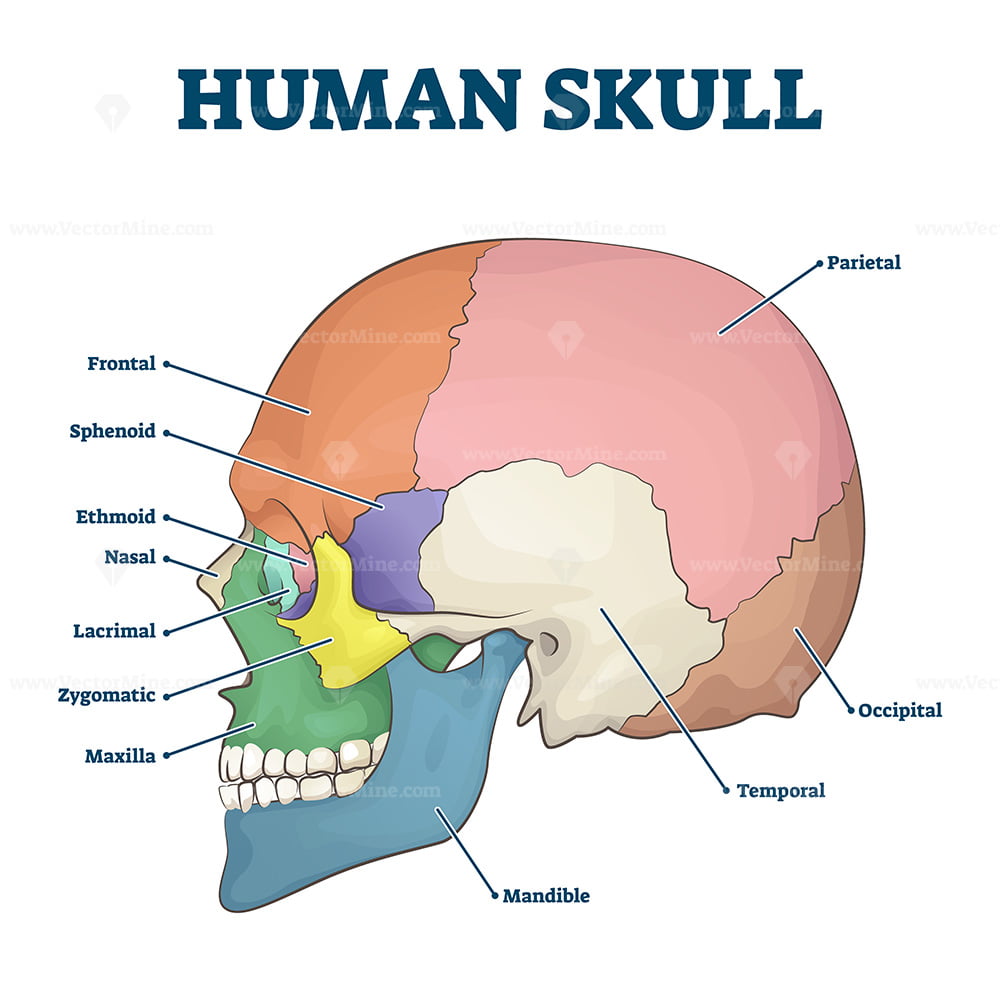
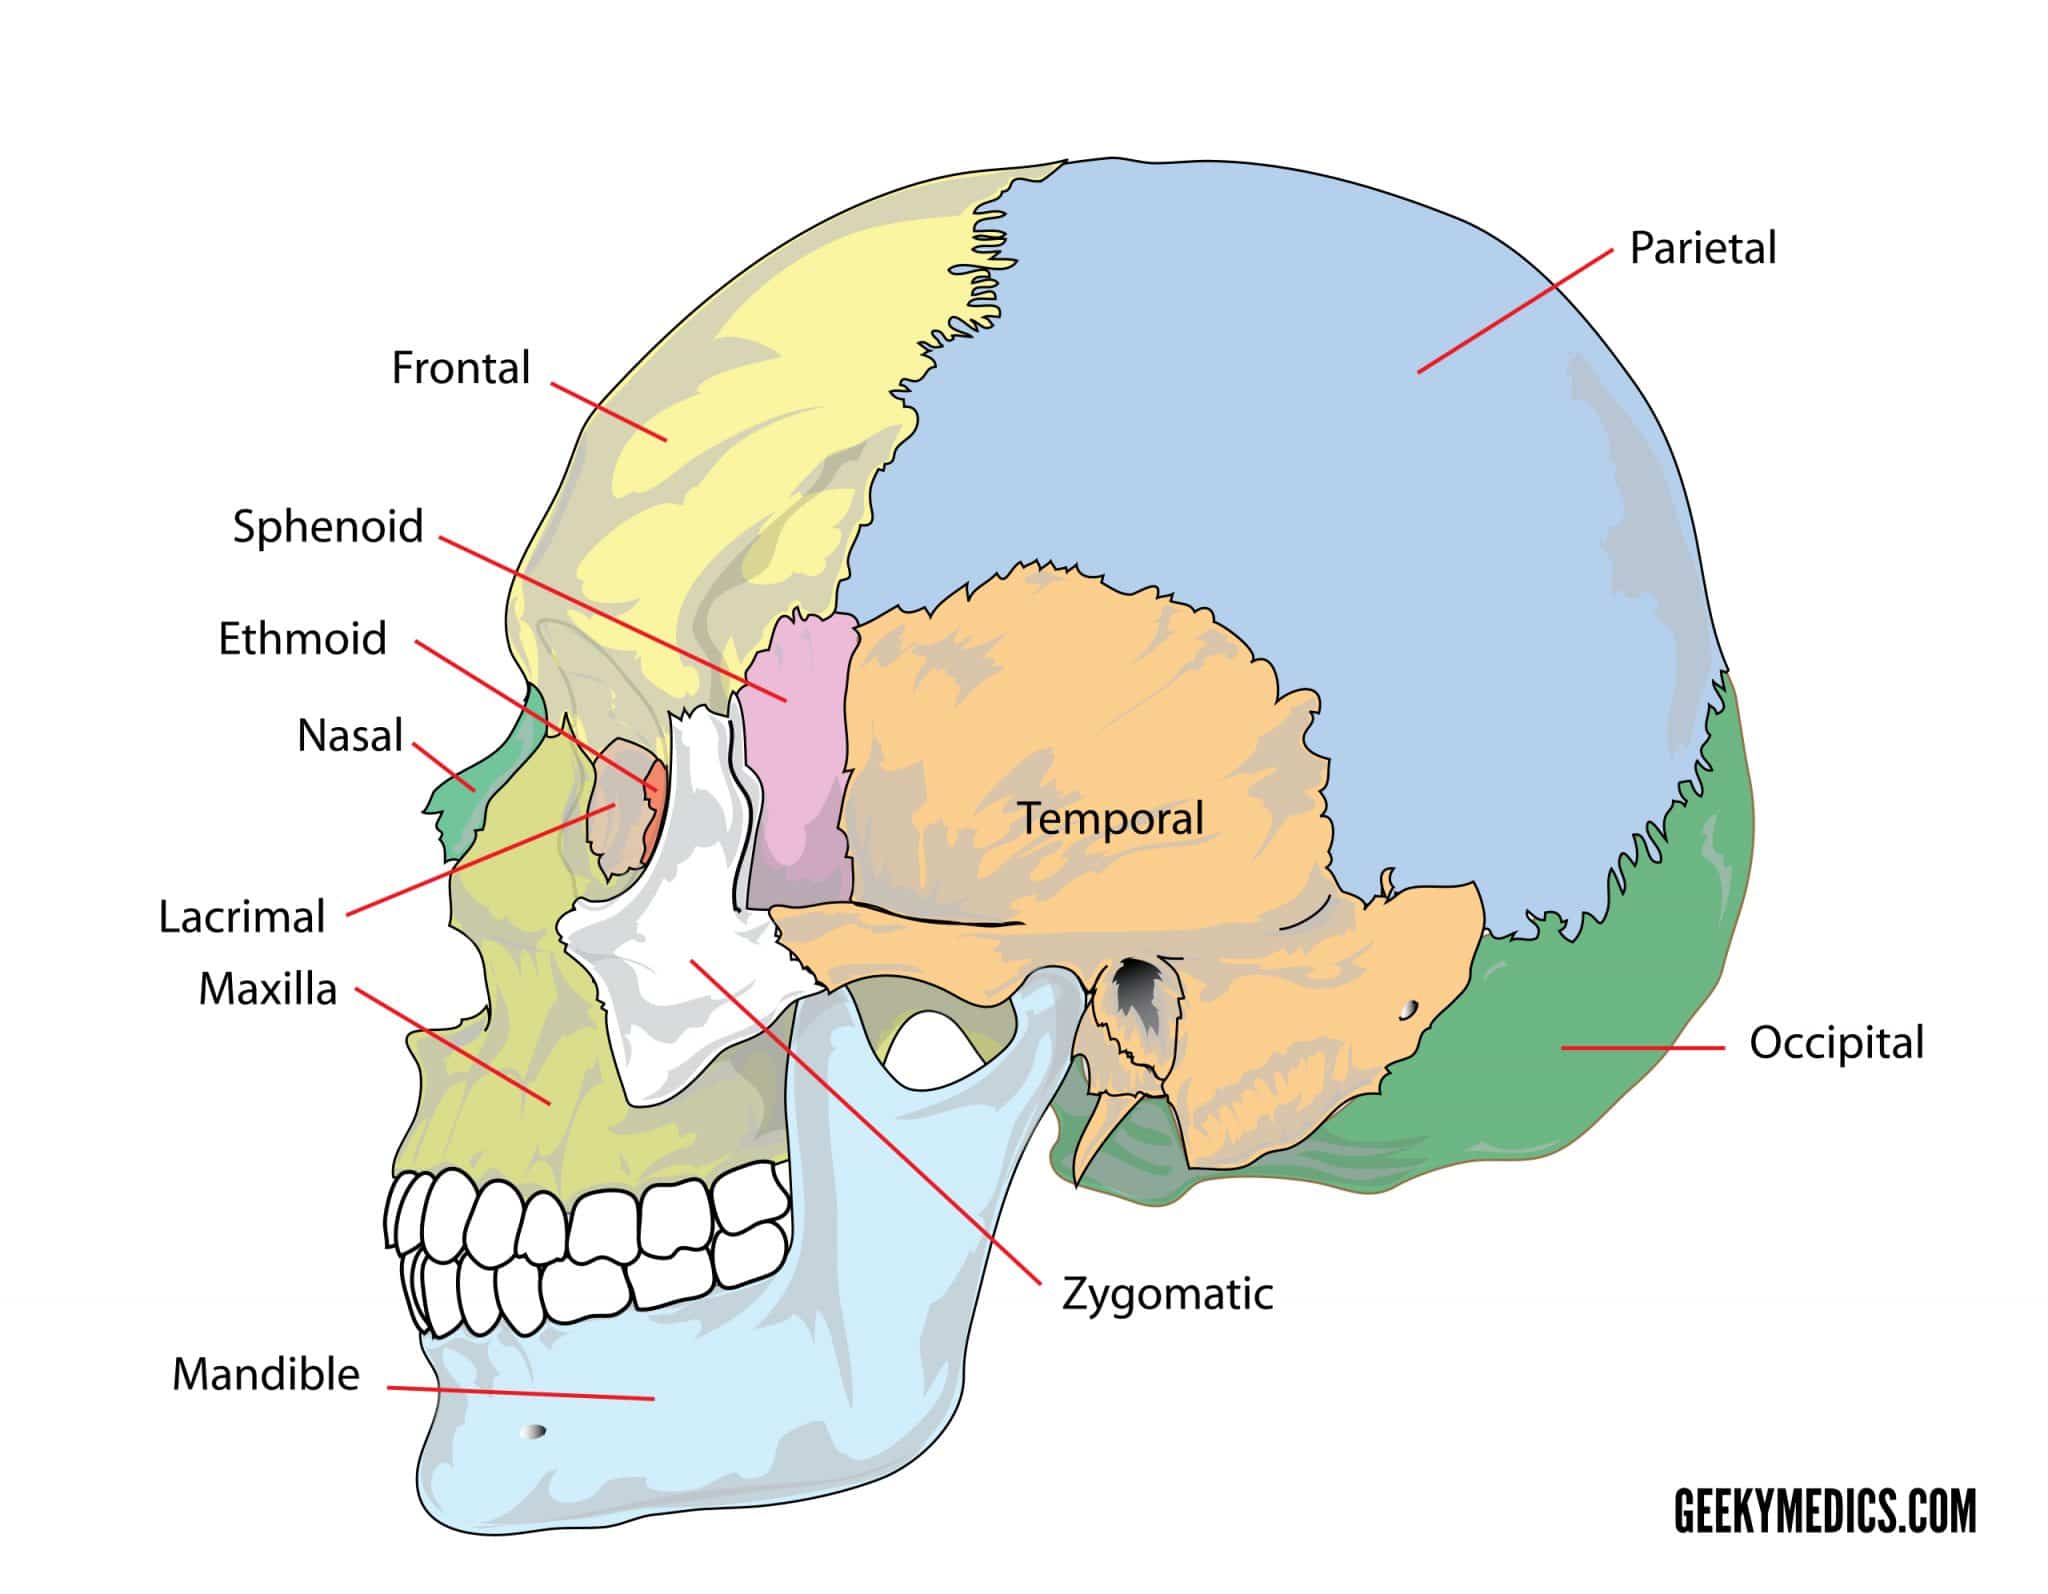
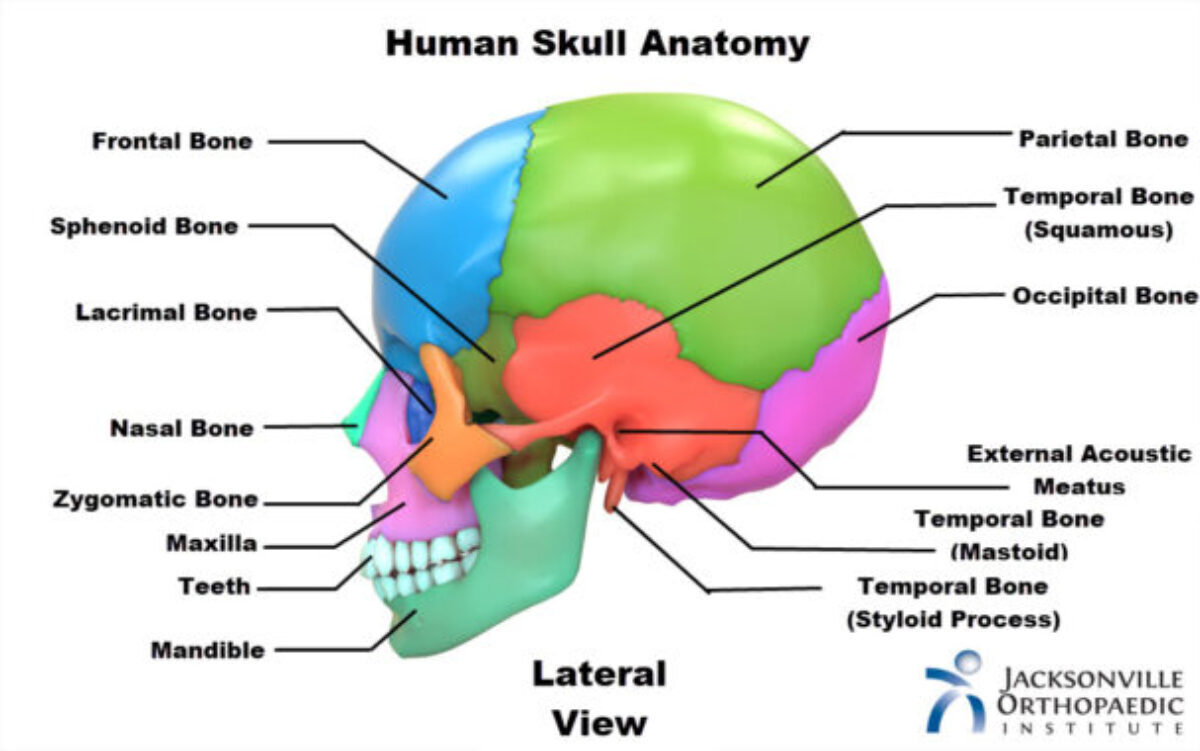
The skull breaks into two main categories. The neurocranium forms the protective case around the brain. The viscerocranium makes up the facial skeleton. Together they contain about twenty-two bones, though some classifications get messy depending on whether you count individual structures like the ossicles separately. Start with the bones themselves. The frontal bone sits at the forehead and upper face. The parietal bones form the sides and roof. The temporal bones sit on each side and house the structures for hearing and balance. The occipital bone is at the back where the foramen magnum sits. The sphenoid bone is that weird bat-shaped one in the middle that connects to almost everything else, which makes it critically important but also confusing for beginners. The ethmoid bone sits between the eyes and contributes to both the nasal cavity and the orbital walls. On the facial side you have the maxillae, which fuse together and form the upper jaw. The zygomatic bones make the cheekbones. The mandible is the only movable bone. The nasal bones are tiny and easy to miss. The inferior nasal conchae curl inward and are often fragmented. The palatine bones sit in the back of the nasal cavity. The vomer forms part of the septum.
Here's what nobody tells you early on: memorizing names without understanding the landmarks is useless for practical work. I spent weeks flashcarding bone names until I realized I couldn't point to the crista galli on an actual specimen. That changed everything. I started learning by palpating my own skull and tracing the sutures with my fingers. It sounds odd but it works. You feel the coronal suture run across the top of your head, the sagittal suture going front to back along the midline, and you quickly start seeing how the shapes interlock rather than just remembering lists.
Get the Full Details
Common Pitfalls And Where People Mess Up
The biggest mistake I see is not learning left from right. Students will point to the wrong side and then get confused about why their labels don't match the diagram. Always orient yourself properly. The glabella sits between the eyebrows as a midline landmark. The mentum or mental protuberance is the chin. Once you anchor yourself to those, lateral structures fall into place. Another issue is confusing the facial features of different bones. The frontal bone has frontal sinuses above the orbits. The maxilla has the larger maxillary sinus. Beginners often mix those up when looking at CT scans or X-rays. I had a case where someone was presenting a radiograph and couldn't tell whether a fracture line ran through the zygomatic arch or the temporal squama. They looked exactly similar on a two-dimensional image. Drawing out the anatomical relationships before looking at scans completely fixed that for them. The sphenoid bone deserves special attention because it shows up everywhere. It forms part of the cranial floor. It has the sella turcica that holds the pituitary gland. It has the pterygoid processes that serve as attachment points for muscles involved in chewing. If you don't understand the sphenoid well, you don't really understand skull anatomy at all.
How To Actually Retain This Information
Flashcards help for vocabulary but they're not enough. You need to handle real specimens or high-quality three-dimensional models. If you're studying for an exam, I'd recommend using a skull app or atlas alongside physical manipulation. Trace each suture. Run your thumb along the inferior orbital margin and feel where it transitions into the zygomatic bone. Notice how the temporal line curves upward and backward from the zygomatic process. For exam purposes, focus heavily on the foramina and what passes through them. The foramen magnum, the superior and inferior orbital fissures, the optic canal, the foramen rotundum, the foramen ovale, the foramen spinosum. Each one has a specific structure associated with it. I used a simple mnemonic system that wasn't particularly elegant but it stuck. I'd draw a rough skull outline and fill in every opening with its contents until I could do it from memory without looking. When dealing with forensic or medical imaging contexts, learn the differences between adult and pediatric skulls. The fontanelles in infants are soft spots where the bones haven't fused yet. Those close at different rates. The anterior fontanelle typically closes by eighteen months. The posterior fontanelle closes much sooner, around two to three months. If you're working with subadult remains, those fusion patterns become important age indicators.
Bones Of The Skull In Practice
I once had a situation where a student was trying to identify fragments from a commingled burial. They found a piece they were fairly certain was part of the temporal bone but couldn't confirm it. The fragment had a portion of petrous ridge and what looked like part of the tympanic ring. Without the rest of the skull context, it was genuinely ambiguous. The workaround was to look at the density and texture. The petrous portion of the temporal bone is some of the densest bone in the entire body, which is why it preserves so well in archaeological contexts. I had them compare the fragment against reference samples of known petrous bone and that sealed it. Density and color difference are usually enough to distinguish it from parietal or occipital fragments. For anyone preparing for practical exams, I'd recommend working with side identification first. Learn to tell left from right on every single bone. Then move on to superior, inferior, anterior, and posterior views. Each bone looks completely different depending on the angle. The mandible is relatively straightforward but the sphenoid and ethmoid change dramatically between different perspectives. The temporal bone alone contains the external acoustic meatus, the styloid process, the mastoid process, the tympanic plate, and the petrous part. That's four major regions in one bone. I've seen people spend an entire study session on just that one bone because it keeps showing up in unexpected ways on tests and in real cases.

If you're looking for resources, most anatomy textbooks cover this thoroughly but they tend to be expensive. Open access atlases like the one from the University of Michigan or the Visible Human Project provide detailed images at no cost. Some online platforms offer interactive 3D models that let you rotate and isolate individual bones, which speeds up the learning curve considerably compared to static diagrams. The bottom line is that skull anatomy requires spatial understanding more than rote memorization. Once you can picture how these bones fit together in three dimensions, the details start connecting on their own. The foramina make sense because you understand what's passing through them. The muscle attachments make sense because you know which movements they facilitate. The sutures make sense because you understand the growth and development patterns. Build that foundation first and everything else becomes significantly easier to handle.