What You Actually Need Before You Touch A Needle
Most people come into Botox And Lip Filler Training thinking the course is about injection technique. It isn't. The course is about not ruining someone's face because you skipped anatomy. I've watched three different programs this year. Two of them spent forty-five minutes on marketing and twenty minutes on actual landmass mapping. That's not uncommon. Here's how the whole process actually works when you strip away the brochure language. You start with cadaver dissection or high-resolution ultrasound lab work. Not the thirty-second video they show you during orientation. Real hands-on identification of the orbicularis oris, the depressor septi, the marginal mandibular branch of the facial nerve. If your program doesn't give you at least six hours in a lab with human tissue, you're not getting trained. You're getting certified online and that's a different thing entirely. I had a student once who came from a nursing background with five years of IV experience. She thought she understood vasculature. She injected a lateral tail of the brow with botulinum toxin type A and missed the frontalis entirely, landing in the orbicularis oculi. The patient developed a complete ptosis on that side and couldn't close the eye for twelve days. We spent the next three weeks doing cold compresses and artificial tears management because there's literally nothing else you can do while the toxin runs its course. It was uncomfortable to watch. I still think about it sometimes when I'm grading practicals.
Botox And Lip Filler Training: What The Curriculum Actually Looks Like
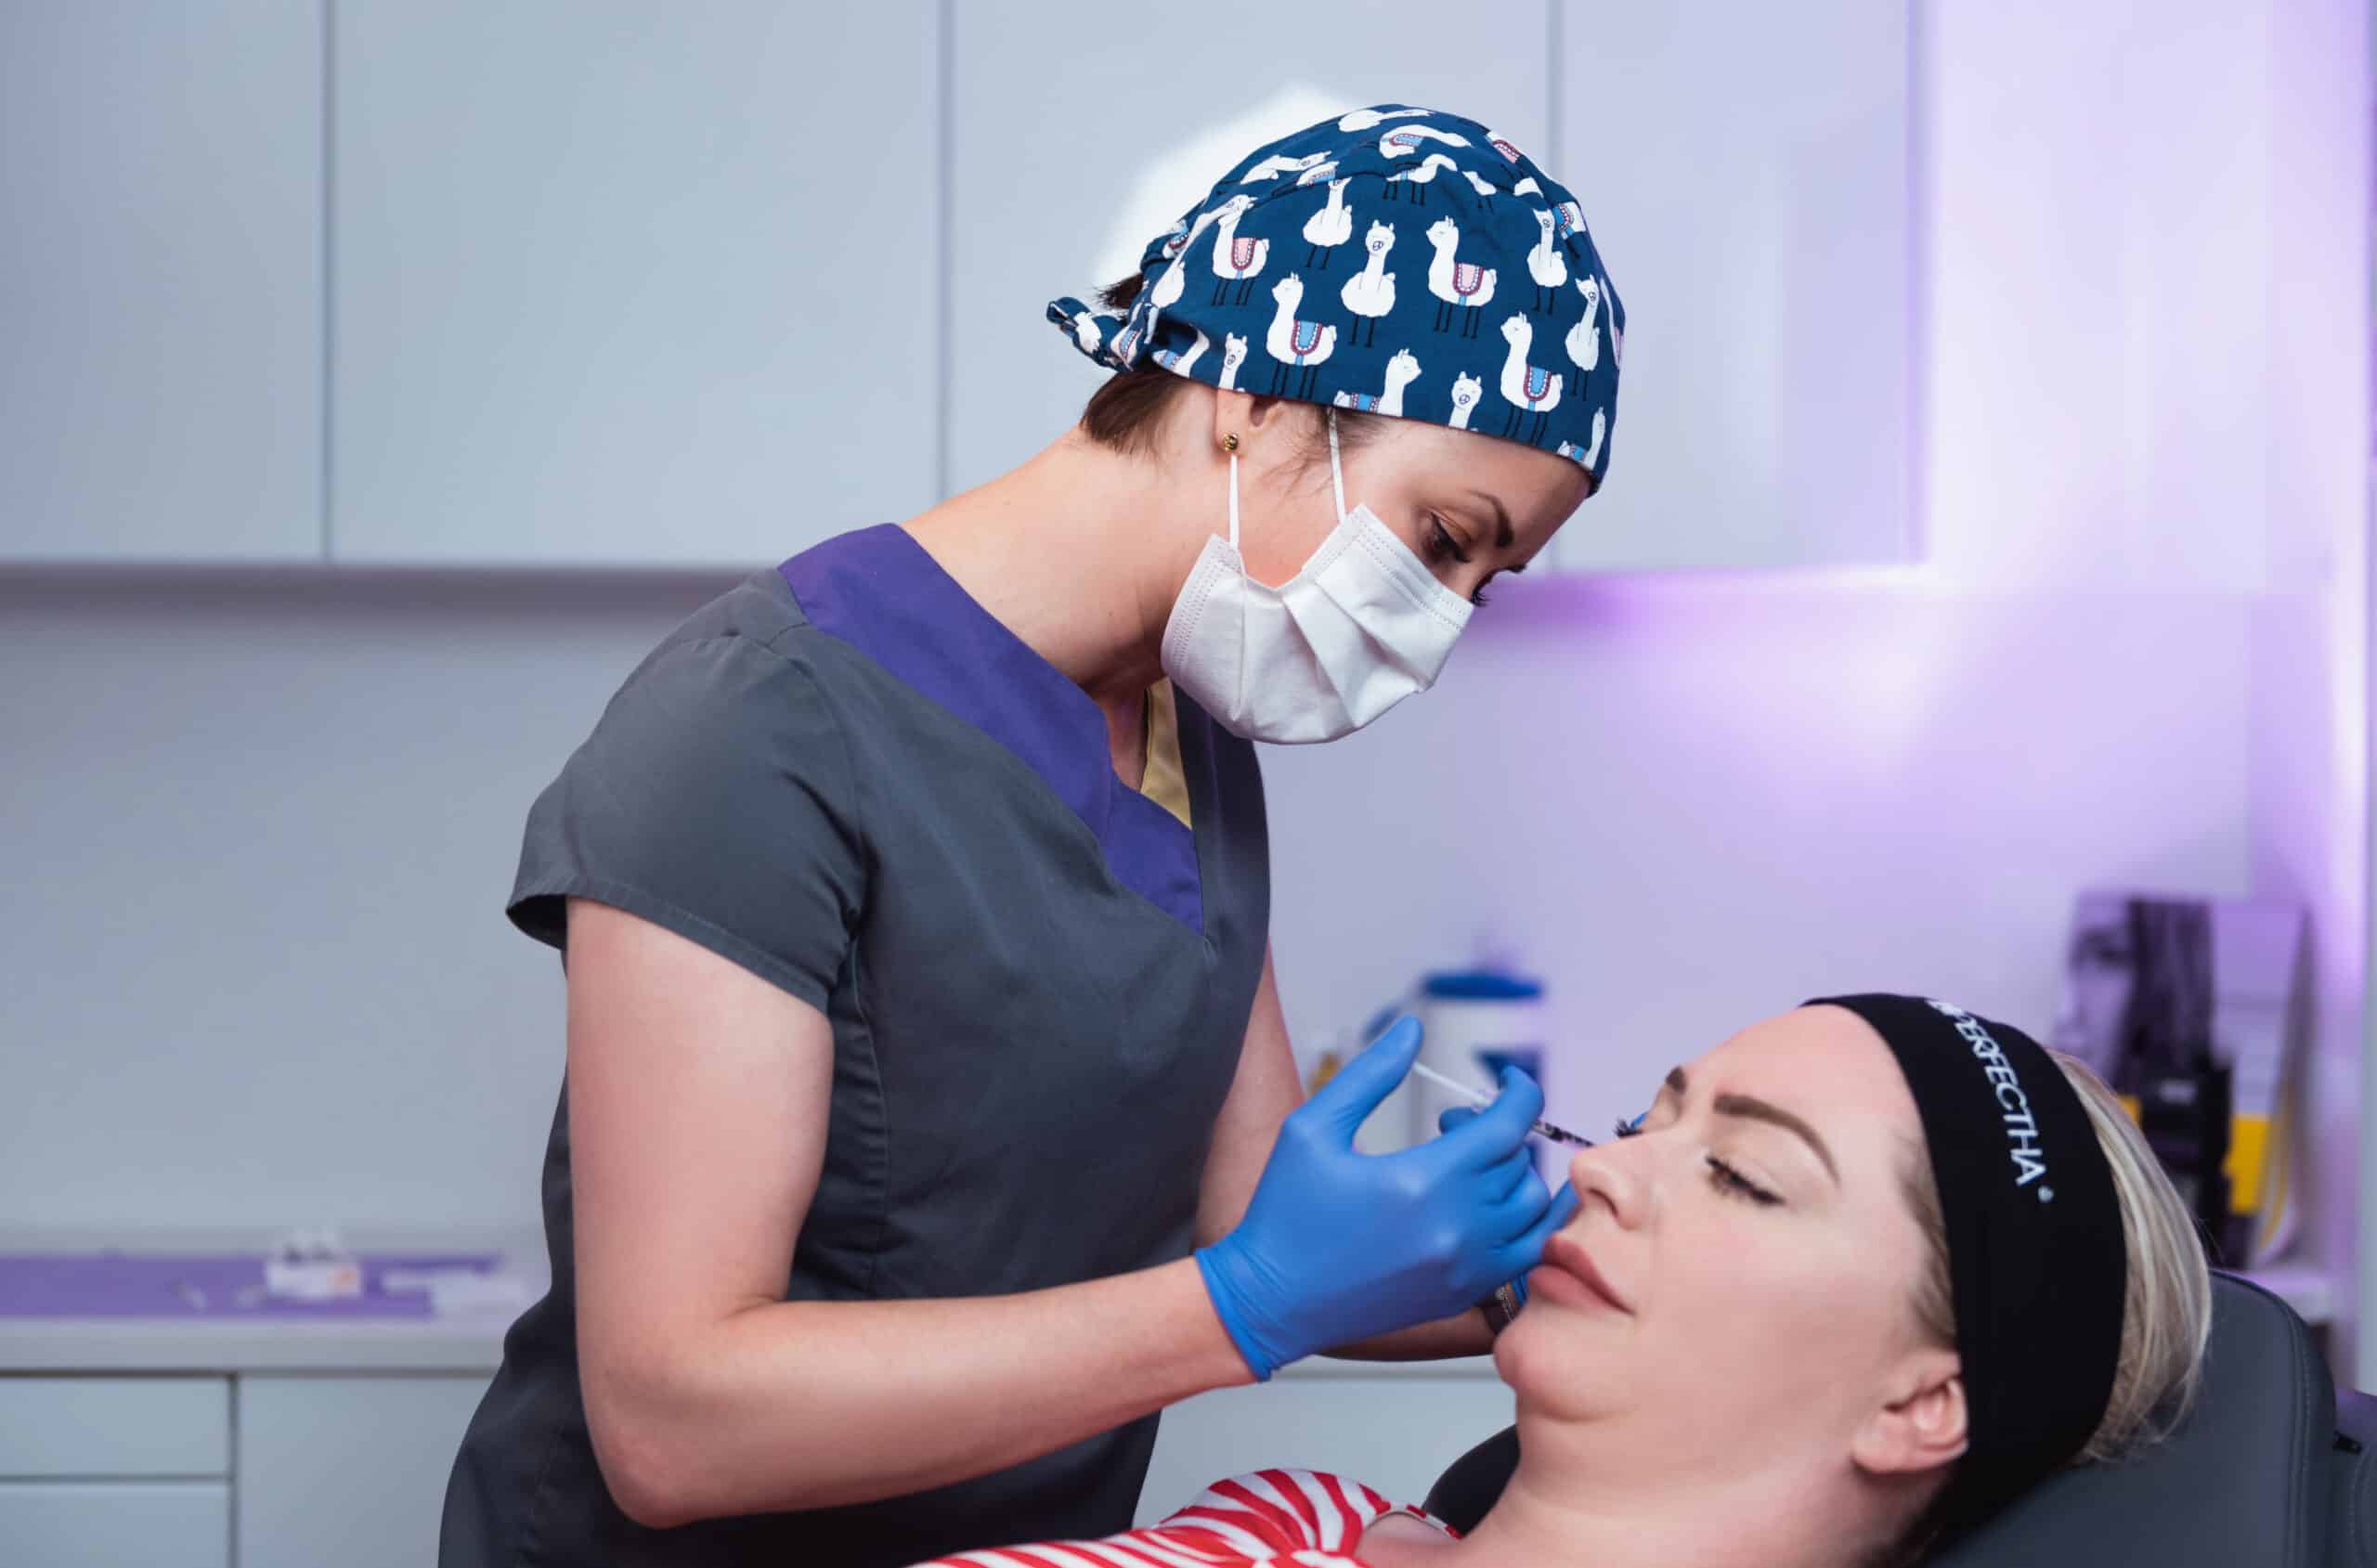
A legitimate program runs between forty and sixty hours. Not four hours over a weekend like some of the pop-up courses running out of dental offices in suburban areas. The structure breaks down into roughly four phases. Phase one is anatomy and surface landmarks. You need to be able to identify every relevant structure blindfolded, literally. I've had my students do this exercise where I point at random spots on a skull and they have to name the underlying neurovascular structure without looking at any diagrams. It takes about two weeks of daily drills to build the muscle memory. Phase two is product knowledge. Not brand names and prices. Mechanism of action, diffusion characteristics, reconstitution ratios, shelf life after opening, contraindications that aren't listed on the FDA insert. For example, people don't talk much about how hyaluronidase timing works when you need to dissolve a filler complication. If you inject Restylane and see immediate vascular occlusion, you don't grab a syringe and run. You calculate the volume needed based on the weight of hyaluronic acid deposited, the area involved, and whether you're using a high-G-prime or low-G-prime product. That matters. A high-G-prime filler like Volux requires significantly more hyaluronidase units per milliliter than a soft product like Captique. Most courses skip this. Phase three is simulation work. You practice on synthetic skin pads, then on fruit, then on live models under direct supervision. The transition from synthetic to live tissue is where most programs fail their students. The feedback loop is completely different. Synthetic material doesn't bleed. It doesn't have fascial planes that resist your needle. It doesn't move when you ask it not to. I require every student to complete at least ten injections on a live model before they touch another person independently. There's no shortcut around that.
Phase four is complication management. This is the part nobody wants to spend time on but it's the part that separates practitioners who build careers from the ones who get sued. You need to know how to recognize early signs of vascular compromise, how to aspirate properly, where to apply hot compress versus cold, when to escalate to a hyperbaric chamber referral, and how to document everything so your malpractice carrier doesn't void your policy because you wrote something ambiguous in your consent forms. The assessment piece is usually a written exam and a practical evaluation. The written exam covers dosing calculations, contraindications, product handling, and emergency protocols. I've seen people fail by not being able to calculate a correct reconstitution ratio for onabotulinumtoxinA. You're diluting 100 units with 2.5 mL of sterile saline to get 4 units per 0.1 mL. Do that wrong and you're either wasting product or creating a dosing error that could spread beyond your target area. The practical has you performing a standard brow lift protocol and a lip augmentation on a live model while an instructor watches and grades each step. There are real limitations to what any classroom setting can teach you. You cannot learn complication management from a textbook. I learned mine from a hematoma that wouldn't stop oozing during a nasolabial fold injection in my second year of practice. The patient was on clopidogrel and hadn't disclosed it during screening. I had a 3M gauze pack, straight pressure, and ice. It took forty minutes to control. After that, my pre-injection screening protocol changed permanently. I ask about every medication, every supplement, every over-the-counter drug. Even fish oil and ibuprofen get flagged now.
Get the Full Details
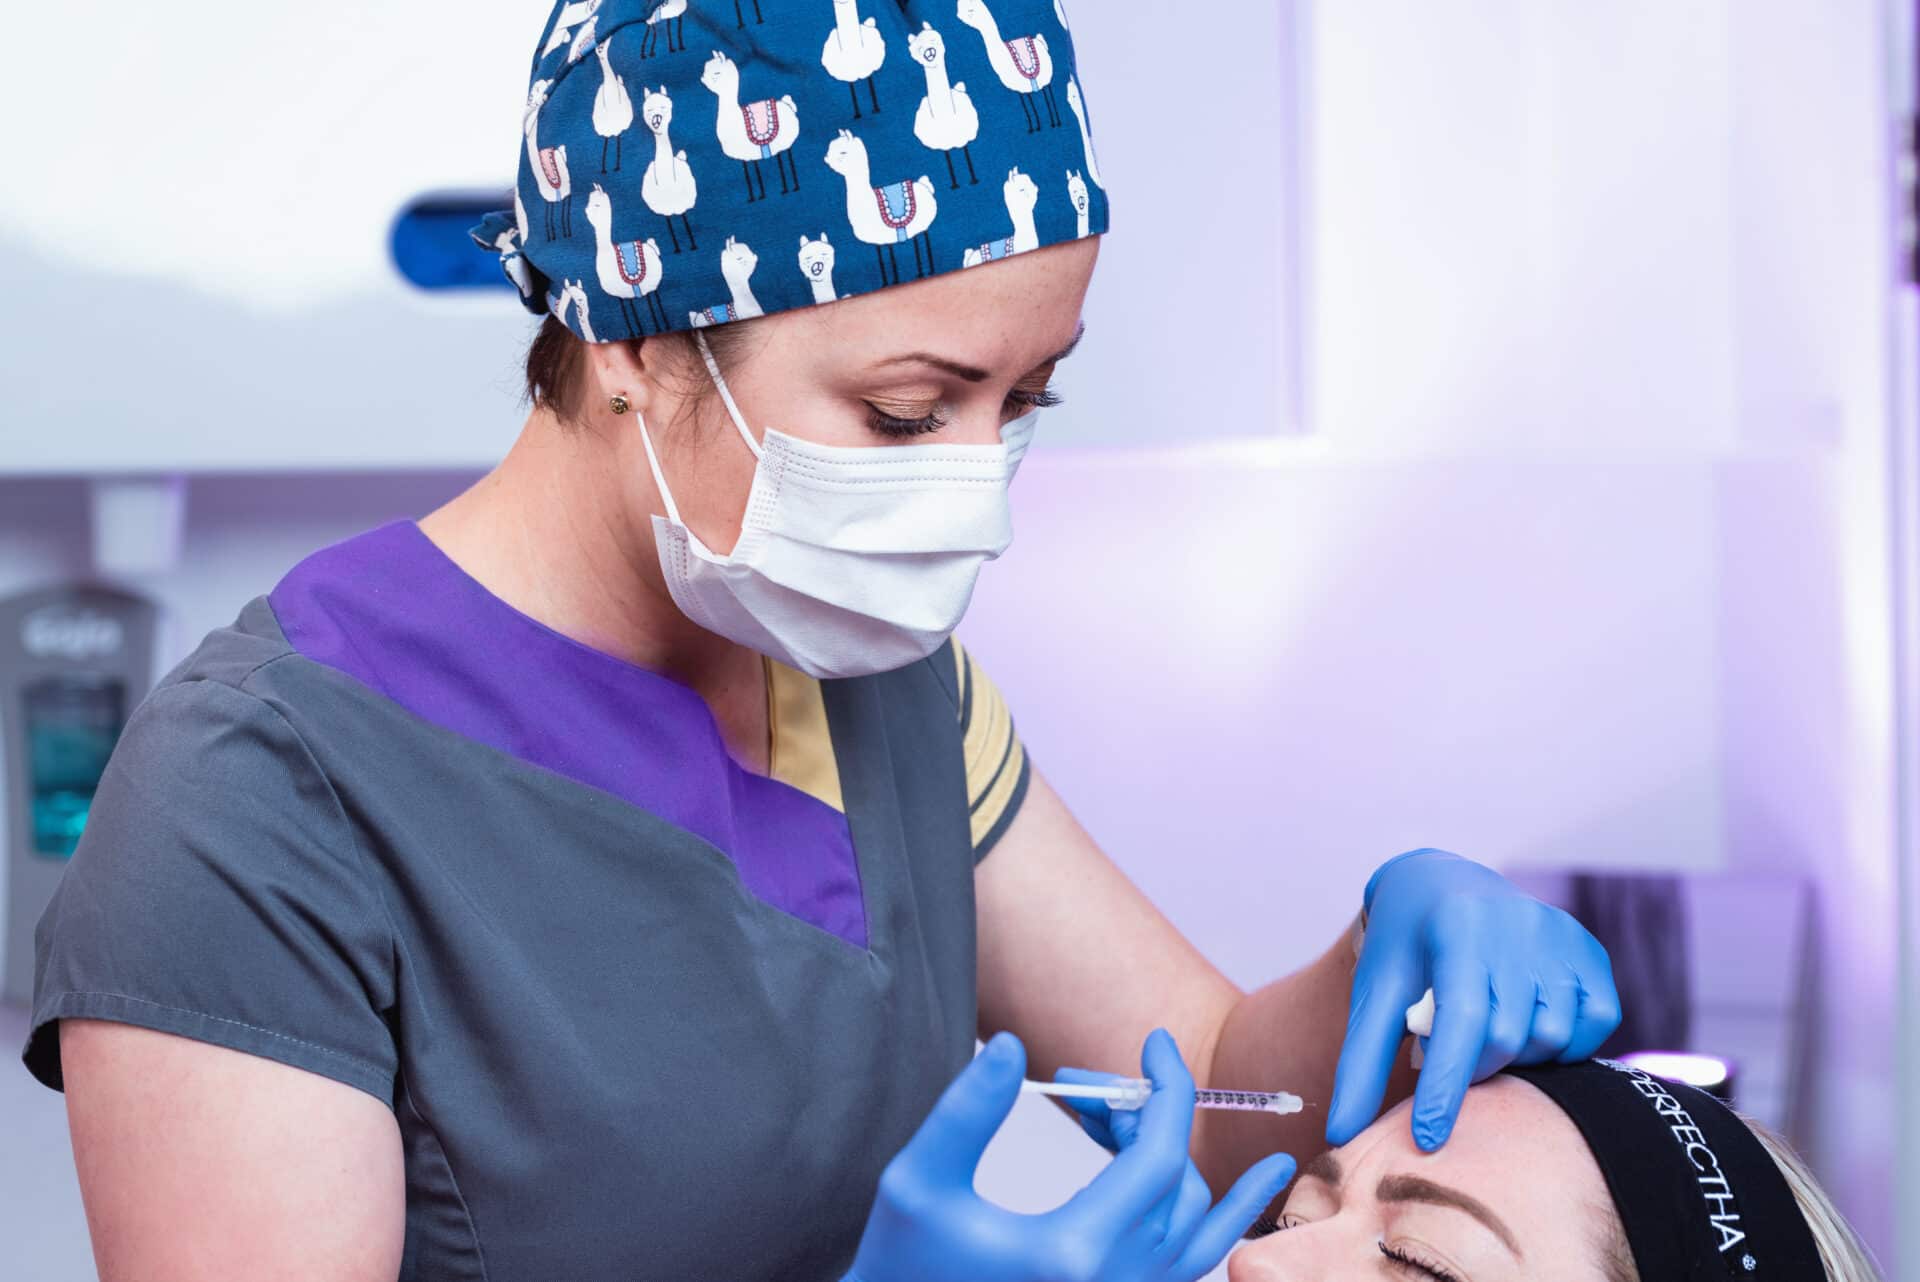
Another counter-intuitive thing: more product is rarely better for lip filler. Beginners consistently overfill because they're chasing volume instead of structure. The vermillion border doesn't need three milliliters. It needs careful placement along the tubercles and the Cupid's bow with a micro-cannula technique using a 25-gauge or 27-gauge device. I typically see practitioners who invest in proper cannula training achieve better aesthetic results with half the product volume compared to those using needle techniques. The cannula also reduces bruising incidence significantly because you're displacing tissue rather than piercing through it. If your training program doesn't include a mentorship period after certification, be cautious. The certificate itself means very little without ongoing supervision. Look for programs that offer at least three months of proctoring where an experienced injector reviews your cases, watches your technique via video, and provides feedback on your anatomical approach. Some jurisdictions require this. California mandates a minimum of sixteen hours of hands-on training with live models under direct supervision before you can legally administer botulinum toxin injections. Texas has similar requirements. Check your state board before enrolling in anything. The cost range for comprehensive training runs from two thousand to eight thousand dollars depending on the depth of cadaver labs included and whether the program offers ongoing mentorship. The cheapest options usually cut corners on hands-on hours or skip complication management entirely. The expensive ones sometimes inflate prices with unnecessary branding and networking events. Pay for lab time and mentorship. Skip the branded tote bags and lunch catering.