How the Braden Scale Actually Works in Practice
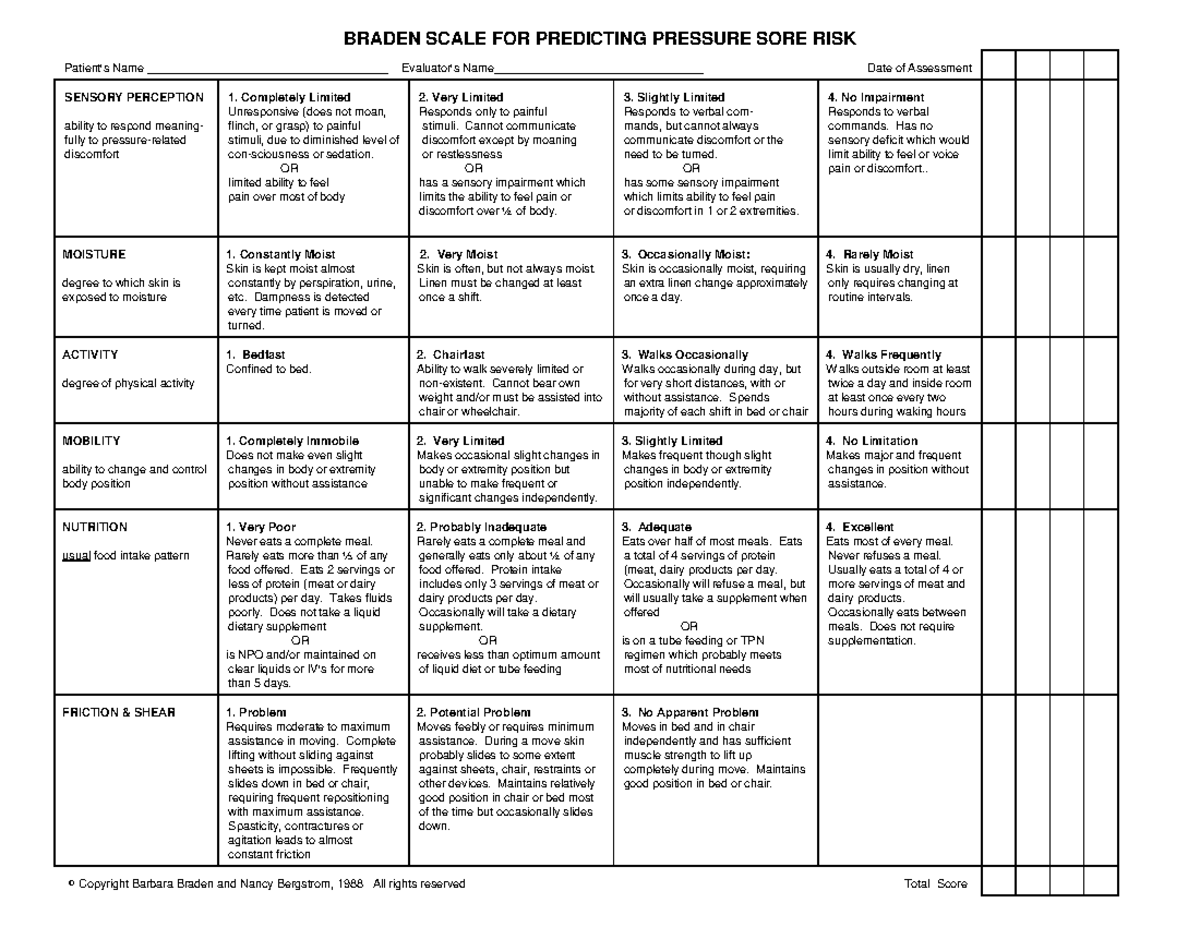
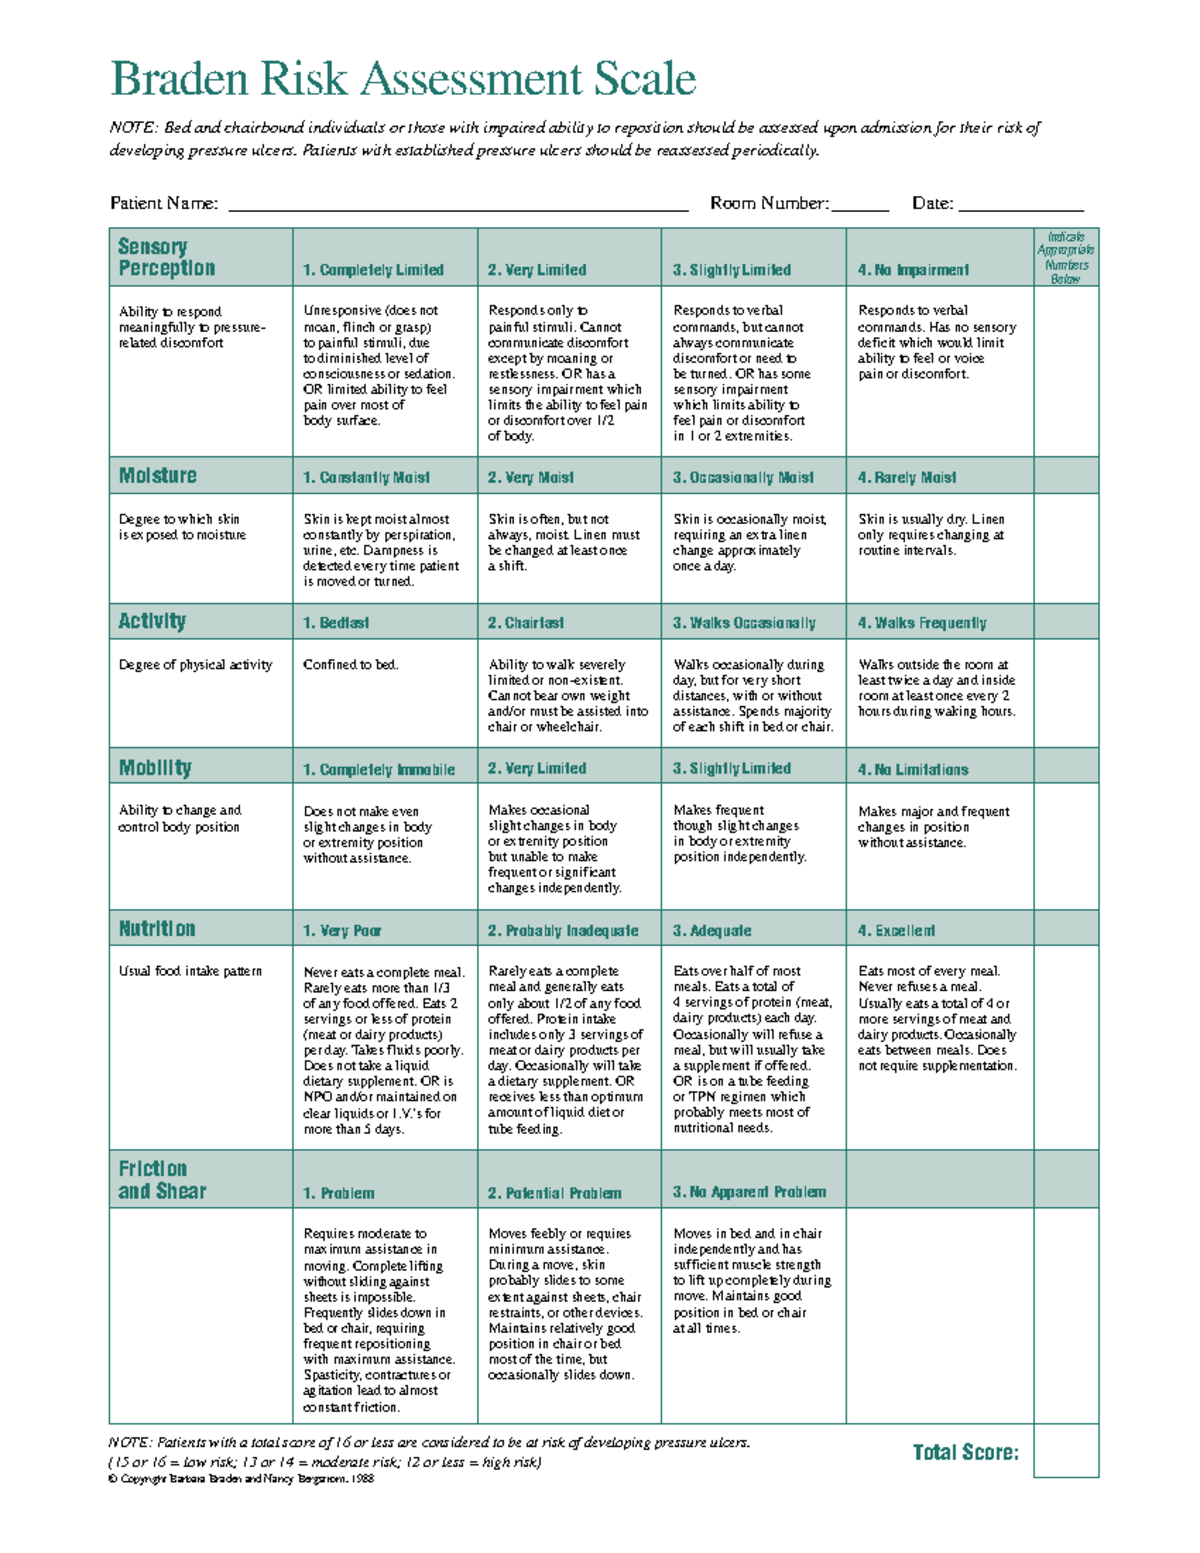
The Braden Scale Assessment Tool scores risk for pressure ulcer development across six domains. Mobility, sensory perception, moisture, activity, nutrition, and friction/shear each get a score from 1 to 4, except friction and shear which top out at 3. A total score between 9 and 23 tells you the severity of risk, with anything under 12 flagged as very high. That is the textbook version. Here is what nobody tells you on orientation. I used to rush through this assessment during morning shifts when everything else was falling apart. I would sit on the edge of the bed, glance at the patient, knock out the scores, and move on. A couple of years ago I caught myself giving a post-op cardiac patient a mobility score of 2 because they were in bed all morning, even though they had walked to the bathroom two hours prior and would be ambulating again that afternoon. The score should have been 3. That one wrong number pushed the total from moderate risk into high risk, which triggered unnecessary wound care consults and alarmist documentation that cluttered the chart. I stopped doing that. Now I wait until I have observed the patient actually moving through their day before I write the score down. It adds about three minutes to the assessment but saves an hour of correcting notes later. The scale asks you to evaluate how a patient moves, not just where they are lying when you walk into the room. Activity is scored based on actual ambulation frequency over a 24-hour period, not momentary ability. A patient who uses a wheelchair but transfers independently gets a different activity score than someone who only walks with two-person assistance. These distinctions matter more than most staff realize during a busy shift.
Sensory perception is the domain people mess up most often. The question is whether the patient can physically feel stimuli that would make them uncomfortable, not whether they understand pain or can describe it verbally. A diabetic neuropathy patient who cannot feel a wet sheet but can still talk to you should receive a score of 2, not 1. That single correction changes the entire risk profile. I learned this after reviewing a wound that developed on the sacrum of a patient whose Braden score listed him as moderately risk, not severely at risk. He had a 2 in sensory perception, not a 1, and the documentation could have caught the issue earlier if the score had been accurate at the start.
Where the Tool Fails and What to Do Instead
The Braden Scale is not designed for all patient populations and pretending it is will get you in trouble. It does not adequately account for vascular compromise, edema, or skin conditions like dermatitis that increase breakdown risk independently of immobility. A patient with severe peripheral arterial disease and dry gangrenous toes can score a 16 on the Braden and still develop tissue loss within days. The tool simply does not measure perfusion. In those cases I supplement the Braden with a peripheral vascular assessment and document the vascular findings separately rather than inflating the Braden score to force it to tell a story it cannot tell. Another gap is moisture. The scale captures whether skin is occasionally moist, frequently moist, or constantly moist, but it does not distinguish between urine, sweat, and wound exudate. Dampness from incontinence carries a different tissue impact than diaphoresis from fever. Both score the same on the scale. I note the source of moisture in my assessment comments so the next nurse understands why the skin is compromised beyond what the number alone conveys. I recently worked with a patient who had a consistent Braden score of 14 throughout the entire admission, yet developed a Stage 2 pressure injury on the left heel within 48 hours. The issue was friction and shear during repositioning. The scale scored the friction and shear domain as 2, which is not the lowest possible score, but it missed the fact that the patient was being dragged across the sheets rather than lifted during turns. Dragging creates shear forces the scale acknowledges in the abstract but does not weight heavily enough against a moderate total score. I started documenting the repositioning technique explicitly and switched to a draw sheet with a lift protocol. The injury stabilized and no new ones developed. The Braden score stayed the same. The intervention changed because I looked past the number.
Get the Full Details
Practical Workflow for Running Through This Quickly and Correctly
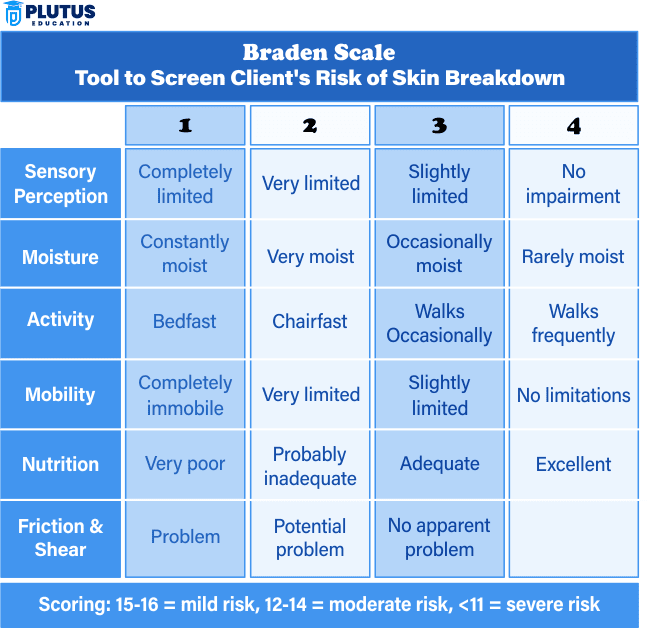
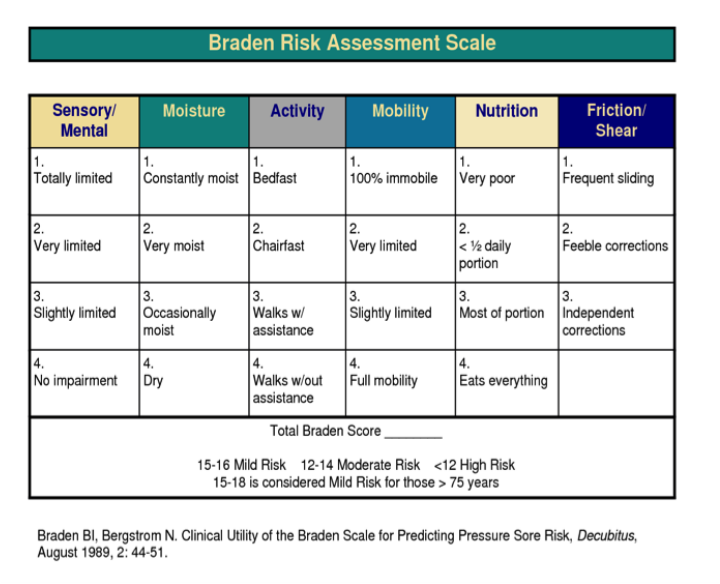
The most efficient way to complete the assessment without cutting corners is to observe the patient for a full cycle of their routine before filling out any numbers. Walk them through what you expect to see: can they change position without help, does their skin stay dry for at least two hours, how far do they walk in a typical shift, what is their oral intake pattern. Then assign the scores. This usually takes about five to seven minutes the first time you do it thoroughly, and drops to two or three minutes after you have the habit locked in. Reassess the Braden Scale Assessment Tool score within 24 hours of admission and then at least weekly, or sooner if the patient's clinical status changes. A patient who goes from walking to bedbound after surgery needs a reassessment the same day, not the next scheduled week. The score can shift dramatically in that window and staying with an outdated number creates a false sense of security. I keep a running log on my assessment sheet so I can track the trajectory instead of staring at a single snapshot. The total score bands break down as follows. A score from 19 to 23 indicates minimal risk. Most ambulatory outpatients land here. Scores from 15 to 18 are low risk, which covers patients who are mostly mobile but may have minor moisture or nutrition concerns. The 13 to 14 range signals moderate risk and is where most medically complex inpatients sit. Scores of 10 to 12 place the patient in high risk territory, typically involving limited mobility plus moisture and sensory deficits. Anything at or below 9 is very high risk and usually requires an immediate bundle of preventive interventions beyond standard turning schedules.
Scoring each domain consistently requires attention to the anchors provided in the scale manual. Mobility ranges from completely immobile at 1 to occasionally walks at 4. Sensory perception goes from completely limited at 1 to not impaired at 4. Moisture runs from rarely moist at 1 to constantly moist at 4. Activity spans bedfast at 1 to walks frequently at 4. Nutrition moves from very poor at 1 to excellent at 4. Friction and shear go from problem present at 1 to no apparent problem at 3. Matching clinical presentation to these anchors correctly is what separates an accurate assessment from a box-checking exercise. There is no downloadable version of the scale that is officially endorsed by the original publishers that requires a purchase or license in most clinical settings. Most hospitals include the form in their electronic health record assessment templates, which auto-calculates the total and triggers alerts when scores fall below certain thresholds. If your facility does not have this built in, the standard paper version circulates freely in nursing supply rooms and is available through most hospital intranets. I prefer the paper form during the initial assessment because it forces you to slow down and look at each domain individually rather than clicking through a digital template that might blur the distinctions between categories. The main limitation I want to stress is that the Braden Scale is a screening tool, not a diagnostic one. A low score predicts risk but does not identify existing wounds. A patient can score in the moderate risk range and already have a Stage 1 injury on the greater trochanter that you missed because you were focused on the number instead of the skin. I make it a rule to complete a full skin inspection before or simultaneously with the Braden scoring. The inspection takes two to three additional minutes and catches problems the scale itself will never show you.
Using the tool well comes down to treating it as one input among several, not the final answer. Combine it with vascular checks, nutrition labs, skin assessments, and actual observation of movement patterns. The number itself is easy to get. Getting the right number and acting on it correctly is what separates competent nursing from thorough nursing.