How the Braden Scale Actually Works in a Real Ward
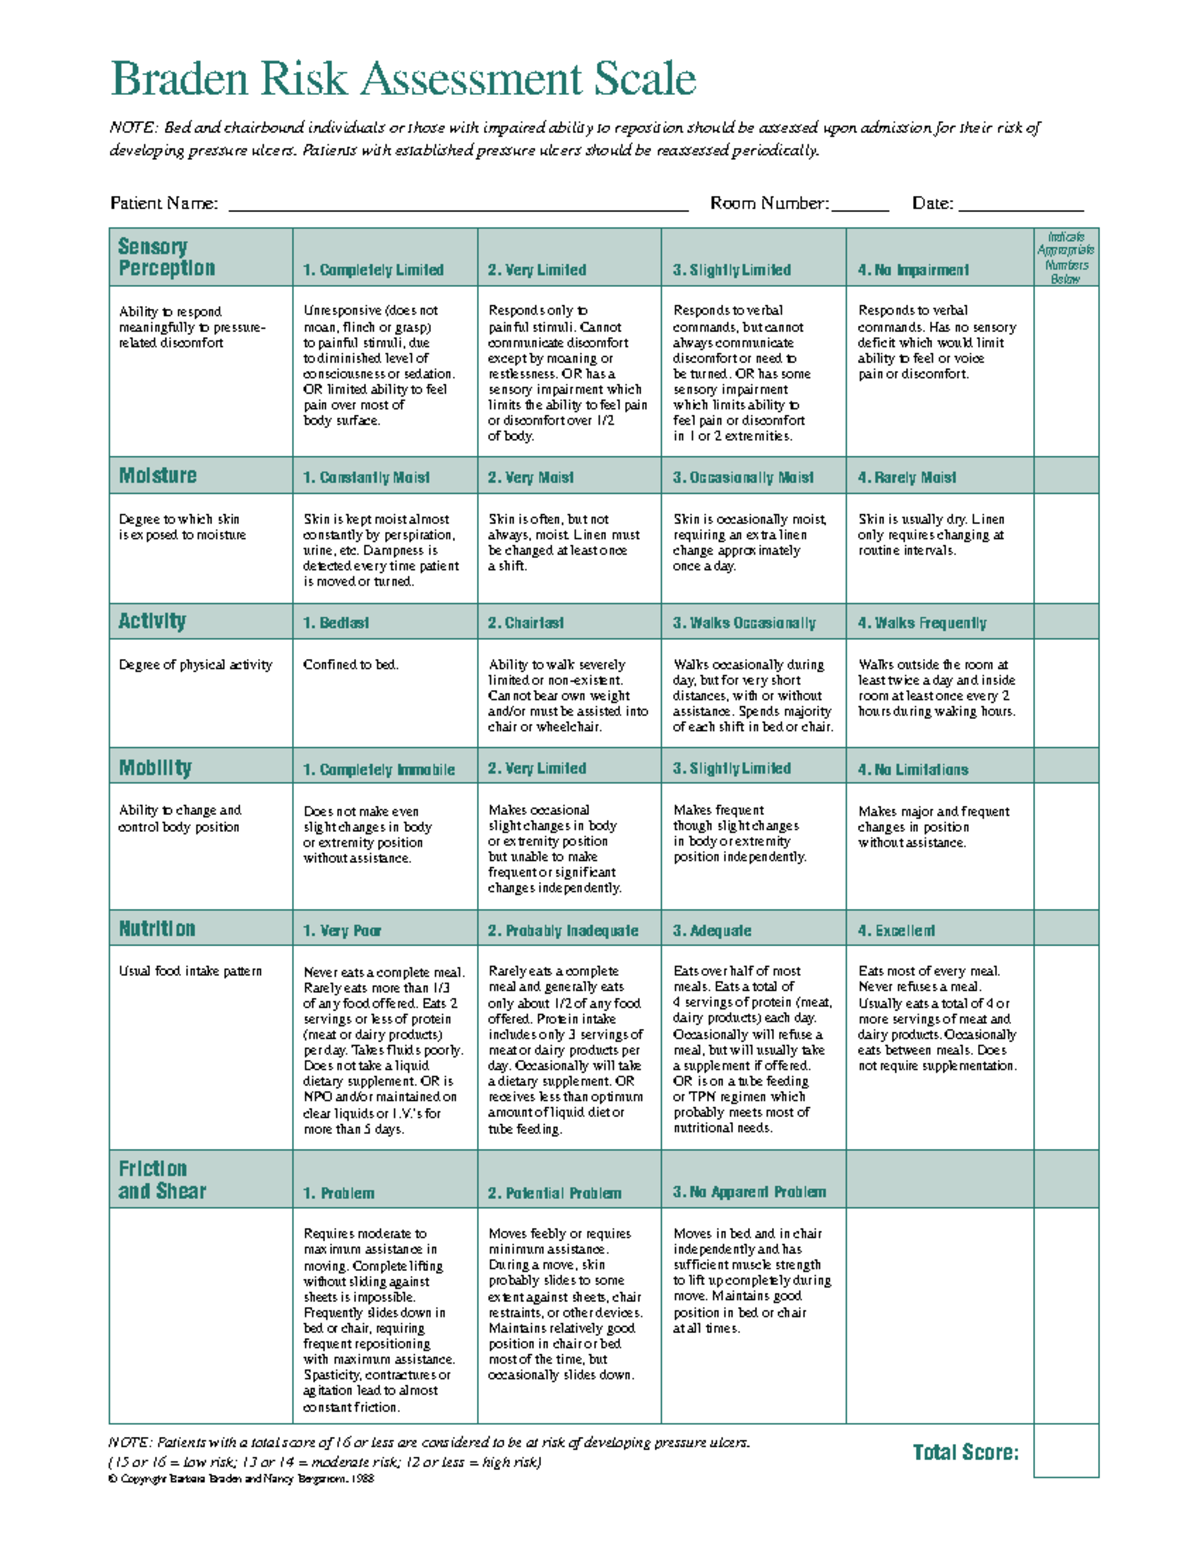
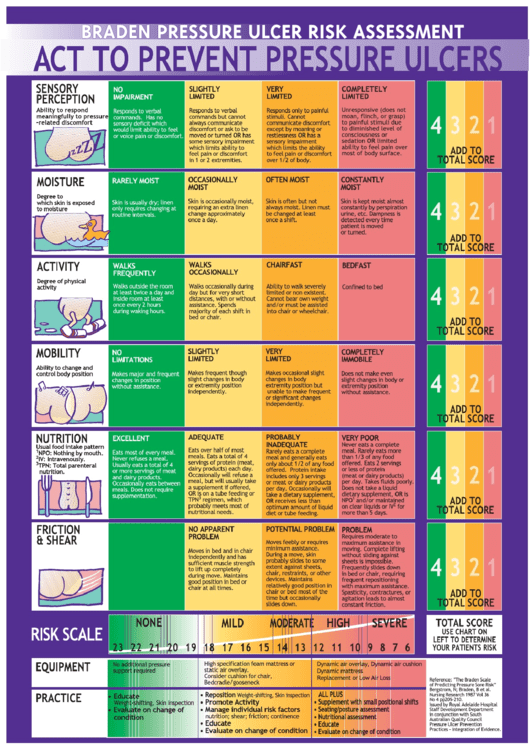
Most people learning this scale think it's about plugging in numbers and getting a risk score at the end. That's technically true, but it misses the part that actually matters: the consistency of your assessments across shifts. I once saw a nurse assign a mobility score of 2 to a patient on day one, then score that same patient a 3 on day three because he sat up for thirty minutes during therapy. Those two numbers aren't different enough to change his risk category, but they create a paperwork trail that looks like he's improving when he's not. Stick to consistent criteria every single time. The scale looks at six domains. Each one gets scored from 1 to 4, with 1 being the worst possible score for that category. You add them all together for a total between 6 and 23. A score of 19 or higher means low risk. 15 to 18 is moderate risk. 13 to 14 is high risk. And anything 12 or below is severely high risk. The lower the number, the worse the patient's prognosis for developing a pressure injury. Sensory Perception - This measures how well the patient can respond to discomfort related to pressure. A score of 1 means completely limited. The patient doesn't feel pressure at all, maybe due to spinal cord injury or heavy sedation. A score of 4 means no impairment. The patient grimaces or shifts position when pressure builds. The tricky middle ground is a score of 2, which means significantly limited. The patient responds only to painful stimuli, not to routine pressure discomfort. I've seen people misclassify this because the patient flinches when you press their sternum with your knuckle, which isn't the same as sensing the pressure of a bed surface over hours.
Mobility - This is about how well the patient can change and control their body position. Score of 1 is bedfast. Score of 4 is fully mobile, meaning they change positions frequently and independently. The most common error here involves patients who can move in bed but refuse to turn because of pain or stubbornness. They aren't bedfast by medical definition, but functionally they stay in one position for long stretches. I score them a 2 in that case, not a 3, because the end result is the same regardless of whether the cause is physical inability or behavioral resistance. Activity - This tracks how often the patient walks. The options range from bedfast to walking daily. Don't conflate this with mobility. Mobility is about repositioning. Activity is about ambulation. A patient who can shift side to side in bed but never leaves it would get a 3 for mobility and a 1 for activity. Moisture - This is perhaps the most misunderstood domain. It's specifically about skin exposure to moisture from sweat, urine, or wound drainage. Score of 1 is constantly moist. The skin is damp almost all the time. Score of 4 is rarely moist. The common pitfall is counting occasional incontinence episodes as "sometimes" moist when the skin has time to dry between episodes. I once had a patient with a urinary catheter who leaked around the balloon every few hours. His skin stayed dry most of the shift because we changed the drainage bag promptly. He got a 3, not a 2, and that single point kept his overall score out of the high-risk category. Whether that was correct clinically is debatable, but it shows how much the granularity of each subscale matters.
Nutrition - This assesses usual food intake. A score of 1 means the patient eats almost nothing. A score of 4 means the patient eats a full diet. The catch is that many patients who say they eat well still have poor protein intake because their meals are mostly carbohydrates. If you're doing nutrition assessment properly, you should already be pulling dietary records. Don't ask the patient what they think they eat. Look at the actual charted intake over 72 hours. Skin Condition - Score of 1 means the skin is impaired. There are existing pressure injuries, breakdown, or chronic conditions that compromise skin integrity. Score of 4 means the skin is never likely to become overly moist and appears intact. I've seen this one misapplied to patients with fragile, thin skin from long-term steroid use who don't yet have visible breakdown. Their skin is impaired in a clinical sense, but the rubric seems aimed at overt damage. In those cases, I tend to score a 3 rather than a 4, because the skin is clearly vulnerable even without an open wound.
Get the Full Details
When the Scale Fails You
The Braden Scale was validated primarily on medical-surgical and intensive care populations. It does not perform well for certain groups. Patients with chronic wounds already present when admission happens will have their scores artificially deflated by the skin condition domain. The scale isn't designed to measure risk for someone who already has a Stage 2 pressure injury on their sacrum. It tells you about future risk, not current status. Performer scale scores are also unreliable for patients with vascular insufficiency or peripheral artery disease. A leg with compromised blood flow will develop tissue damage much faster than the Braden score predicts because the scale doesn't account for perfusion status at all. I've watched patients with a Braden score of 16 develop ulcers within days because the underlying vascular issue wasn't captured by any of the six domains. Another limitation is the moisture domain's dependency on nursing intervention quality. Two nurses assessing the same incontinent patient can arrive at different moisture scores depending on how quickly they change linens between patient contacts. This isn't a flaw in the concept, it's a reliability problem in practice. Standardizing the timing of moisture assessment helps. Doing it immediately after a bowel or bladder episode, before any remedial action, keeps the score consistent.
A Practical Workflow That Takes About Ten Minutes
I assessment takes roughly ten to fifteen minutes if you're thorough. Here's the order I follow to avoid missing anything: Start with nutrition because it requires pulling records rather than observing the patient directly. Check the dietary intake log for the past three days. Note whether supplements are being consumed. This takes about two minutes if the documentation is current. Next, assess sensory perception by testing responsiveness to touch and pressure at bony prominences. Use a light tactile stimulus first, then a deeper pressure stimulus. Watch the patient's facial expression and verbal response. Don't rely solely on the patient telling you they feel something. A sedated patient who occasionally moans when you press their heel is scoring a 2 regardless of whether they claim to feel the touch.
Then evaluate mobility by observing the patient attempt to change position. Some patients look like they can move fine but only manage a partial shift before stopping. Time the repositioning. If they take more than two minutes to roll even a few inches, they're not getting a 4. For activity, ask about ambulation frequency and distance. Cross-reference this with nursing notes from the previous shift. Patients often overestimate their walking when asked directly. Moisture assessment comes next. Examine the skin on the perineal area and any areas prone to sweating. If the patient is incontinent, check the skin after the last documented episode rather than making a guess based on a bowel movement that happened four hours ago.

Finish with skin condition. Perform a full head-to-toe inspection focusing on bony prominences. Document any areas of non-blanchable redness separately from the Braden score. The scale captures current skin integrity, but it doesn't replace a proper skin assessment. I always complete a full skin exam before filling out the Braden form, then use my findings to inform the skin condition score.
Documentation and Frequency
Most facilities require an initial Braden Scale assessment on admission and then every shift or at minimum every eight hours for high-acuity patients. I've worked in places that only required it once daily, which felt insufficient for ICU patients but was the policy. Check your facility's protocol. Some states mandate specific frequencies. When you document, record the individual subscale scores, not just the total. A total of 15 could mean very different things depending on which domains contributed the lowest numbers. A patient scoring 2 on mobility and 2 on nutrition is a different prevention plan than one scoring 2 on sensory perception and 2 on moisture. The total number is useful for tracking trends, but the breakdown drives the clinical interventions.
Where to Get the Official Braden Scale For Pressure Ulcers Form
The tool is in the public domain and widely available. You can find the validated scoring sheet on the Pressure Ulcer Advisory Panel website, or through most hospital supply catalogs. It's also freely downloadable from multiple university nursing departments that host clinical decision support resources. Make sure you're using the original six-domain version, not one of the modified variants that some facilities created internally. Those modifications often strip away important distinctions in the mobility and nutrition categories. I keep a printed copy clipped to the admission folder in my workstation drawer and a digital version in the electronic health record template. Printing one from a random website is tempting, but verify that it matches the published instrument before relying on it for clinical decisions. Minor wording changes in the scoring descriptors can shift how nurses interpret the categories.