Understanding the Braden Scale in Real Clinical Practice
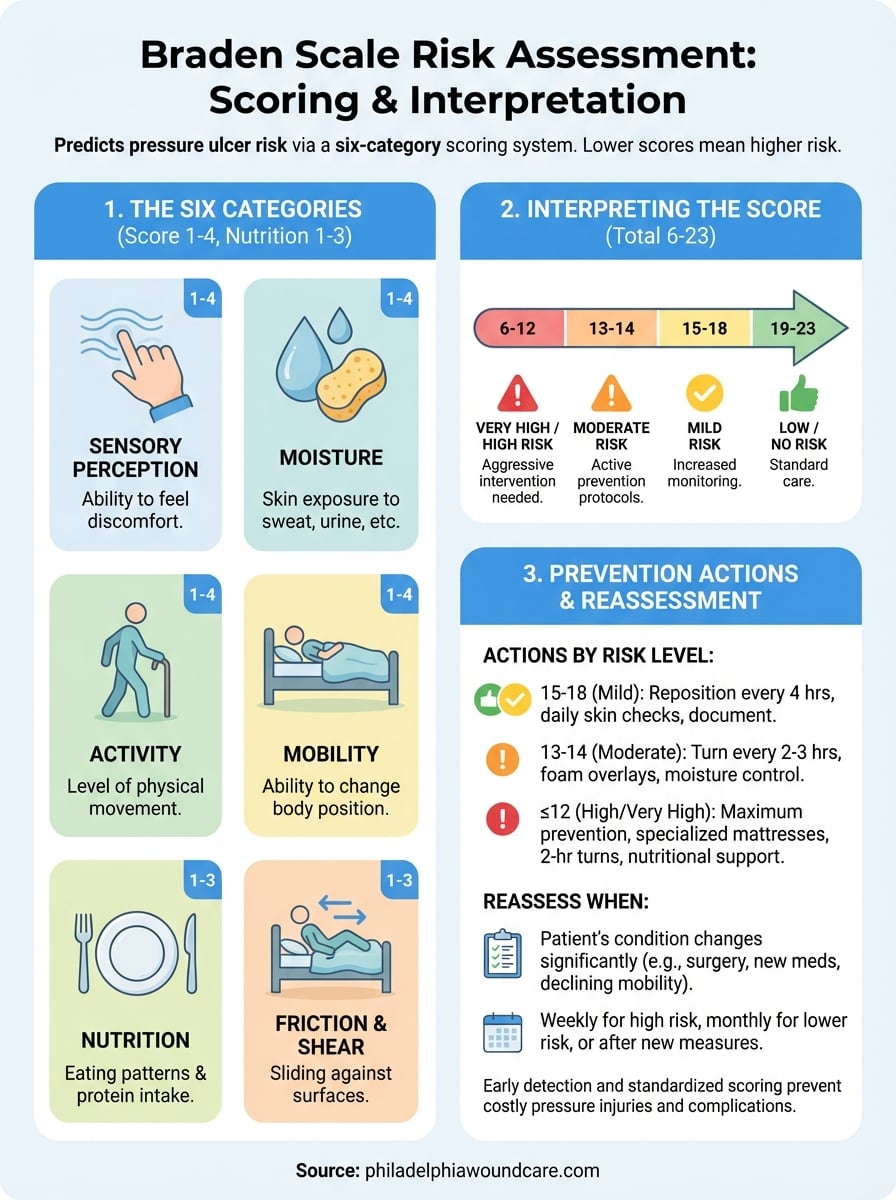
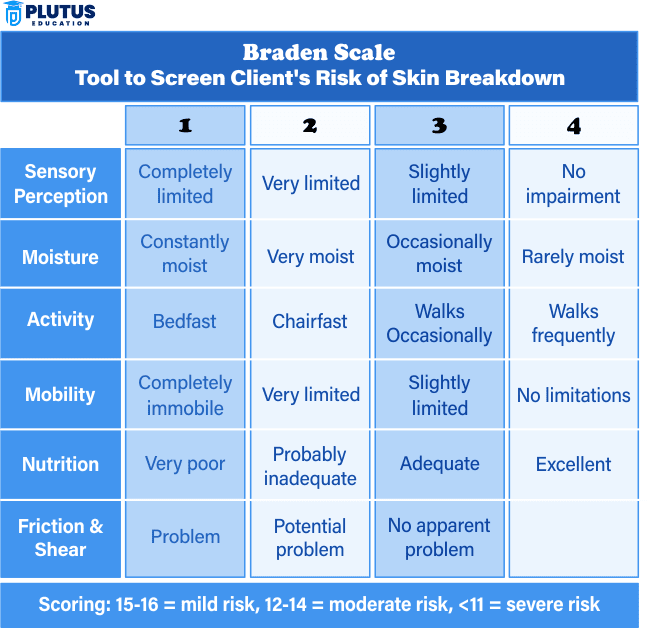
The Braden Scale is a six-domain tool used to assess pressure ulcer risk. It scores mobility, activity, moisture, nutrition, friction, and sensory perception. Each domain gets a point value from one to four, except friction and shear, which are one to three. The total score ranges from six to twenty-three. Lower scores mean higher risk. I have used this instrument across med-surg, long-term care, and wound clinics for over a decade. It is not perfect, but it is the most widely adopted screening tool in hospitals. Here is how it actually works on the floor.
How to Calculate the Braden Scale For Skin Assessment
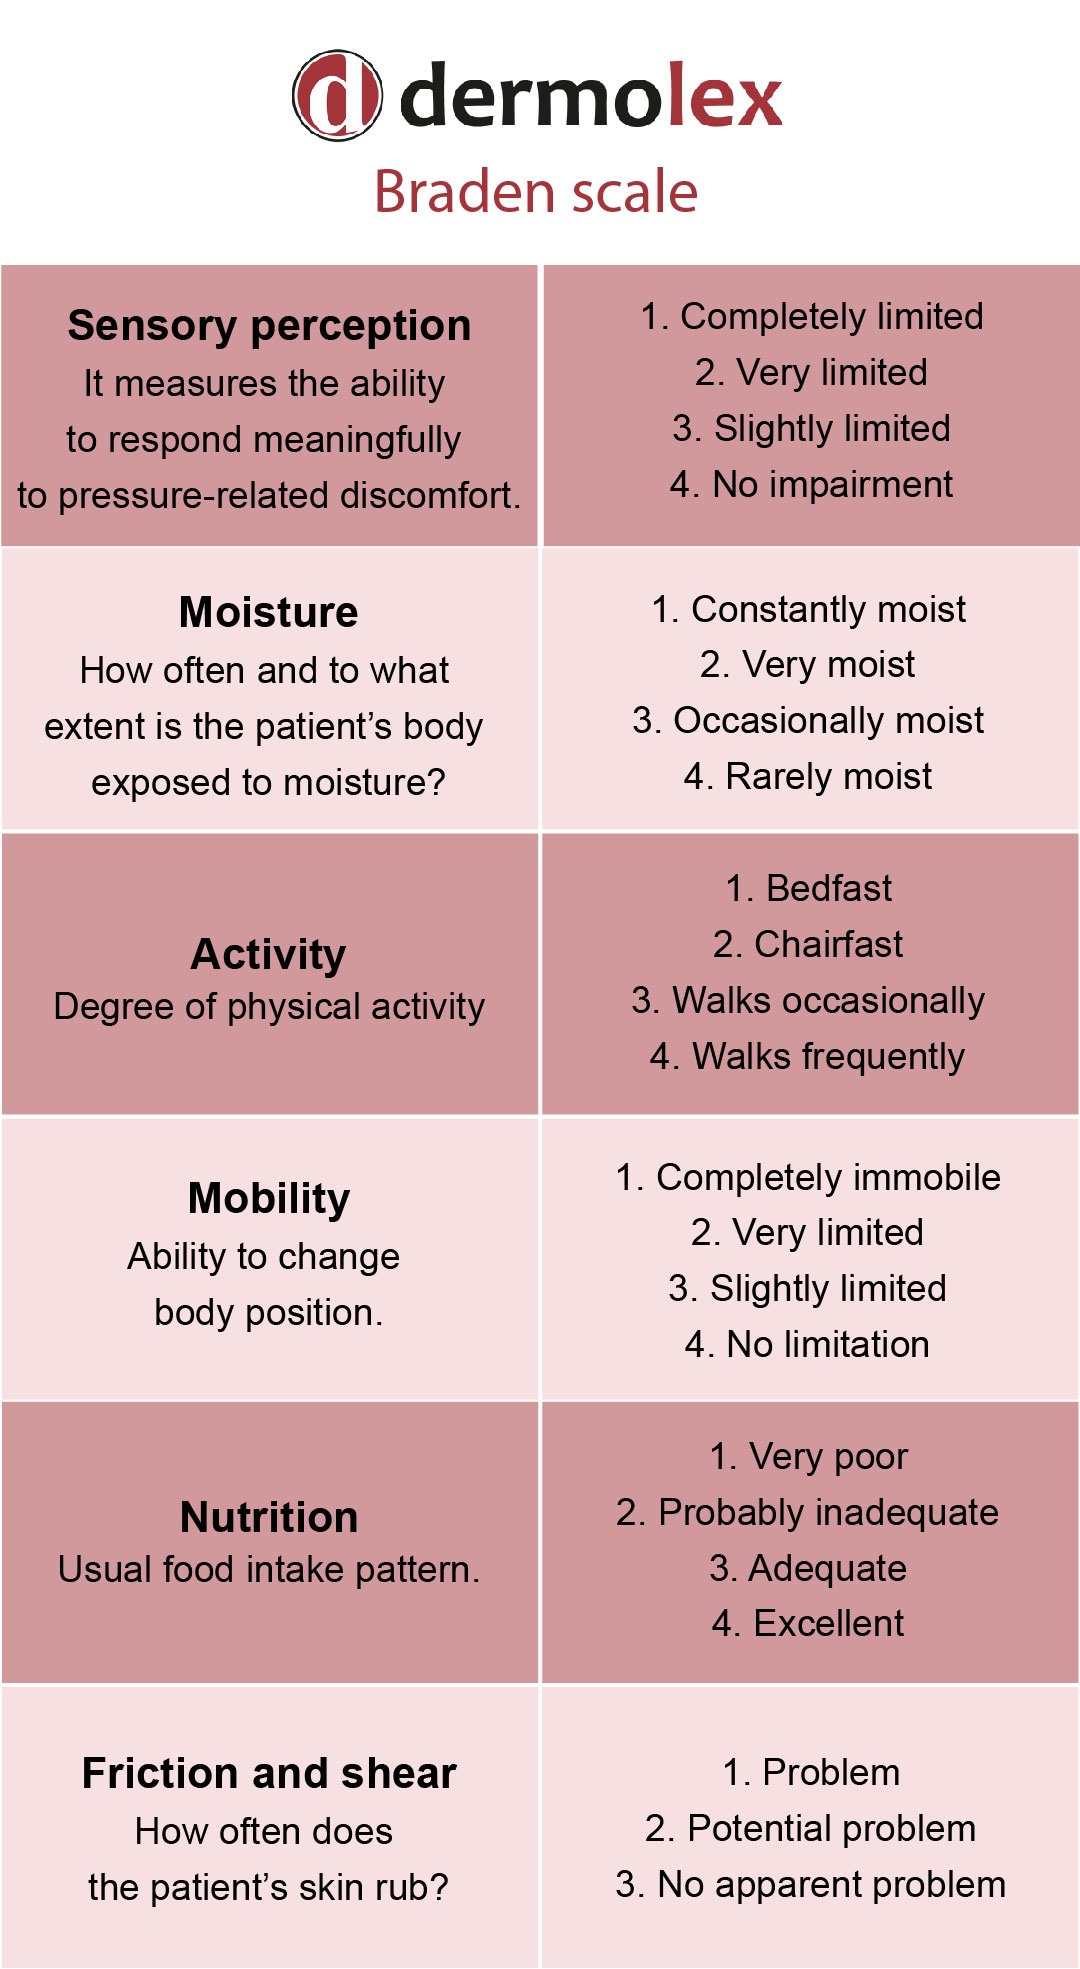
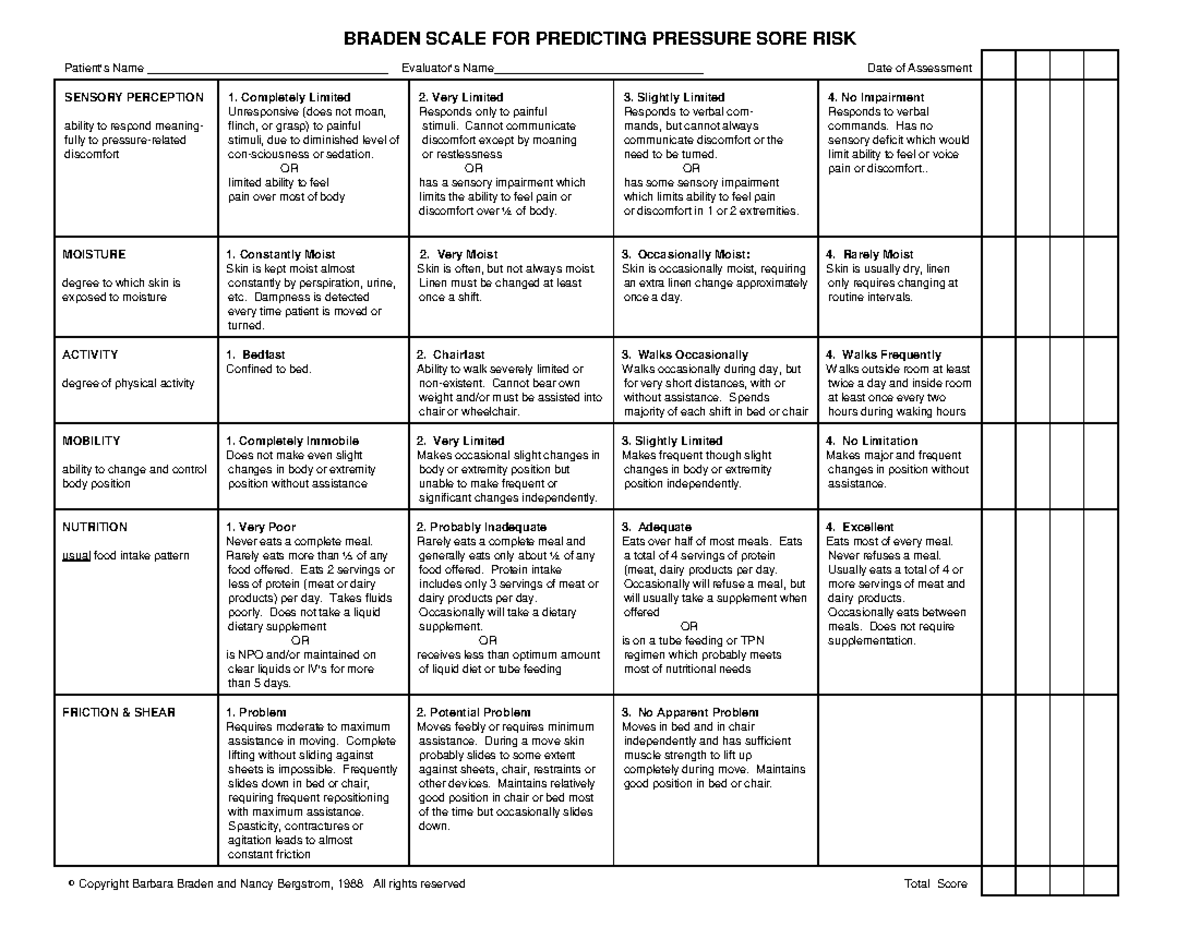
Start with mobility. One means completely immobile. Two means bedfast but unable to change position independently. Three means able to walk indoors occasionally. Four means walks frequently outside the room. This is where most nurses rush. A patient who uses a wheelchair in the hallway should not automatically score a four. Check whether they are actually bearing weight or just being pushed around. Activity level follows. One is bedfast. Two is chairfast. Three is occasional walker. Four walks frequently. Do not confuse mobility and activity. They measure different things. Mobility is ability to move. Activity is frequency of movement throughout the day. Moisture scores reflect skin exposure to wetness. Occasionally moist means the patient sweats a little or has light incontinence. Frequently moist means skin is damp most of the time. Constantly moist means the patient is incontinent of urine and stool with no recovery period. I once scored a patient a two for moisture because she had a urostomy and was continent of stool. She still had frequent urinary leakage onto her skin. That should have been a three. I caught it on the reassessment and corrected it.
Nutrition intake is often the hardest domain to score accurately. Rarely consumes means less than half of recommended calories. Poorly consumes means less than a third. Adequately consumes means eats most meals. I have seen dietitians chart adequate intake while the patient leaves two-thirds of every tray untouched. Verify with the patient at mealtimes instead of relying solely on dietitian notes. This alone changed my accuracy rate significantly. Friction and shear get a one to three range. No issues means the patient moves independently without drag. Potential problem means the patient slides down in bed or chair and needs assistance to reposition. Actual problem means the patient is largely immobile and drags against sheets. The scale here is intentionally subjective. You will learn to recognize the difference between a patient who scoots independently and one who just lies there while you pull them up. Sensory perception measures awareness of pressure-related discomfort. Completely limited means the patient cannot feel discomfort at all. Very limited means they respond to pressure but not to pain. Slightly limited means they respond verbally to discomfort. No impairment means they feel pain and can communicate it. A diabetic neuropathy patient who cannot feel a bump in their shoe is a classic example of a score that matters.
Get the Full Details
Common Pitfalls I See Repeatedly
The biggest mistake is treating the Braden Scale as a one-time assessment. It should be done on admission, then repeated at least weekly, or more often if the patient condition changes. A patient admitted with a score of fourteen can drop to eight within forty-eight hours after surgery. That shift matters. I stopped skipping reassessments after a stage four ulcer developed on a patient I had not reassessed in nine days. Another error is anchoring bias. Once you write a score, you tend to reuse it. I have caught myself copying yesterday's activity score instead of observing the patient for thirty minutes first. If you want accuracy, actually watch the patient move. Sit with them at breakfast. Follow them to physical therapy once. Then score. A third issue is the friction and shear domain. It is vague by design. Different nurses interpret it differently. On my unit we created a quick reference card showing photos of a patient dragging on linens versus one who repositions independently. Inter-rater reliability improved noticeably after that.
What the Scale Does Not Capture Well
The Braden Scale does not account for hemodynamic instability. A patient in septic shock with poor perfusion may have a deceptively high score because they are technically mobile but their tissue tolerance is compromised. In those cases, consider adding a perfusion or oxygenation risk note. It also underestimates risk in patients with vascular disease. Peripheral arterial disease or diabetes with microvascular complications can cause tissue breakdown at scores that would otherwise read moderate or low. I always cross-reference the Braden score with an ankle-brachial index when available. A score of eighteen with an ABI of 0.6 is not a safe score. The nutrition domain is particularly weak. It relies on self-report or brief dietary logs. Albumin and prealbumin levels, when drawn routinely, give you a clearer picture. Combine the Braden nutrition score with lab trends and you get something closer to reality.
Practical Workflow That Cuts Assessment Time
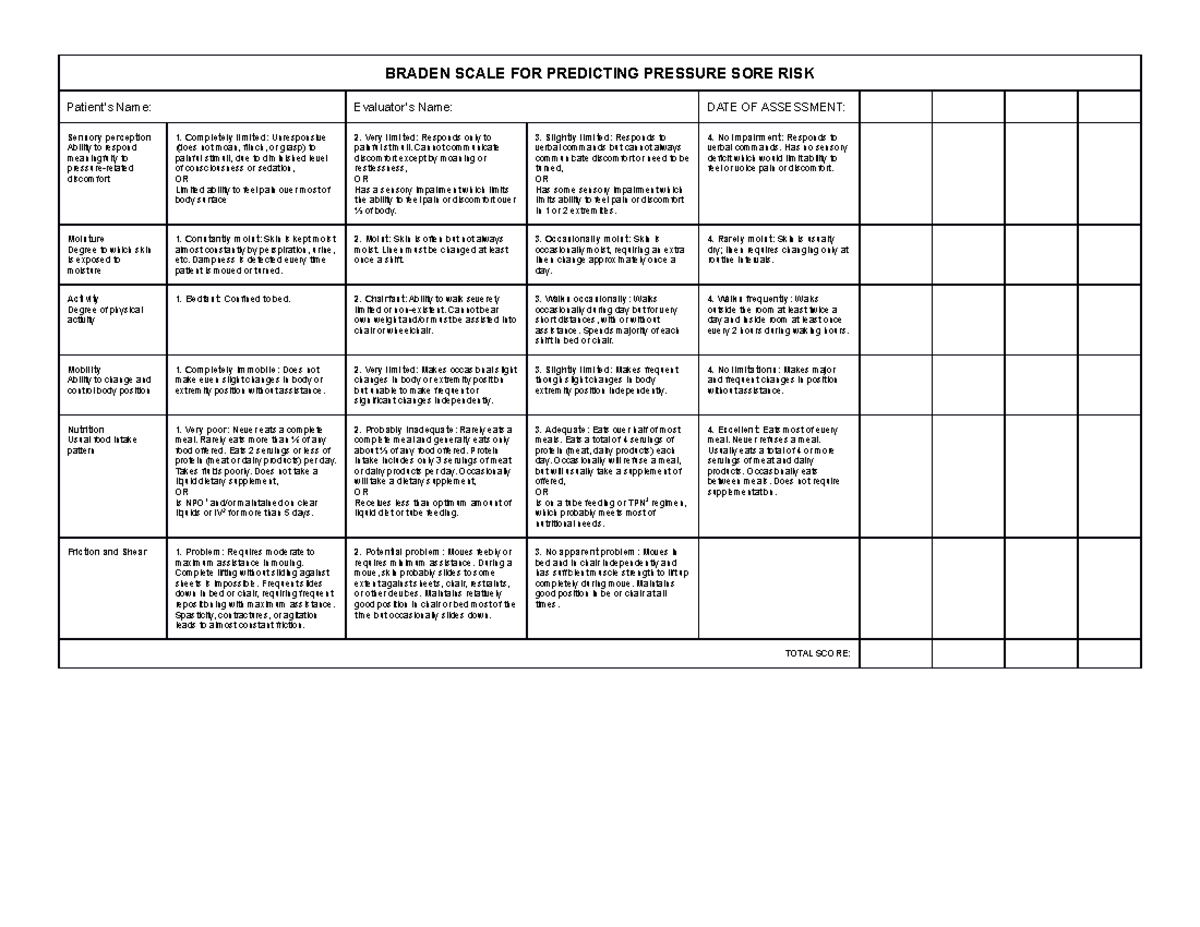
Doing this right takes about twelve minutes if you are organized. I have a pocket-sized scoring sheet clipped to my patient assignment folder. I fill it during my first assessment pass. I do not go back and forth between rooms rechecking domains. I observe each domain sequentially and record it immediately. By the time I finish ten patients, I have solid data without rushing. For electronic health record systems, most platforms include the Braden Scale as a built-in assessment tool. Use the template. The system will flag scores below eighteen automatically. Do not override alerts without a documented reason. If you override, the system should require a clinical note explaining why. I rarely override now. When I do, it is usually because a domain score does not reflect the current status and I need to update it rather than ignore it.
Where to Get the Scale and Scoring Forms
The original Braden Scale was published by Barbara Braden and Nancy Bergstrom. Their work is in the public domain for clinical use. You can find the official scoring sheet on the Braden Q website, which is maintained by the original developers. Many hospital supply catalogs also stock printed versions. I keep a small pad on my clip and use them when the electronic system is down or when I need a quick reference during bedside teaching. For educators, the National Pressure Ulcer Advisory Panel offers training modules that include case studies with Braden Scale application. Those materials are useful if you are preparing staff or studying for certification exams.
When to Use Something Else Instead
The Braden Scale is not the only tool. For pediatric patients, use the Braden Q. For ICU patients, some units prefer the Norton Scale or a combination tool that includes perfusion metrics. If your facility deals with a high volume of wound care, adding a skin integrity checklist alongside the Braden Scale improves detection. I started using a simple skin inspection form for every high-risk patient. It has caught early blanching erythema that the Braden score alone missed. The real value of any assessment tool is not the number it produces. It is what you do with that number. A score tells you risk. It does not tell you how to prevent ulcers. The prevention plan is where the actual work happens. Use the scale as a starting point, not an endpoint.
What Matters After You Score
Score a fourteen and you begin repositioning protocols and pressure-redistributing surfaces. Score below thirteen and you escalate to more aggressive preventive measures. Document everything. The score is a snapshot. The interventions are what protect the patient. That distinction separates competent assessment from performative documentation. I have lost track of how many times a well-scored Braden assessment prevented a pressure injury in my unit. The numbers are not tracked separately, but the trend is visible. Patients who receive consistent pressure relief plans based on accurate scores heal better and stay out of the wound clinic longer. That is the practical outcome. Everything else is just paperwork.