Getting Oriented in Axial Brain Slices
Most people looking at brain anatomy cross section images for the first time get lost within the first five minutes. The gyri and sulci look like an unreadable topographic map, and distinguishing structures that are roughly the same brightness on a standard CT scan is almost impossible without knowing exactly what to look for. I spent about three months watching people try to navigate these slices during residency prep sessions, and the same mistakes came up every single time. They started by trying to memorize everything rather than learning the orientation landmarks first. The way I approach any new slice is to find the midline. Not the skull margin, not the falx cerebri — I'm talking about the interhemispheric fissure, the actual gap between the two cerebral hemispheres. Once you lock onto that, everything else falls into roughly the right place. The lateral ventricles sit just lateral to it, the thalamus is posterior and deep, and you work outward from there. It's not elegant, but it cuts the initial orientation time down from maybe twenty minutes to around four or five. What nobody tells beginners is that the axial plane is actually the hardest plane to read well unless you already have a solid three-dimensional mental model of the brain. The coronal and sagittal views give you much clearer boundaries between structures because they cut across natural anatomical divisions. On axial, the basal ganglia and thalamus are stacked directly on top of each other in the same slice, which means you're essentially interpreting a shadow map rather than a clean dissection. I had a colleague who could read coronal T1 weighted MRIs blindfolded after a year and still struggled with axial slices months later.
Brain Anatomy Cross Section: Landmark Progression
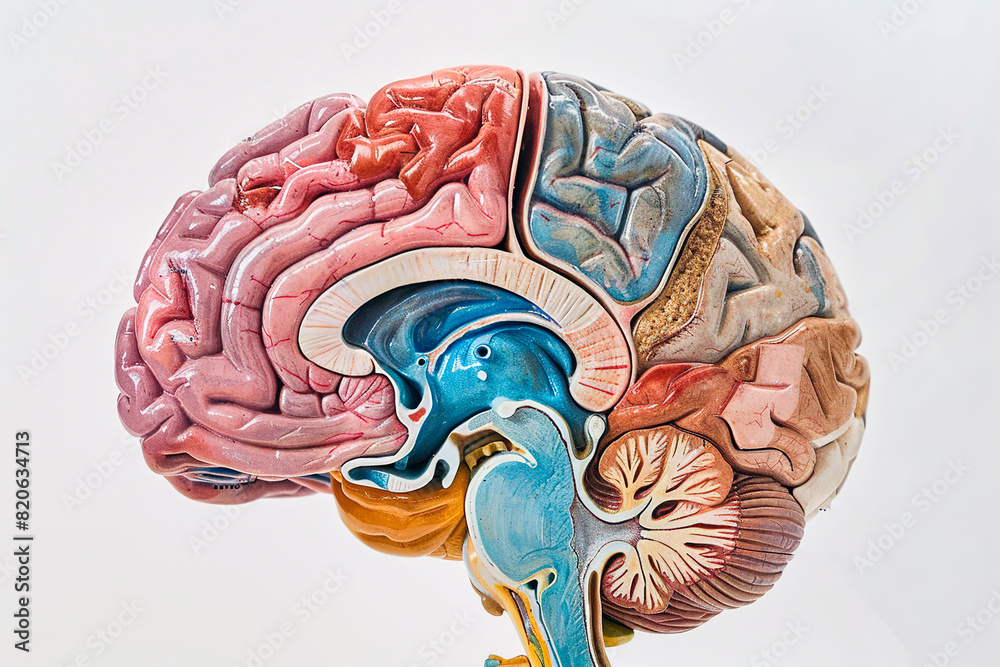
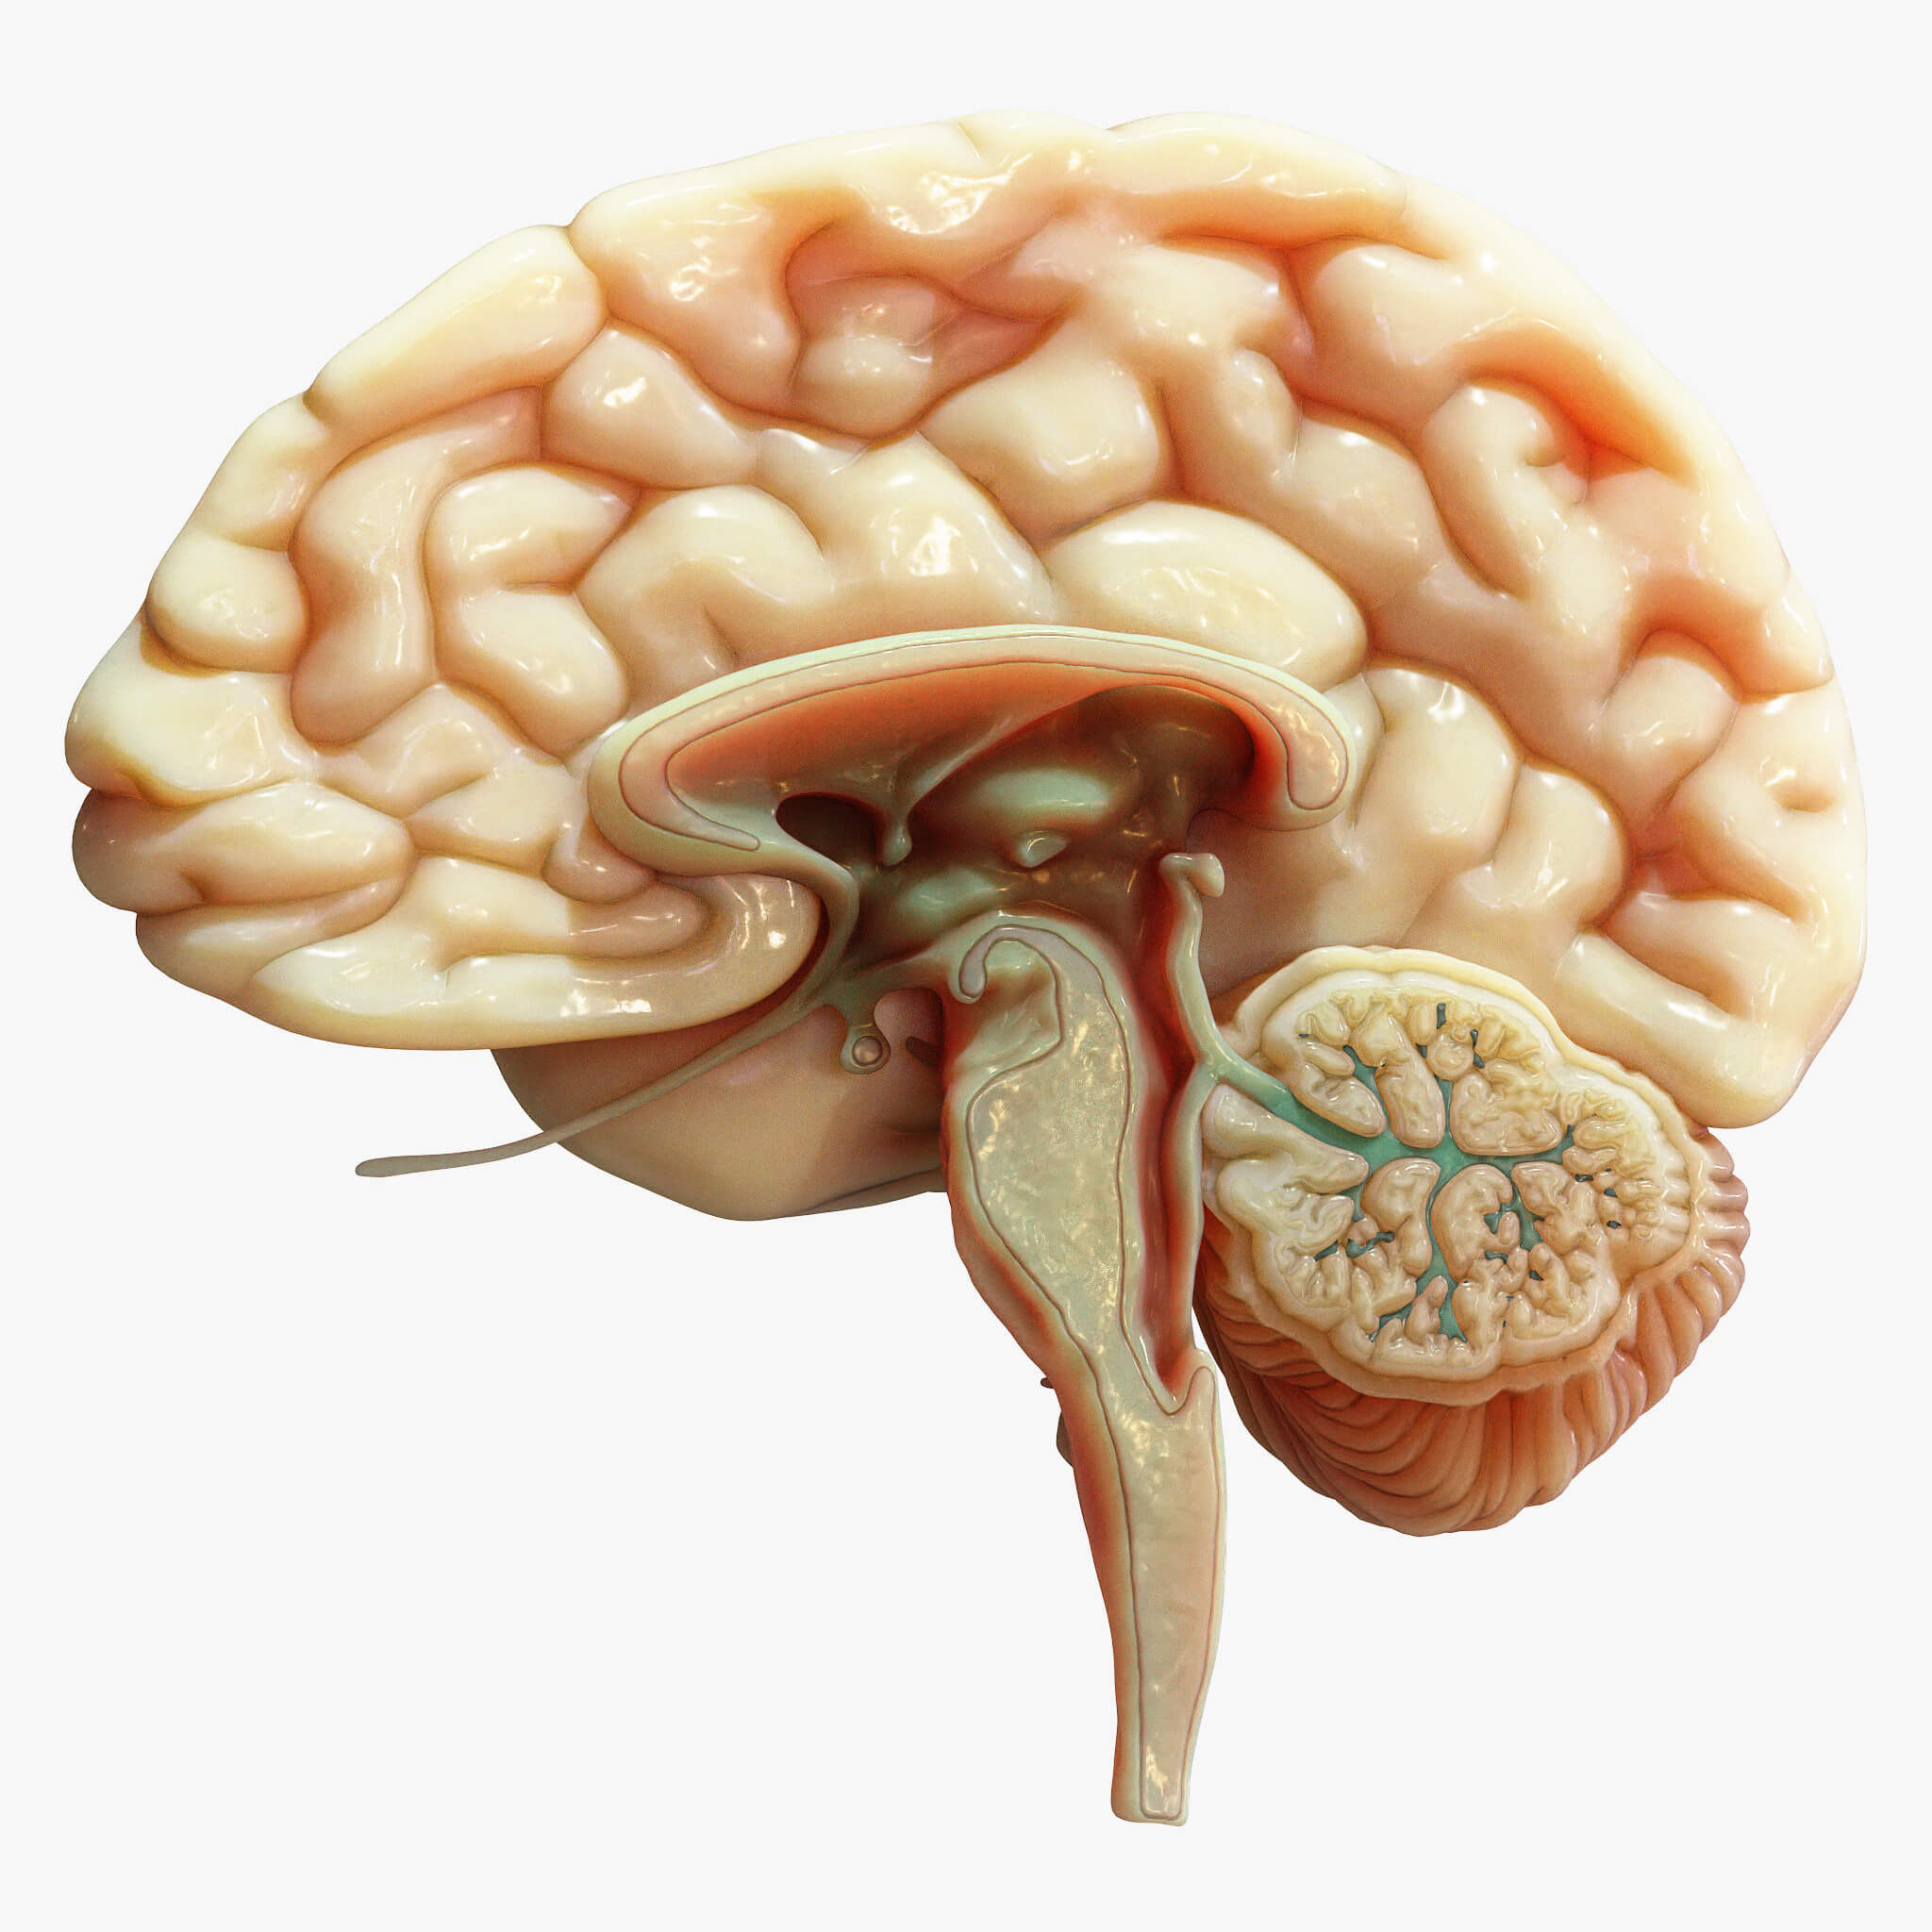
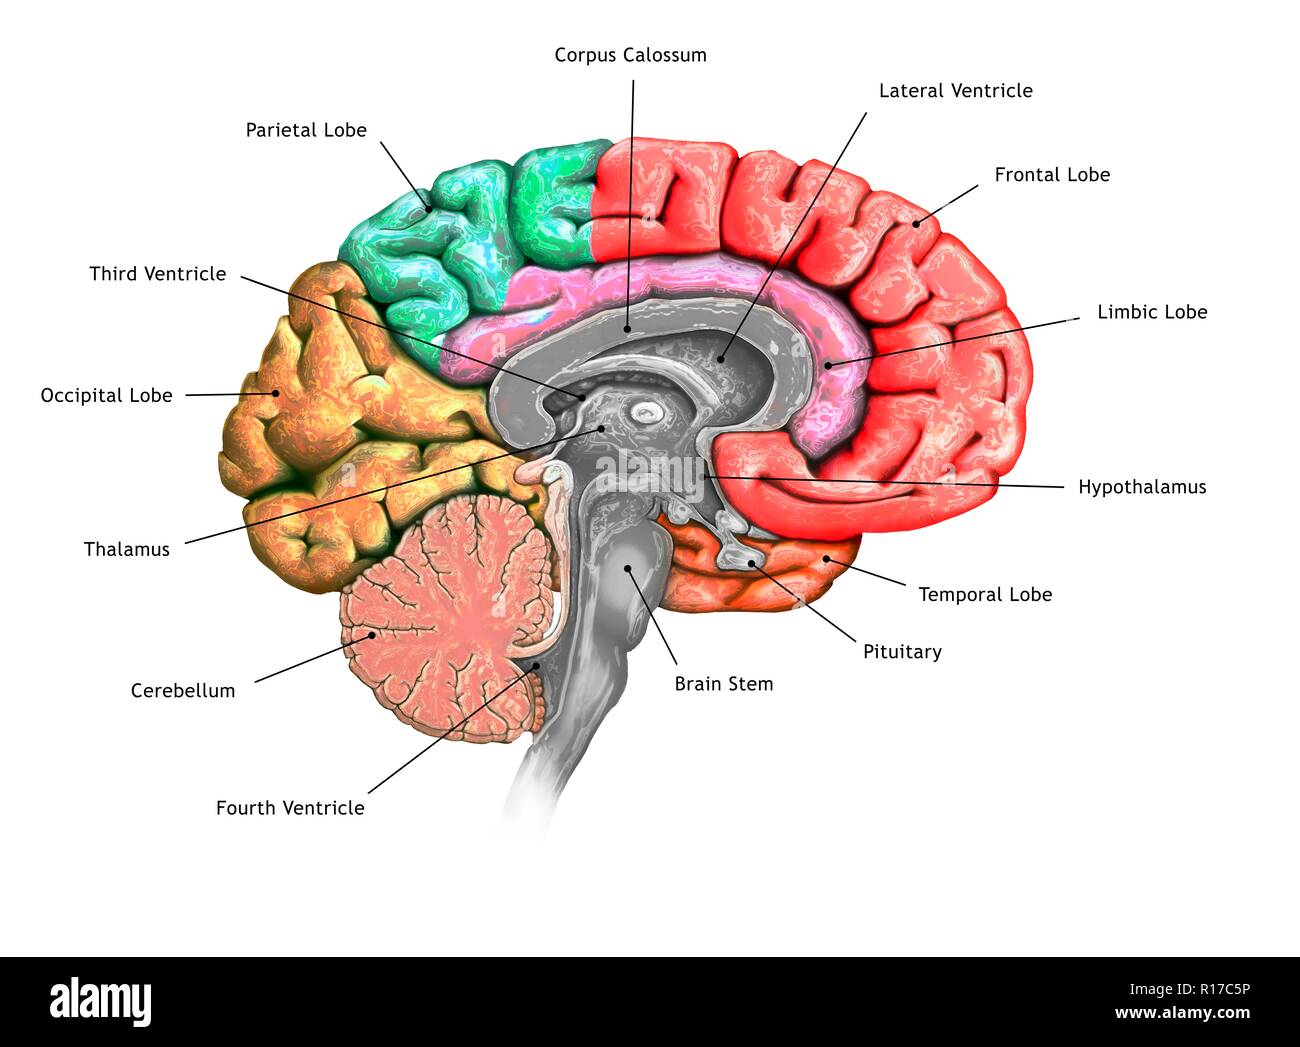
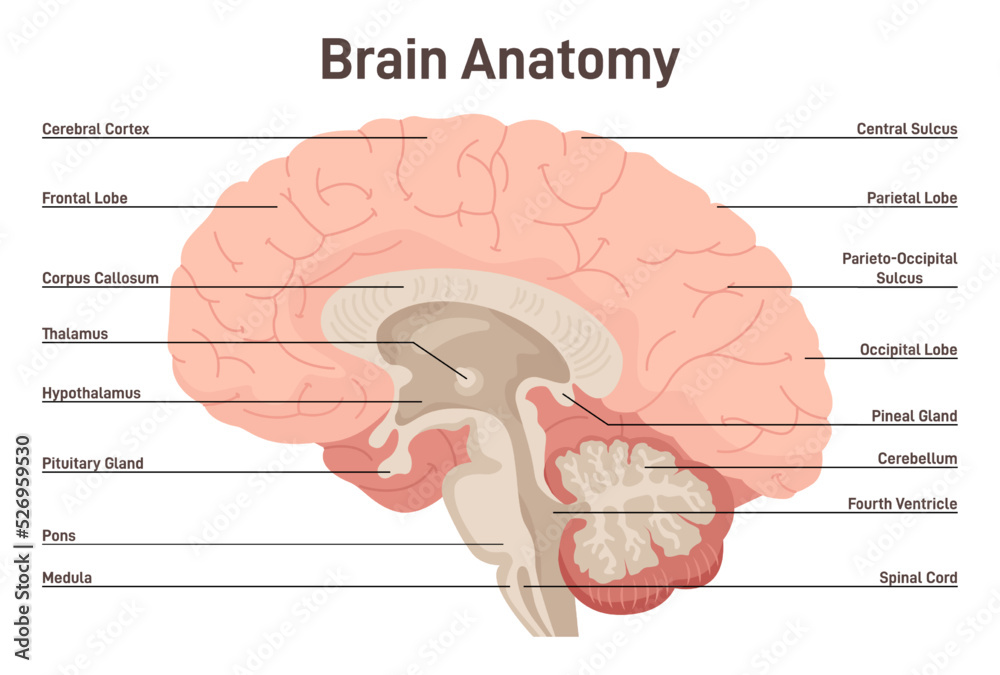
Start at the vertex and work downward. The highest axial slice you'll commonly use as a teaching reference shows only the superior frontal gyri, the high convexity of the parietal lobes, and the longitudinal fissure. Move down one slice and you start seeing the anterior horns of the lateral ventricles — those dark CSF-filled spaces should be roughly symmetric. Asymmetry here is your first red flag, whether it's a mass effect pushing things off midline or atrophy from something like alcohol use disorder showing up as enlarged ventricles. The next major level down is where the caudate nucleus heads become visible flanking the lateral ventricles, and the lentiform nucleus starts to appear lateral to them. This is the basal ganglia level, and it's also where the internal capsule becomes important. The genu of the internal capsule separates the caudate head from the putamen, and the posterior limb runs between the thalamus and the globus pallidus. If you're reading imaging for a stroke, this is the territory you're checking for early ischemic changes on CT — loss of the gray-white differentiation in the internal capsule is an early sign that you don't want to miss. Going further down, the third ventricle appears between the two thalami. The pineal gland sits just posterior to the third ventricle at this level, and it's a useful midline landmark. Past this point you're entering the posterior fossa region, and suddenly the brainstem takes over as the central structure with the cerebellum draped behind it. The fourth ventricle is diamond-shaped and sits between the pons anteriorly and the cerebellum posteriorly. Mistaking the fourth ventricle for the cerebral aqueduct is a common error — the aqueduct is a tiny slit-like channel that sits just anterior to the third ventricle, not the fourth.
Practical Workflows for Reading These Images
When I'm actually working through a series of axial brain slices, I don't go slice by slice from top to bottom. That's slow and you lose the big picture. Instead, I do a sweep at the level of the lateral ventricles first to check for symmetry, then jump to the basal ganglia level to confirm the caudate and lentiform nuclei, then drop to the thalamic level, and finally check the posterior fossa. This hits the clinically relevant structures in about ninety seconds on a normal study. A full systematic top-to-bottom read takes closer to three minutes and mostly catches things you'd see on the quick sweep anyway. The real problem comes when you're dealing with contrast-enhanced studies or MRI sequences where the signal intensities are different from what you're used to. I ran into this specific issue about two years ago when I was reviewing a series of FLAIR images for a migraine workup. The periventricular white matter hyperintensities were making the lateral ventricles look smaller than they actually were, and I initially underestimated the degree of ventricular asymmetry. What I ended up doing was switching to the corresponding T2 sequence to verify the ventricle sizes, then going back to the FLAIR with that reference point. It added maybe two minutes to the read but prevented a misinterpretation that could have sent the patient for an unnecessary lumbar puncture. CT and MRI are not interchangeable when it comes to axial brain anatomy. CT shows bone beautifully, which is useful for trauma cases where you're looking for skull fractures alongside intracranial hemorrhage. But CT has almost no soft tissue contrast compared to MRI. The gray-white differentiation that's reasonably clear on CT is nearly invisible on non-contrast studies in patients over sixty who have age-related white matter changes. If you're reading CTs on older patients and struggling to see the internal capsule boundaries, switch to MRI if it's available, or at minimum lower your confidence in any CT-based structural assessment at that level.
Get the Full Details
Common Pitfalls and Where These Methods Break Down
Axial brain imaging has some fundamental limitations that you need to accept upfront. Artifact from dental fillings is one — it creates streaking that can completely obscure the anterior temporal lobes and the inferior frontal lobes on CT. I've seen cases where a small anterior temporal abscess was missed because the streak artifact from the patient's bridgework made that region uninterpretable. The workaround is ordering a CT with a metal artifact reduction sequence or going straight to MRI if the clinical question involves those regions. Another issue is partial volume averaging, especially at the level of the brainstem and cerebellar vermis. When a structure is smaller than the slice thickness, it gets averaged into the surrounding tissue signal and can disappear entirely. Modern scanners typically use slice thicknesses around 5mm for routine brain CT, which means structures smaller than about 3-4mm in the craniocaudal dimension are unreliable on axial images alone. The basilar artery tip, small pituitary microadenomas, and early demyelinating plaques in the brainstem are all vulnerable to this. You need thinner cuts or a different plane to see them properly. The biggest limitation though is that axial imaging alone will never give you a complete picture of certain pathologies. A meningioma along the falx might look like a vague thickening on axial slices but is dramatically clearer on coronal reconstruction. A posterior fossa lesion can be almost invisible on axial CT because of bone hardening artifacts from the posterior skull base. In practice, most radiologists will look at axial slices first for orientation, then pull up coronal and sagittal reconstructions to confirm anything that's ambiguous. I usually spend about sixty percent of my reading time on axial, twenty-five percent on coronal, and fifteen percent on sagittal. That ratio shifts depending on the clinical question, but it's a reliable starting point.
If you're studying this for an exam or clinical rotation, I'd recommend using a dedicated neuroanatomy atlas app alongside your imaging software. The Netter or Rhoton atlases are fine for gross anatomy, but they don't show you the same structures as they actually appear on axial slices. What looks textbook-perfect in an illustration often appears completely different on a real patient scan due to individual anatomical variation, slice angle, and pathology. I keep a side-by-side reference open while I read and it cuts my uncertainty rate significantly, especially when I'm looking at abnormal studies for the first time.