Understanding the Scoring Process
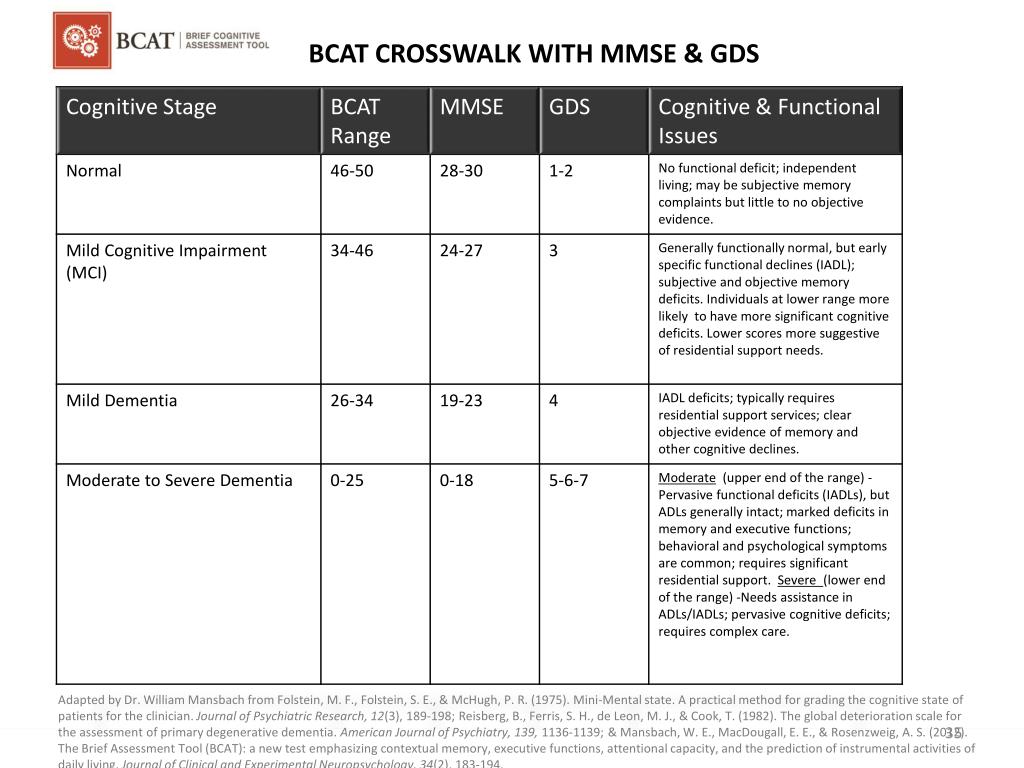
Brief Cognitive Assessment Tool Scoring is where most people get tripped up, and honestly, it's not the calculation itself that's hard — it's knowing which version you're looking at and how the norms are structured. I've seen clinicians mix up the standard score ranges between the 6-item version and the longer 10-item version, then report percentile ranks that don't actually exist in the manual. The tool itself is straightforward, but the documentation around scoring is scattered across different publications, and some of those sources disagree on how to handle partial or missing responses. Here's what it looks like in practice. You administer the cognitive items, record each response as correct or incorrect, then sum the raw score. After that, you convert that raw score into a standardized score using the age-adjusted norm table provided in the manual. The age bands matter more than you'd think — the same raw score can fall into different percentile brackets depending on whether the examinee is in the 60–69 age group or the 70–79 group. Getting that conversion wrong skews the clinical picture immediately.
Why Brief Cognitive Assessment Tool Scoring Is More Tricky Than It Looks
The most common mistake I see is treating every version as interchangeable. The original brief cognitive screener had a maximum raw score of 6, but some clinics extended it to 10 items without realizing that the norm tables don't apply past item 6. When I worked through a case like this, I literally had a raw score of 8 on a 10-item version and was about to convert it using the 6-item norms before catching myself. The workaround was simple — stop and check the instrument's official manual for the exact version being used. There's no universal norm table for modified versions. I flagged it in our clinic notes and referred that patient for a full neuropsychological battery instead, because we had no validated conversion for what we were working with. Another thing people miss is how missing data is supposed to be handled. The guidelines say if a respondent skips an item, you don't simply remove it from the total and divide. The raw score should reflect the maximum possible for the administered version, and missing items are treated as incorrect unless the manual specifies otherwise. This changes the standardized score significantly in borderline cases. A raw score of 4 out of 6 gives a very different normative interpretation than a raw score of 4 out of 5 when you're applying the conversion table. The norm tables themselves are also age-stratified in broad bands, usually ten-year increments. If someone is exactly on a boundary year — say, turning 70 during the assessment period — you use the upper band. Some clinicians round down, which produces a consistently inflated interpretation. It's a small detail, but across a caseload it compounds into systematic misclassification.
Working Through a Score Conversion
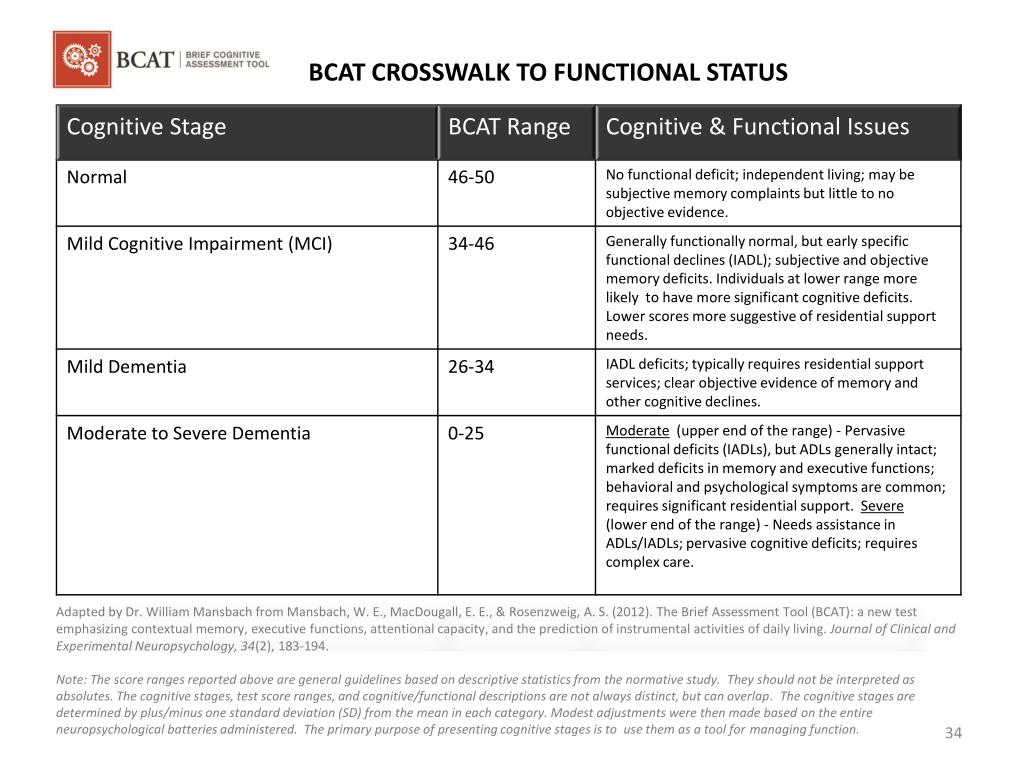
Take a concrete example. A patient scores 5 out of 6 on the standard administration. You pull the norm table for their age group, locate the row for a raw score of 5, and read across to find the corresponding percentile. In the 65–74 age band, a raw score of 5 typically falls around the 60th percentile, which means their performance is within the average range. That's a clean result, but clean results are the easy part. The harder cases come when the score lands in the 20th to 40th percentile range. These borderline scores demand careful consideration of ceiling effects, testing conditions, and the examinee's educational and linguistic background. A person with limited formal education might score in the low-average range on this brief tool without any actual cognitive impairment. The tool was designed as a screening instrument, not a diagnostic one, and the authors are clear about that. What it does well is flag people who need a deeper look. What it doesn't do is tell you why someone scored poorly. I've also encountered situations where motor or visual impairments artificially depress scores. A patient with significant arthritis might have trouble writing the clock-drawing item, not because of cognitive decline but because of physical limitation. In those cases, the scoring sheet sometimes allows the examiner to note the reason for an incorrect response, but that footnote rarely makes it into the final reported score. The numbers don't lie, but they also don't tell the whole story.
Get the Full Details
What the Method Doesn't Cover
The biggest limitation is cultural and linguistic bias. The brief cognitive tools were largely normed on English-speaking, educated populations, and applying those norms to bilingual individuals or people who acquired the test language later in life introduces substantial error. There's no published correction factor for this. If you're working with a population that isn't represented in the norming sample, you need to either use an alternative instrument or clearly state the limitation in your report. Another gap is the floor effect. At the lower end of the score distribution, the tool lacks the sensitivity to distinguish between mild cognitive impairment and moderate impairment. It will catch someone who has a problem, but it won't tell you how bad the problem is. For that, you need a full cognitive battery or at least a more comprehensive screening tool like the MoCA or SLUMS. Speed is where the tool earns its name, but that speed comes at a cost. A full administration and scoring takes roughly 8 to 12 minutes, which is useful in busy clinical settings. But 12 minutes is also enough time to pick up surface-level errors without detecting subtle executive dysfunction. A patient can perform adequately on orientation and recall while still struggling with sequencing, abstraction, and problem-solving — domains this brief tool simply doesn't assess.
If you need a downloadable scoring sheet or norm table, check the official publisher's website for the most current edition. Older versions of the manual have been updated, and the norm data shifted slightly between editions. Using an outdated table is one of those things that looks minor until you realize half your records are built on different standards than your current patients.


