Running a Bruce Protocol properly is harder than most people think
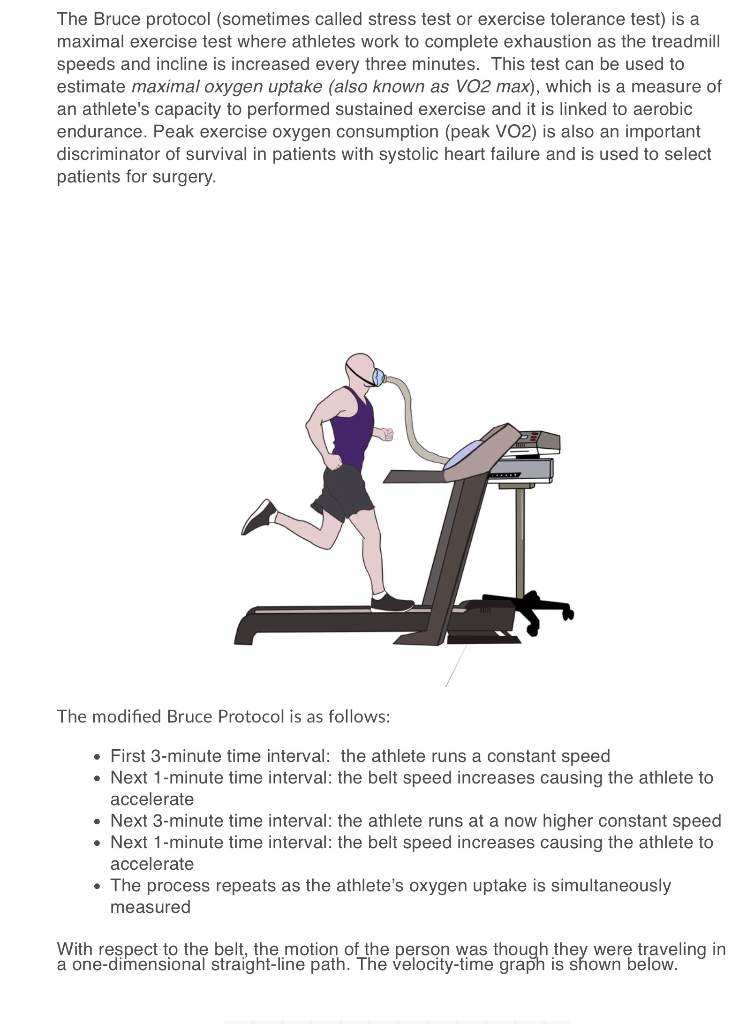
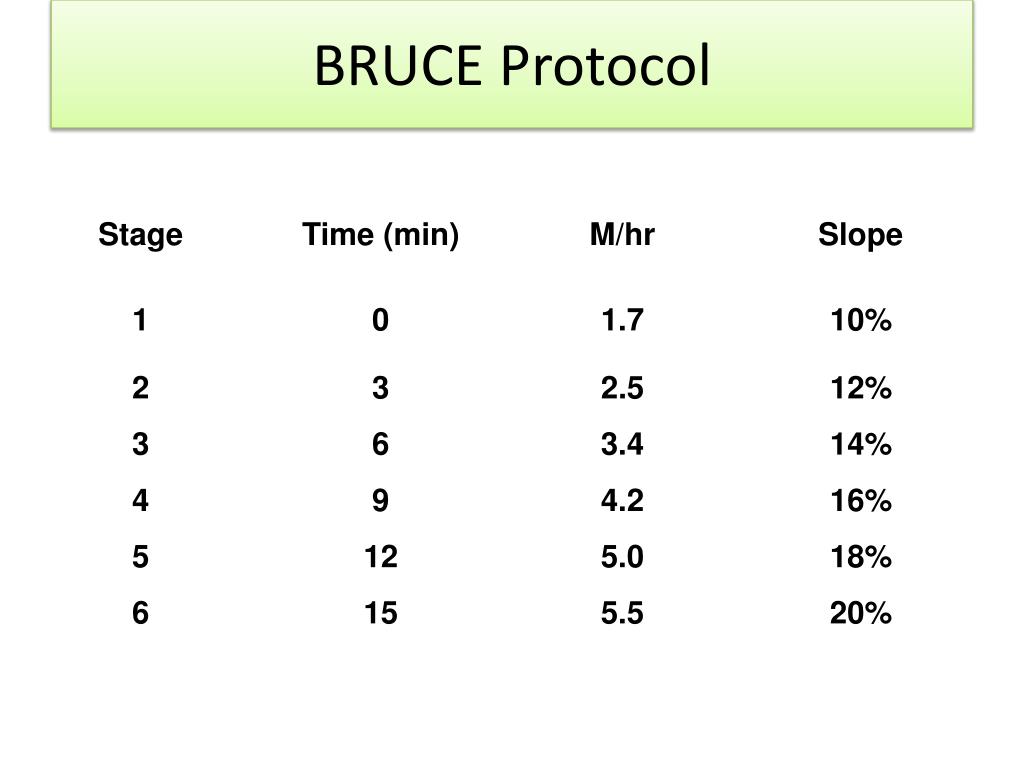
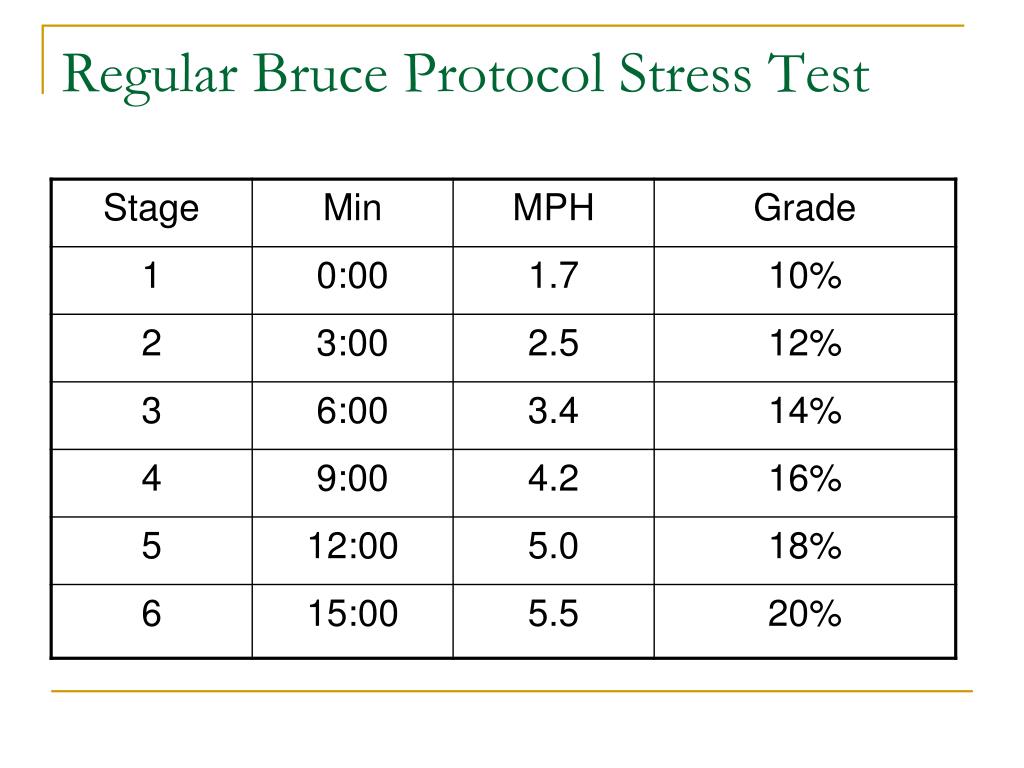
The Bruce Protocol is a treadmill-based exercise test where work rate increases every three minutes by adjusting both speed and incline. Stage 1 is 1.7 mph at 10% grade, Stage 2 jumps to 2.5 mph at 12%, and it keeps climbing from there. The original paper from Dr. Robert Bruce came out in 1972, but the test is still one of the most widely used graded exercise protocols in cardiology departments across the country. It's not fancy, but it's been validated against VO2 max data for over fifty years and still holds up. You hook up a patient, get baseline vitals, attach the electrodes using either the Mason-Likar modification or standard limb placement depending on your lab's preference, and then you start the treadmill. Most of my testing happens with the modified placement because it reduces motion artifact significantly. The nurse or tech pushes the buttons every three minutes, watches the ECG strips like hawks, and calls out heart rates. The test ends when the patient hits their target heart rate, develops significant ST depression, complains of symptoms, or reaches volitional exhaustion. Target heart rate is calculated as 85% of the age-predicted maximum, which is 220 minus age. That formula is approximate and can be off by plus or minus twelve beats per minute in some patients. Don't treat it like gospel, but it works well enough as a stopping criterion when you're combining it with clinical judgment.
I ran into a problem last year with a 62-year-old male who kept hitting 185 bpm at Stage 2 even though his target was supposedly 153. His resting sinus rate was already 105, and he was on low-dose metoprolol. We ended up switching him to a modified Bruce protocol that started at 1.7 mph and 0% grade, keeping the same increments but giving him more breathing room. He completed nine stages without any ischemic changes. Standard Bruce would have stopped him prematurely and we would've missed a significant finding. This isn't covered much in the training manuals, but protocol modification based on baseline vitals is something you need to know how to do. The MET values at each stage are important for interpreting results. Stage 1 is roughly 4.9 METs, Stage 2 is about 8.3, Stage 3 hits 11.8, and by Stage 5 you're at 15.5 METs. A patient who can reach Stage 4 or beyond generally has a good prognosis from a cardiac standpoint. Below Stage 3 raises eyebrows and often triggers further workup. These numbers come directly from the ACSM guidelines and the original Bruce publications.
The counter-intuitive part nobody talks about
ST segment depression doesn't always mean ischemia during a Bruce test, especially in women and patients with baseline repolarization abnormalities. I've seen cases where 2 mm of horizontal ST depression appeared at Stage 3 but the subsequent nuclear perfusion scan came back completely normal. The sensitivity of the standard Bruce protocol without pharmacological stress or imaging sits around 68%, and specificity is closer to 41%. That means you're going to get false positives, and they tend to cluster in certain populations. The other thing that surprises people is that heart rate recovery matters just as much as peak heart rate. A drop of less than 12 beats in the first minute after exercise cessation carries prognostic weight that's independent of the ST findings. Most technicians document the peak and move on, but looking at recovery patterns can catch early autonomic dysfunction before it shows up anywhere else on the report. Artifact from electrode placement is the single biggest source of wasted time on a Bruce Protocol Stress Test. If you're losing signal during Stage 2 or 3, don't just press on and hope it resolves. Nine times out of ten the problem is dry gel or improper skin preparation. Scrape the skin lightly, use abrasive pads, and replace the electrodes mid-test if you notice impedance climbing. A bad signal at 160 bpm looks exactly like ventricular tachycardia to the untrained eye, and misinterpreting that is how you get patients sent to the ER for nothing.
Get the Full Details

When the Bruce Protocol Falls Short
The test assumes the patient can walk on a treadmill. That excludes a lot of people with severe arthritis, amputations, or balance issues. For those patients, you switch to a bike ergometer or use a pharmacological stress test with dobutamine. The Duke Treadmill Score uses the Bruce data to stratify risk into low, intermediate, and high categories, but it only applies when the patient actually completes the test on a treadmill. Blooming artifact on coronary CT angiography can also interfere with interpretation if you're doing a combined test, though that's less common. The bigger issue is that the Bruce Protocol's aggressive stage progression can push some patients into arrhythmia purely from the workload jump rather than from underlying coronary disease. A slower ramp protocol like the Naughton or the Balke might be more appropriate for deconditioned patients or those with a higher risk of fall-related injury. Equipment costs for a proper treadmill stress system run anywhere from eight thousand to twenty-five thousand dollars depending on whether you need integrated imaging or just standard ECG monitoring. Maintenance contracts add another two thousand annually. If your facility is only running twenty or so tests per month, the cost per study starts to look steep compared to alternatives.
The Bruce Protocol Stress Test remains the workhorse of exercise cardiology not because it's perfect but because it's fast, well-understood, and the data is out there. You can compare your results to decades of published literature. Just make sure you're reading the results in context, modifying the protocol when the patient doesn't fit the mold, and watching the recovery phase instead of treating it as an afterthought.