Navigating LVN Practice Boundaries in California
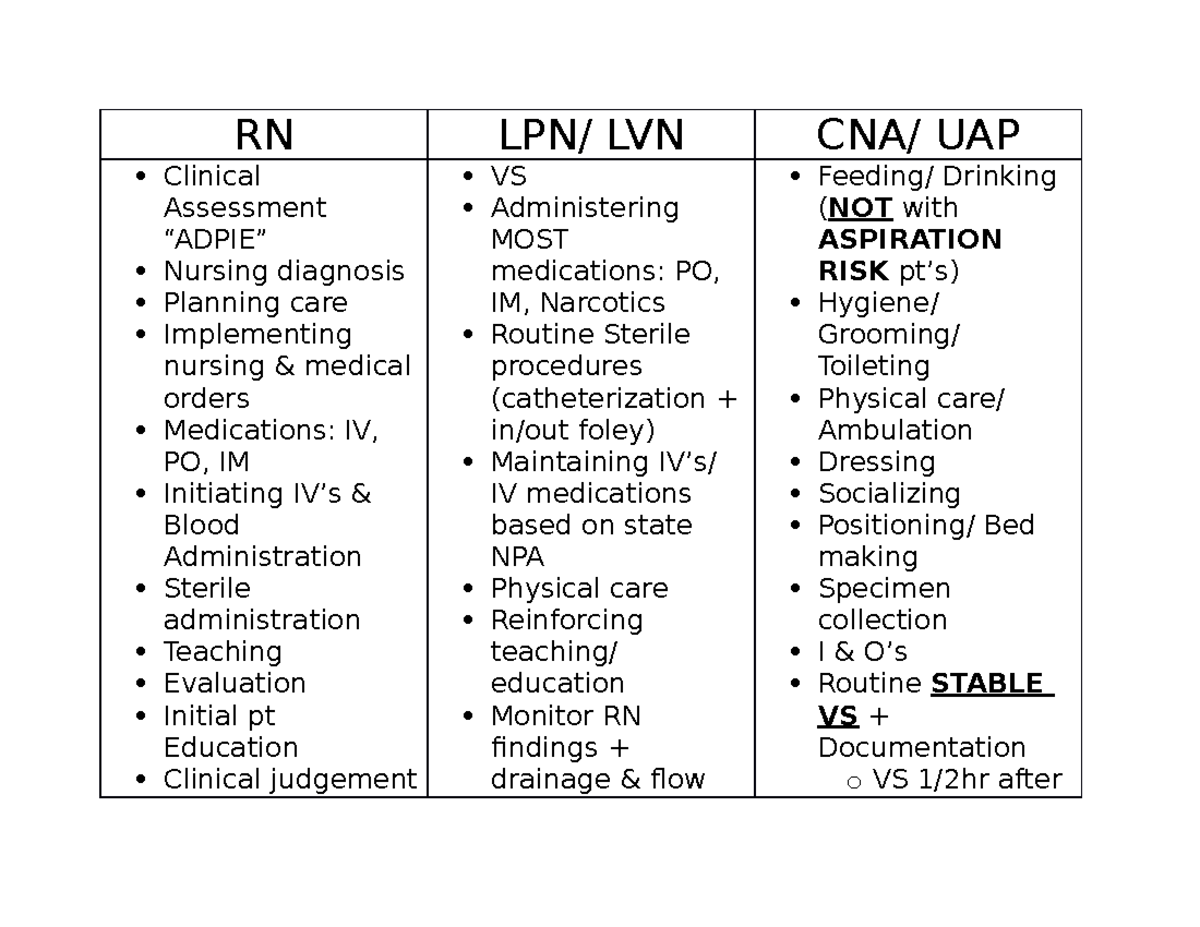
The actual day-to-day reality of being a Licensed Vocational Nurse in this state has a lot more gray area than most people assume when they start study groups. I spent six years working med-surg and then moved into a SNF for four years before going into clinical education, and the thing nobody tells you is that the Board's vocabulary is deliberately vague on certain procedures while being razor-sharp on others. The scope isn't just a list of do's and don'ts — it's a constantly shifting negotiation between facility policy, physician orders, and the actual legal framework that the BSNP enforces when something goes wrong. Here's something that came up pretty recently in a case I was consulting on. An LVN in a skilled nursing facility in San Diego was asked by a covering physician to administer a IV bolus of Lasix for a patient presenting with volume overload. The order said "administer as needed" with no specified rate, concentration, or monitoring parameters. The LVN flagged it to the charge nurse because Lasix IV push in an SNF setting requires specific protocols — dose, rate, electrolyte monitoring, and sometimes cardiac telemetry — that aren't in the standard nursing assistant or LVN skill checklist. The charge nurse had to call the attending physician back to get a modified order with exact parameters before the medication could be given. This isn't a hypothetical — I saw the incident report. The underlying issue was that the original order was incomplete, but the real problem was that the facility's policy didn't clearly define who could initiate IV push diuretics without additional RN-level assessment. This is where most confusion happens. People read the scope document and think "LVNs can give IV medications." That's technically true, but it's also like saying "you can drive a car" without mentioning the licensing tier, the vehicle type, or the road restrictions. In California, LVNs can administer IV medications including continuous IV infusions and blood products, but the initial assessment, dosage calculation verification, and ongoing evaluation of response fall under RN scope. The nuance is that the LVN can administer — meaning hang the bag, regulate the pump, observe the site — but the clinical decision-making about whether that medication is appropriate for that patient at that moment is structured differently between the two roles.
Another area that causes legitimate problems is wound care. The scope document broadly states LVNs can perform wound care, but facility policies in my experience routinely restrict complex wound management — negative pressure therapy, debridement, primary closure — to RNs or wound care specialists. I worked at a facility where an LVN was legitimately confused about whether they could change a wound vac dressing. The answer was yes, but only after the initial placement and protocol setup by an RN or physician, and only using the specific dressings and suction parameters outlined in the physician's order. Cross-contamination between "can do" and "can initiate" is where violations typically occur. There's also the medication administration angle that trips people up. LVNs in California can administer nearly all medication routes — oral, topical, intramuscular, subcutaneous, intravenous. What's restricted is the judgment call around high-alert medications. Insulin, anticoagulants, opioid agonists, and chemotherapy agents require additional safeguards. The 2023 advisory from the Board clarified that while LVNs can administer insulin, they cannot independently initiate insulin protocols or adjust dosing without RN-level assessment data. This means the LVN can hang the pump and monitor for hypoglycemia, but the initial sliding scale order and ongoing titration decisions need to be made or co-signed by an RN or physician. One counter-intuitive thing about the scope is that LVNs actually have broader responsibility in some settings than you'd expect. In long-term care facilities, LVNs often serve as the primary nurses for assigned patients, handling med passes, basic assessments, and care coordination. The RN still owns the admission assessment and the comprehensive care plan, but the day-to-day clinical judgment about whether a patient's wound dressing needs changing, whether their pain medication is adequate, or whether their vital signs are trending in a concerning direction — those moments of micro-decision-making are squarely in the LVN lane. The problem is that most new LVNs don't realize they have this latitude and either under-function or over-function depending on their confidence level.
Let me address the limitation head-on because this matters. The scope of practice document is intentionally flexible, and that flexibility is its greatest weakness. When the Board investigates a complaint, they look at whether the LVN acted within the scope AND whether the facility's policies aligned with that scope. If a facility has a policy that restricts an LVN from doing something the Board scope permits — say, administering a specific IV antibiotic — that policy restriction is legally binding on the employee even if it's not in the statute. Conversely, if the scope permits something and the facility has no policy against it, the LVN can proceed, but they still carry individual liability for their clinical decisions. The Board doesn't protect you because your nurse manager told you it was fine. The biggest practical bottleneck I see is the assessment-versus-monitoring distinction. The Board draws a line between making an assessment (gathering and interpreting new clinical data to form a nursing diagnosis or plan) and monitoring (observing and reporting existing data). LVNs monitor; RNs assess. But in practice, this line blurs constantly. An LVN noticing that a patient's respirations changed from regular to irregular isn't just monitoring — they're interpreting. The safe move is to report the finding immediately to the RN rather than attempting to diagnose the cause. This isn't about limiting the LVN's value — it's about protecting both the patient and the nurse from liability when the interpretation turns out to be wrong. If you're studying for the NCLEX-VN or preparing to work in California, the single most useful thing you can do is get a copy of your facility's policy manual and cross-reference it with the BSNP scope document. Where they conflict, facility policy wins for your employment. Where they're silent, the scope document applies. Where both are silent, you default to the standard of care for your education level and experience. That standard is defined by what a reasonably prudent LVN with similar training would do in the same situation — and that's the benchmark the Board uses in every disciplinary case I've reviewed.
Get the Full Details