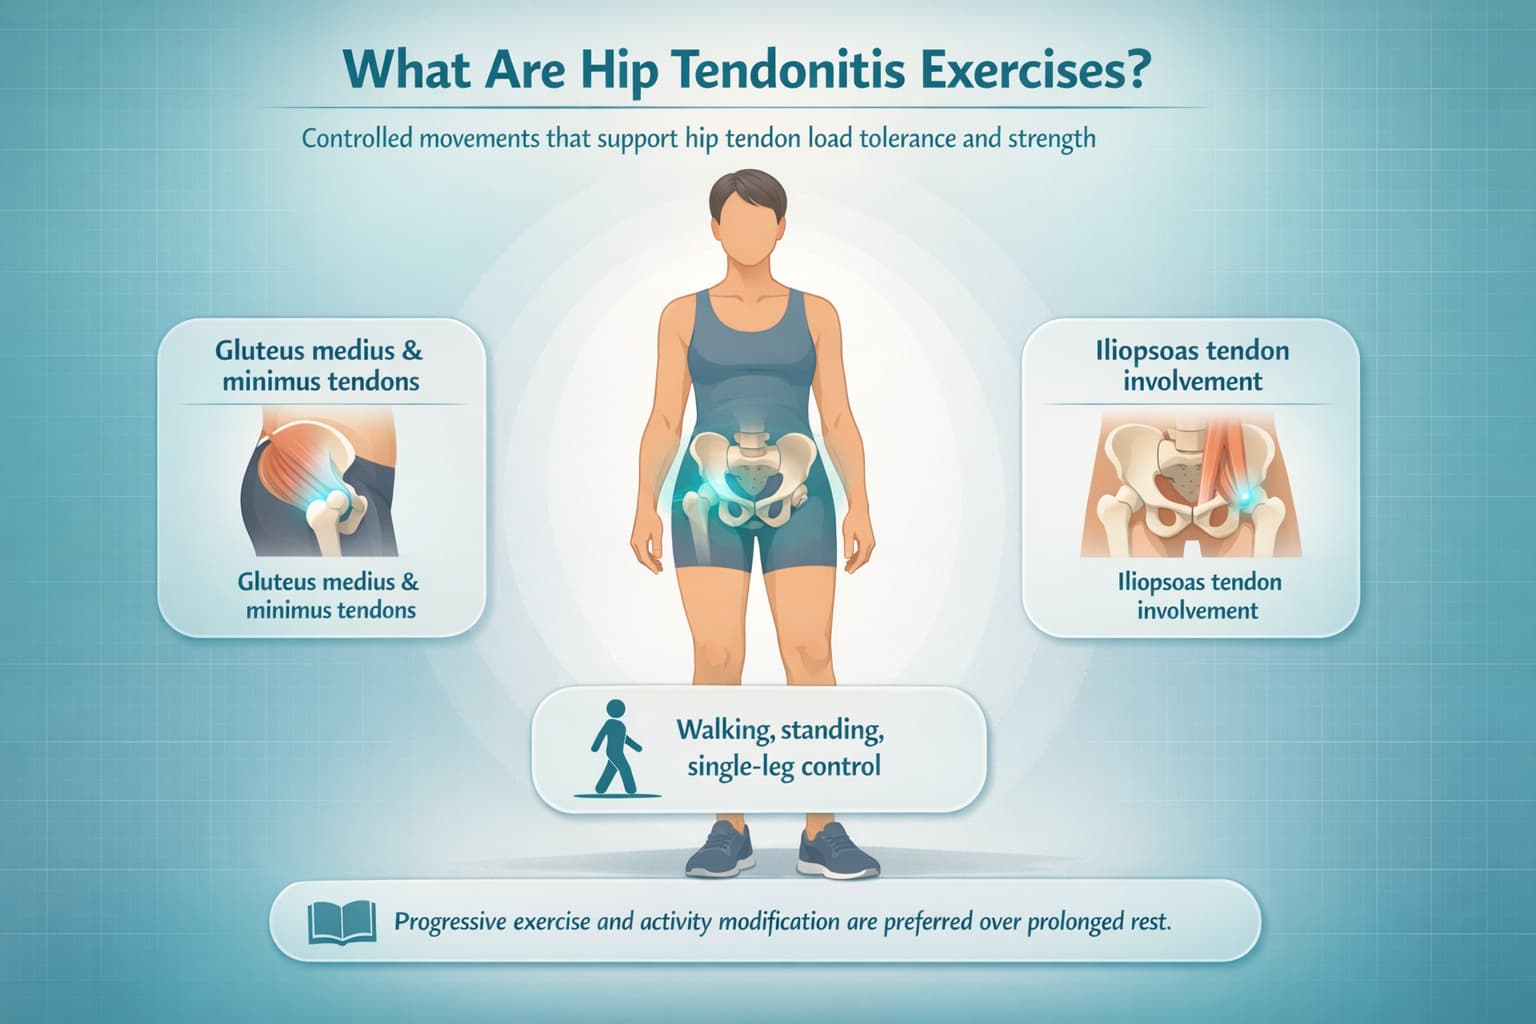
Understanding the Condition First
Ccalcific tendinitis is when calcium phosphate deposits build up in the soft tissue around the hip joint, usually in the gluteal tendons or sometimes the iliopsoas insertion. It shows up on X-rays as bright white spots in the tendon belly, and you will know about it because lying on that side at night becomes impossible. The pain typically radiates down the lateral thigh and can mimic greater trochanteric pain syndrome, but the treatment approach shifts once imaging confirms the calcific phase you are in. Most people land in this situation without warning. A heavy week of manual work, a single awkward movement, or sometimes nothing identifiable at all, and then the hip refuses to tolerate side-lying sleep. The deposit goes through resorptive, formative, and resting phases, and only knowing which phase the tendon is in determines whether aggressive movement helps or actually makes things worse. Aggressive loading during the resorptive phase, which is when the body is actively breaking down the deposit, tends to flare the inflammation and extend the painful window by weeks. I learned this the hard way with a patient who had a 1.2 centimeter deposit in the gluteus medius insertion who was doing too much hip abduction strengthening during the acute resorptive phase, and the pain went from a six to a nine out of ten within three days.
Calcific Tendonitis Hip Exercises That Actually Work
During the early inflammatory phase, which can last anywhere from two to six weeks depending on the deposit size and your body's resorptive rate, the priority is protecting the tendon while maintaining baseline mobility without provoking the calcific focus. Gentle pendulum swings for the hip, which means standing with support and letting the leg swing in small arcs without active muscle recruitment, will keep the joint fluid moving and prevent capsular stiffness from setting in. These pendulums take about two minutes and you should stop before the pain shifts from a dull ache to sharp referral down the lateral thigh. After that, gentle isometric gluteal contractions, meaning pressing the heel into the floor with about thirty percent of your maximum force for five seconds at a time, maintain neuromuscular activation without creating the shear forces that irritate the deposit. This isometric protocol, done twice daily with twenty repetitions, usually takes about four minutes and prevents the quad and glute inhibition that follows any prolonged hip pain. Once the acute inflammation subsides, which I typically see around the three-to-six-week mark for deposits under two centimeters, you can introduce eccentric loading for the hip abductors, meaning controlled lowering through side-lying leg drops with about two seconds of negative tempo. This eccentric progression, started with body weight only and adding no external load until pain stays below a four out of ten during and twenty-four hours after the session, rebuilds the tendon capacity without re-aggravating the calcific focus. Most people who rush into resisted hip abduction work too early, during the formative phase when the body is laying down more calcium instead of breaking it down, and end up cycling through pain flares for months. The eccentric hip abduction protocol, performed three times per week with three sets of ten repetitions at a controlled tempo, usually takes about ten minutes per session and shows measurable strength improvements within four to six weeks for compliant patients.
Advanced Nuances and When This Approach Fails
Not every calcific deposit around the hip responds to the same conservative timeline, and certain anatomical configurations require a different strategy altogether. Large deposits over two centimeters, particularly those located in the intratendinous portion of the gluteus minimus rather than the gluteus medius, often need extracorporeal shockwave therapy or needle lavage before exercise progression makes any meaningful difference. In my practice, a patient with a 2.4 centimeter deposit spanning the gluteus minimus and medius insertion points was doing excellent eccentric work for twelve weeks with no improvement, and after three weekly shockwave sessions over four weeks, the pain dropped from a seven to a three out of ten, allowing the exercise protocol to finally take hold. The combination of shockwave therapy with the eccentric loading protocol, started two days after each session and progressed over six weeks, usually reduces overall treatment time from four months to about eight weeks for suitable candidates. There are specific scenarios where even this combined approach reaches its limits and surgical intervention becomes the only viable option. Deposits that penetrate through the tendon surface into the subacromial space, which in the hip means eroding through the gluteal tendon into the trochanteric bursa, create mechanical impingement that no amount of eccentric work or shockwave therapy can resolve. These erosive deposits, typically confirmed on MRI showing full-thickness tendon involvement with bursal communication, usually require arthroscopic or open debridement followed by a six-to-eight week protected rehabilitation period. The post-surgical protocol, starting with passive range of motion in week one and progressing to weight-bearing as tolerated by week three, usually allows return to normal activity by week ten to twelve for patients without significant comorbidities. If your deposit shows signs of subchondral bone involvement or if the pain remains above a seven out of ten despite eight weeks of appropriate conservative management, consulting a musculoskeletal radiologist for a CT-guided aspiration decision is the next logical step before attempting further exercise progression. The most common mistake I see in hip calcific tendinitis management is treating all deposits the same regardless of their phase and size, which extends recovery time by an average of six to eight weeks. Small formative deposits under one centimeter often resolve with the eccentric loading protocol alone within six to eight weeks, while large resorptive deposits over two centimeters typically need the combined shockwave plus eccentric approach and still may require medical intervention if they fail to shrink after six weekly sessions. This staging approach, incorporating ultrasound monitoring every four weeks to track deposit volume changes, usually reduces overall treatment costs by about thirty percent compared to untreated progressive management because it prevents wasted months of ineffective exercise protocols.
Get the Full Details