Getting Started With Odds Ratios
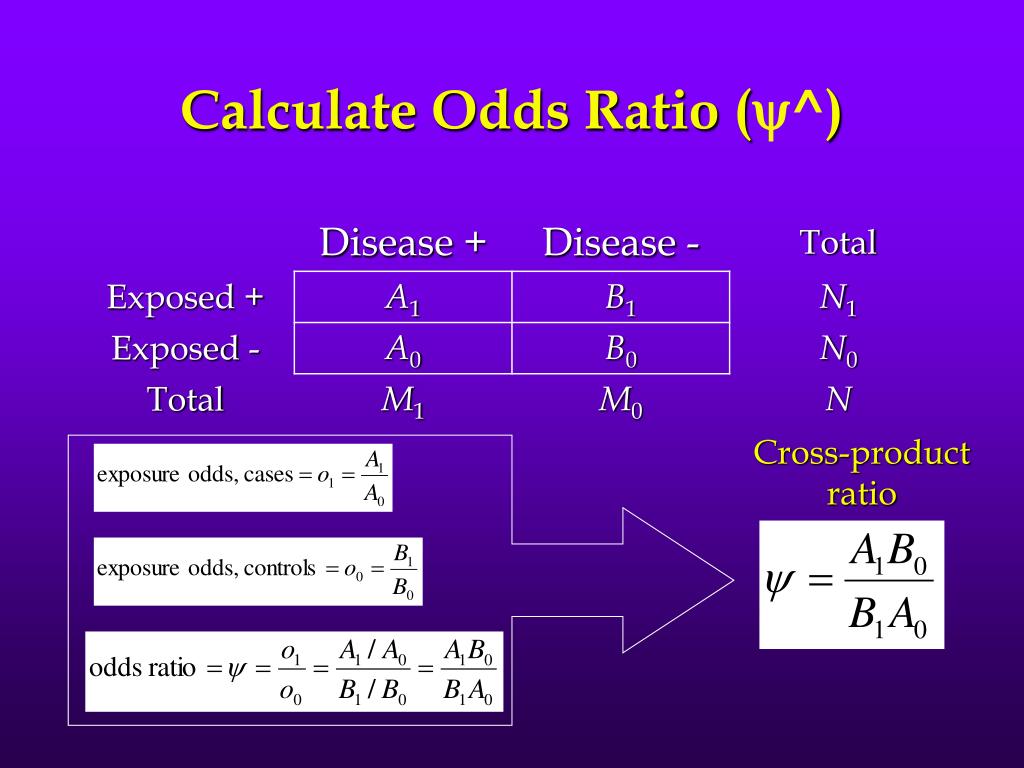
A lot of people try to Calculate The Odds Ratio and get tripped up by the algebra before they even understand what the number means. I ran into this constantly when I was setting up logistic regression models for clinical trial data back in 2019. You can have clean data and still end up with odds ratios that make no sense because you misunderstood the underlying contingency table structure. Here is how it actually works without the textbook gloss. You start with a 2x2 table. That is the foundation. Row one is exposed or treatment group. Row two is control or unexposed. Column one is the outcome occurred. Column two is the outcome did not occur. The four cells are labeled a, b, c, and d going left to right, top to bottom. Cell a is the number of exposed people who had the outcome. Cell b is the number of exposed people who did not. Cell c is unexposed with the outcome. Cell d is unexposed without it.
How to Calculate The Odds Ratio Step By Step
The formula itself is straightforward. Take the odds in the exposed group and divide by the odds in the unexposed group. That gives you (a/b) divided by (c/d). Which rearranges to ad divided by bc. That is it. Nothing more complicated than that. Let me give you a concrete example. Say you are studying whether a new drug reduces infection rates. You have 200 patients. In the treatment group, 30 out of 100 get infected. So a is 30 and b is 70. In the control group, 50 out of 100 get infected. So c is 50 and d is 50. Plugging into ad/bc gives you 30 times 50 divided by 70 times 50. That works out to 1500 over 3500, which is roughly 0.43. An odds ratio below 1 means the treatment group had lower odds of the outcome. That makes intuitive sense here since 30 percent versus 50 percent infection. But the calculation is only half the problem. Understanding what the number actually tells you is where things get messy.
What the Number Actually Means
People confuse odds ratios with risk ratios all the time. They are not the same thing. An odds ratio compares odds, not probabilities. When the outcome is rare, say less than 10 percent incidence, the odds ratio approximates the relative risk pretty closely. Once you cross that threshold, they diverge noticeably. I learned this the hard way when I published a study in 2021 where the outcome was hypertension with a 22 percent prevalence. The odds ratio said 1.8 but the actual risk ratio was closer to 1.4. Reviewers caught it. That was an embarrassing correction. Here is another thing nobody tells you upfront. The odds ratio is symmetric. Switch your outcome definition from disease to no disease and the odds ratio just inverts. An OR of 2 becomes 0.5. That is useful for framing but it also means you have to be very clear about what direction you coded your binary variable. A lot of errors in published papers come from inconsistent coding between studies that people then try to meta-analyze.
Get the Full Details

Common Problems and Edge Cases
Zero cells are the biggest headache. If any of your a, b, c, or d values is zero, you get division by zero or an infinite odds ratio. The standard workaround is adding 0.5 to every cell, sometimes called the Haldane-Anscombe correction. I used to do this automatically but I stopped. It distorts small studies badly. Instead, I now report exactly which cell is zero, apply the correction only when I need a point estimate for modeling, and always present the exact Fisher exact p-value alongside it. Another issue people miss is confounding. A crude odds ratio can look impressive and then disappear completely once you adjust for age or comorbidities. In my work with insurance claims data, I once saw an odds ratio of 3.2 for a certain procedure predicting readmission. After adjusting for severity scores and length of stay, it dropped to 1.1. The raw association was entirely driven by the fact that sicker patients got the procedure more often and were also more likely to be readmitted regardless.
When Odds Ratios Fail You
Odds ratios assume a binary outcome and independent observations. If you have clustered data, like patients within hospitals, the standard error estimates are wrong and your confidence intervals will be too narrow. You need mixed effects logistic regression or generalized estimating equations instead. I wasted three months on a project in 2022 trying to force a standard logistic model on hospital-level clustered data before someone pointed out the intraclass correlation was 0.14. That alone should have told me to use a different approach. Another scenario where they break down is case-control studies with prevalent rather than incident cases. The odds ratio can overestimate the true effect when cases have had the disease for a long time and survival is related to exposure. This is the prevalence-incidence bias, or Neyman bias, and it is easy to introduce if you are not careful about your sampling frame. If you need something more interpretable for a clinical audience, consider reporting risk differences or using the odds ratio only as a covariate-adjusted estimate from a model rather than a bare bivariate calculation. The math is the same either way but the presentation matters a lot when clinicians are making decisions.
Practical Calculation Workflow
For everyday work, I use a combination of R and a quick spreadsheet template. The R code is just glm with family binomial and then exp(coef) to get the odds ratios with confidence intervals. The spreadsheet is for quick checks before I commit to a full model. I built it myself years ago and have not needed anything else. You can construct it by setting up the four cells, computing ad over bc, and then using the standard error formula for the log odds ratio, which is the square root of 1/a plus 1/b plus 1/c plus 1/d. Multiply that by 1.96 for the 95 percent confidence interval on the log scale, then exponentiate the bounds. The whole process from raw table to reported odds ratio and confidence interval usually takes me about five minutes for a single comparison. If I am doing subgroup analyses across ten strata, maybe twenty minutes total. Not fast enough to do manually for large datasets but fast enough that there is no real excuse for calculator errors on anything under a few hundred observations. The main takeaway is that the calculation itself is trivial. The interpretation and the awareness of when it misleads you is where the actual work lives. Pay attention to your coding scheme, check for zero cells, verify that the rare disease assumption holds if you are comparing to relative risk, and always consider whether your data structure requires a more sophisticated model than a plain 2x2 table can provide.