Handling Gallstones When The Gallbladder Isn't Inflamed
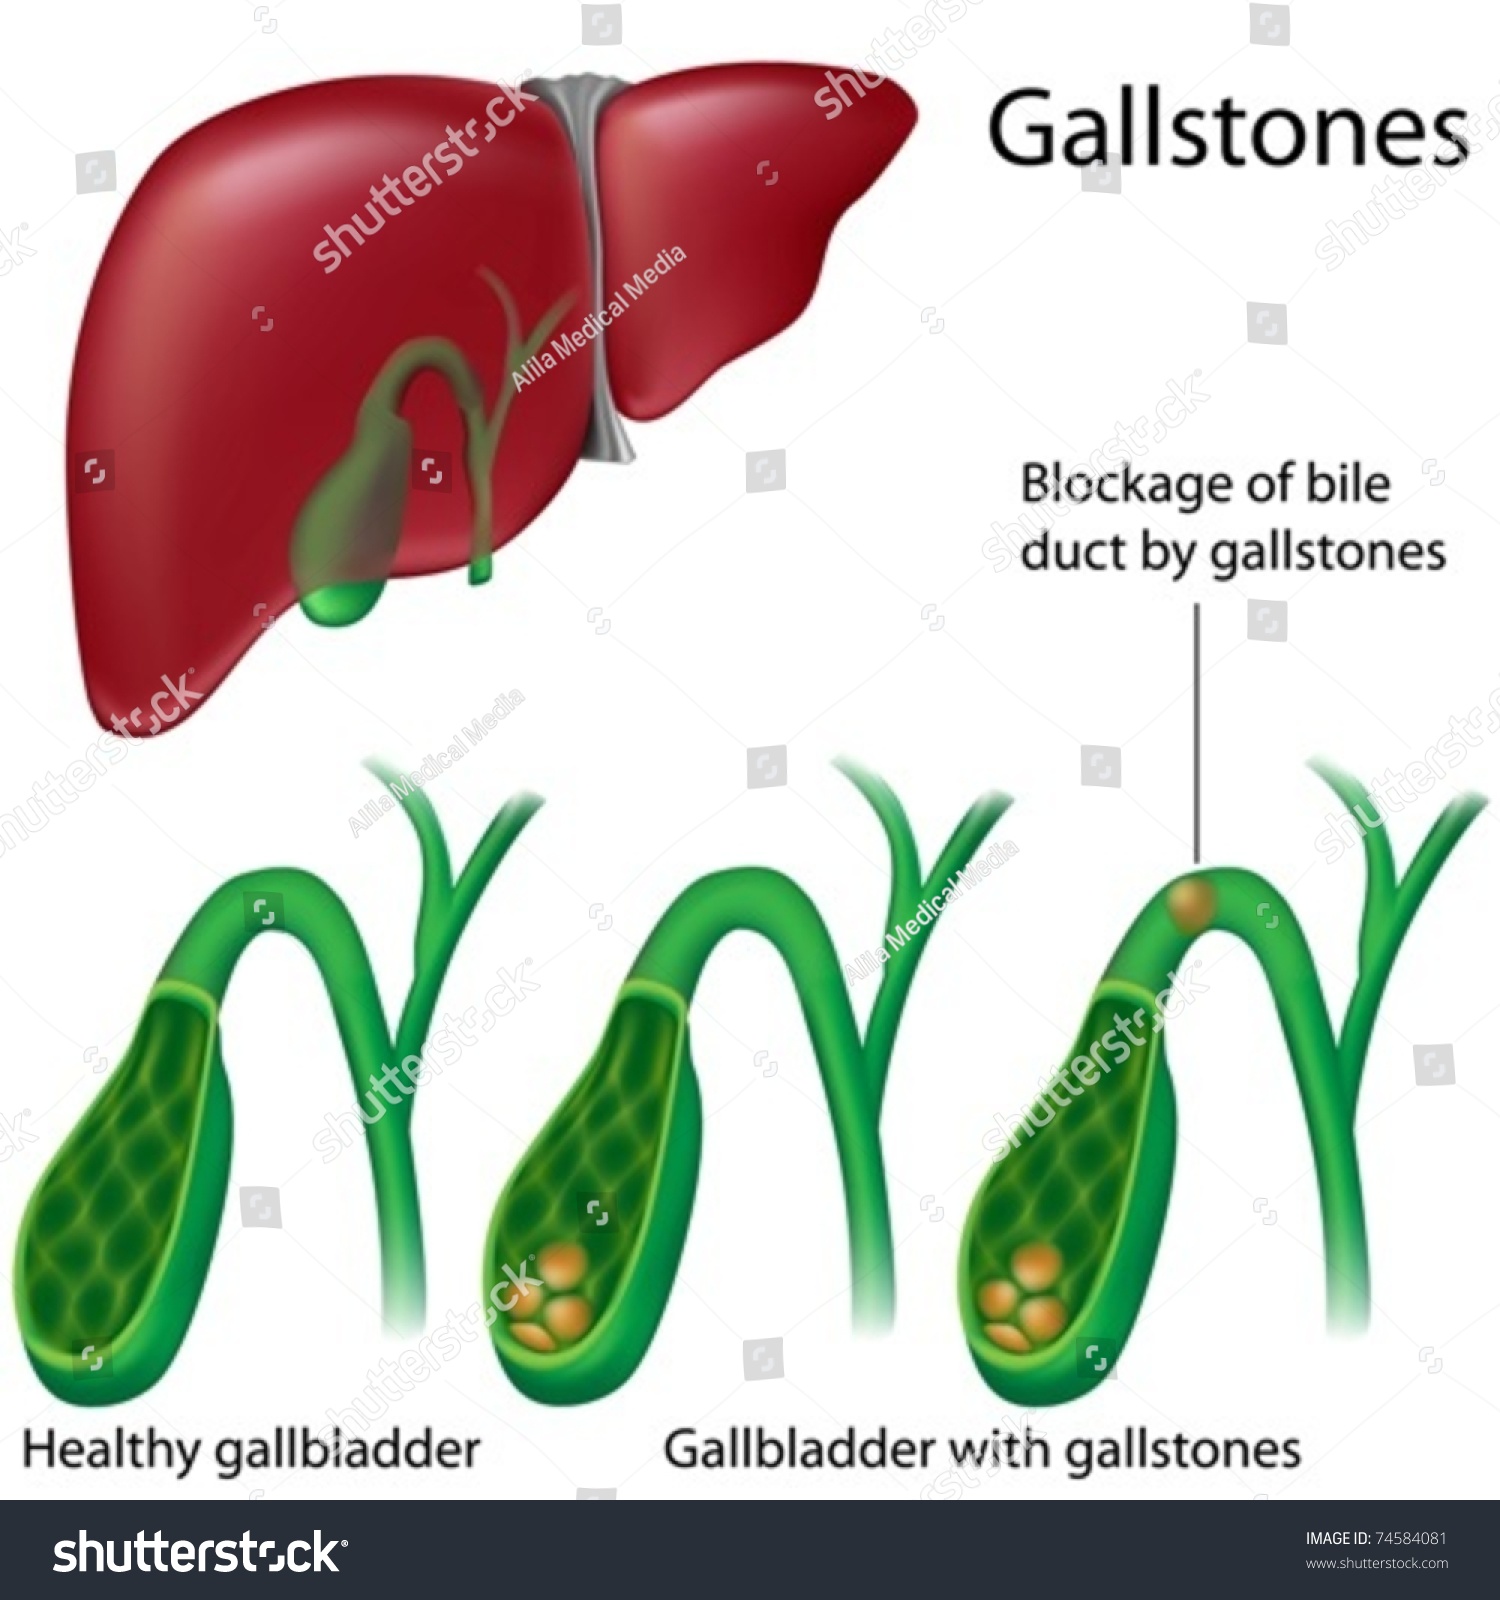
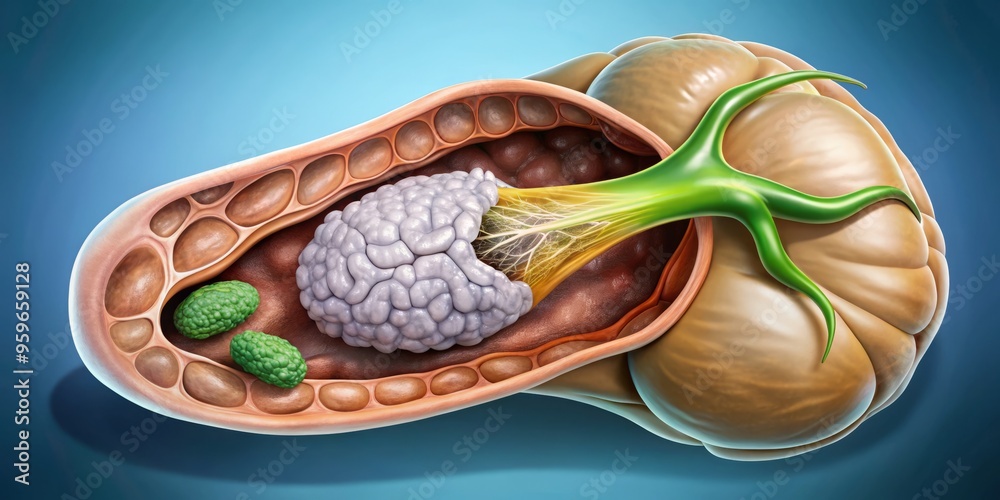
Most people with gallstones never develop cholecystitis. The stones sit there quietly. That changes how you approach diagnosis, monitoring, and whether intervention is even warranted. This is one of those areas where guidelines and actual practice drift apart. You're dealing with gallstones that haven't triggered acute inflammation. Technically called asymptomatic cholelithiasis when symptoms are absent, though plenty of these patients report vague upper abdominal discomfort that never quite meets the threshold for calling it biliary colic. The ultrasound findings are straightforward. Hyperechoic foci within the gallbladder lumen with posterior acoustic shadowing. Stones larger than 3 centimeters carry a higher malignancy risk over time, which is worth flagging but rarely prompts immediate action. Multiple small stones actually pose a greater immediate risk because they can migrate into the cystic or common bile duct.
I ran into a case last year where a patient had what looked like routine gallstones on routine imaging. Everything appeared stable. No wall thickening, no pericholecystic fluid. But the stones were densely packed and the gallbladder was contracted around them. On follow-up three months later, she'd developed recurrent biliary colic despite initially reporting no symptoms. The takeaway is that a single normal scan doesn't lock in an asymptomatic classification. Gallbladder dynamics change.
How I Approach Management Decisions
Watchful waiting remains the standard for truly asymptomatic patients. The annual risk of developing symptoms is roughly 1 to 2 percent. Prophylactic cholecystectomy isn't recommended for the general population with incidental gallstones. I've seen it attempted in diabetic patients on the theory that diabetes masks symptoms, but the evidence there is weak and most surgeons still defer. There are exceptions where I'd move toward intervention even without cholecystitis. Patients scheduled for bariatric surgery benefit from prophylactic gallbladder removal because rapid weight loss dramatically increases stone formation and complication rates. Same consideration for patients receiving total parenteral nutrition long-term. Solid organ transplant candidates often get the gallbladder addressed pre-transplant due to immunosuppression altering the risk calculus. When symptoms do emerge, the picture shifts. Biliary colic typically presents as steady right upper quadrant or epigastric pain lasting 30 minutes to several hours, often postprandial after fatty meals. Unlike cholecystitis, there's no fever, no leukocytosis, and no Murphy's sign on examination. If those inflammatory markers appear, you're no longer in the asymptomatic category.
Get the Full Details

Diagnostics beyond the initial ultrasound are limited. HIDA scans with CCK stimulation can identify biliary dyskinesia in patients with pain but normal anatomical imaging. The test takes about two hours. Elevation of liver enzymes or bilirubin during an episode suggests choledocholithiasis, which is a separate problem requiring ERCP rather than immediate surgery. Ursodeoxycholic acid is theoretically an option for dissolution therapy, but it takes 6 to 24 months of daily medication, has a high recurrence rate after discontinuation, and only works on cholesterol stones under 1.5 centimeters. I've prescribed it maybe twice in fifteen years. It's not worth the discussion unless a patient absolutely refuses surgery and understands the odds. The real complication to watch for is gallstone pancreatitis. A single stone passing through the ampulla can trigger severe pancreatitis even without any gallbladder inflammation. This isn't theoretical. I had a patient whose only presentation was a gallstone-induced pancreatic event. By the time it was caught, she'd already been through the emergency department twice for unrelated-sounding abdominal pain over six weeks.
Surgical removal, when indicated, is laparoscopic in nearly all cases. Recovery is typically one to two weeks for normal activity. Complication rates for elective cholecystectomy sit below 5 percent for major adverse events. The common bile duct injury rate is approximately 0.3 to 0.5 percent in experienced hands. You accept that risk against the alternative of unpredictable symptomatic progression. One thing nobody warns patients about: post-cholecystectomy diarrhea affects roughly 10 percent of people and can persist for months. Bile flows continuously into the intestine without the gallbladder's storage function. Loperamide or bile acid sequestrants like cholestyramine usually manage it, but patients should know upfront so they aren't surprised. If you're managing this conservatively, repeat ultrasound in 6 to 12 months isn't routinely necessary for truly asymptomatic cases, but I tend to schedule one anyway. It catches gallbladder wall changes or ductal dilation before they become urgent. Cost-effective in the long run compared to an emergency presentation.