Understanding the Mechanics Before You Try to Fix Anything
Anxiety attacks are not mysterious events that happen to you without cause. They are a physiological cascade, the same fight-or-flight response that evolved to protect us from physical threats, misfiring when there is no actual danger present. The sympathetic nervous system dumps adrenaline into your bloodstream. Your heart rate spikes. Blood vessels constrict. Your breathing becomes shallow and rapid. This is biology, not weakness, and understanding the mechanism is the first step toward intervention. I spent years watching people try to think their way out of panic. It does not work. You cannot cognitive-reframe your way out of an adrenal surge. When the attack is already happening, the prefrontal cortex — the part of your brain responsible for rational thought — is essentially offline. The amygdala has hijacked the system. That is why breathing exercises and grounding techniques need to be practiced during calm states so they become accessible when the hijacking occurs.
Can Anxiety Attacks Be Controlled
The honest answer is no and yes simultaneously, and the distinction matters more than most people realize. You cannot control whether an anxiety attack will occur in any given moment. The triggers are often unpredictable, sometimes internal like a fluctuation in blood sugar or a vague memory surfacing without context. But you can absolutely control the duration, intensity, and aftermath of an attack once it begins. That shift in framing — from prevention to management — is where most people get stuck because they exhaust themselves trying to eliminate attacks entirely, which is not realistically possible for anyone with a diagnosed anxiety disorder. The control question also depends on what kind of anxiety event you are dealing with. A panic attack, which peaks within ten minutes and then subsides, responds differently to intervention than a generalized anxiety episode that simmers for hours or days. I learned this the hard way during a period when I was treating both as identical problems. I prescribed the same breathing protocol for a two-hour wave of chronic worry as I would for a twelve-minute acute panic spike. The results were predictably inconsistent and I wasted months wondering why some interventions seemed to fail completely.
The Physiological Interrupt
The most effective immediate intervention targets the body first, not the mind. When you experience the onset of an attack — the tight chest, the ringing in your ears, the sense that something is catastrophically wrong — the fastest way to signal to your nervous system that you are not in danger is through active stimulation of the vagus nerve. This is the long nerve that runs from your brainstem through your chest and abdomen and acts as the main highway for parasympathetic activation, the branch of your nervous system responsible for bringing you back down. Here is what actually works and what people usually get wrong about cold exposure as a vagal stimulant. Dipping your face into a bowl of ice water for thirty seconds triggers the mammalian dive reflex, which immediately slows your heart rate. This is well-documented in medical literature. But most people do this half-heartedly, splashing a little cold water on their face, which does nothing. The water needs to be cold enough to be uncomfortable and you need to hold your breath while submerging for at least fifteen to twenty seconds. I keep a small bowl of ice water at my desk specifically for this purpose. The first time I used it correctly during a panic onset at work, the attack dropped from what would have been a twenty-minute episode to roughly four minutes. The difference between those two outcomes was the quality of the cold stimulus, not the technique itself. If you do not have access to ice water, another vagal stimulation method is applying strong pressure to the carotid sinus area on the side of your neck. This is the same mechanism behind the Valsalva maneuver and it can reset heart rate variability. Press firmly but do not press on both sides simultaneously — that can drop your blood pressure too drastically. Ten seconds of pressure on one side is sufficient.
Get the Full Details

Grounding Techniques That Actually Work
The 5-4-3-2-1 grounding method gets recommended everywhere, but most people execute it poorly. They rush through it in under thirty seconds while still hyperventilating, which defeats the purpose. The technique works because it forces your attention away from internal catastrophic thinking and onto external sensory input, which requires engagement from different neural pathways. But it only works if you slow down enough to actually register each sensory detail. Here is what I found through trial and error: start with something that provides physical resistance rather than just observation. Press your feet flat against the floor and note the pressure. Squeeze your hands into fists and hold for five seconds, then release. Then move to the visual count — name five things you can see, but do not just glance at them. Describe each one in your head with specific details: the color, the texture, the light hitting it. This specificity matters because a panicked brain tends to process information in broad, distorted strokes. Forcing detailed observation disrupts that pattern. One thing about grounding that nobody mentions is that it does not work for everyone during the peak of an attack. Some people find that trying to focus externally when they are in full panic mode feels impossible and only increases frustration. If you try grounding and it makes things worse, stop. Return to the physiological interrupt — cold water, breath retention, controlled exhale breathing — and only attempt grounding again once the initial surge has decreased. The timing of when you introduce cognitive techniques matters significantly.
Prevention Through Nervous System Conditioning
Controlling future attacks requires building tolerance in your baseline nervous system. This is the part most people skip because it is not dramatic or immediately rewarding, but it is where the real long-term control happens. Regular diaphragmatic breathing practice, ideally twice daily even when you are not anxious, gradually increases your heart rate variability. Higher HRV is associated with better emotional regulation and a higher threshold for panic onset. Studies consistently show this correlation, though the practical application is less discussed than the statistical finding. I recommend five minutes of box breathing every morning and every evening. Inhale for four counts, hold for four, exhale for four, hold for four. The holds are the critical component that most people omit because they feel unnecessary. The breath retention builds CO2 tolerance, which directly affects how your body responds to the hyperventilation that accompanies panic. People with low CO2 tolerance begin hyperventilating sooner and more severely when stressed. Building that tolerance is like conditioning a muscle. Magnesium glycinate supplementation is another underutilized tool. Magnesium plays a role in regulating neurotransmitters and the HPA axis, which is your stress response system. A deficiency makes anxiety symptoms worse and harder to manage. I started taking 200mg of magnesium glycinate before bed about eighteen months ago and noticed a measurable difference in my baseline anxiety levels within three weeks. It is not a panic treatment — it is a system-level support that raises your threshold before attacks even begin. If you are considering supplementation, talk to a healthcare provider first, especially if you have kidney issues or take medications that interact with magnesium.
When Professional Intervention Is Necessary
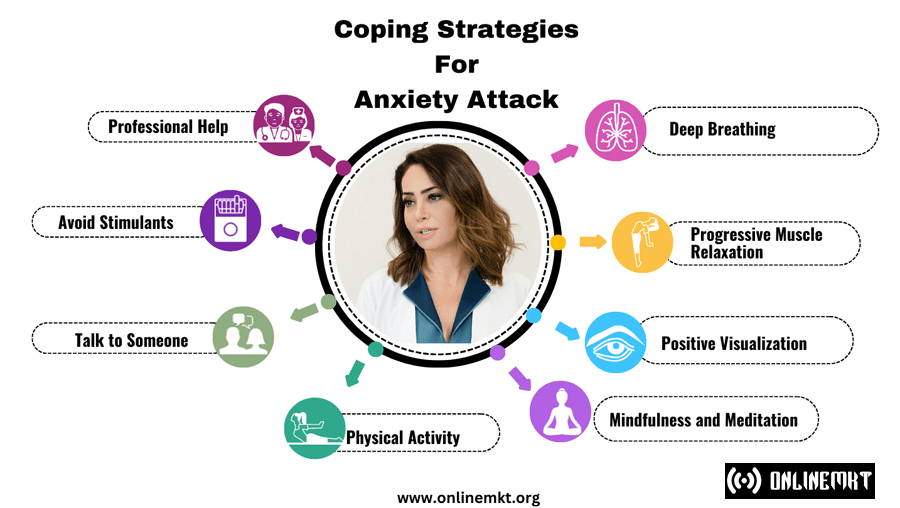
Self-management has hard limits and recognizing those limits is part of controlling the problem. If you are experiencing more than two panic attacks per week, if you are developing avoidance behaviors that interfere with your daily life, or if over-the-counter strategies have not reduced frequency after a consistent three-month trial, professional treatment is not optional — it is necessary. Cognitive behavioral therapy, specifically exposure-based CBT, has the strongest evidence base for panic disorder treatment. It is not about thinking positively. It is about systematic desensitization where you gradually expose yourself to the physical sensations of panic in a controlled environment so your brain learns they are not dangerous. This rewires the fear response over time. Medication is another option that carries real trade-offs. SSRIs reduce the frequency and severity of attacks for most people, but they take six to eight weeks to reach full effect and have side effects that some people find intolerable. Benzodiazepines work immediately but carry dependency risk and cognitive side effects that make them unsuitable for regular use. I am not prescribing anything here — those decisions belong with a psychiatrist — but understanding the mechanism and the timeline of each approach helps you make informed choices rather than reacting to whatever your doctor suggests without context.

The Edge Case Nobody Talks About
There is a specific type of anxiety onset that behaves differently and most standard advice does not address it. I call it the delayed cascade, where you experience what seems like a mild anxiety episode — elevated heart rate, slight restlessness, some mental fog — but instead of resolving, it amplifies over the next forty-five to ninety minutes into a full attack. This typically happens when you dismiss early signals and continue normal activity, allowing the physiological cascade to build unchecked. The workaround I developed involves setting a hard stop at the first sign of symptoms. If I notice the early indicators, I immediately enter a low-stimulation environment: quiet room, dim lighting, no screens, seated or lying down position. I begin the breathing protocol before the attack escalates. This interrupts the cascade before it gains momentum. The early window is roughly fifteen minutes long, and using it effectively requires recognizing your personal early warning signs, which takes honest self-observation over several weeks. You will not always catch it in time, but increasing your detection rate even slightly makes a measurable difference in attack frequency over months. Anxiety attacks can be managed, but the word managed is doing important work here. Control implies prediction and prevention, and neither is fully achievable. What is achievable is reducing duration, decreasing frequency through conditioning, and building the skills to interrupt attacks before they reach full intensity. The people who fare best are the ones who stop treating anxiety attacks as emergencies to be survived and start treating them as physiological events to be understood and systematically addressed.



