Can Quiet Anxiety Attacks Be Dangerous?
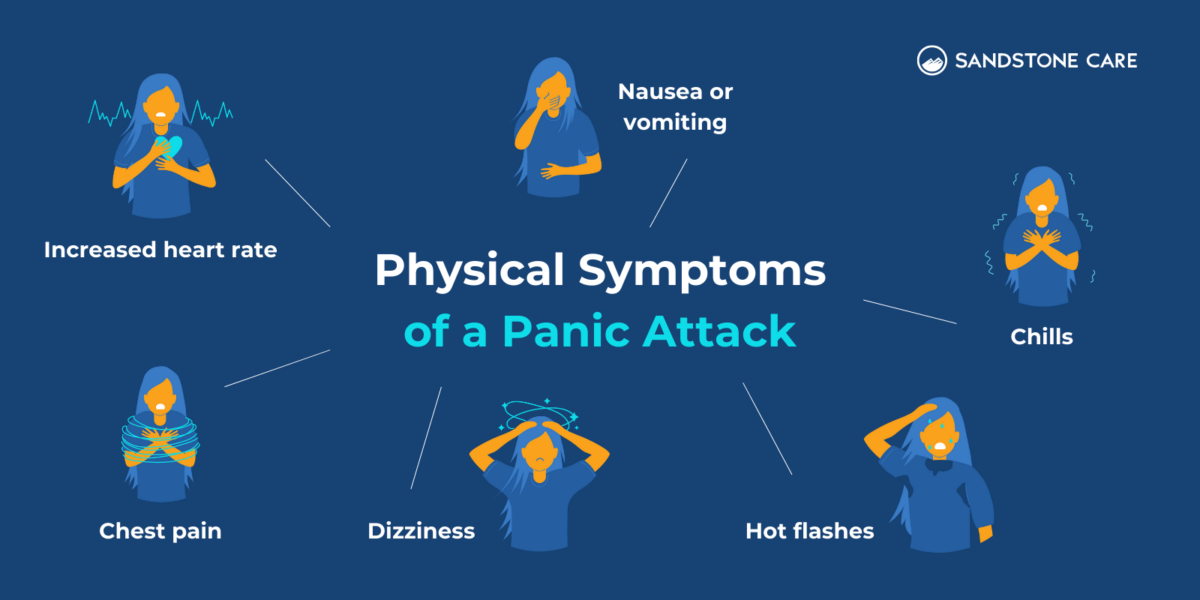
Most people think of anxiety attacks as the classic full-body panic episode — racing heart, visible trembling, maybe hyperventilating enough that someone notices. But there is a category of attack that looks like nothing from the outside. You might be sitting at your desk, or in the middle of a conversation, and internally it is already level five. Your breath shortens. Your chest tightens. Your thoughts start looping on the same worst-case scenario for ten minutes straight, and nobody around you knows. Yes. Quiet anxiety attacks are a real thing, and they are actually more common than most people realize. The clinical term you might run into is restricted or minimally expressed panic — an episode where the autonomic symptoms are present but muted, or where the person has learned to suppress the outward signs so thoroughly that only they can feel what is happening. Sometimes it is because the attack manifests primarily as cognitive and emotional distress rather than physical agitation. Sometimes it is because social conditioning, especially in certain workplaces or family environments, taught the person to stay completely still and keep their voice level even when they were falling apart inside. I spent a few years working with people who came in thinking they did not have anxiety because they could not point to the obvious physical symptoms. One person I worked with described her episodes as "just a heavy feeling in my chest that lasts about twelve minutes and then vanishes." She had no trembling, no crying, no visible distress. What she did have was a spike in heart rate, a sudden inability to process language while reading emails, and a compulsive need to check the same spreadsheet cell seventeen times in a row. The physical marker was almost entirely invisible. A standard self-report questionnaire rated her anxiety as "low" or "minimal." An ambulatory heart rate monitor during an episode, though, showed her resting rate jumping from 72 to 134 beats per minute. That is not a small feeling. That is a significant physiological event.
The danger here is that quiet attacks get missed. Not just by other people, but often by the person experiencing them. Without the dramatic external feedback loop — the sweat, the shaking, the audible breathing — it is easy to rationalize the episode away. You tell yourself you are just tired, or stressed about one specific thing, or that you are overreacting to a minor inconvenience. You go home and sleep it off. But if these episodes are happening weekly or multiple times a week, the cumulative effect on your nervous system is real. Chronic low-grade activation, even when it feels contained, raises cortisol levels, disrupts sleep architecture, and can lead to burnout or the development of full panic disorder over time. There is also a second category that deserves attention. Some people do not have restricted symptoms — they have what researchers call expected panic, where the attack is tied to a specific trigger they can anticipate. If you know that making a phone call to your insurance company always sets off a seven-minute spike of dread and chest pressure, that is still a panic response. It might not look dramatic. You might sit perfectly still in your car in the parking lot and breathe through it until it passes. But the body is still running a fight-or-flight sequence. The distinction matters because the treatment path for expected panic differs slightly from unexpected or situationally predisposed panic. Exposure-based work, where you gradually and systematically face the avoided trigger, tends to help with expected panic. With truly unexpected attacks, the focus often shifts more toward interoceptive exposure — deliberately inducing the physical sensations so the brain stops interpreting them as catastrophic. Another thing most people do not consider is that quiet anxiety attacks can present as what looks like indecision or perfectionism. I had a client who would spend forty-five minutes staring at a blank document before sending a simple internal memo. Nobody would call that anxiety. They would call him slow or overthinking. But when we mapped it out, each forty-five minute stare session correlated directly with a measurable spike in his galvanic skin response — his body was in a state of high arousal, just directed inward instead of outward. The fix was not time management. It was realizing that the paralysis was a panic response to perceived threat, and treating it as one. Cognitive reframing around the actual likelihood of negative outcomes, paired with a forced time limit on drafts, brought his memo time down from forty-five minutes to about six within three weeks.
If you suspect you are having quiet attacks, the first step is documentation. Keep a simple log for two weeks: note the time of day, what you were doing immediately before, what you felt physically (even subtle things like jaw tension or a flutter in your stomach), how long it lasted, and how intense the subjective distress was on a scale of one to ten. This log does two things. First, it helps you spot patterns that are invisible in the moment. Second, it gives a clinician something concrete to work with instead of a vague description like "I feel anxious sometimes." You do not need a doctor's referral to start basic interventions. Diaphragmatic breathing practiced for five minutes twice a day can lower your baseline arousal over a few weeks. The mechanism is straightforward: slow, controlled exhales stimulate the vagus nerve, which activates the parasympathetic system and counters the sympathetic fight-or-flight response. It is not a cure for underlying anxiety disorders, but it is a functional tool that reduces the intensity and frequency of episodes for a lot of people. Grounding techniques like the 5-4-3-2-1 method can also interrupt the escalation loop during an active episode, pulling your attention away from the internal spiral and back to external sensory input. There are limits to what self-management can do, and it is worth stating them plainly. If your quiet attacks are accompanied by chest pain that radiates, fainting, or shortness of breath that does not resolve within twenty minutes, rule out medical causes first. Cardiac issues and thyroid dysfunction can mimic anxiety symptoms. Once a physician clears those, the next step is typically therapy. Cognitive behavioral therapy has the strongest evidence base for panic and anxiety disorders. Medication is an option some people find helpful, particularly SSRIs for recurrent episodes, but it is not a first-line requirement for everyone. A lot of people with mild to moderate quiet attacks see meaningful improvement with CBT alone within eight to twelve weeks.
Get the Full Details

The broader point is that the absence of visible symptoms does not mean the absence of a problem. The nervous system does not care whether your attack looks scary to other people. It responds the same way whether the panic is internalized or externalized. Recognizing that, tracking it honestly, and addressing it proactively is what separates people who manage to live with quiet attacks from the people who eventually get overwhelmed by them.