The Practical Reality of Treating Anxiety
Most people asking this question have already tried breathing exercises from YouTube and decided they didn't work. That's not because breathing exercises don't work. It's because they're treating the wrong symptom at the wrong time.Can Anxiety Disorder Be Overcome
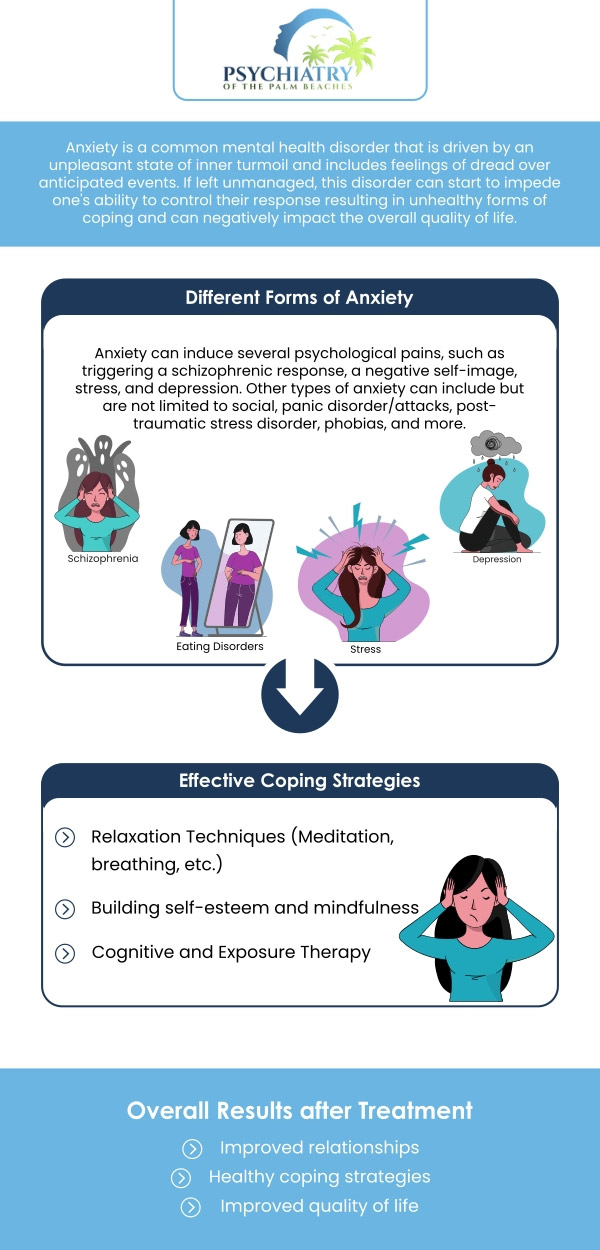
Yes, but the word "overcome" is the problem. It sets up an expectation of total elimination, which rarely happens and often makes things worse when people panic because they're still anxious. The clinical goal isn't eradication. It's reduction to a level where it stops interfering with your life and doesn't hijack your decisions. Most people who do therapy reach that point. Some need maintenance work. A small subset doesn't respond well to first-line treatments and needs something else entirely. The gold standard treatment is CBT, specifically the version that includes exposure work. Not the watered-down self-help books. Actual CBT with a trained therapist who will assign you homework and push back when you're doing it wrong. The mechanism is straightforward: anxiety maintains itself through avoidance. Every time you avoid the thing you're afraid of, your brain files it under "danger confirmed." Exposure breaks that loop by forcing new evidence into the system.
I worked with someone for about eight months who had severe health anxiety. She'd gone to the ER seventeen times in two years for chest pain that was always anxiety-driven. She couldn't get past reading this article because she kept stopping mid-sentence to Google whether chest pain was a heart attack. The standard exposure protocol would've been to have her sit and monitor her heartbeat without checking it for increasing intervals. Instead, I had her do something more specific: she had to write out a 500-word essay describing her worst-case health scenario in vivid detail every single day for two weeks. No distractions. No Googling after. Just the essay. That sounds counterintuitive, but it's called embodied cognitive restructuring. Reading about fear doesn't trigger the physiological response the way actually engaging with the content does. By week four, the essays were half the length because her brain had started losing interest in the scenario. That's extinction learning happening in real time. She's since gone twelve months without an ER visit. Here's what most guides won't tell you about CBT. The therapeutic relationship matters more than the technique, and most people skip past that point. You can have the best protocol in the world, but if you're sitting across from someone who talks down to you or doesn't actually listen, you're wasting six months of your life. I've seen it repeatedly. The fix is usually brutal honesty with your therapist about whether the fit is working, or finding someone else. There's no shame in switching providers.
The medication conversation is separate. SSRIs like sertraline or escitalopram are first-line pharmacological options and they work for a meaningful portion of people. But they're not a cure. They lower the volume on the anxiety signal so therapy can actually be effective. Some people come off them successfully. Some need long-term maintenance. That's not failure. It's like someone needing glasses for their whole life. The analogy is imperfect but the point stands.There's a specific trap with benzodiazepines that almost nobody warns people about properly. Xanax and similar drugs work fast and feel miraculous. They also accelerate tolerance in a way that makes future treatment harder. I had a patient who'd been on clonazepam for three years at a moderate dose and couldn't engage in exposure therapy because the medication was bluntening the emotional learning required for it to work. We tapered her off over four months and restarted CBT. The first six sessions were rougher than they would've been on the benzo, but by session twelve her progress was significantly better than where she'd been stuck for two years. If your doctor prescribes benzos for anxiety, ask them directly about the plan for eventually getting you off them. If they don't have an answer, that's a red flag. Medication side effects are worth taking seriously. Nausea, sexual dysfunction, weight changes, emotional blunting. These aren't minor inconveniences for everyone. If you're experiencing them, don't just suffer through it. Talk to your prescriber about dose adjustments or switching medications. There are at least a dozen SSRIs and SNRIs, and the right one for someone else might be terrible for you and vice versa. Finding the right match usually takes two to four attempts.
The Uncomfortable Parts Nobody Talks About
Lifestyle factors matter less than therapy or medication but more than people admit. Sleep disruption is a massive amplifier. One night of poor sleep can increase amygdala reactivity by roughly sixty percent according to research from the University of Chicago. Not a little bit. Significantly. If you're consistently getting less than six hours or dealing with fragmented sleep, no amount of CBT will work as well as it should.Exercise is genuinely anabolic for your nervous system over time, not just a band-aid. Regular aerobic exercise increases BDNF production, which supports neuroplasticity and makes the learning components of therapy more effective. I'm not talking about joining a gym and suffering through it. I'm talking about twenty minutes of brisk walking five days a week. That's the dosage that shows up in the studies. Anything less has diminishing returns. Anything more beyond that doesn't add much additional benefit for anxiety specifically. Alcohol is worse. It temporarily reduces anxiety through GABA enhancement but creates a rebound effect that's measurably worse than your baseline within forty-eight hours. People who drink to cope with anxiety consistently have worse outcomes than those who don't. This isn't moralizing. It's pharmacology.
Get the Full Details

When Standard Treatment Doesn't Work
About thirty percent of people don't respond adequately to first-line CBT and SSRIs. This is where treatment-resistant anxiety gets interesting and where most guides just say "talk to your doctor" and move on. There are actual options beyond that vague statement.SNRIs like venlafaxine and duloxetine are the next pharmacological step. They affect both serotonin and norepinephrine. For some people the norepinephrine component makes a real difference. For others it makes anxiety worse. You won't know until you try, which is why the trial-and-error process is frustrating but necessary.
Pregabalin is used in Europe as a first-line treatment and hasn't gotten the same traction in the US, though it's gaining ground. It works on calcium channels in the nervous system rather than serotonin, which means a completely different mechanism. Response rates are decent and it works faster than SSRIs, though withdrawal can be unpleasant if stopped abruptly.For people who've tried multiple SSRIs, SNRIs, and therapy without success, TMS (transcranial magnetic stimulation) is an emerging option. It's not FDA-approved specifically for anxiety yet, but it's used off-label and the data is promising. It's also expensive and not covered by all insurers. I've seen it help people who'd given up after three failed medication trials.
Ketamine-assisted therapy is another route that's still being studied but showing early promise for treatment-resistant cases. It's not a routine option yet and shouldn't be dismissed as a trend. The mechanisms are different enough from standard treatments that some people who don't respond to anything else do respond to ketamine. But access is limited, it's expensive, and the long-term data is still incomplete.What Actually Determines Outcomes
The single biggest predictor of whether anxiety treatment works isn't the type of therapy or the medication. It's adherence. People who actually do the exposure exercises, who show up to sessions consistently, who take their medication as prescribed and give it adequate time to work, have significantly better outcomes. The average person drops out of CBT after six to eight sessions. The average course is twelve to twenty. That gap matters more than any treatment modality choice.Another predictor nobody talks about enough is your baseline stress load. If you're in an abusive relationship, working a job that's destroying you, or dealing with chronic financial insecurity, anxiety treatment will be dramatically harder. Therapy can teach you skills, but it can't fix a situation that's actively generating the anxiety. Sometimes the most effective intervention is addressing the environmental source, not just the internal response. That's not a failure of treatment. It's a limitation of what treatment can address.