
Understanding Quiet Panic
Panic attacks aren't always people hyperventilating in public restrooms screaming for help. Some of them look like someone sitting perfectly still on a bench, staring at their phone while their nervous system is firing off every alarm it has at once. I spent years misunderstanding this because the textbooks and media portrayals painted such a narrow picture. The external presentation of a panic attack exists on a spectrum. The classic fight-or-flight response involves visible symptoms: rapid breathing, trembling, pacing. But there's another branch that doesn't fit neatly into that description. It's sometimes called the freeze or collapse response, and it shows up more often in people who've had panic for a long time and learned, consciously or not, to suppress the outward signs.
Can Panic Attacks Look Calm
Yes, absolutely. A person can be experiencing intense internal panic while appearing completely composed to anyone watching. Their heart rate might be climbing past 140 beats per minute. Their hands could be sweating through their pockets. They might feel detached from their own body, like they're watching themselves from three feet away. None of that is visible from the outside if they've trained themselves not to show it. I worked with a client once who was a middle manager at a logistics firm. She would have these episodes right before quarterly reviews. She'd sit in the conference room, nodding at the right moments, asking the right follow-up questions, and internally feeling like her chest was caving in. Her colleagues had no idea. She didn't either, for the most part, because she misattributed the physical sensations to indigestion or lack of sleep for months before connecting the dots. What makes quiet panic particularly tricky is the feedback loop. When you can't see yourself panicking, you miss the external validation that something is wrong. You don't get the chance to say out loud, "I'm having a hard time," because nobody around you would understand. You just keep functioning until you can't, which usually happens in private after the social situation ends.
There's also the interoception problem. Interoception is your ability to sense internal bodily signals. Some people with chronic anxiety actually develop blunted interoception over time. Their nervous system fires the panic signals but their brain stops registering them as significant because the signals became so common. This means they can be in full panic and genuinely not realize it until physical symptoms surface hours later — a headache, nausea, muscle tension that won't release.
Get the Full Details

Identifying the Quiet Version
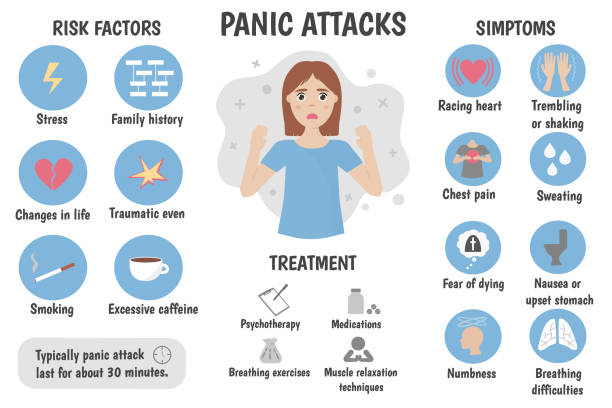
If you're trying to figure out whether what you're experiencing counts as a panic attack despite looking calm externally, here are the internal markers that matter more than outward appearance: A sense of impending doom — not worry about a specific thing, but a raw, unexplained feeling that something terrible is about to happen. This is one of the diagnostic criteria in the DSM-5 and it's remarkably distinct from regular anxiety. Regular anxiety has a cause. Impending doom during a panic episode often has no identifiable trigger. Depersonalization or derealization — the world feeling unreal, or yourself feeling like you're not actually in your body. This is the nervous system's way of trying to protect you from overwhelming arousal by numbing your perception. It sounds dramatic but it's actually a very common symptom during panic, and it can occur without any visible physical manifestation.
Surges of physiological arousal that come and go in waves — panic attacks typically peak within ten minutes. If you notice that your internal state rises sharply, hits a ceiling, and then gradually descends over a relatively short window, that's characteristic of panic. Generalized anxiety tends to build more slowly and stay elevated rather than producing those distinct waves. Specific feared outcomes — during a quiet panic attack, the internal narrative often includes thoughts like "I'm going to pass out," "I'm having a heart attack," or "I'm losing control." These aren't rational assessments. They're the amygdala misfiring and sending false alarms to the prefrontal cortex. One thing I've found that helps people distinguish quiet panic from other states is keeping a simple log. Not a fancy journal. Just note the time, what you were doing, what you felt internally on a scale of one to ten, and any physical sensations. After two or three weeks, patterns usually emerge that make the diagnosis clearer than any single episode ever could.
Why People Learn to Mask It
There are practical reasons panic can look calm, and some of them aren't even about the panic itself. Social conditioning plays a role. People who grew up in environments where showing distress was punished or mocked learn early to compress their reactions inward. This isn't a choice made in the moment of panic. It's a behavioral pattern so deeply ingrained that the masking happens automatically. Certain professions reinforce this. Healthcare workers, teachers, customer service employees — all of these roles reward composure under pressure. I knew a nurse who described having panic attacks in the staff bathroom between patient rounds. She'd splash water on her face, check her reflection to make sure she looked normal, and walk back out. The patients never knew. This isn't unusual in that field. There's also a biological component. Some people naturally have a higher threshold for visible motor output during stress. Their sympathetic nervous system activates the same way, but their motor cortex doesn't translate that activation into visible fidgeting or movement as readily. This variation is normal and it's not something that can be fixed or changed. It's just how their nervous system is wired.
What Actually Helps
The standard breathing exercises you find online tend to be less effective for quiet panic because the person isn't hyperventilating. Their breathing might actually be normal or even slightly shallow without them noticing. So grounding techniques that rely on breath regulation need to be adapted. Temperature change is one of the most reliable interventions for sudden panic regardless of how it presents externally. Splashing cold water on your face, holding an ice cube in your hand, or stepping outside into cold air activates the mammalian dive reflex, which directly stimulates the vagus nerve and forces your parasympathetic system to engage. This isn't a coping strategy you practice daily. It's an emergency brake you pull when the panic is happening now. It works within about thirty seconds for most people. Another technique that specifically addresses the interoception issue is named orienting. You sit somewhere and literally name five things you can see, four things you can touch, three things you can hear, two things you can smell, and one thing you can taste. The point isn't mindfulness or relaxation. The point is forcing your prefrontal cortex to engage with concrete sensory data, which pulls processing away from the amygdala. It sounds simple because it is simple, and that simplicity is why it works when complex cognitive strategies fail during acute panic.
I should mention that medication can be useful here, and I say that without enthusiasm because the medical system tends to overprescribe and under-explain. SSRIs like sertraline or escitalopram are first-line treatments for panic disorder, and they work by gradually raising the threshold at which your nervous system triggers a panic response. The catch is that they take four to six weeks to reach full effect, and they don't help with the actual technique of handling an episode in the moment. They make the episodes less frequent and less intense over time, which is different from teaching you how to ride one out when it hits.
When Quiet Panic Is Misdiagnosed
This is where things get frustrating. People with quiet panic attacks are frequently misdiagnosed with general anxiety disorder, somatic symptom disorder, or even depression. The reason is straightforward: they present for treatment when the episode is over, and by then the most dramatic symptoms have passed. What remains is chronic background worry, fatigue, and a vague sense that something is wrong. Clinicians who don't ask the right questions will fill in the blanks with whatever diagnosis fits the visible symptoms. I've seen this with cardiology patients who get referred for panic after normal cardiac workups. The doctor hears "my chest feels tight and I feel like something bad is going to happen" and thinks heart issue first. When the EKG is clear, the patient is told it's probably anxiety. But the patient wasn't told that what they experienced was a discrete panic attack. They were told they have anxiety. Those are different things, and the distinction matters for treatment. There's also the reverse problem. Some people with panic disorder are told they have a medical condition when they don't. Hyperthyroidism, arrhythmias, and pheochromocytoma can all mimic panic symptoms. A basic workup including thyroid panel, EKG, and blood pressure monitoring should be standard before settling on a panic diagnosis, but it's surprising how often that doesn't happen.

The Limitations
No single intervention works for everyone, and I want to be blunt about that. Grounding techniques require cognitive function that panic temporarily impairs. If you're in the middle of a severe episode with depersonalization, you might not be able to follow a five-four-three-two-one sensory exercise. It sounds condescending to say this, but it's true, and knowing it in advance helps. Having a pre-decided simple action like pressing your thumbs together hard or naming one repeated word can bypass the need for complex cognitive processing during the worst moments. Medication has side effects that aren't trivial. Sexual dysfunction, weight changes, emotional blunting — these are real and they affect quality of life in ways that aren't always discussed upfront. Therapy helps, but finding a therapist who actually understands panic disorder rather than just general anxiety is harder than it should be. Many clinicians are trained in CBT for generalized anxiety and apply it uniformly, which misses the specific mechanisms of panic. The biggest limitation I see in practice is the isolation factor. Quiet panic is lonely because nobody knows it's happening, including sometimes the person experiencing it. Support groups exist for panic disorder, but they tend to attract people with more visibly disruptive symptoms. People who can function during episodes often don't seek out that community, which means they're missing out on the practical knowledge that comes from shared experience.
If you suspect you or someone you know is dealing with quiet panic, the most useful first step isn't a self-diagnosis quiz. It's keeping a symptom log for a couple of weeks and taking it to a qualified clinician. Bring the log. Clinicians respond better to concrete data than to descriptions of internal experience, and the pattern you've documented will do more to get you proper treatment than any conversation about how you felt on a particular Tuesday afternoon.


