The Short Answer
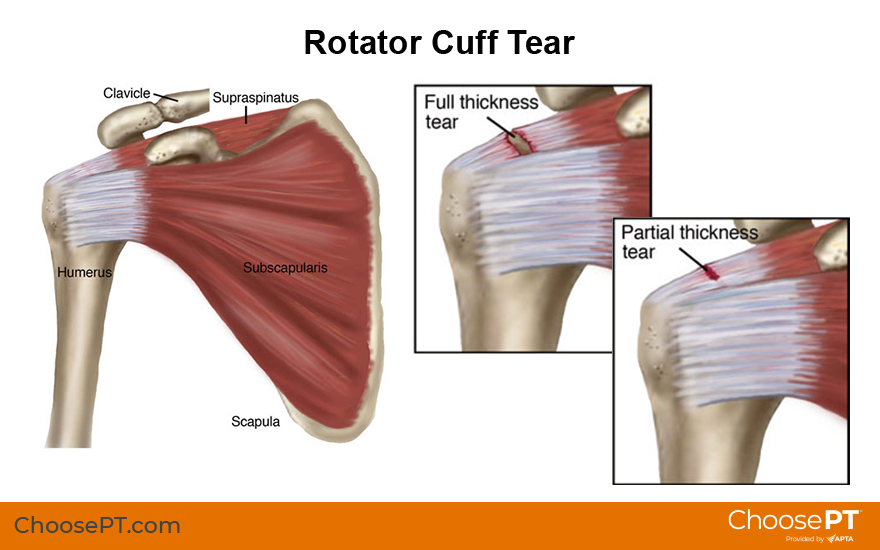
Physical therapy can absolutely make a rotator cuff tear worse, but it usually depends on the type and size of the tear and how aggressive the rehab program gets. Most full-thickness tears that have already degenerated past a certain point won't get better from PT alone. They can get worse if someone starts pushing through pain like it's just soreness from a workout. A small partial-thickness tear might calm down with the right approach. A complete tear with retraction and muscle atrophy just gets more damaged the more you load it without surgical repair. I've seen this play out in clinic after clinic. The most common scenario involves someone who gets diagnosed with a rotator cuff tear — maybe it's a 50-year-old who's been dealing with shoulder pain for six months, or a construction worker who pushed through a sudden pop in his shoulder and thought it would settle down. They get sent to physical therapy, and somewhere around week three or four, things get worse instead of better. This usually happens because the rehab protocol was written for a general rotator cuff tendinopathy case, not an actual tear. The therapist might have progressed them into eccentric loading or resisted external rotation too early. The supraspinatus tendon fibers are already disrupted. Pushing resistance against them before the healing environment is right doesn't strengthen anything. It stretches the tear wider.
What Actually Happens During Rehab
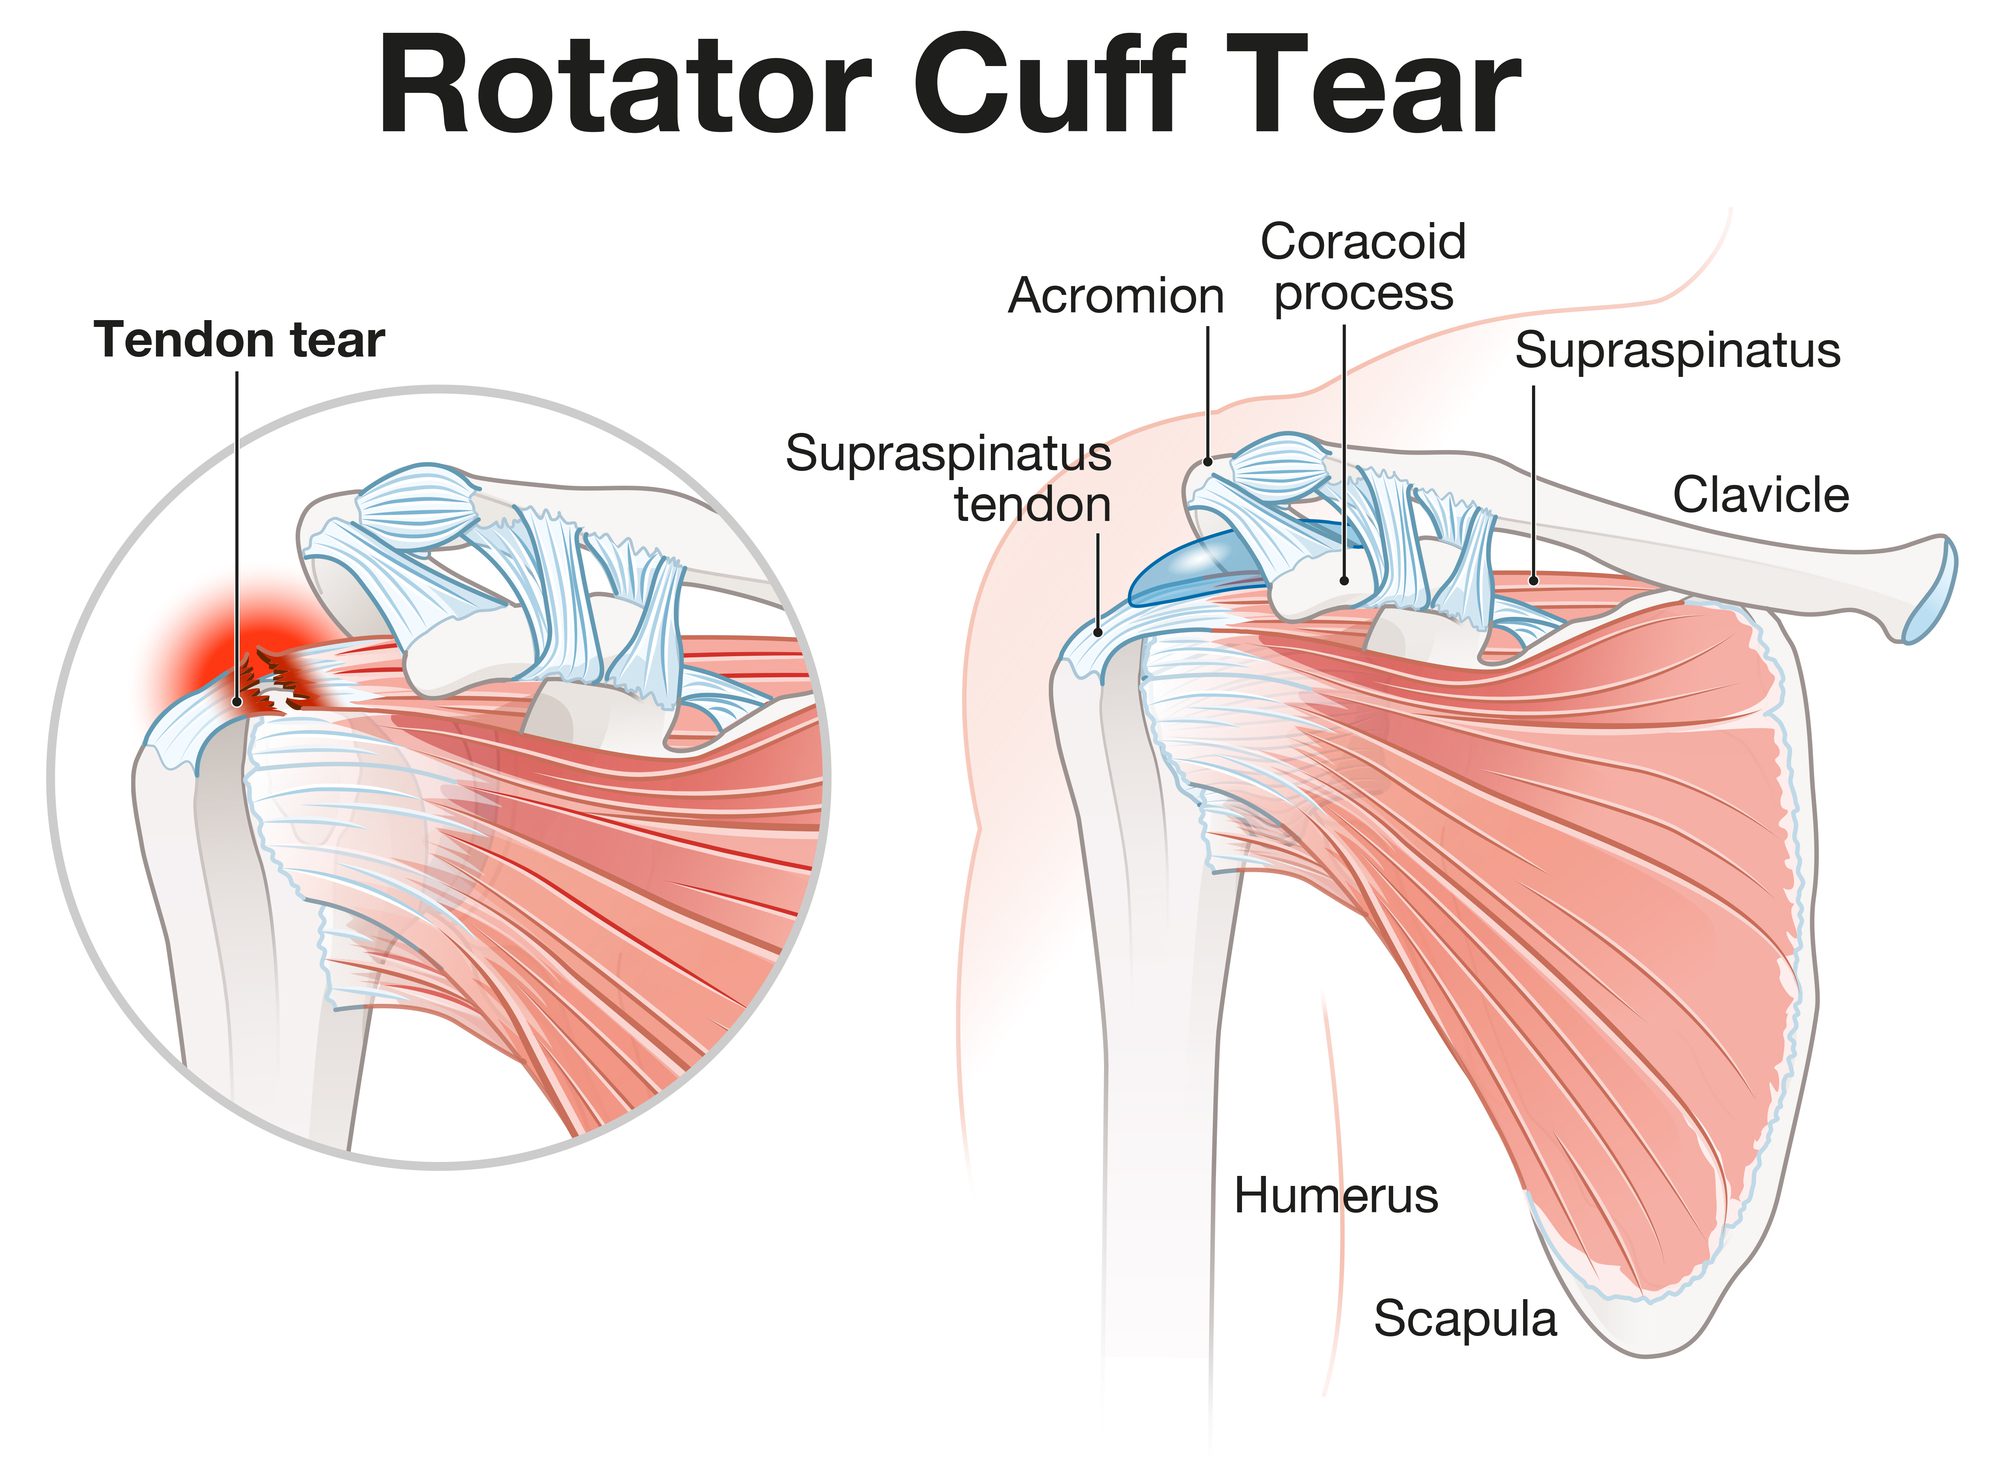
Physical therapy for rotator cuff injuries follows different phases depending on the pathology. Phase one is about protecting the tissue and reducing inflammation. This means no active overhead movement, limited range of motion within a pain-free window, and mostly isometric contractions. Isometrics don't create much tensile load across the torn fibers, so they're relatively safe even when the tear is present. Phase two introduces controlled active range of motion once the acute pain settles. This is where things get tricky. If the tear is large or has progressed to chronic retraction, the shoulder biomechanics change. The humeral head migrates upward because the supraspinatus isn't depressing it properly anymore. The deltoid takes over, but it pulls the arm upward instead of rotating it smoothly. You get impingement. The pain comes back worse than before because the structures are getting pinched differently. Phase three is strengthening. For a repaired cuff, this starts very gently around week six post-op. For a non-operative tear, many programs skip straight to phase two and never come back. The patient ends up doing external rotation with a resistance band, maybe some prone horizontal abduction, and scapular stabilization work. If the tear is large enough, the strengthening doesn't build functional capacity. It just compresses the torn edges against the acromion repeatedly.
Red Flags That PT Is Making It Worse
Not all pain during rehabilitation is bad pain. Some discomfort from tissue irritation is normal, especially early on. But there are signs that the program is crossing the line. Night pain that intensifies rather than gradually improves over four to six weeks is one. Increasing weakness in specific movements, particularly external rotation or overhead reach, is another. A noticeable change in the shoulder's resting position — the arm sitting slightly externally rotated at rest instead of neutral — suggests the tear is progressing. I remember one patient who came to me after completing an eight-week physical therapy program elsewhere for what was diagnosed as a partial-thickness supraspinatus tear. She'd been told the tears heal with conservative care and to just work through the stiffness. By week five, she was doing full resisted external rotation with a Theraband every day. When she showed up at my office, her MRI confirmed the tear had progressed from a 50% thickness defect to a nearly full-thickness tear with about four millimeters of retraction. The therapist had advanced the program aggressively based on a protocol designed for tendinopathy, not a progressive tear. That's not an outlier. It happens regularly in practice.
Get the Full Details
Where PT Actually Helps
Rotator cuff tears don't all behave the same way. A small, chronic, asymptomatic tear found incidentally on an MRI in a 65-year-old often doesn't need aggressive treatment at all. These tears exist in many healthy older adults and frequently stay stable for years. Physical therapy focused on scapular control, postural correction, and maintaining range of motion can help these patients stay functional without any risk of progression. Smaller partial-thickness tears, particularly those under three centimeters without significant retraction, have a reasonable chance of improving with a structured non-operative program. The key is patient selection and appropriate exercise selection. External rotation strengthening is useful only if the tear isn't in the critical zone where the superficial fibers of the supraspinatus insert. If the tear involves the undersurface (articular side), resisted external rotation can worsen it by spreading the fibers apart. Post-operative rehabilitation after rotator cuff repair follows a very different timeline than non-operative management. The repaired tendon needs eight to twelve weeks of protected healing before any meaningful strengthening begins. Pushing into strengthening too early is the most common reason for re-tear after surgery. Studies show re-tear rates climb significantly when patients exceed the prescribed range-of-motion limits in the first six weeks.
What Most People Miss
One thing that comes up repeatedly in my experience is the assumption that pain equals progress. With rotator cuff pathology, that assumption is almost always wrong. Tendons adapt slowly, and inflammation from overloading a torn tendon doesn't lead to strengthening. It leads to increased edema, more pain, and delayed healing. The shoulder responds to appropriate load, not excessive load. There's a narrow window between too little and too much, and it's easy to miss if you're following a generic protocol rather than adjusting based on the patient's actual tissue response. Another thing people overlook is the role of the scapulothoracic rhythm. The rotator cuff doesn't work in isolation. If the serratus anterior and lower trapezius are weak or inhibited, the scapula doesn't rotate properly during overhead movement. The humeral head jams into the acromion regardless of how strong the rotator cuff itself is. Many rehabilitation programs focus almost exclusively on the cuff muscles and neglect scapular control. The patient feels stronger in isolation exercises but continues to have pain during functional overhead activities because the underlying biomechanical issue wasn't addressed. There's also the issue of nerve involvement. A shoulder that feels weak and painful might not have a worsening tear at all. It could be a cervical radiculopathy referring pain to the shoulder, or suprascapular nerve entrapment at the spinoglenoid notch, which causes isolated infraspinatus weakness. I've had patients who were told they needed rotator cuff surgery when the real problem was a C5-C6 disc issue. PT made their symptoms worse because it was targeting the wrong structure entirely.
When to Stop and Reassess
If you've been doing physical therapy for a rotator cuff tear for more than six to eight weeks and you're not seeing any improvement, or if your symptoms are worsening, it's worth getting a re-evaluation. A repeat MRI can show whether the tear has progressed. A consultation with an orthopedic specialist can clarify whether the diagnosis is accurate and whether surgery should be discussed. There's no benefit to continuing a treatment plan that isn't working. The decision between non-operative management and surgical repair depends on several factors: tear size, retraction distance, muscle quality on MRI (fatty infiltration grade), age, activity level, and duration of symptoms. A 45-year-old painter with a two-centimeter full-thickness tear who's failed six months of physical therapy is a very different candidate than a 70-year-old with a small partial tear and mild symptoms. The first may benefit from repair. The second likely won't need one. Physical therapy is a valid treatment option for many rotator cuff problems, but it's not universally beneficial. Knowing when it helps and when it harms requires understanding the underlying pathology rather than applying a one-size-fits-all protocol. If your rehab program is making you worse, that's not a sign to push harder. It's a sign to change the approach.