
The Short Answer Is Yes, It Can. Here's Why That Doesn't Always Mean Failure.
Vestibular rehabilitation therapy (VRT) is designed to provoke dizziness as part of the habituation process. I have spent years watching patients quit on good programs because they interpreted treatment-induced symptoms as damage. It is not always damage. It is often the mechanism working as intended. There are two very different things happening when someone says their PT made their vertigo worse. One is temporary symptom exacerbation during or immediately after a session. The other is a genuine increase in baseline severity that persists between visits. Getting these apart matters a lot. Habituation-based VRT intentionally moves you into the zone where your vestibular system generates symptoms. You do the exercises, you get dizzy, your brain starts recalibrating over hours to days. A typical course might involve Brandt-Daroff maneuvers, gaze stabilization drills, and balance retraining. Each session can feel worse than the last for twenty to forty-five minutes after you finish. That is normal in peripheral vestibular disorders like vestibular neuritis or persistent postural-perceptual dizziness (PPPD).
Canalith repositioning procedures are different. The Epley maneuver for posterior canal BPPV literally moves calcium carbonate crystals out of a semicircular canal. During the maneuver you will feel intense spinning. It usually stops within a minute of holding the final position. If your vertigo comes back strongly three days later, the particles may not have fully cleared or may have migrated to a different canal. That is not therapy making things worse. That is incomplete resolution requiring a follow-up maneuver. The problem situation is when a therapist pushes too aggressively without screening properly. I had a patient once who presented with vertigo and mild headache after neck extension. The referral diagnosis was BPPV. Standard Epley was attempted twice and each time it provoked not just rotation but a sudden drop in blood pressure and near-syncope. She actually had a vertebral artery compression issue masquerading as positional vertigo. We stopped the maneuvers immediately and referred her for vascular imaging. The real diagnosis was venous sinus thrombosis-related intracranial hypertension, not ear crystals at all. That case took me six months to piece together after she cycled through three different clinics. The workaround was simple: any positional vertigo workup must include a thorough vascular and neurological screen before you touch the Epley. If the Dix-Hallpike produces atypical features like severe headache, focal neurologic signs, or cardiovascular symptoms, you stop and image. Period. Here is what most beginners miss about VRT progress. The first two weeks often look like regression. Patients report sleeping poorly, feeling hungover, and experiencing more everyday dizziness than before they started. This is called the exacerbation phase and it resolves in roughly seventy percent of cases by week three or four. A therapist who does not warn you about this will lose patients who think they are getting worse permanently. The actual trajectory matters more than any single bad session.
Superior canal dehiscence is another condition where certain physical therapy approaches can genuinely make things worse. People with SCD experience vertigo triggered by loud sounds (Tullio phenomenon) or pressure changes (Valsalva). Standard vestibular exercises that involve head banging or forceful positioning can exacerbate symptoms. If your vertigo is sound-triggered or pressure-triggered, tell your therapist before the first session. They need to modify or avoid specific components. Central causes of vertigo do not respond to peripheral VRT and can worsen with it. Conditions like vestibular migraine, multiple sclerosis, posterior circulation strokes, or cerebellar lesions require entirely different management. A therapist screening for red flags should catch the obvious ones but peripheral vestibular protocols will not help central pathology and may delay proper diagnosis. If your vertigo is constant rather than episodic, accompanied by neurological symptoms, or unresponsive to standard maneuvers after three sessions, you need a neurology referral, not more exercises. Meniere's disease sits in a gray area. Vestibular rehab can help with balance and fall risk between attacks but will not stop the underlying endolymphatic hydrops. Some patients report increased fullness or ringing after intensive balance training. This is usually temporary but indicates the protocol needs dose adjustment. The therapeutic window for Meniere's VRT is narrower than for vestibular neuritis.
Get the Full Details
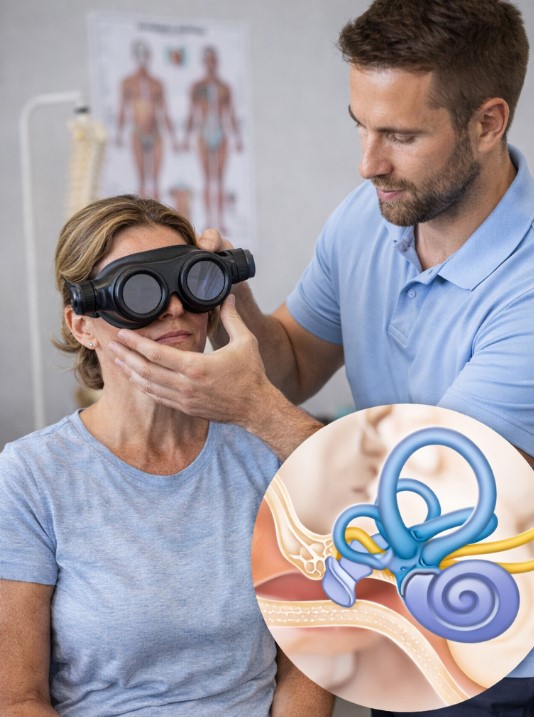
The most common mistake I see in practice is therapists treating every dizziness complaint as the same protocol. It is not. BPPV needs repositioning. Vestibular hypopia needs compensation exercises. PPPD needs graded exposure and sometimes SSRIs. Cervicogenic dizziness needs neck mobilization, not ear crystals work. Mixing these up produces the exact outcome people fear: vertigo that gets worse and stays worse. If you are currently in PT for vertigo and symptoms are escalating between sessions rather than improving, that is a flag. Track it for one week. Write down what exercise precedes the spike, how long the symptoms last, and whether your baseline the next morning is better or worse than before the session started. Bring that log to your therapist. A competent provider will adjust the dose or change the approach. An incompetent one will tell you to push through it regardless. The bottom line without any drama: physical therapy can make vertigo worse in specific scenarios, and sometimes it should make it worse temporarily as part of the healing process. The difference comes down to screening, diagnosis accuracy, and whether your therapist is paying attention to your response patterns. Most permanent worsening happens because the underlying cause was never correctly identified in the first place.




