Understanding Treatment Outcomes in Mental Health
The conversation around whether psychological disorders can be cured is muddled by pop psychology and well-meaning but inaccurate self-help content. The reality is more nuanced than a simple yes or no. I have worked with clinical populations for long enough to know that outcomes vary wildly depending on the disorder, the individual, and the treatment approach used. The word "cured" implies complete elimination of a condition with no possibility of return. That framework works for bacterial infections where antibiotics can eradicate the pathogen entirely. It does not map cleanly onto most psychological conditions. Some disorders do resolve completely. Most require management strategies rather than permanent eradication. Consider specific phobias. Exposure therapy, done correctly, can eliminate the fear response entirely. I had a client with a severe blood-injection-injury phobia who had not seen a doctor in twenty years. We did in vivo exposure over six sessions. The fear was gone. Not managed. Gone. That is a genuine cure in the traditional sense.
Now consider something like major depressive disorder. The relapse rate after a single episode is approximately fifty percent. After two episodes it jumps to seventy percent. After three episodes it approaches ninety percent. This is not a failure of treatment. This is the nature of the condition. Remission is absolutely achievable. Maintenance treatment is often necessary. Calling that a cure would be dishonest. Obsessive-compulsive disorder follows a similar pattern. Cognitive behavioral therapy with exposure and response prevention can produce significant symptom reduction. Some people reach a point where symptoms are no longer clinically significant. Others find that stress, life transitions, or biological changes can trigger a return of symptoms even years later. The tools they learned help them manage it, but the underlying vulnerability remains. Bipolar disorder is perhaps the clearest example where the concept of cure breaks down entirely. It is a chronic biological condition. Mood stabilizers can keep people stable for decades. But stopping medication almost universally leads to relapse. This is not a moral failing or a lack of coping skills. It is the same category of chronic management that diabetes requires. Insulin does not cure diabetes. It manages it. The same logic applies here.
What Actually Works in Practice
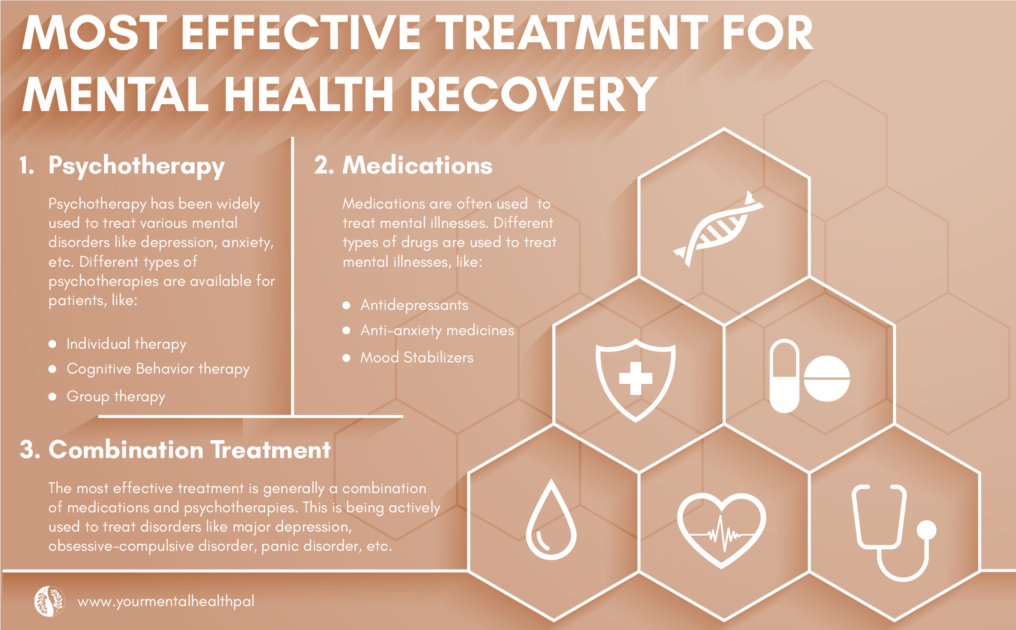
Evidence-based treatments exist for most diagnosed conditions. The problem is not that effective treatments lack evidence. The problem is access, adherence, and matching the right intervention to the right person at the right time. Cognitive behavioral therapy has the strongest evidence base across the widest range of disorders. It is not a panacea. It does not work for everyone. But meta-analyses consistently show moderate to large effect sizes for anxiety disorders, depression, and several personality disorder diagnoses. The average course runs between twelve and twenty sessions for well-defined conditions like panic disorder or social anxiety. Medication matters. It matters significantly for severe depression, bipolar disorder, schizophrenia, and severe OCD. I once worked with a client who had treatment-resistant depression after failing three different SSRIs and two trials of CBT. We added low-dose aripiprazole as an adjunct. Remission happened within eight weeks. That combination would never have occurred with either modality alone. Dismissing medication as a crutch ignores what the literature actually shows.
Get the Full Details

Here is something many people miss about treatment outcomes. The therapeutic alliance accounts for roughly thirty percent of outcome variance across all therapy modalities. That means the relationship between therapist and client matters more than the specific technique being used. A good therapist using a mediocre protocol often outperforms a brilliant therapist using an excellent protocol with a client who does not trust them. This is not controversial in clinical psychology. It is widely ignored in public discourse.
Common Pitfalls in Treatment
One major issue is premature termination. People stop treatment when they feel better rather than completing the full course. This is especially common with depression and anxiety. Symptoms improve within the first few weeks of treatment. The underlying cognitive patterns and behavioral avoidance haven't actually been rewired yet. Stopping at four weeks instead of twelve leaves a significant portion of clients vulnerable to relapse. Another issue is the assumption that medication eliminates the need for therapy. For mild to moderate depression and anxiety, medication and therapy are roughly equivalent in effectiveness. For moderate to severe cases, the combination outperforms either alone. But medication alone does not teach coping skills, challenge distorted thinking patterns, or address behavioral avoidance. Those require active psychological work. There is also the problem of unqualified practitioners. Online therapy platforms have improved access dramatically. They have also created a situation where anyone with a weekend certification can call themselves a therapist. Screening for licensed clinicians with documented training in evidence-based protocols is essential. The difference between a competent CBT therapist and someone who just talks about your childhood is enormous and measurable.
When Treatment Fails
Somewhere between ten and twenty percent of clients with depression do not respond to any first-line treatment. This is treatment-resistant depression and it requires a different approach entirely. Options include switching medication classes, combining medications, transcranial magnetic stimulation, ketamine-assisted therapy, or electroconvulsive therapy. ECT has the highest response rates of any intervention for severe depression, around eighty-five percent. It is also the most stigmatized, largely because of outdated pop culture portrayals. Personality disorders present a different set of challenges. Borderline personality disorder was considered untreatable until Marsha Linehan developed dialectical behavior therapy in the nineteen-eighties. DBT now has solid evidence supporting its efficacy. But it requires significant commitment from both therapist and client. Standard weekly talk therapy is insufficient and can actually worsen outcomes for some clients with BPD. Substance use disorders consistently show the highest relapse rates across all mental health conditions. This is partly because addiction changes brain circuitry related to reward and impulse control in ways that make abstinence fundamentally harder to maintain. Medication-assisted treatment for opioid and alcohol use disorders improves outcomes substantially compared to withdrawal management alone. But they are not cures. They are evidence-based management strategies.

Practical Guidance for Seeking Help
If you or someone you know is dealing with a psychological condition, start by getting an accurate diagnosis from a licensed clinician. Self-diagnosis through internet screenings is unreliable. Many conditions share overlapping symptoms. Anxiety and ADHD look very similar. Bipolar depression is frequently misdiagnosed as unipolar depression. Antidepressants given to someone with undiagnosed bipolar disorder can trigger manic episodes. Ask about the treatment plan before committing. A competent therapist should be able to explain their approach, the expected duration, how progress will be measured, and what the research says about that approach for your specific concern. If they cannot or will not provide this information, find someone else. Track your symptoms objectively. Use standardized measures like the PHQ-9 for depression or the GAD-7 for anxiety. Take them every two to four weeks during treatment. This gives you and your therapist concrete data on whether the intervention is working. Subjective impressions of progress are unreliable. Two weeks feels like a long time when you are depressed. Four months feels like yesterday. Numbers don't lie.
Understanding whether Can Psychological Disorders Be Cured requires abandoning the binary thinking that drives most of this conversation. Some conditions resolve permanently. Most improve significantly with the right treatment. Some require lifelong management strategies. All of these outcomes are valid. None of them reflect personal failure. The goal should not be cure. The goal should be functioning. Quality of life. Reduced suffering. Those are measurable, achievable targets regardless of where a condition falls on the spectrum from acute to chronic.