Chronic Anxiety Without Panic: What It Actually Looks Like
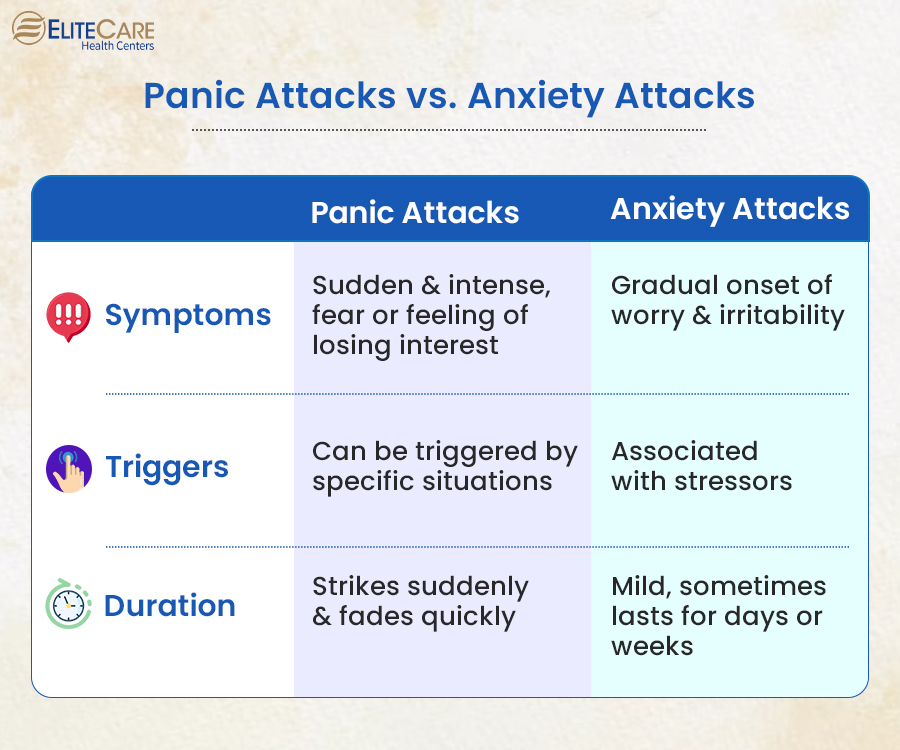
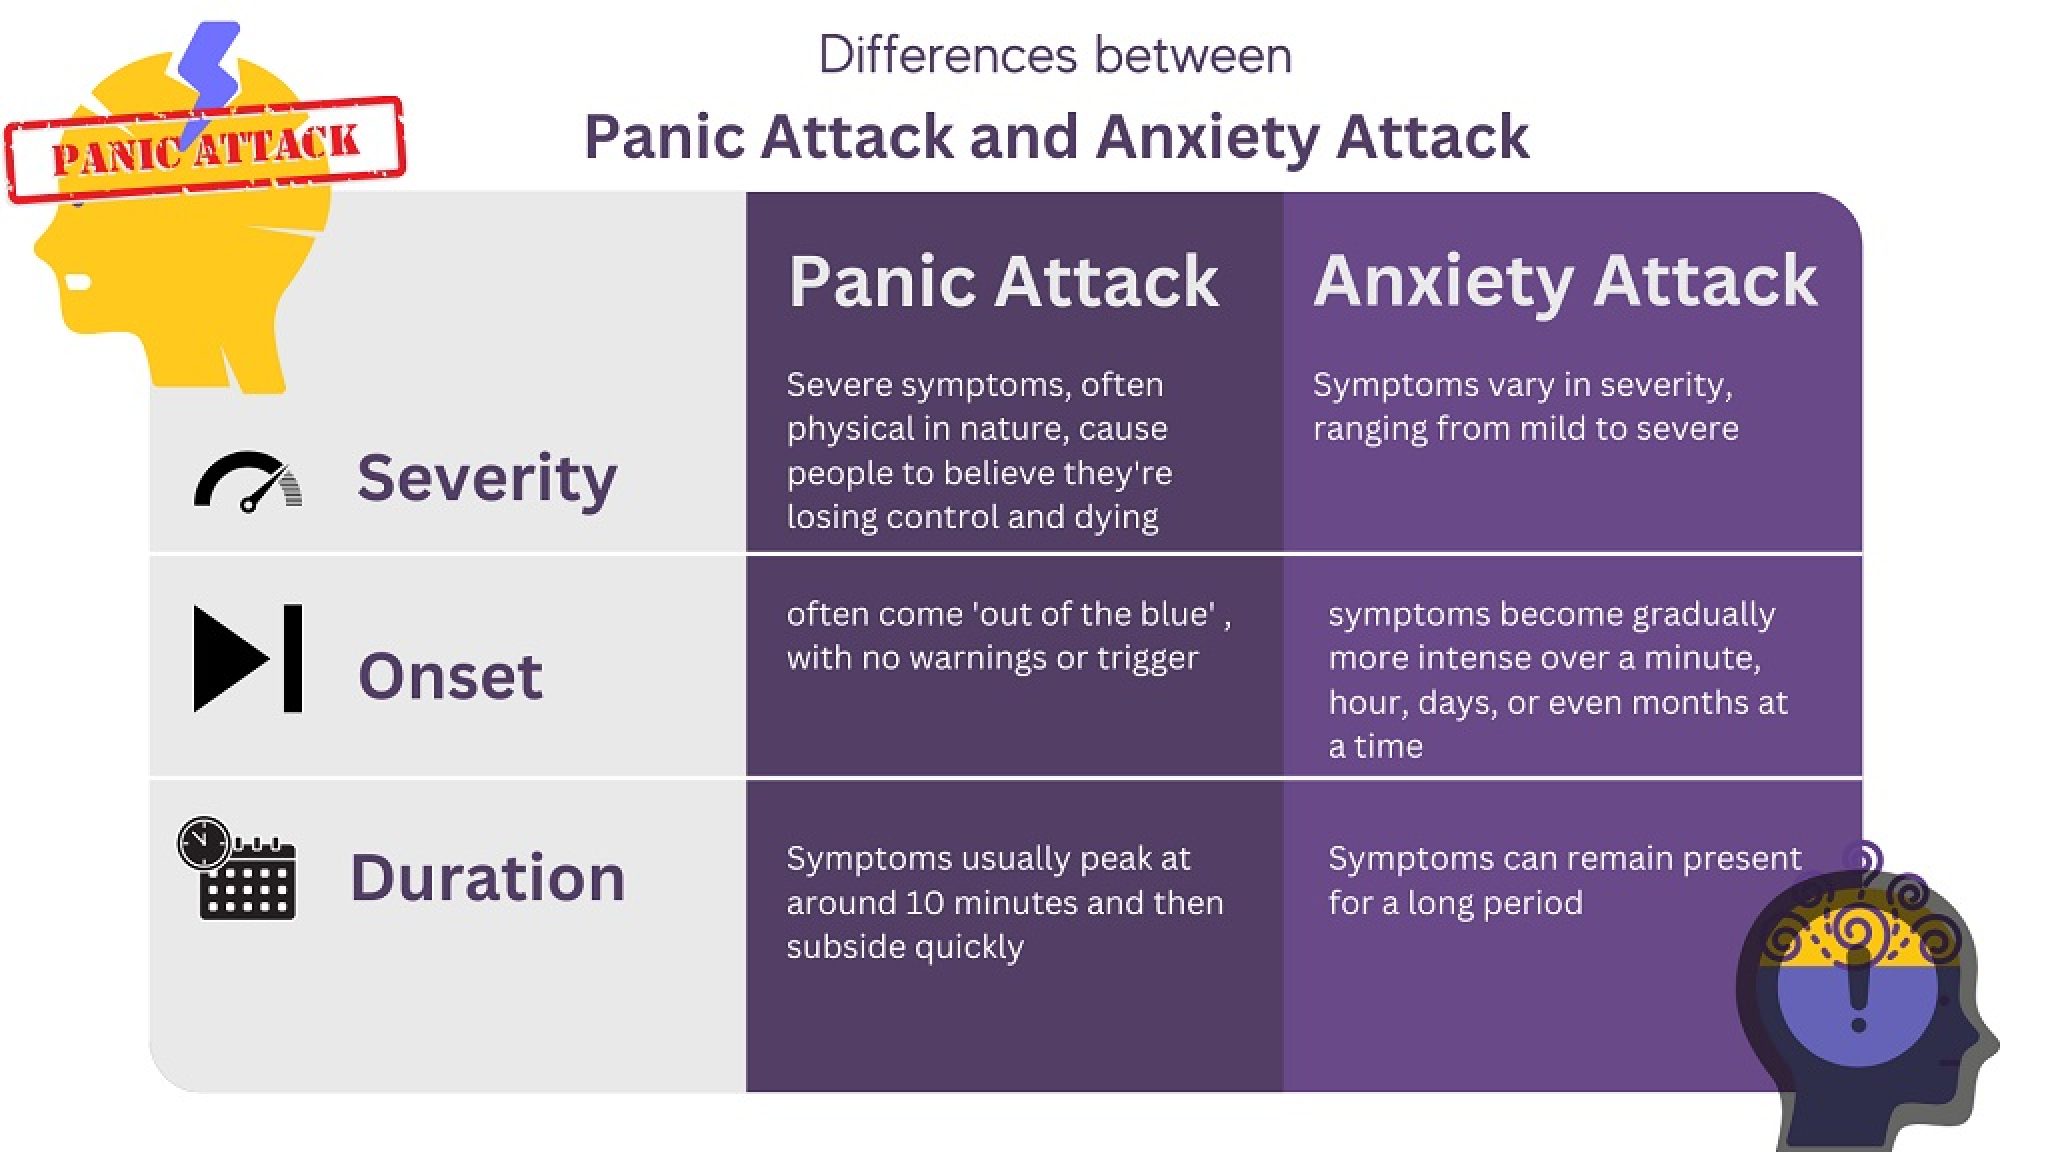
The clinical distinction between generalized anxiety and panic disorder isn't as clear-cut as most patient handouts suggest. You can absolutely have severe anxiety without ever experiencing a full-blown panic attack. I've worked with enough people in this space to tell you that the DSM criteria for GAD don't require panic attacks, and having them doesn't automatically mean you have panic disorder either. They're separate mechanisms that sometimes overlap and sometimes don't. Yes, it's completely possible and actually more common than most people realize. Severe generalized anxiety means your baseline stress response is chronically elevated. Your sympathetic nervous system is stuck in the "on" position, but that's not the same thing as panic. Panic is a sudden surge — a discrete event where your body thinks it's dying right now. Generalized anxiety is a background hum that never goes away. It's exhausting in a different way. One is a thunderstorm, the other is living in a place where the air is always slightly too thin. I spent several years helping people manage chronic anxiety before I ever encountered someone with severe GAD who'd never had a panic episode. What was striking about that case was how much functional impairment they had without meeting panic criteria. They couldn't sleep past 4 AM. Their shoulders were permanently knotted. They avoided social situations not because they feared losing control, but because the effort of being around people felt like wading through wet concrete. Standard panic-focused protocols didn't map onto their experience well at all.
The neurobiology here is worth noting. Anxiety and panic use overlapping circuitry — the amygdala, the locus coeruleus, the hypothalamic-pituitary-adrenal axis — but the temporal patterns differ. Anxiety tends to involve sustained elevation of cortisol and norepinephrine. Panic involves a sharp, acute burst of noradrenergic firing from the locus coeruleus, often without the prolonged cortisol elevation. That's why someone can feel chronically wired for months and never cross into panic territory. The threshold for that sudden noradrenergic spike varies from person to person and is influenced by things like sleep architecture, caffeine sensitivity, and whether they've had prior trauma responses that sensitize the acute fear circuit.
How It Manifests in Real Life
Severe anxiety without panic tends to show up as persistent physical symptoms and cognitive overload rather than sudden episodes. People describe it as feeling like they're always bracing for something they can't identify. The body stays in a low-grade fight-or-flight state. Heart rate is elevated but stable. Muscle tension is constant. Digestion becomes unreliable. Sleep is fragmented rather than absent. What I've observed repeatedly is that these patients often get misdiagnosed or told their symptoms are "just stress" because there's no dramatic event to point to. A panic attack is something both the person and the doctor can point at. Chronic severe anxiety doesn't offer that visual proof. It just looks like someone who is always tense, which people dismiss as personality or poor lifestyle choices. The cognitive symptoms tend to be different too. Instead of the catastrophic thinking that accompanies panic, severe generalized anxiety produces what clinicians call anticipatory anxiety — a constant forward-looking worry that everything will go wrong. Decision-making becomes paralyzing not because of fear of failure in the moment, but because the brain can't settle on any option without simulating every possible negative outcome first. This is why some people with severe GAD become what I'd call decision-fatigued at a fundamental level. Simple choices like what to eat or what to wear can take twenty minutes because the anxiety system is flagging every option as potentially dangerous.
Get the Full Details

Working With It: What Actually Helps
The standard first-line approaches for severe generalized anxiety without panic tend to be SSRIs or SNRIs, cognitive behavioral therapy adapted for GAD, and lifestyle modifications. But the nuance matters a lot here. Standard CBT protocols that focus on cognitive restructuring around catastrophic thoughts work okay for mild cases. For severe chronic anxiety, the evidence tends to support approaches that target the physiological baseline rather than just the thoughts. I found that acceptance and commitment therapy approaches, combined with somatic interventions, tend to produce more durable results for this presentation than pure thought-challenging. The reason is straightforward. When your nervous system is chronically activated, telling yourself "this thought isn't rational" doesn't reach the right level of the brain. You're trying to use the prefrontal cortex to modulate a system that has effectively gone rogue at the brainstem and hypothalamic level. Specifically, I've had good outcomes with protocols that combine vagal tone building — things like slow diaphragmatic breathing at around six breaths per minute, cold exposure, and regular low-intensity exercise — alongside the psychological work. The physiological regulation needs to happen first or simultaneously. Without it, the psychological interventions hit a ceiling. I've watched capable people spend months doing cognitive work that only produced marginal improvement because their baseline arousal was too high for the therapy to take hold effectively.
One thing I want to flag that isn't commonly discussed: benzodiazepines tend to be counterproductive for this presentation when used long-term. They can blunt the acute symptoms, but they disrupt sleep architecture in a way that often worsens the underlying anxiety over time. The rebound effect between doses is also significant. For someone with chronic severe anxiety, this creates a cycle where the medication manages the surface symptoms while the underlying dysregulation gets worse. I've seen this pattern play out repeatedly. Buspirone or hydroxyzine are often better options for the pharmacological side when medication is needed, though neither is a magic solution.
When It's Not Just Anxiety
Before settling on a GAD diagnosis, it's worth ruling out a few medical conditions that mimic chronic severe anxiety. Hyperthyroidism is the classic one. Pheochromocytoma is rare but produces nearly identical symptoms. Sleep apnea can manifest primarily as anxiety rather than obvious sleepiness. Caffeine sensitivity develops or worsens over time for some people and presents exactly like anxiety disorder. I once worked with someone who had been treated for severe GAD for three years with minimal improvement before we discovered they had undiagnosed sleep apnea. Their anxiety was a secondary symptom of chronic intermittent hypoxia and fragmented sleep. Treating the apnea with CPAP resolved about sixty percent of their symptoms within weeks. This is why basic medical workup matters before committing to a psychiatric treatment plan, especially when the presentation doesn't include panic attacks.
What to Expect Long-Term
Severe anxiety without panic tends to be more chronic and less episodic than anxiety with panic. The flip side is that it also tends to respond more slowly to treatment. People sometimes get discouraged because they don't experience the dramatic shifts that come with panic treatment, where avoiding one feared situation can produce noticeable improvement quickly. With GAD, progress is usually measured in small increments over months rather than weeks. The realistic trajectory involves learning to live with a higher baseline than most people have, developing tools to prevent escalation, and accepting that complete remission isn't always achievable. Some people do reach a point where symptoms are manageable and don't significantly impair their life. Others find that even with treatment, they carry a noticeable level of anxiety into adulthood. Neither outcome is unusual, and neither is a failure of the person or the treatment.