What Happens When the Pancreas Goes
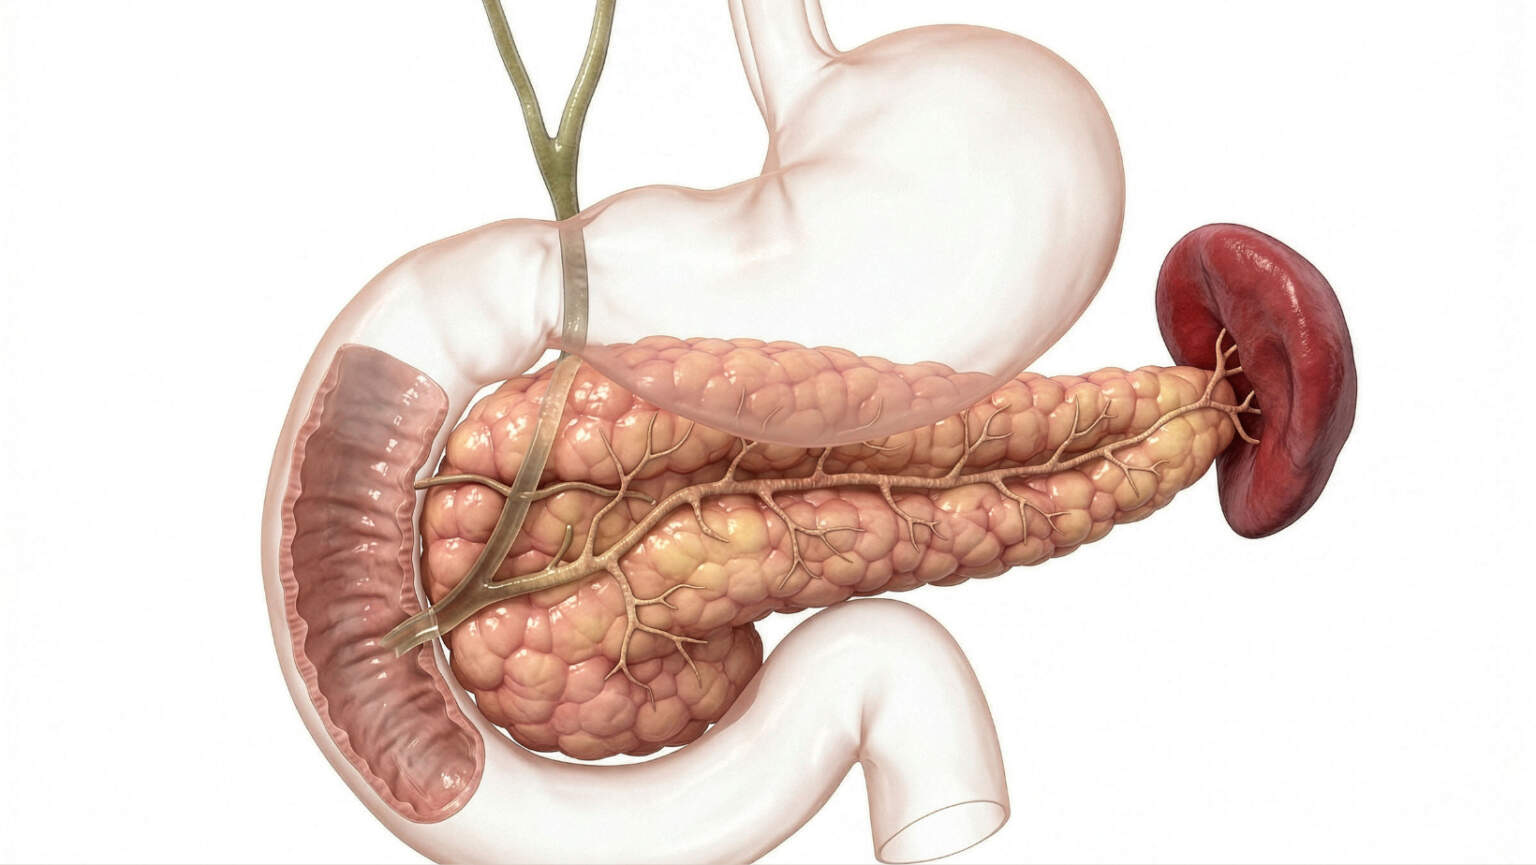
The pancreas does two jobs: it makes digestive enzymes that break down food, and it produces hormones like insulin and glucagon that control blood sugar. Take it out and both systems break. People absolutely live without it, but the rest of their life looks very different. It is not a simple switch you flip off. The short answer is yes. The longer answer involves insulin injections, prescription enzymes with every meal, and a level of daily logistics that most people never have to think about. Some patients do fine for years. Others struggle with brittle diabetes or recurrent digestive problems. The outcome depends heavily on why the organ was removed, what exactly was taken, and how closely the patient can stick to a rigid routine. Total pancreatectomy is rare. Most removals are partial. A Whipple procedure takes the head of the pancreas, part of the small intestine, the gallbladder, and sometimes part of the stomach. A distal pancreatectomy removes the tail and body. The spleen often comes along for the ride with distal procedures. Each variation changes the hormonal and digestive hit you take.
I dealt with a case where a patient had a total pancreatectomy for chronic pancreatitis and then kept having severe hypoglycemic episodes despite what seemed like a solid insulin regimen. The issue was that without a pancreas you also lose the alpha cells that produce glucagon. Most people do not realize how much glucagon matters when blood sugar drops. Insulin brings glucose down. Glucagon brings it back up. Remove the source of both and you lose the natural safety net. The workaround was switching to an insulin pump with continuous glucose monitoring and setting up automated correction boluses with glucagon nasal spray on standby. It cut the hospital visits from about four per month down to one. Not perfect, but manageable.
How the Body Adapts
After surgery the immediate concern is usually bleeding, infection, or a pancreatic fistula where digestive enzymes leak into the abdomen. Those are surgical risks that happen in the first few weeks. Long term, the body has to cope with exocrine and endocrine insufficiency. Exocrine insufficiency means your gut cannot properly digest fat, protein, and carbohydrates. You will lose weight, get diarrhea, and miss fat-soluble vitamins unless you take pancreatin capsules with every meal and snack. The standard starting dose is around 40,000 to 50,000 lipase units per main meal, split between the beginning and middle of eating. Some people need more. You adjust based on stool consistency and weight stabilization. Endocrine insufficiency means type 3c diabetes, also called pancreatogenic diabetes. It is different from type 1 and type 2. Type 3c diabetes often comes with fragile blood sugar swings because you lack both insulin and glucagon. Oral medications like metformin rarely help much. Insulin is usually necessary from day one after a total pancreatectomy. Some patients with partial removals can manage with diet alone at first, but many eventually need insulin as the remaining tissue struggles under the new demand.
Get the Full Details
What Daily Life Looks Like
Food becomes a calculation. Every meal requires enzyme dosing. Blood sugar needs checking multiple times a day. Skipping an enzyme capsule with a high-fat meal usually means urgent bathroom trips and cramping within an hour. Missing insulin is not a minor inconvenience either. Blood sugar can spike quickly and stay there. Hospitalization after total pancreatectomy typically runs five to ten days if recovery goes smoothly. Return to normal activities usually takes four to eight weeks. Long term, most patients settle into a routine that involves finger sticks or CGM checks, multiple daily injections or pump management, and enzymes with every eating event. Life expectancy after total pancreatectomy for benign disease is reasonably good if diabetes is managed well. The real killer is usually the underlying condition that required the surgery in the first place, not the absence of the organ itself. One thing people miss is the vaccine schedule. Without a spleen, which happens frequently with distal pancreatectomy, you are vulnerable to encapsulated bacteria. Pneumococcal, meningococcal, and Haemophilus influenzae type B vaccines are mandatory. I had a patient who skipped the annual flu shot and ended up in the ICU with streptococcal pneumonia. It was preventable. Get the vaccines and keep them updated.
Common Pitfalls
The biggest mistake patients make is under-dosing enzymes. Many think one capsule with a meal is enough. It is not. The enzymes need to mix with the food, so taking them mid-meal matters. Another pitfall is assuming type 3c diabetes behaves like type 2. It does not. Metformin and sulfonylureas often cause more harm than help in these patients because they do not address the underlying hormone deficiency and can worsen hypoglycemia. Some surgeons will attempt islet cell autotransplantation during pancreatectomy for chronic pancreatitis. The idea is to harvest the patient's own islet cells and infuse them into the liver after removal. It works sometimes. The cells engraft and produce enough insulin to reduce or eliminate the need for injections. But it is not reliable. Success rates vary widely across centers, and even when it works, the islets can decline over time. Do not view it as a guaranteed fix. It is a gamble with variable returns.
Monitoring and Follow-Up
Bone density testing is important after total pancreatectomy. Malabsorption of vitamin D and calcium leads to osteopenia faster than most people expect. I recommend a DEXA scan within the first year and then every two years. Magnesium and B12 levels also tend to run low. Regular lipid panels matter too since fat malabsorption can skew cholesterol readings in unexpected ways. Dental health gets overlooked. Chronic pancreatitis and diabetes both increase gum disease risk. Enzyme replacement can alter the oral environment slightly. Routine cleanings every six months are worthwhile.
When It Does Not Work
There are scenarios where living without a pancreas becomes dangerously difficult. Patients who cannot afford enzymes or insulin will degrade quickly. The medication costs are substantial. Enzymes run several hundred dollars a month without insurance. Insulin and supplies add another chunk. Financial assistance programs exist through pharmaceutical manufacturers and nonprofit organizations, but navigating them takes time most sick people do not have. Polypharmacy is another real issue. Patients often end up on insulin, enzymes, vitamin supplements, bone health medications, and sometimes antibiotics for bacterial overgrowth. That is a lot of pills and injections for one person to manage. Cognitive decline or dementia makes this nearly impossible. In those cases, the quality of life after pancreatectomy can be worse than if the surgery had been avoided. Psychological adjustment is real too. The constant vigilance required creates a background anxiety that does not go away. Some patients develop diabetes distress, which is different from clinical depression but just as impairing. Support groups help, but they are not available everywhere. Online forums and patient advocacy organizations are the next best thing.
The Bottom Line
Living without a pancreas is possible. It requires discipline, resources, and regular medical follow-up. The medical community has workable protocols, but they are not forgiving of slipups. The people who do best are those who treat their new regimen like a full-time job. Those who try to eyeball it usually pay for it in emergencies.