
Documenting Cannabis-Induced Psychosis: A Clinical Template
The form most people use for a Cannabis Induced Psychosis Case Study is either too vague to be useful or so dense with checkboxes that clinicians waste more time filling it out than they do reviewing the actual case. What follows is a working template built from cases I have seen repeatedly over the years. It strips out the filler and focuses on what actually changes outcomes. I start every case by locking down the substance timeline before touching the psychiatric history. A patient presenting with acute psychosis after heavy cannabis use can look identical to someone with first-episode schizophrenia. The difference almost always hides in the timeline, not the symptom profile. Here is the section that catches that. Cannabis Use History (fill this completely)
Frequency of use: daily | weekly | occasional Potency: average THC content (lab result or patient estimate, e.g., 12%, 24%) Route of administration: smoked | vaped | edible | other
Duration of current pattern: years Last use before symptom onset: hours ago | days ago | weeks ago Previous attempts to stop: yes | no
Get the Full Details

History of cannabis withdrawal: yes | no This might seem like basic intake data, but most cases I reviewed had zero lab-verified THC data. Patients routinely misestimate potency by a factor of two or three. If you are writing a formal case study, request a urine toxicology screen with THC-COOH and a blood test for active THC. The half-life of THC in chronic users is roughly 25 to 66 hours. Blood levels drop below detection faster than urine metabolites. This gap matters when determining whether symptoms are substance-induced versus an independent psychotic episode.
Symptom Onset and Trajectory
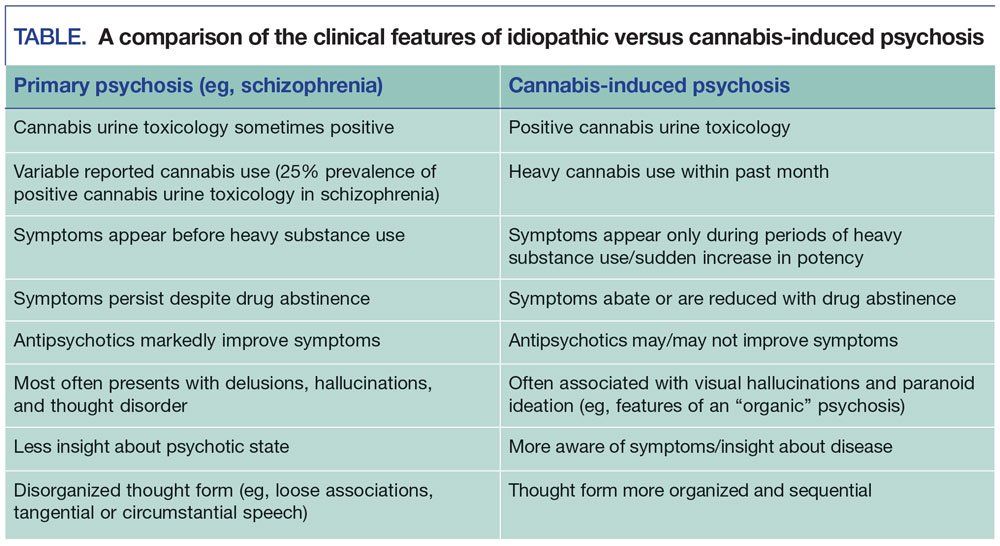
Document the exact moment the patient or a witness noticed the first psychotic feature. Was it paranoia first? Auditory hallucinations? Disorganized speech? Visual hallucinations are less common with cannabis alone. When they appear prominently, you should consider an alternative or comorbid cause. The duration of acute symptoms is the next critical variable. In a true cannabis-induced presentation, positive psychotic symptoms usually peak within 24 to 72 hours after last use and then plateau. I had one case where a 22-year-old male presented with visual hallucinations and paranoia that never resolved after three weeks of abstinence. He had been smoking a product labeled as high-THC hemp. Lab testing revealed synthetic cannabinoid contamination. The presentation mimicked cannabis-induced psychosis but was caused by a different receptor agonist entirely. This is why the substance confirmation step is not optional. Symptom checklist
Paranoid delusions: present | absent Auditory hallucinations: present | absent Visual hallucinations: present | absent
Disorganized thinking: present | absent Akathisia or agitation: present | absent Cognitive blunting: present | absent
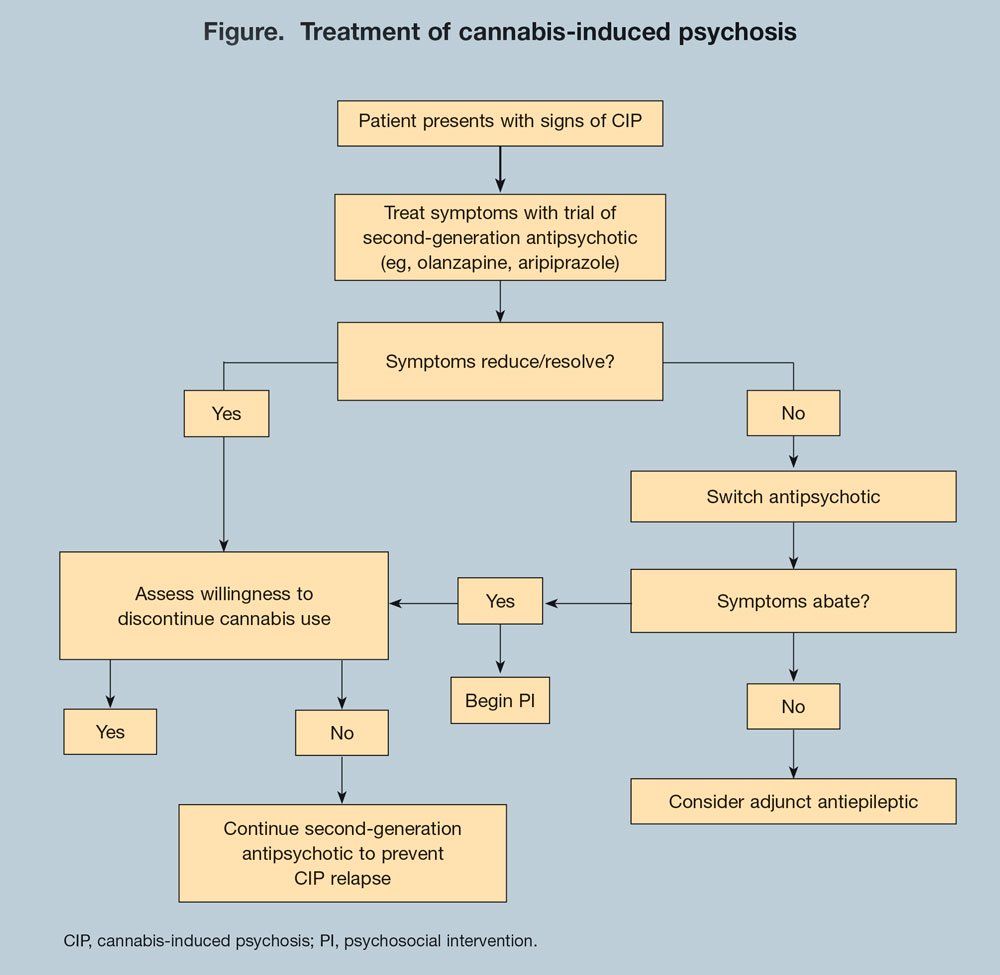
Note akathisia separately. It is frequently misread as worsening psychosis when it is actually a side effect of antipsychotics prescribed during the initial stabilization phase. I switched one patient from haloperidol to quetiapine specifically because the akathisia was obscuring the true psychosis trajectory. That decision came from watching the same presentation happen repeatedly with the wrong medication choice.
Assessment Tools to Include
The PANSS or BPRS gives you a baseline score. Use whichever you are already trained on. The scale matters less than consistency. Record the score at admission, at 72 hours, and at discharge. This lets you separate drug-induced symptom resolution from spontaneous fluctuation. Also add a simple CIWA or CAGE screening for alcohol or other substances. Poly-substance use changes everything. I have seen multiple case reports skip this step and later get pulled apart during peer review because the patient was also using stimulants. Stimulant-induced psychosis and cannabis-induced psychosis can overlap in presentation but require different management windows.

Course and Resolution
Most cannabis-induced psychotic symptoms resolve within two to four weeks of sustained abstinence. Some resolve faster. Some do not resolve at all, and the patient meets criteria for a primary psychotic disorder afterward. Your case study needs to track this transition carefully. Write it as a timeline, not a paragraph. Week 1: Active psychosis. Antipsychotic started or adjusted. Week 2: Symptom reduction noted. PANSS change recorded.
Week 3: Further reduction or plateau. Determine trajectory. Week 4: Discharge status. Return to baseline functioning or residual symptoms. If the patient still meets full criteria for a psychotic disorder at four weeks post-abstinence, you should note that explicitly. The DSM-5 specifier for substance-induced psychotic disorder requires that symptoms do not persist for a substantial period after cessation. Four weeks is a commonly used cutoff in research. Some clinicians extend to eight weeks for heavy chronic users. Pick one and state it upfront.
Common Pitfall: Mislabeling a Vulnerability Event
Here is where most case studies go wrong. Cannabis often unmasks an underlying vulnerability rather than causing psychosis de novo. A patient with a family history of schizophrenia or a personal history of subtle prodromal symptoms may develop acute psychosis after cannabis use. Labeling this purely as cannabis-induced without addressing the vulnerability is incomplete and potentially misleading. I keep a single line in every chart: "Primary psychotic disorder vs. substance-induced psychosis. Uncertain at this time. Reassess at week four." That uncertainty is honest. The alternative is a false certainty that makes the case study weaker, not stronger.
Genetic and Biological Notes
If your institution allows access to pharmacogenomic data, including COMT and AKT1 genotype results strengthens the case significantly. The COMT Val158Met polymorphism affects dopamine breakdown in the prefrontal cortex. Heavy cannabis use in carriers of the Met allele has been associated with higher risk of psychosis onset. You do not need this data to diagnose. You do need it if you want to explain inter-individual variability in the case study. Write a concrete plan. Vague discharge instructions are the reason some of these cases recur. Specify the abstinence target, the follow-up appointment date, and the early warning signs the patient should report. Most relapses happen within the first three months. That is the window that matters. I also recommend adding a brief section on patient education provided. Did you explain THC potency? Did you discuss the difference between medical and recreational product labeling? Did you address the possibility of persistent vulnerability? These details are often skipped but they make the case study reproducible.
Limitations of This Approach
This template works well for acute presentations in controlled settings. It breaks down for patients who continue using while being treated. It also struggles with cases involving synthetic cannabinoids, where the timeline is unpredictable and standard detox protocols do not apply reliably. Synthetic cannabinoid cases often require longer observation and higher antipsychotic doses than natural cannabis cases. If your patient used a synthetic product, note that separately and consider consulting toxicology before finalizing the discharge plan. The data you collect here is only as good as what the patient reports and what the lab confirms. Self-report is unreliable under acute psychosis. Cross-reference everything you can with collateral sources before writing the final version. A case study built on unverified self-report gets rejected during review, and the author looks careless rather than rigorous.

