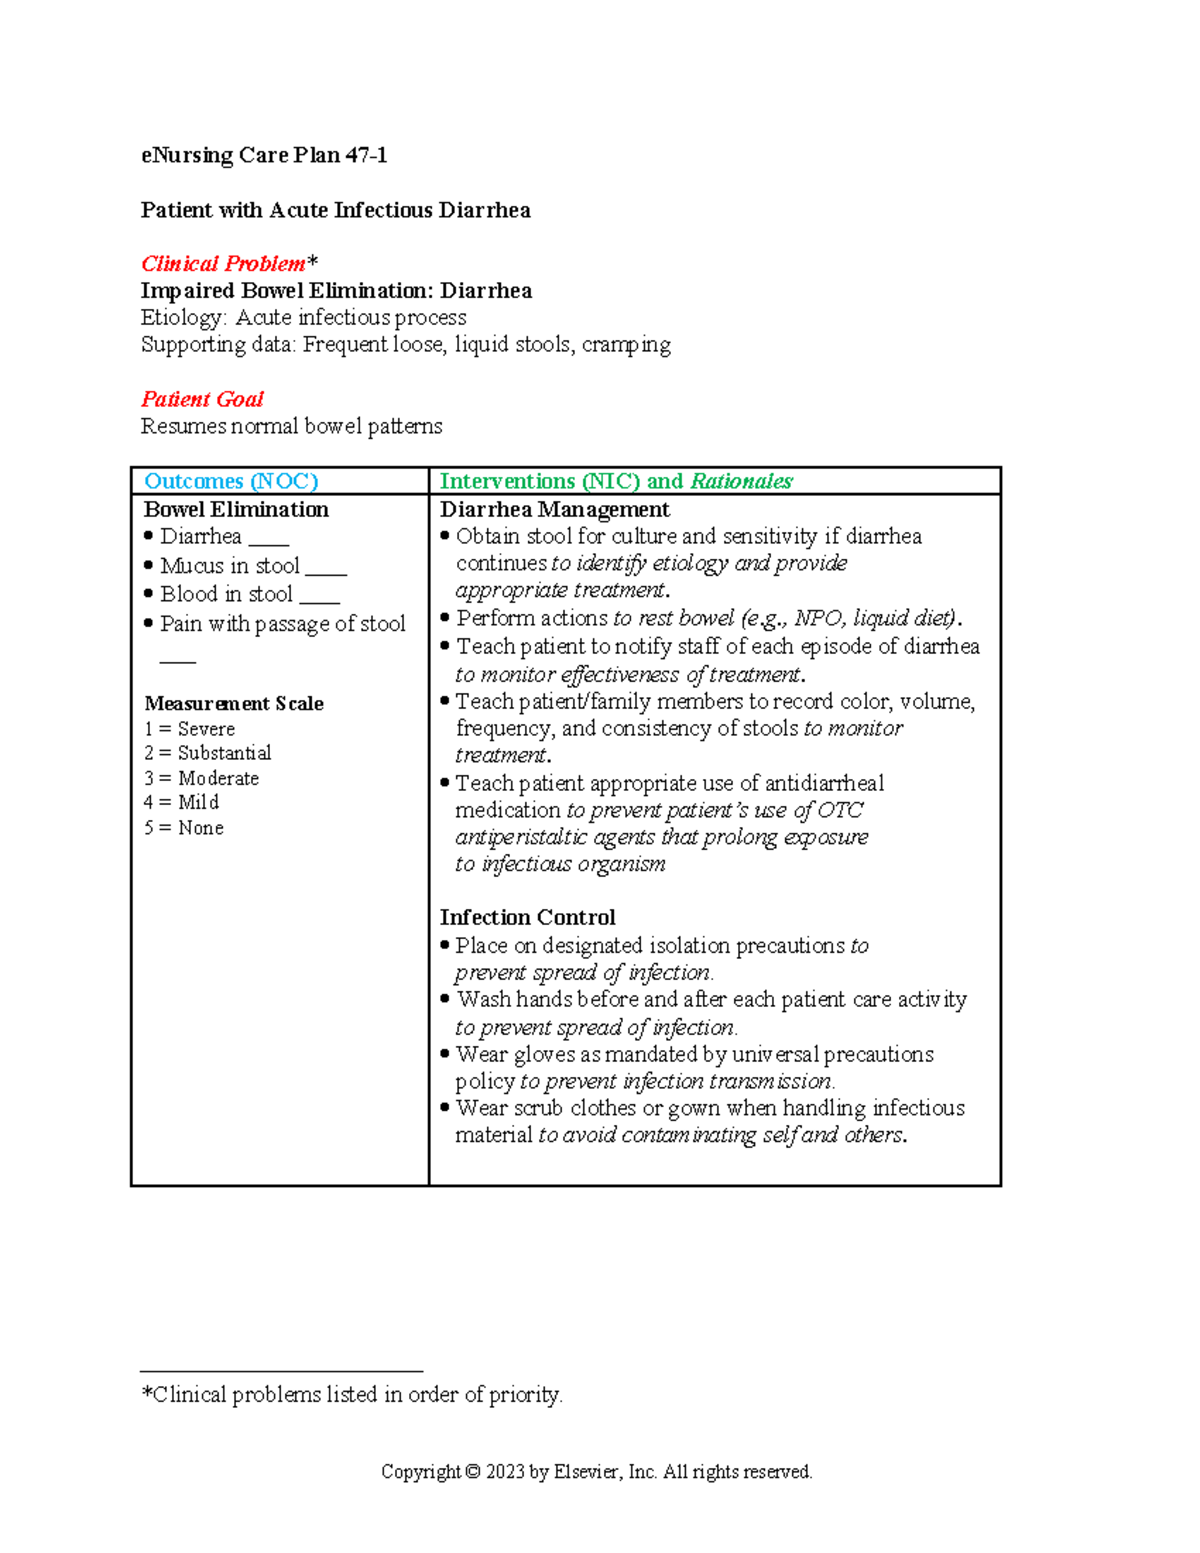
Oral Rehydration First, Everything Else Second
Diarrhoea care isn't complicated when you strip away the noise. The single most important intervention is fluid and electrolyte replacement. Everything else is secondary. I have watched colleagues agonize over antiproliferative agents and anti-motility drugs while a patient sits on the edge of a bed with a half-empty IV bag, and it makes my head hurt every time. Before you start documenting a Care Plan Of Diarrhoea, get these data points first. I cannot stress this enough. Assessment comes before intervention in actual clinical practice, even though textbooks sometimes present it the other way around. You need a weight. Not an estimate. Actual current weight if possible. This determines your rehydration volume calculations and maintenance fluid requirements. A 70kg adult needs something fundamentally different from a 7kg infant, and guessing at weight will give you dangerous fluid calculations. Check this at least once during the illness trajectory because ongoing losses can shift body weight measurably within 24 hours.
Document stool characteristics. Frequency, volume estimates, color, consistency. Is there blood? Mucus? Foul odor? These details separate simple viral gastroenteritis from dysentery, Clostridium difficile infection, or inflammatory bowel disease flare. I once prescribed a standard rehydration protocol for a patient presenting with what was documented as "diarrhea" and missed the underlying C. diff until the patient became septic 36 hours later. The stool had been described as "loose" in the handoff note rather than "watery" or "bloody," which would have triggered the appropriate testing immediately. Check vital signs and calculate a dehydration score. The WHO plan approach uses three categories: no dehydration, some dehydration, and severe dehydration. For pediatric patients, the Modified Oxford Dehydration Score or the WHS (Wellcome Work Group Score) gives you structured criteria. For adults, you can use the Clinical Dehydration Scale or simply rely on orthostatic blood pressure measurements, mucous membrane assessment, skin turgor, and heart rate trends.
Setting Up a Care Plan Of Diarrhoea: The Practical Framework
Write the plan with clear goals, interventions, and measurable outcomes. The plan should have time-bound targets so you know whether it is working or failing. If you write something that cannot be measured, it is not a care plan, it is a wish list. Goal 1: Fluid and Electrolyte Replacement For mild to moderate dehydration, oral rehydration solution (ORS) is first-line. Use WHO-ORs or an equivalent formulation with 2.6g sodium chloride, 2.9g trisodium citrate dihydrate, 1.5g potassium chloride, and 13.5g glucose per liter. The glucose-sodium co-transport mechanism in the small intestine is what makes ORS work. It does not matter what brand you use. It matters that the osmolality and ion concentrations are correct. Standard half-strength sports drinks have far too much sugar and far too little sodium for therapeutic rehydration. Do not substitute them for ORS in moderate-to-severe cases.
Get the Full Details

For moderate dehydration, give 50ml/kg over 2-4 hours for children, or 5% body weight in fluids over 4 hours for adults. That means roughly 3-4 liters for a 70kg adult spread across the initial replacement phase. Then switch to maintenance plus ongoing loss replacement. For severe dehydration, start IV crystalloid. Lactated Ringer's or normal saline, whichever your protocol favors. Bolus 20ml/kg for pediatric patients, 1-2 liters for adults, then reassess. Goal 2: Identify and Treat the Underlying Cause This is where most plans go wrong. Diarrhoea is a symptom, not a diagnosis. A proper care plan includes diagnostic steps, not just symptomatic treatment. Stool culture and sensitivity for bacterial pathogens. C. diff toxin PCR or EIA if the patient has been on antibiotics in the past 90 days. Ova and parasite exam if travel history or epidemiological risk exists. Closer to 10% of hospital-acquired diarrhoea cases are C. diff, and the rate is significantly higher in patients over 65 or those on PPIs.
I had a patient last year who had been treated with ORS and loperamide for what was presumed to be simple viral gastroenteritis. The stool culture finally came back positive for Salmonella enteritidis after five days. The loperamide had masked the diarrhea but prevented pathogen clearance, and the infection seeded into the bloodstream. Never use antimotility agents in suspected invasive bacterial diarrhea or when the patient has fever, bloody stool, or significant leukocytosis. That should be in every plan as a contraindication warning. Goal 3: Symptom Management Zinc supplementation reduces duration and severity in pediatric cases. The WHO recommends 20mg daily for 10-14 days in children over 6 months, 10mg daily in infants under 6 months. This is one of the most evidence-backed interventions in diarrhoeal management and is routinely underutilized in resource-rich settings where clinicians forget it exists.
Probiotics have modest evidence for certain strains. Lactobacillus rhamnosus GG and Saccharomyces boulardii show the best data for reducing duration by approximately 24 hours in acute infectious diarrhoea. They are not cure-alls. They shift the probability distribution slightly. Include them if your patient is immunocompetent. Do not use S. boulardii in immunocompromised patients due to rare but documented cases of fungemia. Bismuth subsalicylate can reduce stool frequency and volume in non-invasive cases. It has antisecretory and mild antimicrobial properties. Watch for drug interactions with warfarin and methotrexate.
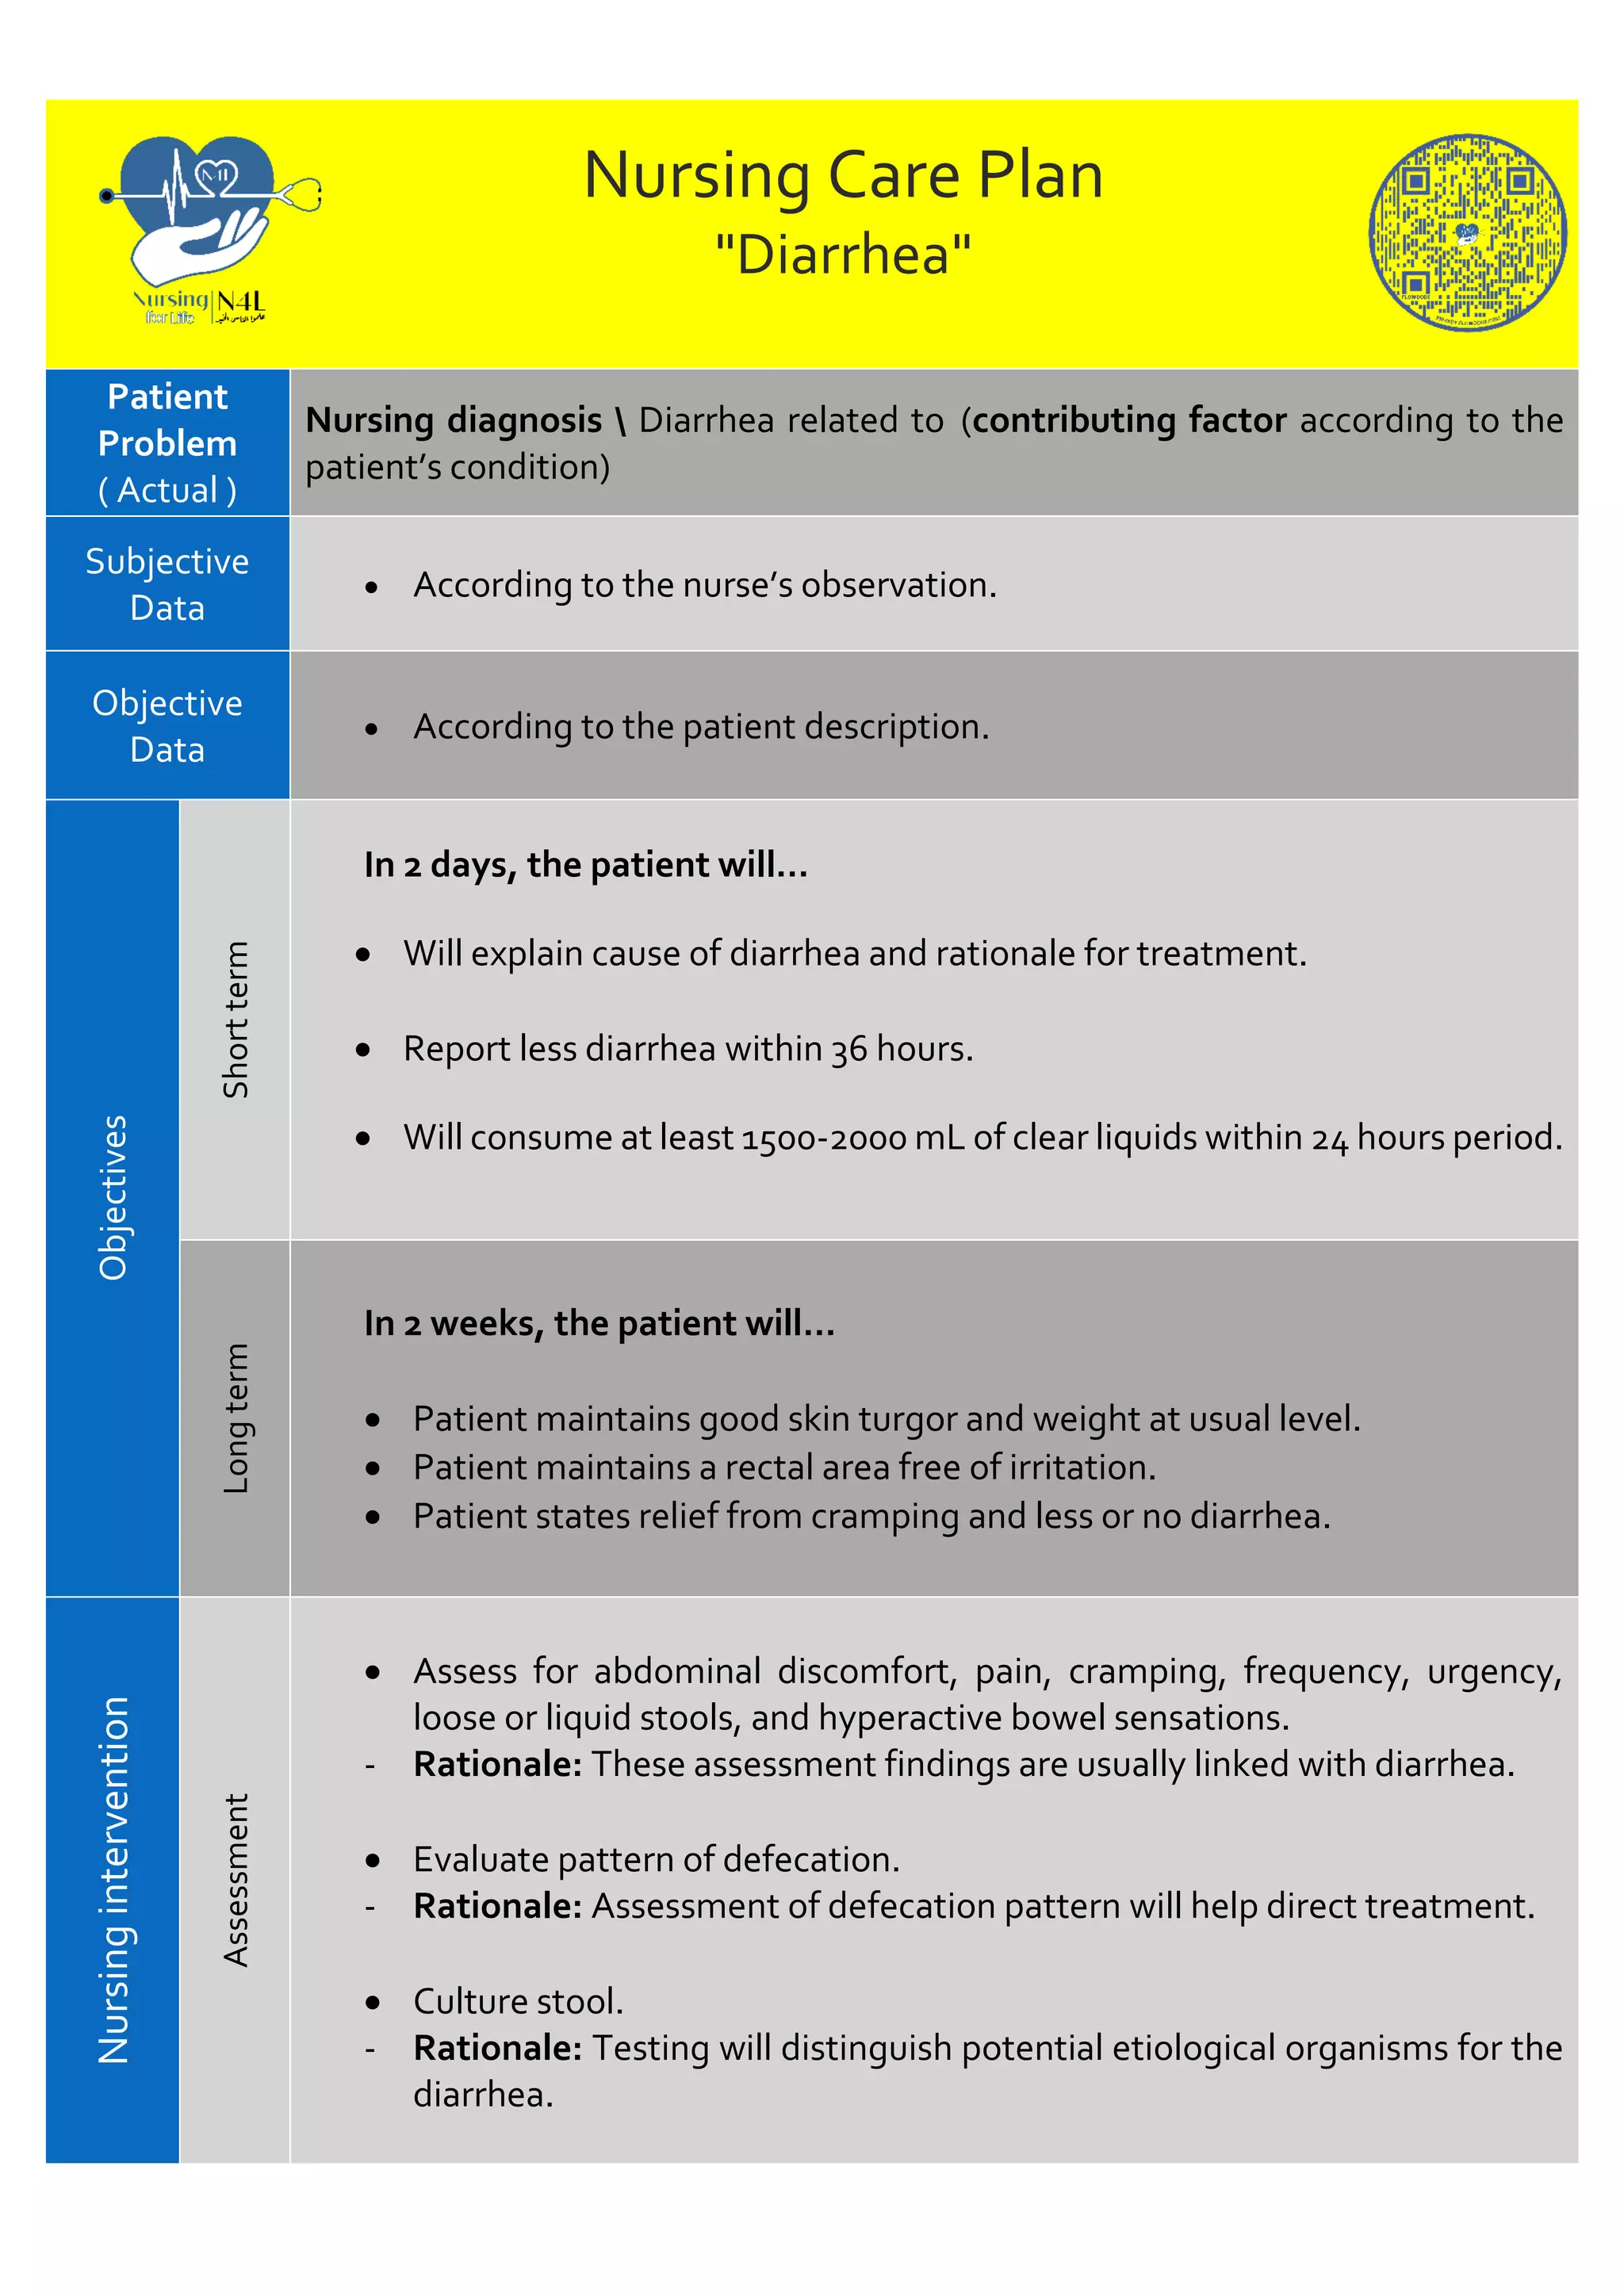
Monitoring and Reassessment Protocol
A Care Plan Of Diarrhoea without built-in reassessment checkpoints is an incomplete plan. Document how often you will reassess and what changes will trigger modification. For inpatients: vital signs every 4 hours, strict intake and output documentation, daily weights when feasible, electrolyte panel at least every 24 hours during active rehydration, and serum bicarbonate to monitor for metabolic acidosis from bicarbonate loss in stool. For outpatient management: the patient should be instructed to return if they develop inability to tolerate oral fluids, persistent vomiting, worsening dehydration signs, blood in stool, fever above 38.5°C lasting more than 48 hours, or no improvement after 72 hours. Most acute infectious diarrhoea resolves within 3-7 days. If it persists beyond that, you need to reconsider the diagnosis, not just escalate symptomatic treatment.
Urine output is the best bedside indicator of adequate resuscitation. Aim for at least 0.5ml/kg/hour in adults and 1ml/kg/hour in children. Specific gravity below 1.020 suggests reasonable hydration status.
Common Pitfalls in Diarrhoea Management
Over-reliance on anti-motility medications. Loperamide and diphenoxylate/atropine make the patient feel better but do nothing for the underlying pathology and can prolong infection in certain cases. I see them overprescribed constantly. Inadequate electrolyte monitoring. Replacing volume without checking potassium and magnesium is asking for arrhythmias. Diarrhoea causes significant potassium and magnesium wasting through the gastrointestinal tract. Hypokalemia can present as ileus, which then worsens the clinical picture by causing abdominal distension and further discomfort. Failure to isolate. If the aetiology is unknown in a healthcare setting, contact precautions should be assumed until proven otherwise. Norovirus, C. diff, and Shigella are all highly contagious. A single case in a long-term care facility can spark an outbreak that keeps staff short for weeks.
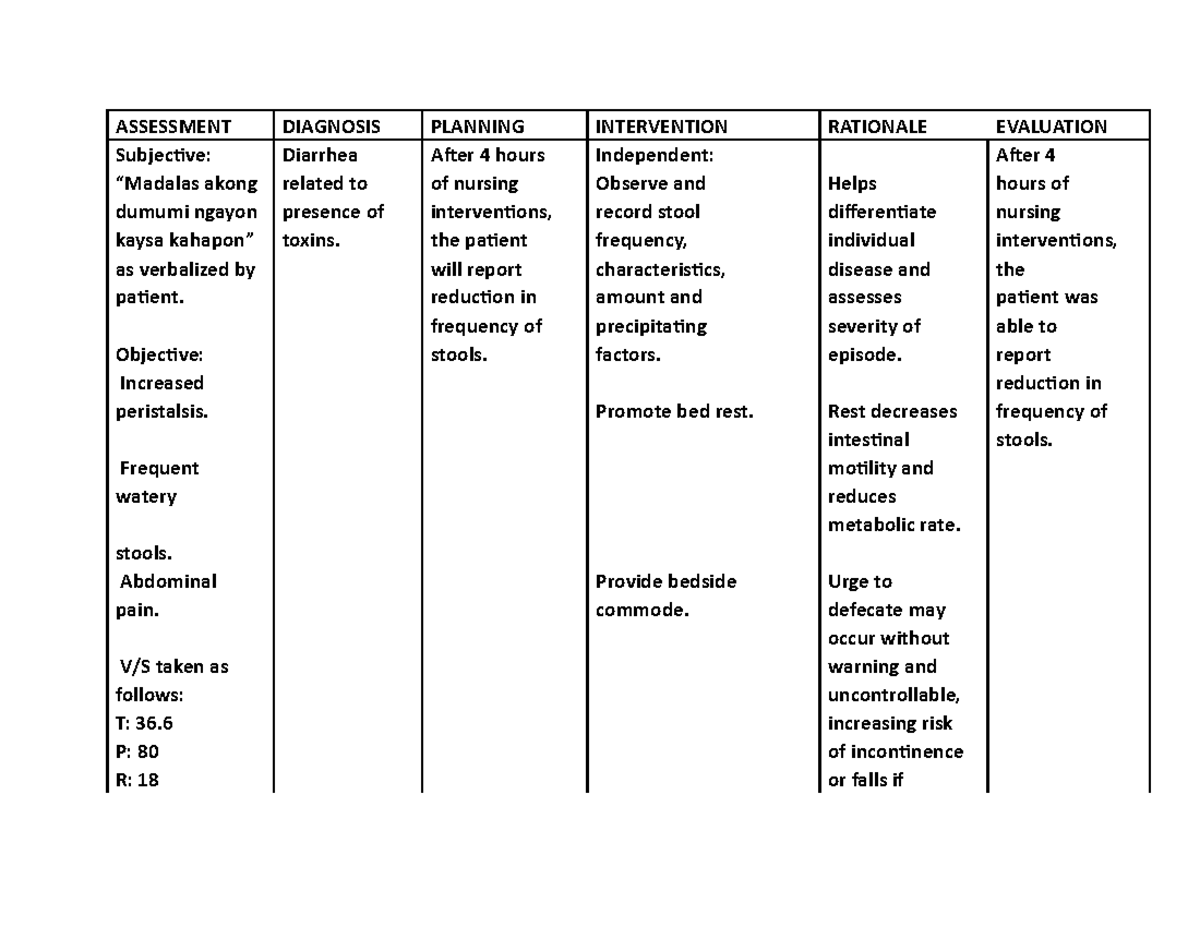
Ignoring nutritional needs. The old advice to "rest the bowel" with NPO status is outdated for most cases. Early refeeding with age-appropriate diets, including complex carbohydrates, lean meats, yogurt, and fruits and vegetables, shortens recovery compared to prolonged fasting. Breastfeeding should continue in infants. For adults, the BRAT diet alone is inadequate nutritionally and provides insufficient protein and calories for recovery.
When Standard Protocols Fail
Sometimes the standard approach does not work, and your care plan needs to account for that scenario upfront. If a patient remains dehydrated despite adequate oral rehydration attempts, consider feeding intolerance, malabsorption syndromes, or an alternative diagnosis entirely. Short bowel syndrome, chronic pancreatitis, celiac disease, and microscopic colitis can all present with persistent diarrhoea that responds poorly to standard supportive care. I once managed a patient whose diarrhoea persisted despite three rounds of appropriate antimicrobial therapy and aggressive rehydration. The turning point came when I stopped looking at the stool and started looking at the medication list. The patient had been on metformin for diabetes management, which causes secretory diarrhoea in roughly 10-15% of users. The diarrhoea predated the "infection" but was attributed to it because the timing coincided with a suspected foodborne illness outbreak at their assisted living facility. Stopping metformin resolved the diarrhoea within 48 hours. Medication review should be a standard step in every diarrhoea care plan, not an afterthought. Ongoing fluid replacement calculations need to be adjusted based on actual stool output, not just theoretical estimates. Weigh diapers in infants for precise measurement. Use calibrated collection bags or containers for adults when output is high. Guessing at output volume introduces significant error into fluid balance calculations.
The plan should also specify what happens if the patient improves. Step-down criteria from IV to oral fluids, from frequent monitoring to routine nursing assessments, and from active treatment to observation-only. A discharge plan is part of the care plan. Write it. Include dietary recommendations, warning signs for return, follow-up timing, and medication instructions with specific dosing schedules.
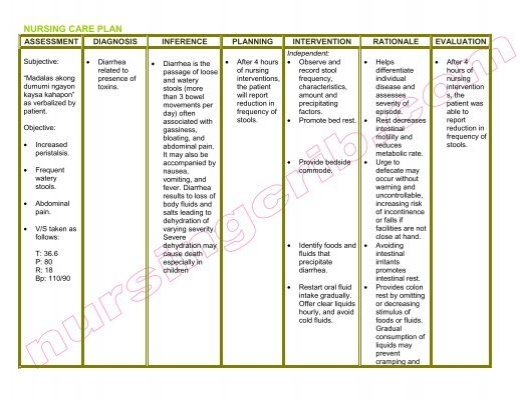
Special Populations
Pediatric patients dehydrate faster than adults due to higher metabolic rate, greater body surface area to mass ratio, and less efficient renal concentrating ability. An infant can go from mild to severe dehydration in hours. Their plans need tighter monitoring intervals and lower thresholds for IV intervention. Elderly patients often present atypically. Fever may be absent. Mental status changes can be the primary complaint. Comorbidities and polypharmacy complicate fluid management. Cardiac patients may not tolerate aggressive fluid resuscitation. Renal patients may not handle potassium replacement safely. Each plan needs individualization based on comorbid conditions. Pregnant patients require attention to uteroplacental perfusion. Dehydration can trigger contractions. ORS is safe. IV fluids may be necessary. Avoid tetracyclines and fluoroquinolones for infectious causes. Ceftriaxone is generally considered safe in pregnancy for severe bacterial infections.
Immunocompromised patients, particularly those with HIV, transplant recipients, and chemotherapy patients, need broader diagnostic workup and lower thresholds for hospitalization. Opportunistic pathogens like Cryptosporidium, Cyclospora, and CMV colitis present with diarrhoea that standard protocols do not address.
Documentation Standards
Your Care Plan Of Diarrhoea documentation should include the assessment findings that justified each intervention, the rationale for treatment selection, the monitoring schedule, expected outcomes with timeframes, and contingency plans for treatment failure. This is both a clinical tool and a legal document. Write it as if both purposes matter equally. Include the date and time of plan initiation, the anticipated duration, and the responsible clinician. Update the plan each time it is modified. Changes made without documentation create liability and clinical gaps. The most effective care plans are the ones that get used. If the plan is so long or so complex that no one reads it, it serves no purpose. Clarity and brevity matter more than comprehensiveness that no one consults. Structure the plan so the next clinician on shift can read it in under two minutes and know exactly what is happening and what to do next.

