How to actually do a SWOT for a care operation
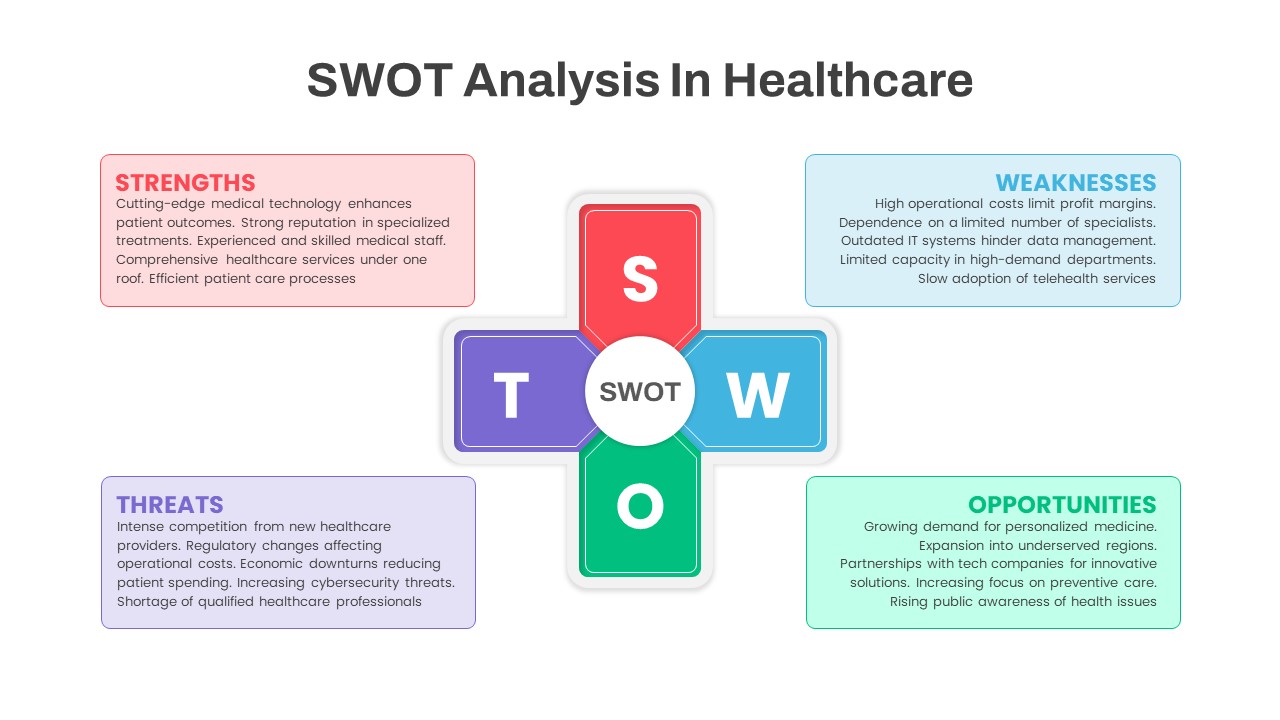
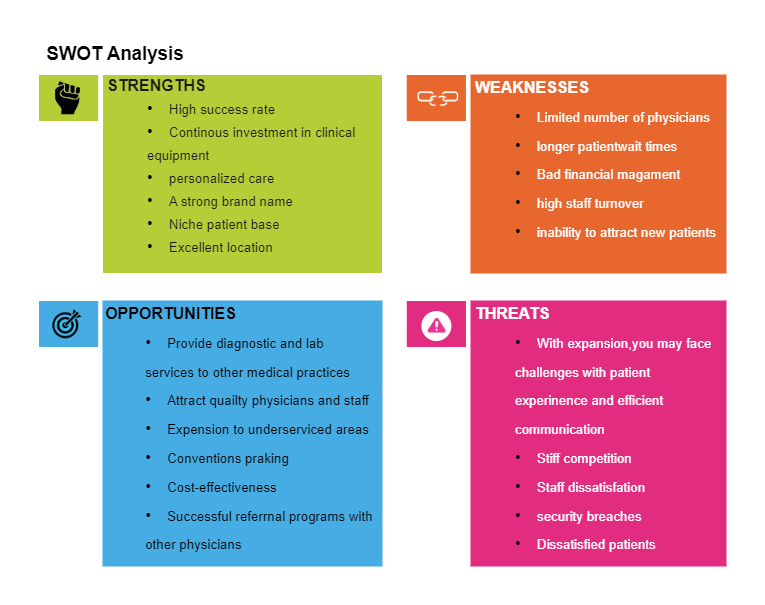
A SWOT is just a way of organizing what you know about your position before you start making decisions. For care providers — whether you run a home care agency, an adult day program, a pediatric therapy clinic, or a residential facility — the matrix itself isn't different from anything else. What makes it painful is that the data is messy, the stakeholders disagree, and the "threats" are often things you can't control. I've run probably two dozen of these across different types of care operations, and the ones that work are the ones where someone forces the team to pick a real decision at the end instead of walking away with four lists that nobody reads again. The quick definition: you list internal Strengths and Weaknesses, then external Opportunities and Threats. That's it. In practice, a good one for a care business looks something like this in the first draft: Strengths: licensed and experienced direct care staff, established referral relationships with local hospitals, Electronic Visit Verification (EVV) compliance already sorted, low turnover in key positions, strong online reviews, proprietary training program for aides.
Weaknesses: heavy reliance on two referral sources, limited marketing budget, scheduling software is outdated, insurance credentialing takes 90 days per new clinician, no succession plan for the director of nursing. Opportunities: aging-in-place demand growing in your county, new Medicaid waiver opening up next quarter, telehealth reimbursement now permanent for certain evaluations, local hospital launching a post-acute transition program, grant funding available for rural care expansion. Threats: state-level staffing ratio requirements tightening, competitive agency backed by a national chain opening nearby, rising wage floor pushing your margins thin, changes to EVV enforcement penalties, payer mix shifting toward lower-reimbursement Medicaid.
That last row is where people usually get stuck. Threats in care are rarely clean. A regulatory change might actually be an opportunity if you're already compliant while your competitors aren't. I learned that the hard way in 2023 when our state quietly updated its EVV exception policy for rural providers. Everyone in our region treated it as a threat because it added reporting burden. I cross-referenced it with the enforcement timeline and realized the new exceptions were only enforceable if you had fewer than five active cases in a zip code. We had twelve. The reporting requirement never applied to us. What looked like a threat was actually a competitive moat. That insight came from reading the actual regulatory text, not from a consultant's summary. Most people don't do that. They grab the executive brief and run with it. Here's the process I actually use, not the textbook version. Start with the decision. A SWOT without a question attached is just a exercise in group therapy. Are you deciding whether to take on a new payer contract? Whether to expand to a new service line? Whether to close a location? Write that down first. It determines what goes in the grid and what stays out. I've seen people spend three hours listing "strengths" like "we have a nice waiting room" when the actual question was "should we hire a second clinical director?" Nice waiting rooms are irrelevant to that. The discipline of filtering entries through the decision question is what separates a useful SWOT from a wall of noise.
Get the Full Details

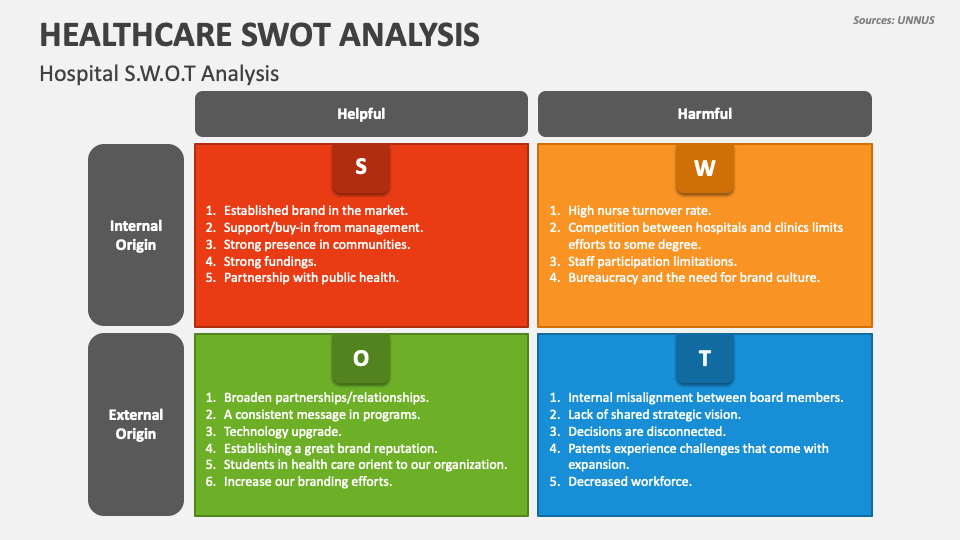
Then gather data before you bring anyone into the room. Pull your actual numbers: staff turnover rate by department, referral source breakdown, payer mix percentages, average days to credential, occupancy or utilization rates if you're residential. Write them down. When you enter the session with real data instead of opinions, people argue less and the resulting SWOT is closer to accurate. The session itself should take about 45 minutes max. Longer than that and you're just repeating yourselves. Fill the quadrants separately. Don't let the group mix internal and external. I've watched teams put "competitor lowered their rates" in weaknesses, which makes no sense — that's a threat. Or they wrote "our staff is well-trained" under opportunities. It's a strength. Keep the categories clean. That discipline matters more than people realize because it forces you to think about control. Things you can control go on the left side. Things you can't go on the right. If something sits in the middle, you're not being honest about it yet. After the grid is filled, do the cross-references. This is the part most people skip and the part that actually creates value. Match each strength against each opportunity — that's your SO strategy. How do you use what you're good at to capture what's available? Then match weaknesses against opportunities — WO strategies. How do you fix enough of yourself to take advantage of what's happening? Then strengths against threats — ST. How do you use your advantages to defend against real risks? Finally, weaknesses against threats — WT. This is the defensive strategy. It tells you where you're most exposed and what you should stop doing or exit from entirely.
For example, if your strength is a fast credentialing pipeline and your threat is a competitor trying to poach your referral sources, your ST move might be to lock in long-term contracts with those referrers while your speed gives you a window they can't match. If your weakness is high turnover and your threat is a new staffing mandate, your WT flag is real. You need to address turnover before the mandate hits or you'll be non-compliant. That's not dramatic. It's just math. There are real limitations to this method and I should be blunt about them. A SWOT assumes you can see your environment clearly enough to categorize it. In care, that's often false. Regulatory shifts happen fast. Payer policies change with six months notice. A SWOT completed in January might be wrong by April if your state restructures its waivers. Treat every Care SWOT Analysis as a snapshot, not a monument. Revisit it quarterly at minimum, or whenever a material external change happens — new regulation, a major payer contracting shift, a key referral source changing their policies. Another limitation: SWOT doesn't rank anything. It lists. Two strengths and three weaknesses look equally important on paper until you force a priority order. After you build the grid, go back and number each item by impact and likelihood. Not a gut feeling — estimate it. If you're a small home care agency and your biggest strength is "good relationships with discharge planners," rate that high on impact but medium on durability because those relationships are person-dependent, not system-dependent. If the planner retires, the strength vanishes. That's a nuance a plain SWOT won't show you, but it should be part of your analysis.
Also, be careful about the weakness column. Teams have a tendency to list genuine operational problems there and then do nothing about them because "we already listed it." Writing a weakness down is not fixing it. If something is a weakness and it matters for your decision, it needs an owner and a timeline. Not always, but if it shows up in a SWOT tied to an actual strategic question, it earns the follow-up. The format I use is simple. Spreadsheet with four columns. Name, description, evidence, and relevance to the decision question. The evidence column is what separates a responsible analysis from a brainstorming session. Every entry should have a source. "Low staff turnover" needs a number. "Strong hospital relationships" needs names or a referral count. When you write it that way, people can't hide behind vague confidence. If you need a template, I use a basic four-quadrant layout with the decision question at the top and the cross-reference matrix below it. There are free versions of this online from health administration programs and nonprofit consultancies. Search for "SWOT template healthcare" or "SWOT template home care" and you'll find something usable within a minute. The template itself is trivial. The value is in the discipline of filling it out correctly.
One last thing that trips people up: the difference between a strength and a competitive advantage. Having licensed staff is a strength. Having licensed staff who are also bilingual and can handle complex wound care while another agency in your market can't is an advantage. Write the advantage in stronger language. It matters when you're deciding whether to compete on price or on capability. Most care operators understate their advantages because they're too close to the work to see what's distinctive. An outside person looking at the same SWOT will usually spot things the internal team misses. Consider bringing someone in for the review phase even if you built the grid yourself.